For over a decade, the medical community has possessed the tools to effectively eliminate the Hepatitis C virus (HCV), a pathogen that once required arduous, often ineffective interferon-based regimens. Today, oral direct-acting antivirals (DAAs) offer cure rates exceeding 95%. Yet, despite these medical marvels, the incidence of HCV is climbing. In the United States alone, an estimated 69,000 new infections were recorded in 2023—nearly double the rate observed in the mid-2010s.
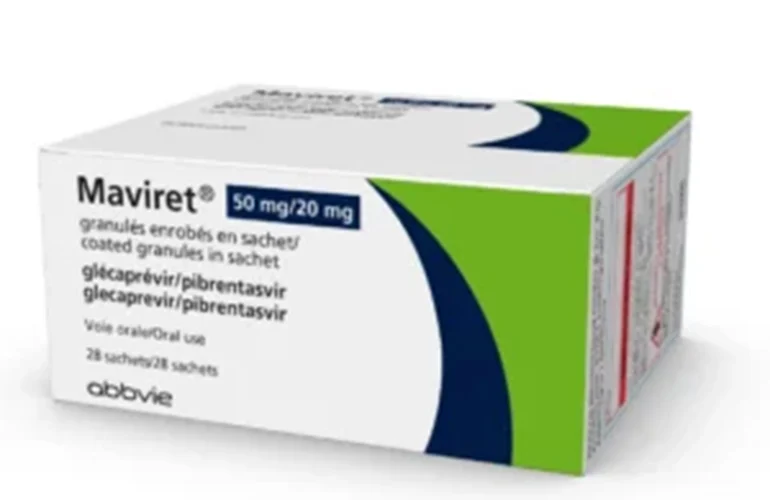
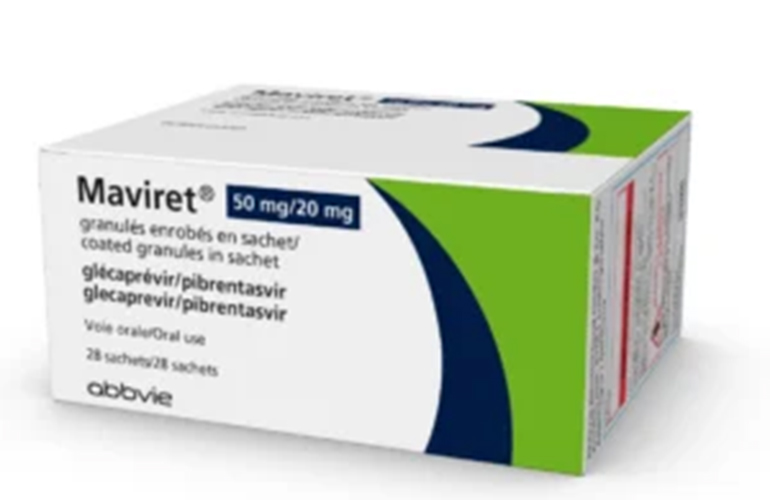
The recent regulatory approval for the use of AbbVie’s Mavyret (glecaprevir/pibrentasvir) to treat acute HCV infections represents a significant shift in clinical strategy. While the drug’s performance in controlled clinical trials is nothing short of exemplary, the transition from clinical efficacy to "real-world" effectiveness remains a formidable hurdle.
The Evolution of HCV Therapeutics: A Chronology
The trajectory of HCV treatment is a story of rapid innovation pitted against systemic logistical failure.
- 1991: The FDA approves the first treatment for HCV: alpha-interferon injections. The therapy was grueling for patients, accompanied by severe side effects and a meager 10% viral eradication rate.
- 2017: A landmark year for hepatology. The European Union and the U.S. FDA approve Mavyret for the treatment of chronic HCV across all major genotypes (1–6). Its rapid, eight-week course transformed the standard of care.
- June 2025: The FDA grants a critical label expansion for Mavyret, authorizing it as the first and only treatment specifically indicated for acute HCV infection in the United States.
- June 2026: Following the U.S. precedent, the European Commission grants similar approval, allowing clinicians across the EU to treat acute infections without waiting for the virus to transition into a chronic state.
This move toward early intervention is a direct response to the limitations of previous clinical protocols, which often forced physicians to wait for evidence of chronicity before authorizing treatment—a process that frequently resulted in patient disengagement and further viral transmission.
Supporting Data: Efficacy vs. Reality
The efficacy of the glecaprevir/pibrentasvir combination is supported by robust Phase 3 clinical data. In trials evaluating the drug for acute infection, participants achieved a sustained virologic response (SVR) of 96.2% at the 12-week mark. Even more impressive, the modified intention-to-treat population saw a 100% cure rate, with zero documented on-treatment virologic failures or post-treatment relapses.
The Reinfection Paradox
A unique challenge explored in the Phase 3 trials was the phenomenon of repeat infection. Approximately 18% of trial participants were being treated for at least their second HCV infection, with nearly 40% of that subset having contracted the virus three or more times.
Crucially, the clinical data suggests that prior exposure to the virus—or even prior treatment with Mavyret—does not diminish the drug’s effectiveness. "The study found that a history of prior HCV infection did not appear to affect the SVR," noted Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and co-author of the study. "These findings suggest that neither prior infection nor previous exposure to the same regimen compromised the virologic response."
However, while the drug works, the biology of the virus is only half the battle. Studies indicate that while the general population experiences a reinfection rate of approximately 1.27 per 100 person-years, that rate spikes to 5.9 per 100 person-years among populations with recent drug use. This discrepancy highlights that while the pharmaceutical solution is "cured," the social and behavioral environment remains unchanged.
Official Responses and Clinical Perspectives
The medical community has largely lauded the label expansion as a victory for public health, yet experts emphasize that a pill alone cannot solve the epidemic.
John Ward, director of the Coalition for Global Hepatitis Elimination, stressed the importance of aggressive, early intervention. "If treated early with safe and effective therapies, providers can cure virtually all patients with hepatitis C before it escalates to chronic disease," Ward stated in an AbbVie press release.
Dr. Gentile echoes this sentiment but warns of the "administrative inertia" that has historically plagued HCV care. "Before the acute indication, patients could be required to wait for confirmation of chronicity," Gentile explained. "That delay can add unnecessary visits, create administrative barriers, and, most importantly, increase the risk that patients disengage from care."
By removing the requirement to wait for chronic progression, the new label provides a "valuable tool" for clinicians to act before patients disappear from the medical system.
The "Real World" Implementation Gap
Despite the clinical success, the transition to real-world application faces significant structural challenges. The trial populations that provided the evidence for Mavyret’s approval were, by design, connected to the healthcare system.
Limitations of Current Clinical Trials
The Phase 3 trial for acute HCV had specific demographic characteristics that may not reflect the most vulnerable segments of the population. For instance, nearly 50% of participants were living with HIV and were already receiving antiretroviral therapy, ensuring they were stable, monitored, and compliant with medical instructions. Only 14.3% of participants were classified as individuals who currently or recently injected drugs.
This selection bias creates a "best-case scenario" in the data. In the real world, the patients who are most at risk—those who are homeless, struggling with substance use disorders, or lacking stable insurance—are the least likely to remain in a clinical trial or complete a full course of treatment.
The Need for Integrated Care
Dr. Gentile argues that treating the virus is insufficient without addressing the underlying social determinants of health. "Antiviral treatment does not modify the underlying exposure," he noted.
To achieve true elimination, clinical intervention must be embedded within a broader public health framework:
- Harm Reduction: Access to sterile injecting equipment and safe consumption sites.
- Wraparound Services: Treatment for substance-use disorders and sexual health counseling.
- Surveillance: Regular HCV RNA testing and, crucially, rapid retreatment protocols for those who are reinfected.
The consensus among infectious disease experts is that reinfection should not be treated as a clinical failure or a reason to withhold care. Instead, it must be viewed as a signal that the patient requires more intensive support, not less.
Implications for Future Public Health Policy
The path forward requires a shift in how healthcare systems define "success." For a pharmaceutical company, success is a 96% SVR in a clinical trial. For a public health department, success is the total eradication of the virus in a community.
To bridge this gap, future clinical studies must move beyond simply measuring SVR. As Dr. Gentile suggests, researchers should focus on tracking metrics that quantify real-world access:
- Time-to-treatment: Measuring the duration from diagnosis to the first dose.
- Retention: Tracking the percentage of diagnosed patients who complete the full course.
- Loss-to-follow-up: Identifying where in the chain of care the system fails.
- Retreatment efficacy: Documenting success rates specifically for those returning after a reinfection.
The approval of Mavyret for acute HCV is a milestone in drug development, moving us closer to the goal of global HCV elimination. Yet, it serves as a stark reminder that even the most effective cure is only as powerful as the infrastructure that delivers it. As we look toward the future, the challenge will be to ensure that these cutting-edge therapies reach not just the patients who are easy to track, but the populations who have historically been left behind by the medical establishment.
The science has provided the solution; the burden of success now rests on our ability to integrate that science into the lives of the most vulnerable. Only by treating the patient, rather than just the pathogen, can we hope to stem the tide of rising HCV infections and finally close the chapter on this public health crisis.
About the Author