
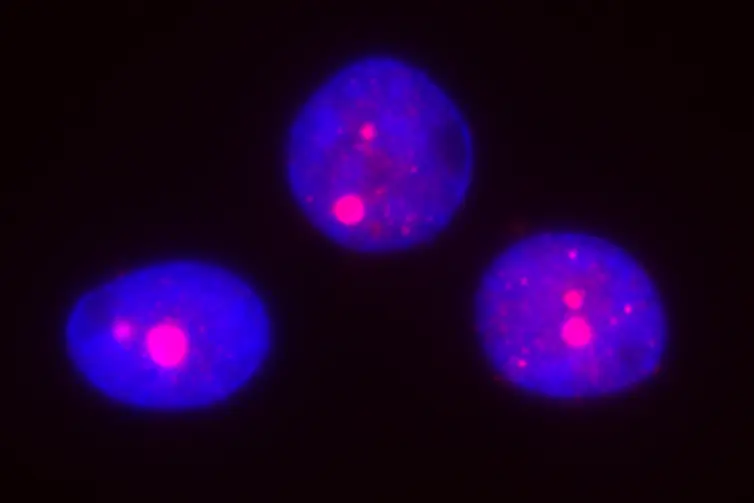
In a significant leap forward for neurodegenerative medicine, a collaborative research team from the Broad Institute of MIT and Harvard, Harvard Medical School, and McLean Hospital has identified a unifying mechanism behind the devastation caused by Huntington’s disease. Their latest findings, published in the journal Cell, confirm that the progressive expansion of DNA repeats—previously thought to be isolated to the striatum—is a widespread culprit across the brain, including the neocortex. This discovery provides a long-sought roadmap for the development of systemic therapies that could halt the disease’s progression across multiple neurological fronts.
The Core Mechanism: A Ticking Genetic Time Bomb
Huntington’s disease (HD) is a devastating, fatal neurodegenerative condition characterized by motor dysfunction, cognitive decline, and psychiatric disturbances. For decades, the medical community has understood the fundamental genetic cause: an inherited mutation in the Huntingtin (HTT) gene. Specifically, individuals with 40 or more repeats of the three-letter DNA sequence "CAG" are at high risk of developing the disease.
However, the "why" and "how" remained elusive. It was not simply the presence of the mutation that caused cell death; rather, it was a dynamic process. In 2025, researchers revealed that these CAG repeats do not remain static. Instead, they slowly expand throughout an individual’s lifetime. The disease reaches a critical inflection point only after these repeats enlarge to approximately 150 or more, at which point the genetic material becomes toxic to the cell.
While this discovery was a watershed moment, it was limited in scope. Initially, the mechanism was observed exclusively in the striatum—the region of the brain that governs movement and is typically the first to show symptoms in HD patients. Scientists were left wondering if this "repeat expansion" was a universal mechanism of the disease or a localized phenomenon specific to the striatum.
Chronology of a Scientific Breakthrough
The journey to this discovery represents a multi-year effort to map the molecular trajectory of Huntington’s disease.
- The 2025 Foundation: Scientists at the Broad Institute established that the HTT gene exhibits "somatic expansion" in the striatum. They demonstrated that toxic effects correlate with reaching a threshold of 150 repeats.
- Expansion of Scope: Building on this, the research team—led by geneticist Steve McCarroll and psychiatrist Sabina Berretta—sought to determine if the same pathology occurred in the neocortex, a region associated with higher-order cognitive functions and emotional regulation.
- The 2026 Analysis: Utilizing advanced single-cell sequencing, the team examined over 125,000 cells derived from neocortex samples provided by eleven deceased patients who had suffered from Huntington’s.
- The "Cell" Publication: The peer-reviewed findings, published in Cell, confirmed that the neocortex follows the same biological "clock" as the striatum. Cells in the cortex also began showing signs of toxicity only after surpassing the 150-repeat threshold.
Supporting Data: Why the Brain Withers Differently
One of the most compelling aspects of the new study is the explanation it offers for why Huntington’s disease manifests differently in various patients and different regions of the brain.
The Speed of Expansion
The research team discovered that while both the striatum and the neocortex are susceptible to HTT repeat expansion, they operate at vastly different speeds. The neocortex takes significantly longer to reach the toxic 150-repeat threshold. In many cases, the process is so slow that a vast majority of cortical cells never reach the critical limit before the patient succumbs to the disease. This variability in the "speed of the clock" explains why certain brain regions are affected earlier or more severely than others, providing a nuanced view of the disease’s progression.
The Mystery of Nuclear Inclusions
For years, neuropathologists have debated the role of "nuclear inclusions"—clumps of mutant Huntingtin protein found within the nuclei of brain cells. Some theories posited that these inclusions were a protective mechanism to sequester toxic proteins, while others argued they were the primary drivers of cell death.
The data from the Broad Institute team offers a definitive new interpretation. By analyzing cell samples, researchers found that nuclear inclusions appear only in cells that have already accumulated well over 150 repeats and are in a state of terminal dysfunction. These inclusions, therefore, are not protective; they are a "red flag" or a biological warning sign that the cell is in its final stages of life. The gene expression patterns within these inclusion-carrying cells were found to be profoundly abnormal, confirming that these neurons are undergoing severe molecular collapse.
Official Responses and Expert Perspectives
The findings have been met with enthusiasm by the neuroscience community, as they simplify the target for pharmaceutical intervention.
"These new results suggest that such medicines, if and when they’re successfully developed, might be able to address not just one of the pathologies in the disease, but the two big ones," said Steve McCarroll, co-senior author of the study. McCarroll, who serves as an institute member at the Broad and a professor at Harvard Medical School, emphasized that the discovery validates the current pivot in drug development toward targeting the repeat expansion process itself.
Seva Kashin, a scientist in the McCarroll lab and co-first author, noted the intellectual satisfaction of the discovery: "It’s satisfying that a single mechanism could be at play in multiple brain areas, explaining pathologies that had once appeared to be so different."
Dr. Sabina Berretta, associate professor of psychiatry at Harvard Medical School and director of the Harvard Brain Tissue Resource Center, underscored the urgency of the work. "By pointing to a shared disease mechanism across brain regions, our findings suggest these new efforts are on the right track. We hope this evidence adds urgency to developing such treatments."
Dr. Berretta also took a moment to acknowledge the human element of the research: "Above all, this work is a testament to the extraordinary generosity, commitment, and foresight of brain donors and their families, whose contributions made these discoveries possible and to whom we are deeply grateful."
Implications for Future Medicine
The implications for the future of Huntington’s disease treatment are profound. By confirming that the 150-repeat threshold is a universal mechanism of toxicity across different types of brain cells, researchers can now shift their focus from developing region-specific treatments to systemic interventions.
A Unified Therapeutic Target
If pharmaceutical companies can develop a therapy that prevents or slows the expansion of HTT repeats, they may be able to "reset the clock" in both the striatum and the neocortex. Such a drug would not merely manage symptoms—it would address the root cause of cellular toxicity. This could potentially delay the onset of the disease by years or even decades, or halt its progression entirely if caught early enough.
Beyond Motor Symptoms
Previous attempts at treating Huntington’s have often struggled to address the cognitive and psychiatric symptoms that arise from cortical damage. Because this new research confirms that the neocortex suffers from the same repeat-expansion pathology as the motor-controlling striatum, it provides a scientific rationale for therapies that can protect the brain’s higher-order functions.
A New Diagnostic Window
The identification of nuclear inclusions as a sign of late-stage dysfunction could also change how researchers monitor disease progression in clinical trials. By identifying these markers, scientists may gain a clearer picture of how effective a candidate drug is at preventing cells from reaching that point of "no return."
Conclusion: A Path Toward Hope
The battle against Huntington’s disease has long been defined by its complexity and the daunting nature of its neurodegenerative toll. However, the findings from the Broad Institute and its partners provide a beacon of clarity. By identifying a shared, predictable, and measurable mechanism—the expansion of HTT repeats to a 150-unit threshold—scientists have turned a chaotic disease process into a clear biological target.
As the scientific community moves forward, the focus will undoubtedly be on small molecules or gene-editing technologies capable of slowing this expansion. While there is still much work to be done in translating these laboratory findings into clinical realities, the path is now clearer than it has ever been. For the families living in the shadow of Huntington’s, this research offers more than just academic progress; it offers the tangible, scientific promise of a future where this fatal diagnosis may one day be transformed into a manageable condition.
About the Author




