The pharmaceutical industry stands at a critical juncture. As clinical trial protocols grow exponentially in complexity—now capturing millions of data points where they once captured thousands—the human capacity to synthesize, monitor, and act upon this information is reaching a breaking point. A landmark analysis by the Tufts Center for the Study of Drug Development (CSDD) and clinical trial technology leader Medable suggests that the solution to this "data-wrangling" crisis may finally be here: agentic AI.
The study, which quantifies the financial impact of Medable’s Clinical Monitoring Agent, reveals staggering potential for efficiency. According to the analysis, deploying these AI agents could generate an 82x return on investment (ROI) for Phase 3 oncology trials and a 64x return for Phase 2. In terms of net present value (eNPV), this translates to approximately $21 million in added value for a single Phase 3 trial and $7.5 million for Phase 2.
The Convergence of Agency and Necessity
The rise of "agentic" workflows—AI systems capable of performing discrete tasks, reasoning through workflows, and executing actions—is reshaping the enterprise landscape. While sectors ranging from software engineering to finance have embraced AI to handle routine business tasks, the life sciences industry has historically been more cautious, hampered by regulatory strictures and the mission-critical nature of patient safety.
However, the tide is turning. McKinsey’s 2025 research indicates that despite budget overruns, the adoption of agents is seen as a strategic imperative, with software developers reporting that agents save them hours of manual labor daily. In the context of drug development, where the cost of failure is measured in years and hundreds of millions of dollars, the "agentic" promise is not just about speed—it is about de-risking the pipeline.
A Chronology of Clinical Transformation
To understand the significance of the Tufts-Medable collaboration, one must look at the recent evolution of AI in clinical trials:
- 2024–2025 (The Pilot Phase): Early adopters began testing AI/ML use cases, primarily focusing on patient recruitment and simple monitoring.
- Late 2025 (The Efficiency Realization): IBM and other industry analysts reported that AI was no longer just a theoretical research interest; it was tangibly reducing administrative burdens, with 41% of developers seeing immediate time-saving impacts.
- 2026 (The Quantified Shift): The Tufts CSDD published an analysis of 36 industry-reported AI/ML use cases, documenting an average 18% reduction in trial cycle times.
- Late 2026 (The Financial Validation): The current Medable-Tufts study marks a transition from "efficiency gains" to "financial impact." By moving beyond anecdotal success, the industry now has a framework to justify the capital expenditure required to implement agentic systems at scale.
Supporting Data: The Complexity Crisis
The necessity for these tools is driven by an unprecedented volume of information. A recent joint analysis by Tufts CSDD and TransCelerate, reviewing 105 protocols across 15 major pharmaceutical companies, found that the average Phase 3 clinical trial protocol now collects 5.9 million data points. This is a staggering leap from the 929,000 data points collected in 2012.
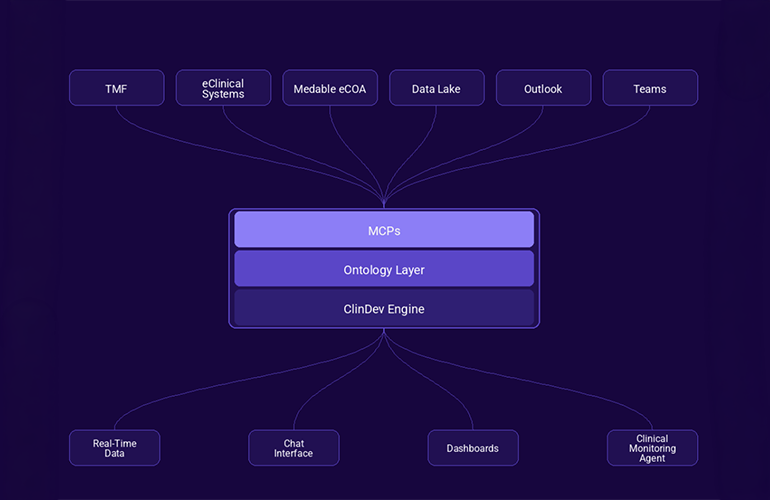
When a Clinical Research Associate (CRA) is tasked with "wrangling" this data, they are forced to synthesize information from Electronic Data Capture (EDC) systems, Clinical Trial Management Systems (CTMS), and Trial Master Files (TMF). The margin for human error in this environment is significant.
The financial stakes are equally daunting. With the failure rate for small-molecule cancer drugs remaining at roughly 95% from Phase 1 through Phase 3, even a marginal improvement in trial execution can lead to massive swings in portfolio value. The Tufts/Medable analysis suggests that for a sponsor with 50 active indications, applying these agentic efficiencies could result in an incremental portfolio eNPV of up to $565 million.
Official Responses: Putting Numbers on Innovation
Ken Getz, executive director of the Tufts CSDD, emphasized that the industry has long suffered from a "quantification gap."
"We’ve known for some time that companies have been piloting AI enablement tools, but what they’ve often been lacking is any kind of quantification of the actual ROI, the value proposition," Getz noted. "We were really interested in doing a study where we could put some hard numbers around a specific AI enablement solution."

Dr. Pamela Tenaerts, Chief Medical Officer at Medable, highlighted that these agents act as a force multiplier for human intelligence rather than a replacement. In a demonstration of the technology, the agent successfully cross-referenced multiple clinical systems to identify a site with unusually low adverse-event reporting. By flagging concomitant medications recorded without corresponding adverse events, the agent alerted the team to a potential data integrity issue—a pattern that would have been invisible to a human auditor reviewing a single system in isolation.
"The agent has the ability to see things slightly earlier than a human would," Dr. Tenaerts explained. "That likely happens faster than a human can make that connection, so the person can intervene on that issue."
Strategic Implications: Redefining the Role of the CRA
The shift toward AI-enabled monitoring forces a re-evaluation of the human role in clinical trials. If an agent can automatically draft queries for missing fields and file them in the TMF, the CRA is liberated from the "data-wrangling" phase of their job.
However, experts caution that this transition is not a "plug-and-play" solution. Medable’s architecture, which integrates with roughly 40 external systems including Oracle Argus, Veeva, and Snowflake, still requires approximately 20% customization to match the unique operational requirements of different sponsors.
Furthermore, as Venu Mallarapu, chief transformation and AI officer at eClinical Solutions, points out, we are currently in the era of "assistive" rather than "fully autonomous" AI. "There’s nobody that is running fully autonomous agents that not only process the data but also make decisions without human involvement," Mallarapu noted.

This sentiment is echoed by Dr. Tenaerts, who emphasizes the "recommend-and-review" paradigm. "The agent doesn’t suspend the CRA from thinking," she said. "The CRA still needs to be there."
Challenges and the Future of Scaling
While the 82x ROI is a compelling headline, the industry must still navigate the "balloon effect"—the risk that by compressing timelines in one area (monitoring), you simply push the bottleneck elsewhere (site operations). If an agent drastically increases the volume of queries sent to a site, the sites themselves may become overwhelmed unless their workflows are similarly digitized.
Looking ahead, the potential for these agents to move beyond oncology is high. While the model has been tested primarily within the context of complex cancer trials, the logic of data synthesis and pattern recognition is universal.
"It makes logical sense that something you do in an oncology program we could probably replicate in other programs," Dr. Tenaerts said.
As clinical trials become increasingly digital, the adoption of agents appears inevitable. By providing a framework for the financial, operational, and clinical benefits of these tools, the Tufts-Medable analysis has provided the "proof of concept" that the industry needed to move from tentative pilots to full-scale enterprise transformation. The question for pharmaceutical executives is no longer whether they can afford to implement agentic AI, but rather, can they afford not to?
About the Author