Four years after the U.S. Supreme Court’s landmark Dobbs v. Jackson Women’s Health Organization decision effectively dismantled federal abortion protections, the landscape of reproductive healthcare in the United States remains profoundly fractured. While 13 states have enacted total bans on abortion, the crisis of access extends far beyond those jurisdictions. In states where abortion remains legal, a quiet, persistent barrier is undermining the stability of reproductive health services: the systemic inadequacy of Medicaid reimbursement rates.
A new, comprehensive analysis by KFF researchers illuminates how the structure and valuation of Medicaid payments for abortion services create a precarious environment for both providers and patients. By reviewing physician fee schedules across states that permit abortion, the data reveals a stark reality: even where legal, abortion care is increasingly threatened by financial policies that fail to keep pace with the realities of clinical practice.
Main Facts: The Intersection of Policy and Payment
The federal Hyde Amendment remains a foundational constraint on reproductive healthcare in the United States. Since its inception, the amendment has prohibited the use of federal Medicaid funds for abortion, except in the narrowest circumstances: pregnancies that endanger the life of the pregnant person, or those resulting from rape or incest.
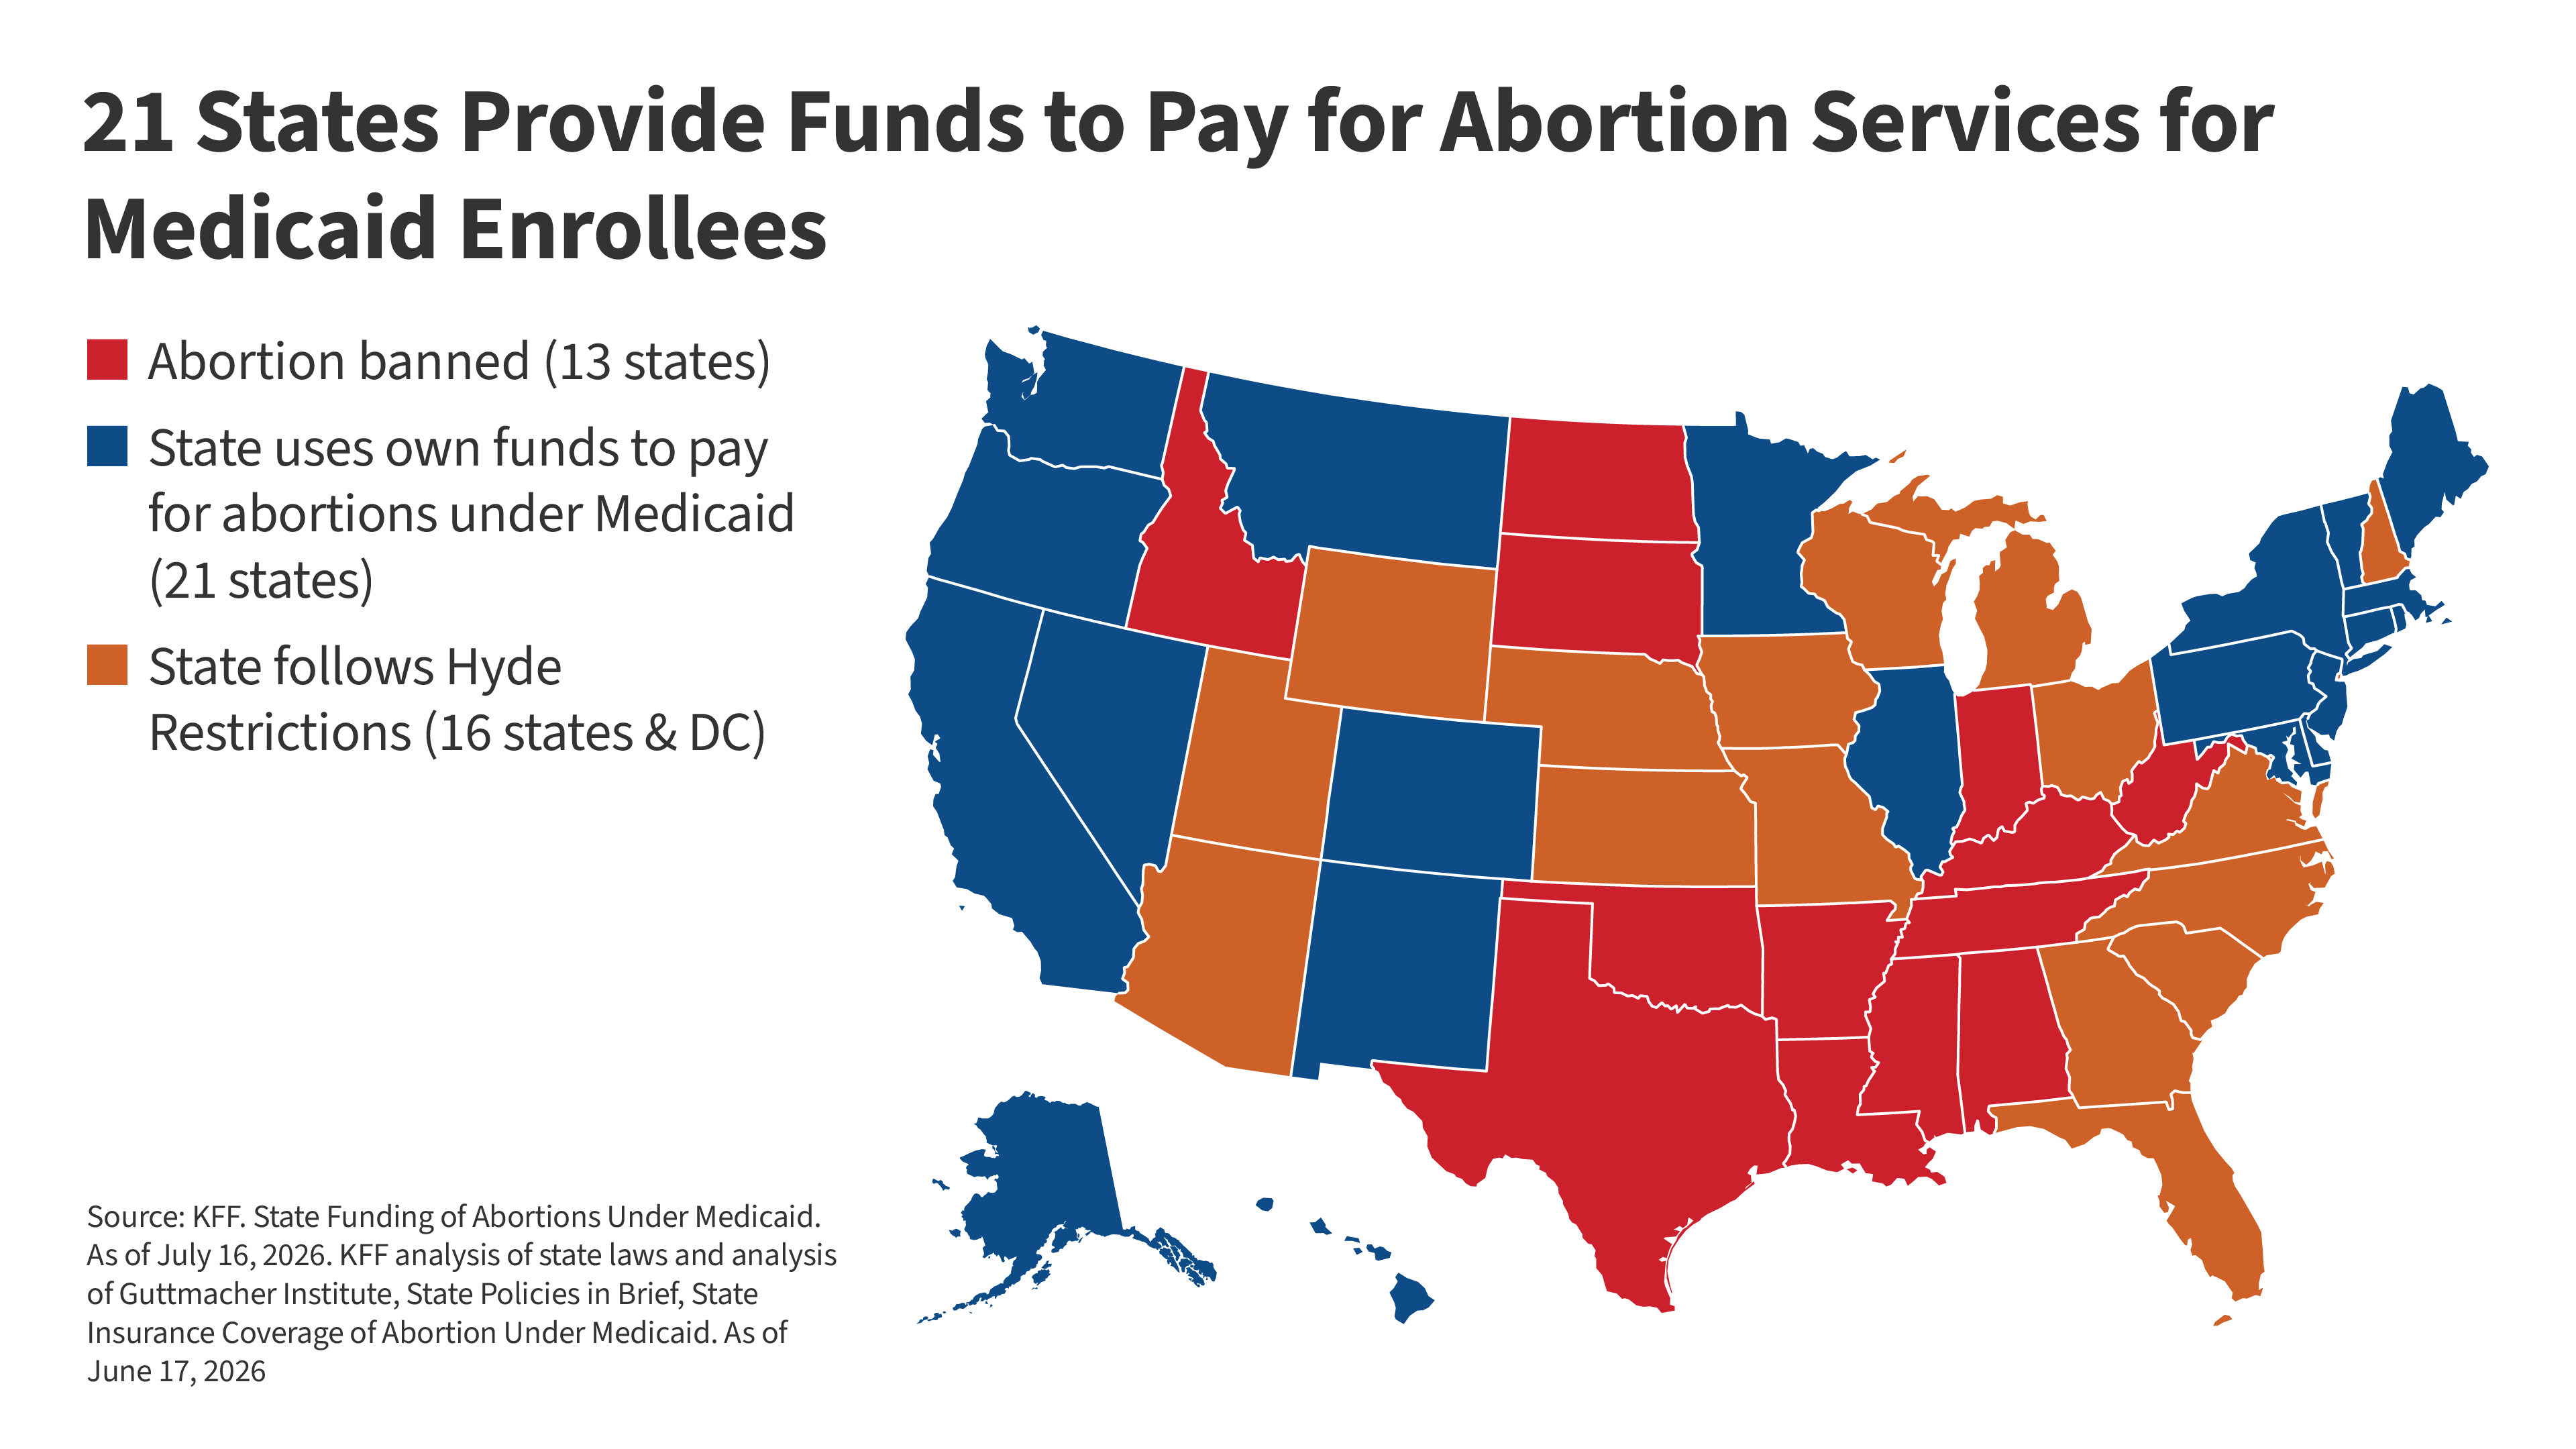
Currently, the national landscape is divided into three distinct tiers:
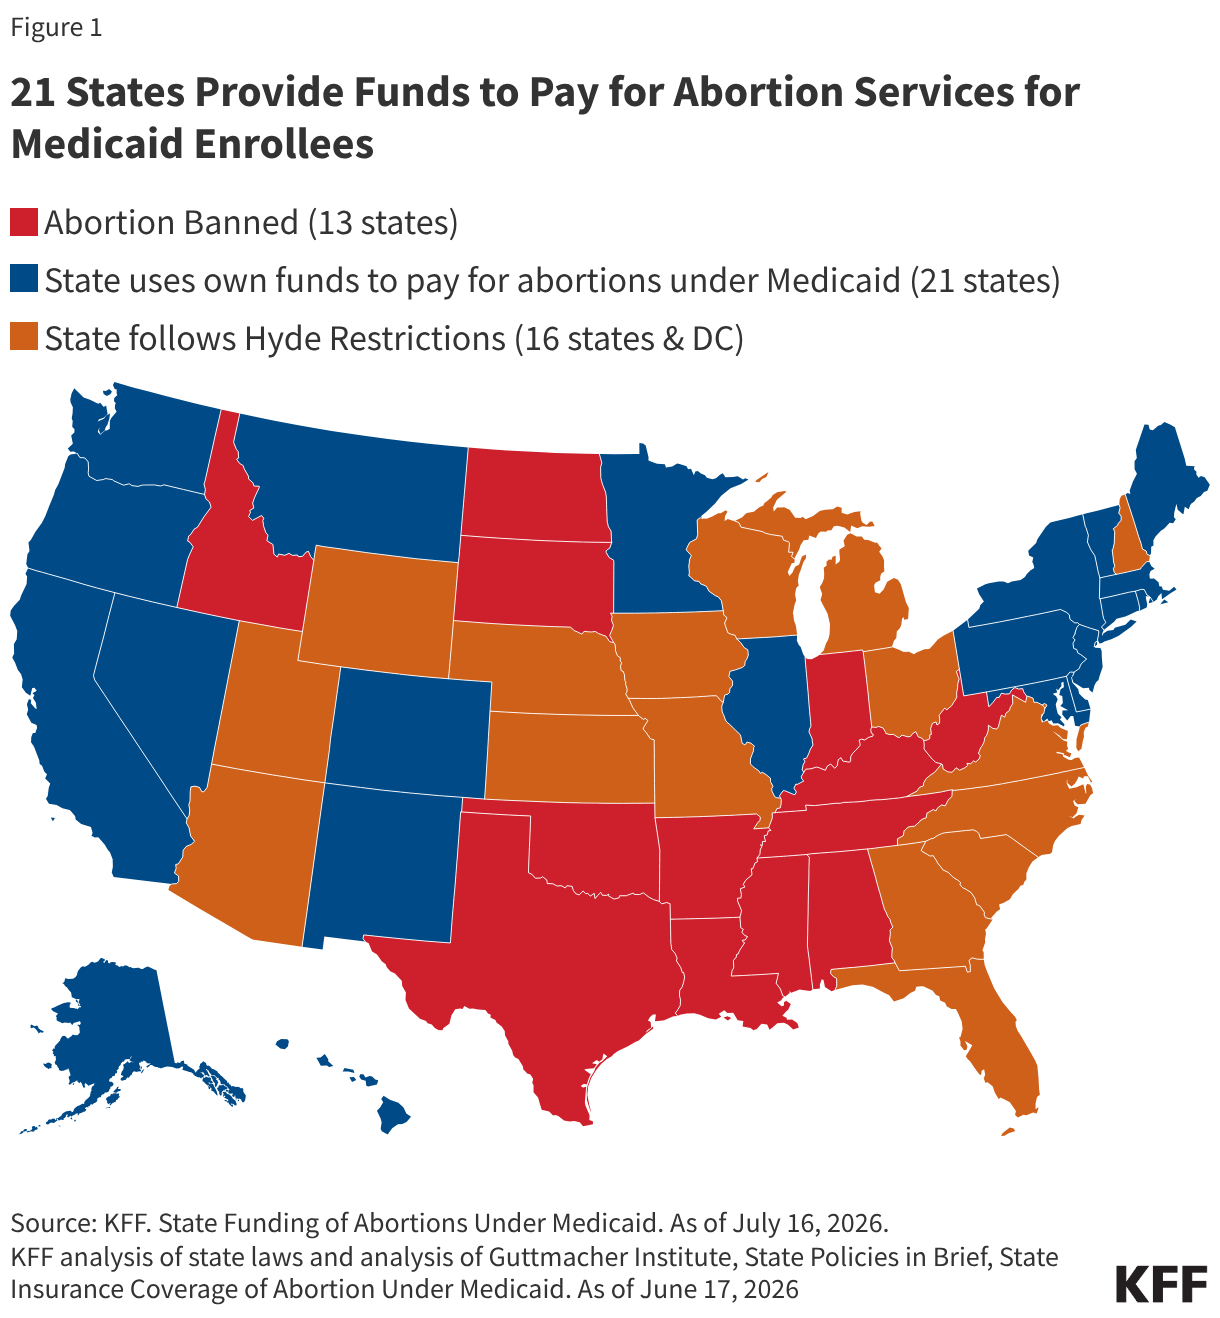
- Banned Jurisdictions: 13 states have banned abortion entirely, effectively removing Medicaid as a factor for these services.
- State-Funded Expansion: 21 states use their own non-federal revenues to expand Medicaid coverage for abortion services beyond the rigid restrictions of the Hyde Amendment.
- Hyde-Restricted States: 16 states and the District of Columbia permit abortion but limit Medicaid coverage strictly to the Hyde-defined exceptions.
The core issue identified by researchers is that Medicaid reimbursement rates—set by states under broad federal guidelines—have historically lagged significantly behind both Medicare and private insurance benchmarks. This persistent underpayment creates a "reimbursement gap" that forces providers to choose between absorbing substantial financial losses or restricting their Medicaid caseloads, ultimately limiting access for the low-income populations that rely on the program.
Chronology: A Shifting Landscape Since 2022
The trajectory of Medicaid abortion funding has been volatile since the summer of 2022.
- June 2022: The Dobbs decision triggers an immediate wave of legislative activity. Thirteen states move to implement near-total bans, drastically altering the geography of care.
- 2023: Medication abortion, already a primary method of pregnancy termination, sees its share of the abortion market climb to 65% following FDA regulatory shifts that expanded access via telehealth and mail.
- 2024: KFF publishes its initial analysis of the reimbursement gap. Reports from organizations like the National Health Law Program begin highlighting the inconsistent state of "telehealth parity," where some states briefly adopted, then abandoned, policies that allowed for fair compensation for virtual visits.
- 2025: A U.S. Government Accountability Office (GAO) report confirms widespread non-compliance among states in the Medicaid Drug Rebate Program, finding that 14 states were failing to cover FDA-approved medication abortion drugs even in instances where such coverage was legally mandated under the Hyde Amendment.
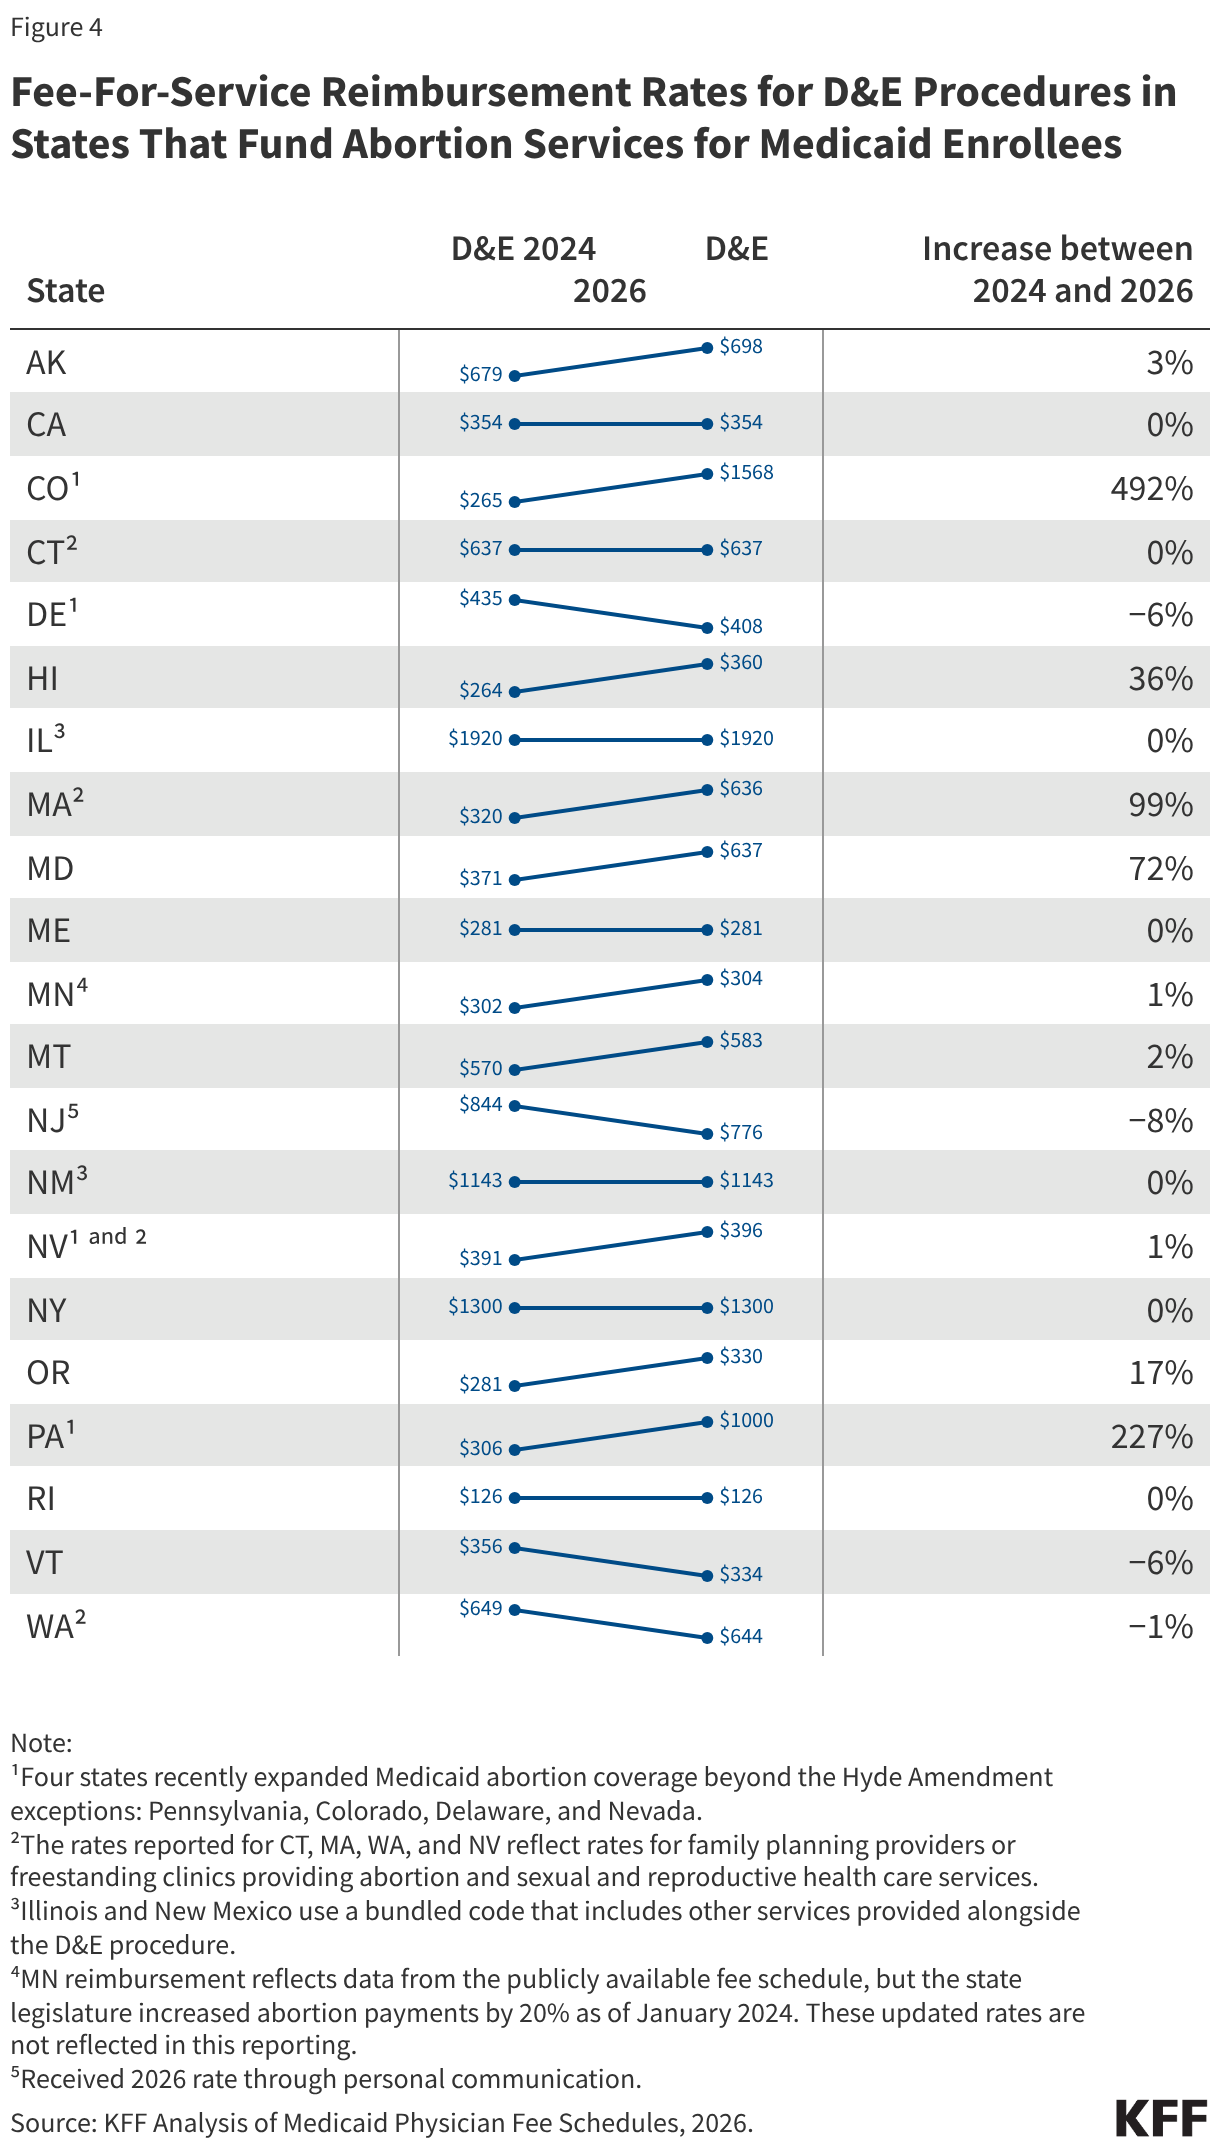
- 2026 (Present): New data shows that while some states—most notably Pennsylvania, Colorado, and Massachusetts—have made significant, corrective increases to their reimbursement rates, the majority of states have seen either stagnation or actual decreases in rates when adjusted for health care inflation.
Supporting Data: The Cost of Care vs. The Price of Payment
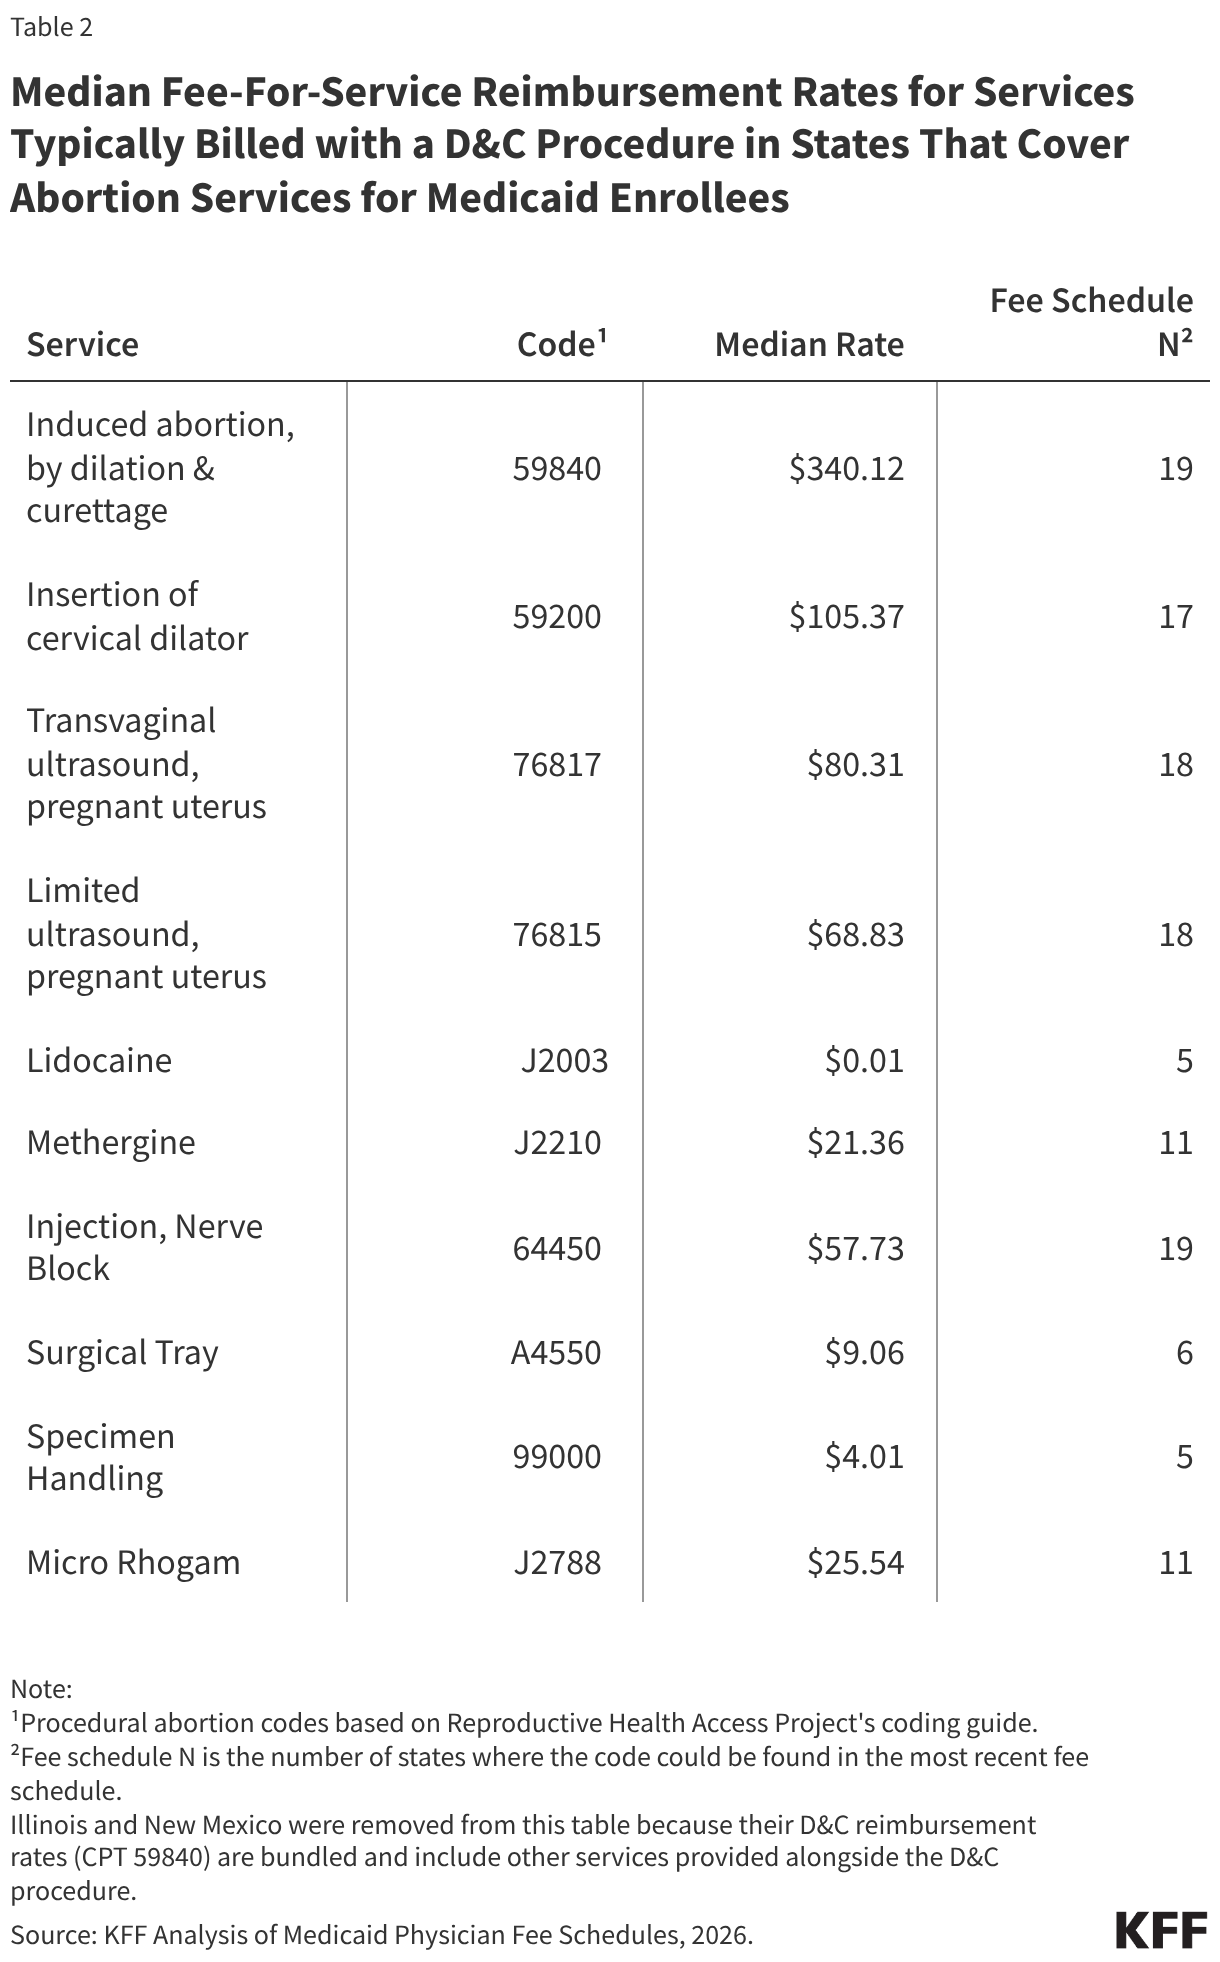
The discrepancy between what providers charge self-pay patients and what they receive from Medicaid is striking. Research indicates that median Medicaid reimbursements for first-trimester D&C procedures often cover less than 40% of the market rate charged to self-pay patients.
The Medication Abortion Disparity
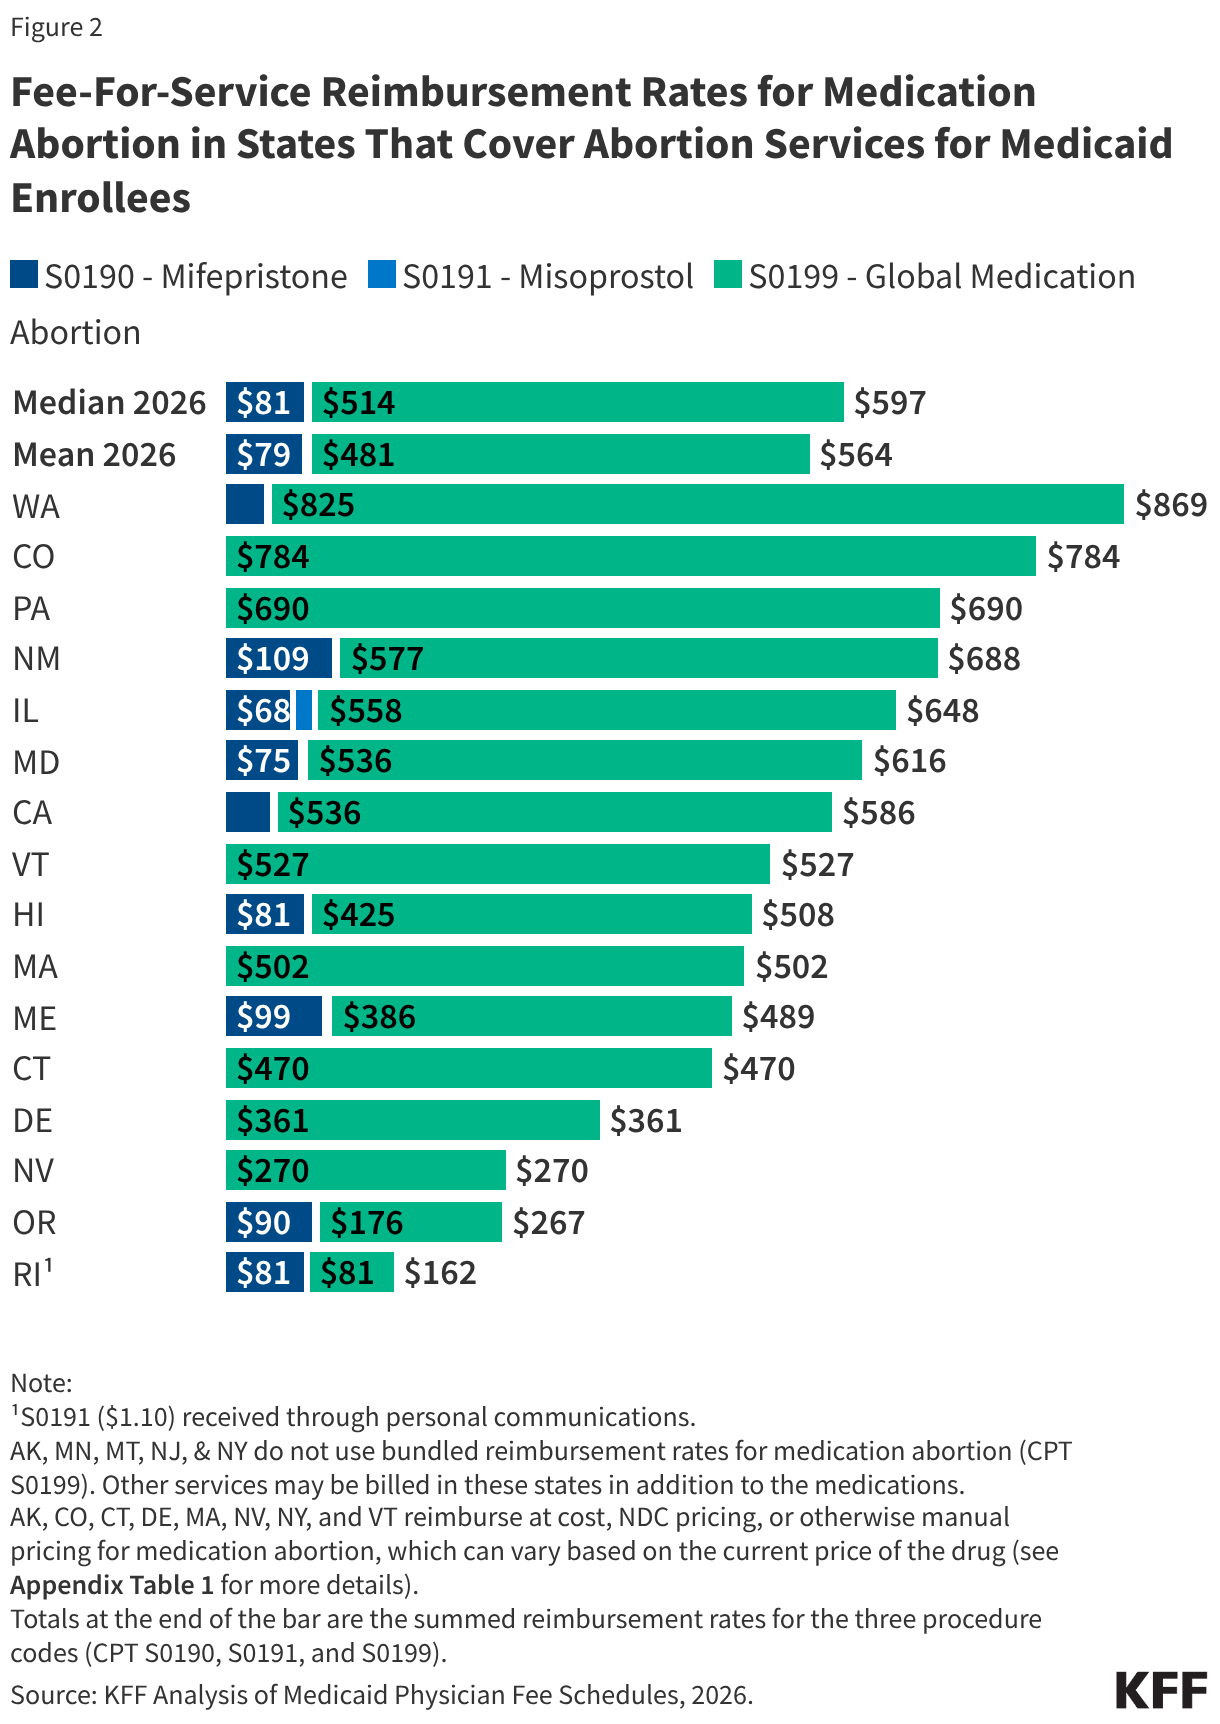
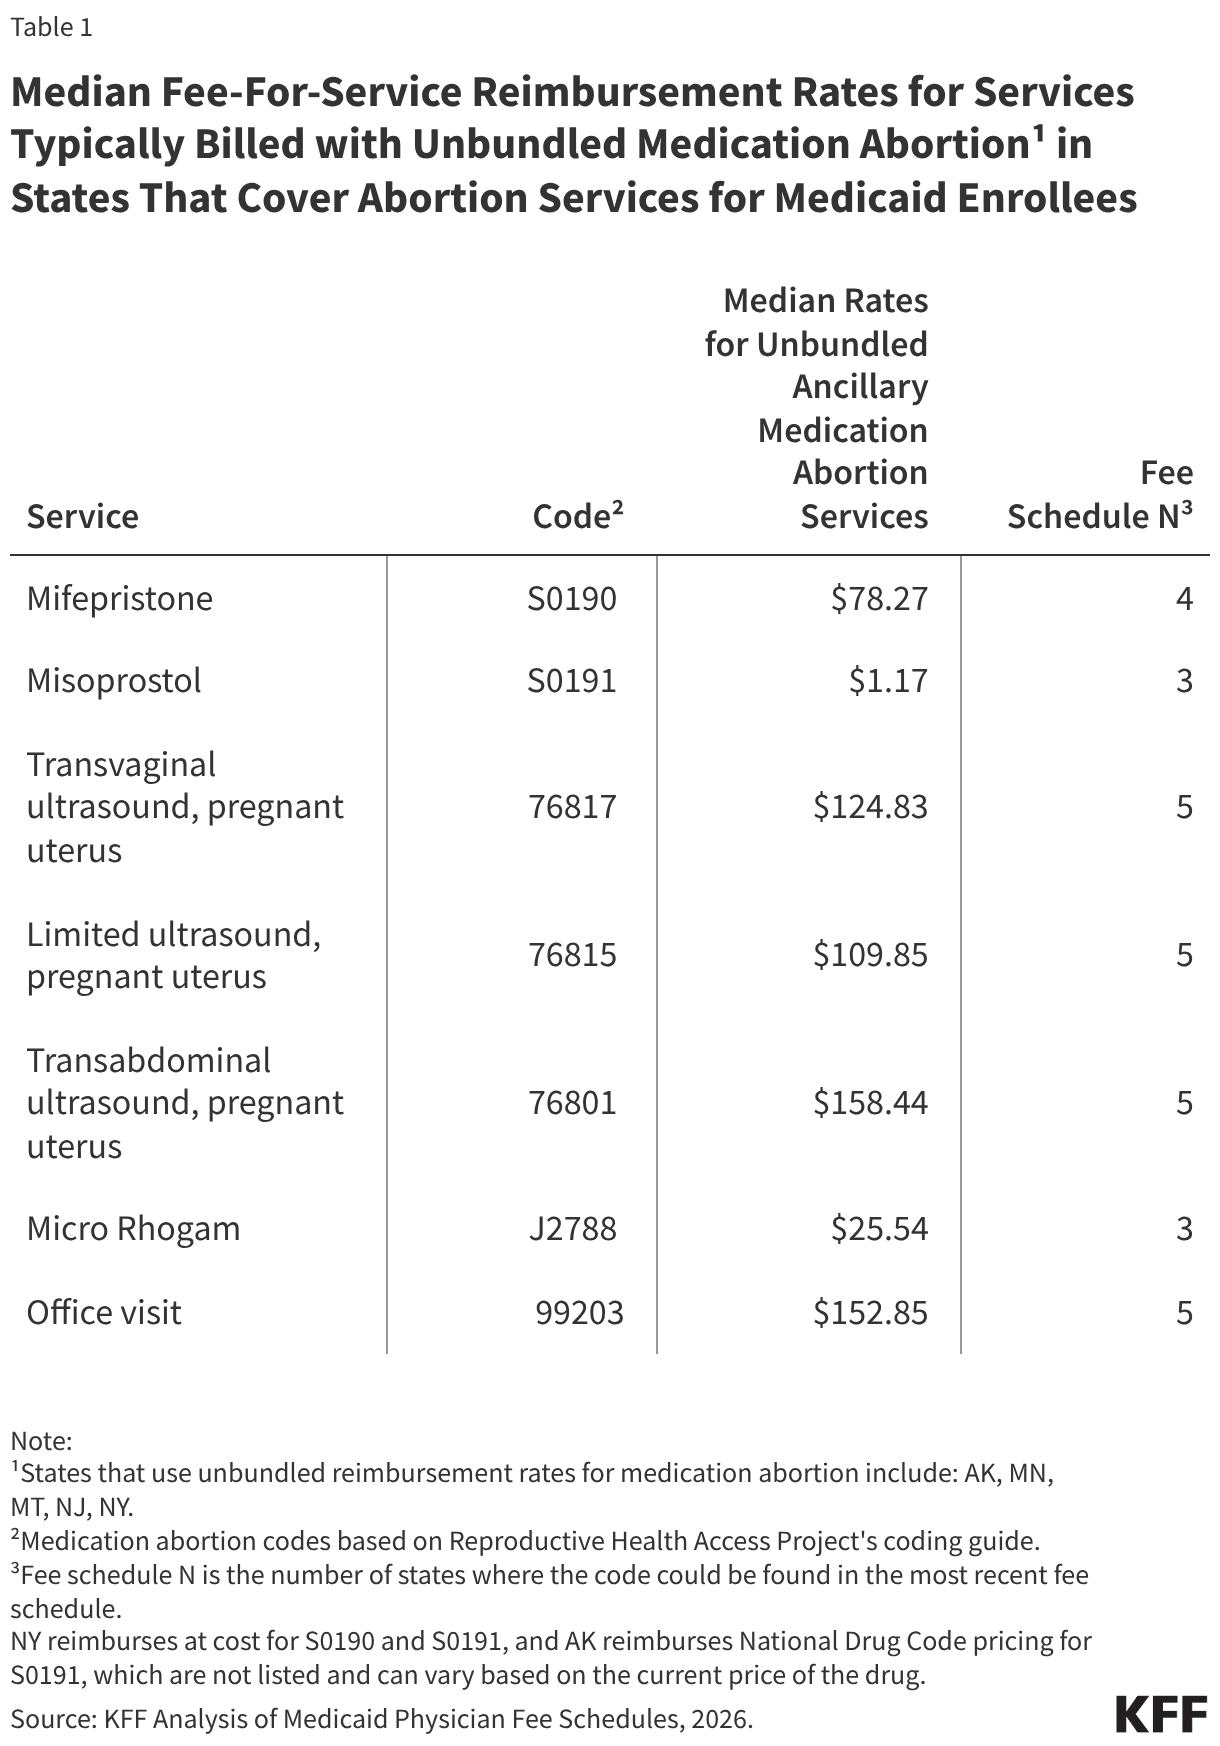
Medication abortion, which relies on a regimen of mifepristone and misoprostol, is often billed using a "global" code (S0199) meant to cover the medication, counseling, and follow-up ultrasounds. The median reimbursement rate for this global code sits at $514. However, this national median masks a staggering variance: rates range from as low as $81 in Rhode Island to $825 in Washington. When ancillary services—such as mandatory ultrasounds or Rh testing—are not included in a "bundled" payment, providers are often left to navigate an unbundled billing system that is complex, administratively burdensome, and prone to denial.
Procedural Abortion Trends
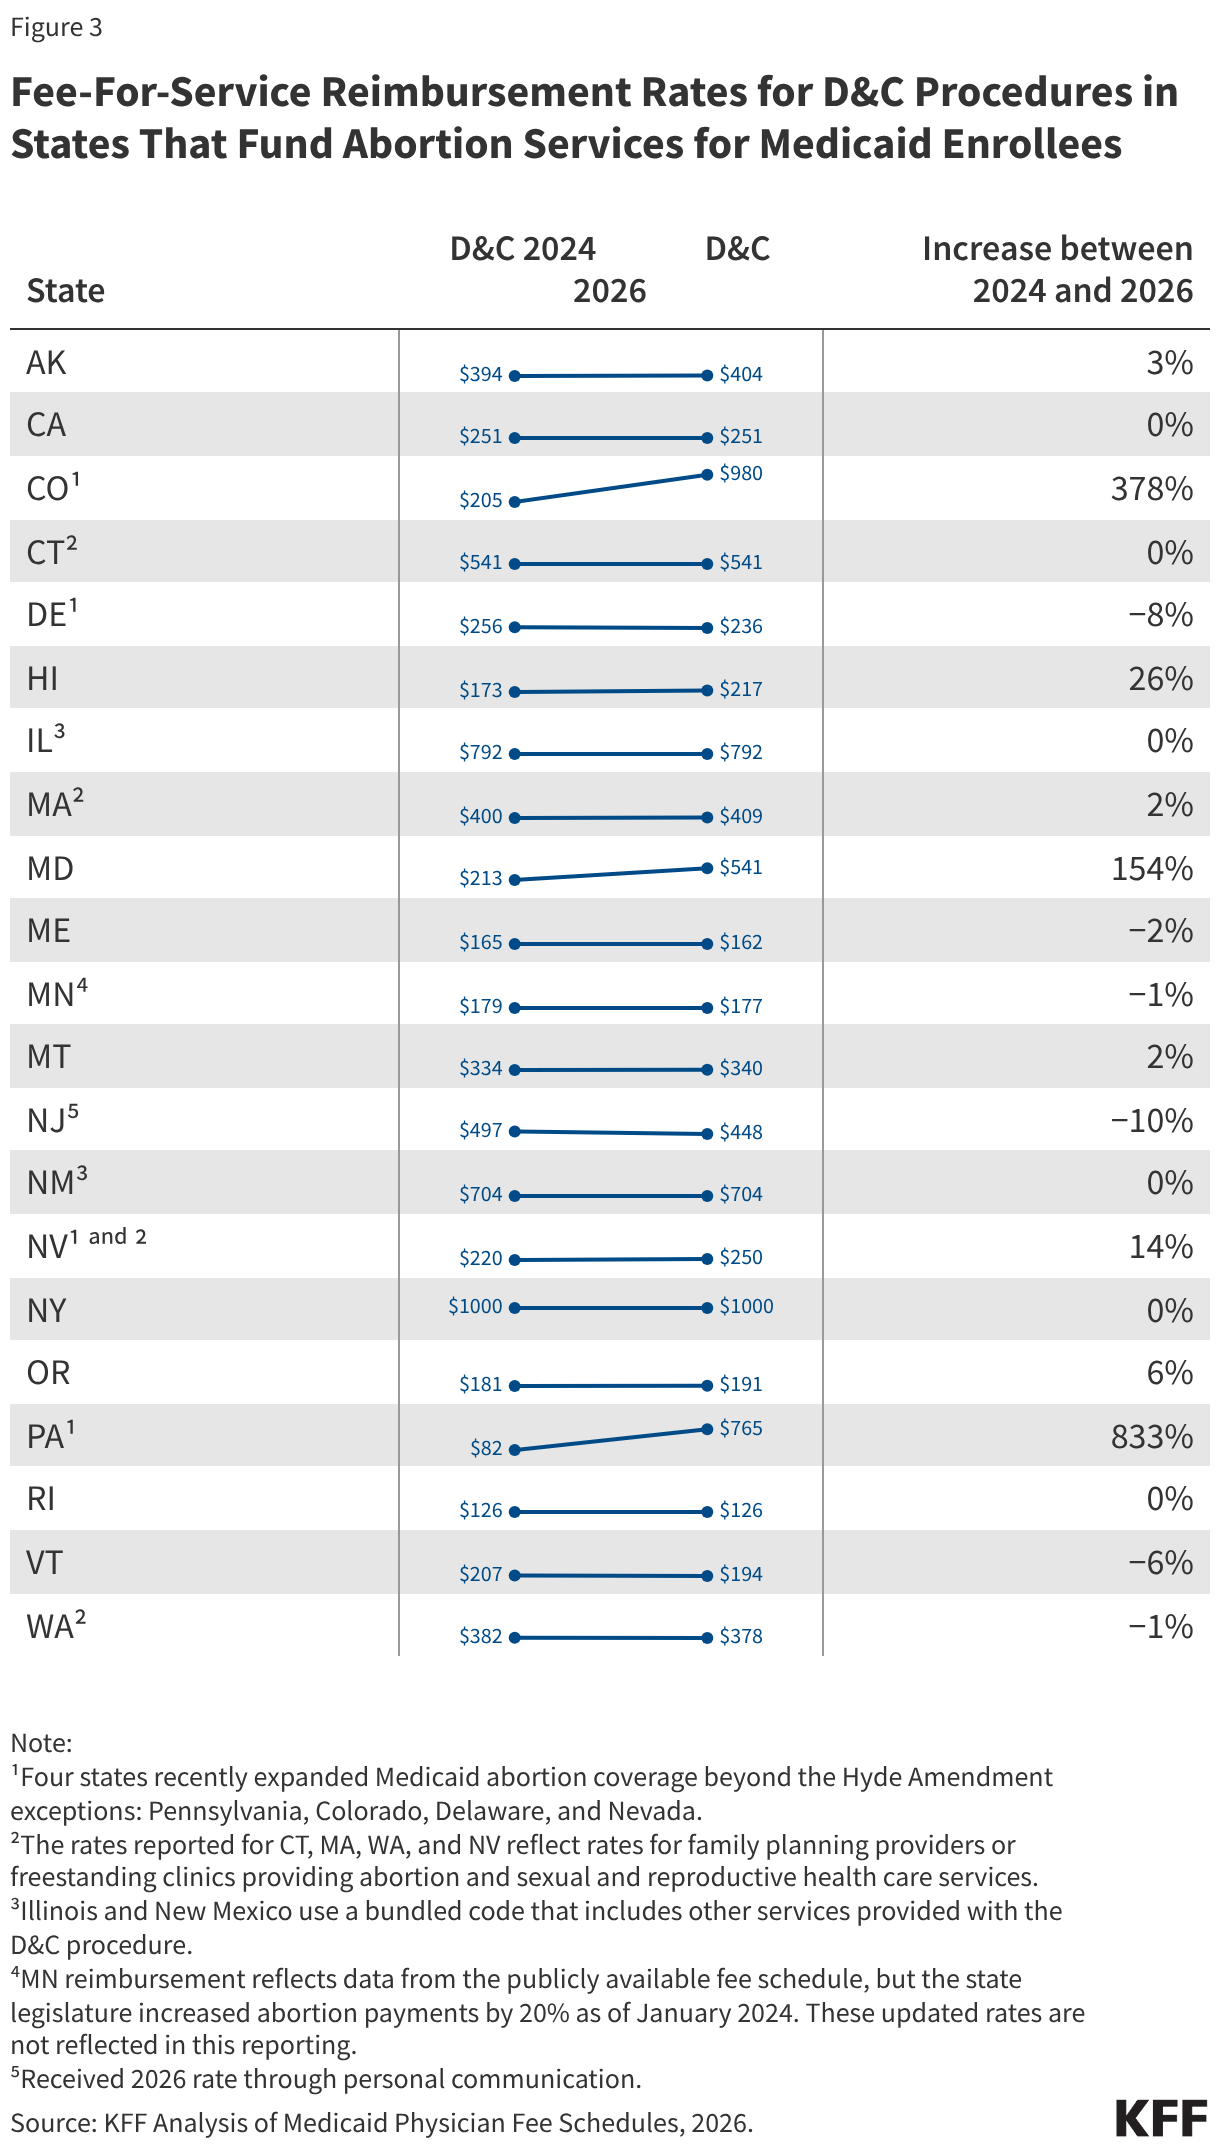
For surgical procedures like Dilation and Curettage (D&C) and Dilation and Evacuation (D&E), the financial landscape is equally uneven. While states like Pennsylvania have recently implemented massive increases in reimbursement (up 833% for D&C), these are outliers. Of the 21 states using state funds to cover abortions, only five have increased their rates at or above the rate of medical inflation over the last two years. Many states continue to reimburse for D&E procedures—which are more complex and resource-intensive—at rates nearly identical to simpler D&C procedures, effectively punishing providers for performing later-term care.
Official Responses and Regulatory Hurdles
The Centers for Medicare and Medicaid Services (CMS) faces increasing pressure to address the findings of the 2025 GAO report. The failure of 14 states to provide coverage for medication abortion in cases of rape, incest, or life endangerment represents a clear violation of federal requirements. Advocates argue that without aggressive oversight from CMS to ensure state compliance, the "right" to an abortion in cases permitted by law remains a theoretical privilege rather than a practical reality.
Furthermore, the emergence of telehealth has complicated the regulatory picture. While some states have codified payment parity—ensuring that a virtual consultation is reimbursed at the same rate as an in-person visit—many others have allowed pandemic-era emergency policies to expire. This creates a "zip-code lottery" where a provider’s ability to sustain a practice depends entirely on the specific Medicaid billing policies of their home state.
Implications: A Fragile Safety Net
The consequences of these financial policies reach far beyond balance sheets.
Erosion of the Provider Workforce
Abortion providers operate in a unique and hostile environment. They face extraordinary overhead costs that standard outpatient clinics do not, including the necessity of professional security, bulletproof infrastructure, and intensive staff training to manage the constant threat of anti-abortion violence. When Medicaid rates fail to cover even the basic cost of clinical delivery, these security expenses become impossible to sustain, leading to clinic closures and a diminishing workforce.
The Burden on Patients and Abortion Funds
When Medicaid does not cover the full cost of a procedure, the burden shifts to the patient. For the low-income individuals who make up the majority of the Medicaid population, this often means relying on abortion funds. However, these funds are currently facing a "post-Dobbs" crisis of their own: as the demand for financial assistance has surged, charitable donations have declined, leaving these essential safety nets in a state of depletion.
Deepening Reproductive Inequity
The data makes it clear that insurance coverage is, in itself, insufficient to guarantee access. When the reimbursement structure is designed to discourage participation, the result is a systemic withdrawal of providers from the Medicaid market. This effectively creates a tiered system of healthcare where high-quality, professional abortion care is increasingly reserved for those with private insurance or the ability to pay out-of-pocket, while Medicaid beneficiaries are left with a shrinking number of clinics and growing financial barriers.
The current trajectory suggests that without a standardized, nationwide commitment to fair Medicaid reimbursement, the reproductive healthcare infrastructure in the United States will continue to erode from within. As clinical costs rise and the political environment remains volatile, the financial sustainability of the abortion provider network remains the most critical, and overlooked, front in the fight for reproductive autonomy.
About the Author