The rapid ascent of weight-loss blockbusters like Ozempic, Wegovy, and Zepbound has triggered a secondary, often unregulated, gold rush. As demand for these GLP-1 receptor agonists far outstripped supply, a sprawling network of compounding pharmacies and tech-enabled, direct-to-consumer (DTC) telehealth clinics emerged to fill the gap. Today, that industry faces a reckoning as federal regulators, pharmaceutical giants, and a wave of litigation converge on what appears to be a systemic public health risk.
With over 1,700 adverse event reports logged by the FDA specifically linked to compounded semaglutide and tirzepatide, the veneer of the "weight-loss revolution" is cracking. What was once heralded as a democratizing force in metabolic health is now being scrutinized for deceptive marketing, questionable clinical oversight, and significant patient safety failures.
A Chronology of a Regulatory Cat-and-Mouse Game
The current chaos in the compounded GLP-1 market is rooted in the FDA’s decision to allow compounding during national drug shortages. When Wegovy and Ozempic were added to the FDA’s shortage list in 2022, it opened a narrow legal window under section 503A of the Federal Food, Drug, and Cosmetic Act, permitting pharmacies to create "essentially identical" copies of patented drugs.
- 2022–2024 (The Shortage Window): Manufacturers Novo Nordisk and Eli Lilly struggled to scale production. Telehealth startups, sensing a massive market, began using aggressive digital marketing to connect patients with compounding pharmacies, often with little more than a digital questionnaire serving as a "clinical consultation."
- Late 2024 – Early 2025 (The Tide Turns): The FDA declared the shortages of tirzepatide and semaglutide resolved. The subsequent enforcement discretion period ended on May 22, 2025. This effectively criminalized the production of "copycat" versions of these drugs.
- 2025–2026 (The Crackdown): The FDA intensified its regulatory posture, issuing waves of warning letters. In September 2025 alone, the agency targeted dozens of sellers in a single day. By mid-2026, the agency had issued over 100 warning letters, citing misbranding and the unauthorized marketing of unapproved drugs.
The MEDVi Paradigm: A Blueprint for Potential Fraud
Perhaps no company better encapsulates the volatility of this sector than MEDVi. In April 2026, The New York Times reported that the AI-driven firm was on track for $1.8 billion in annual sales, with 2025 revenues hitting $401 million. Yet, beneath the veneer of high-tech innovation, the company faced significant regulatory fire.

In February 2026, the FDA issued a scathing warning letter to MEDVi, alleging that the company had obfuscated the true source of its products and misleadingly implied they were FDA-approved. MEDVi’s response—that the letter was directed at an "affiliate" rather than the parent company—did little to assuage critics. Evidence emerged showing that MEDVi’s web infrastructure was designed to funnel unsuspecting users into an intake system that blurred the lines between disparate entities.
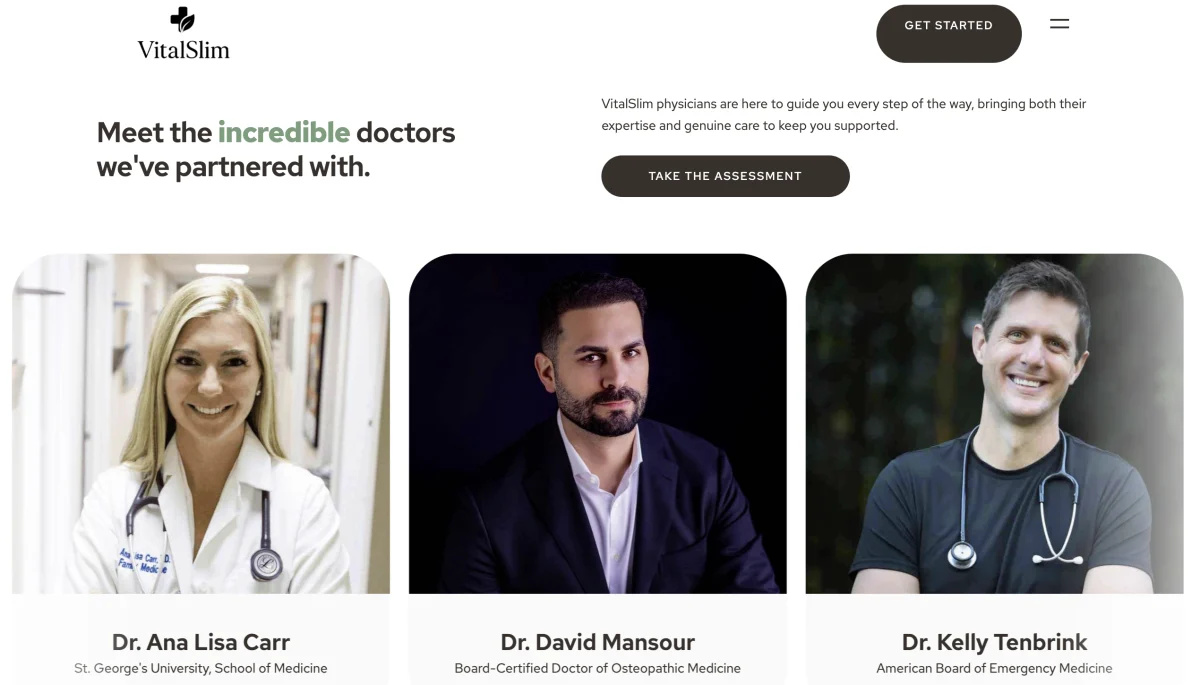
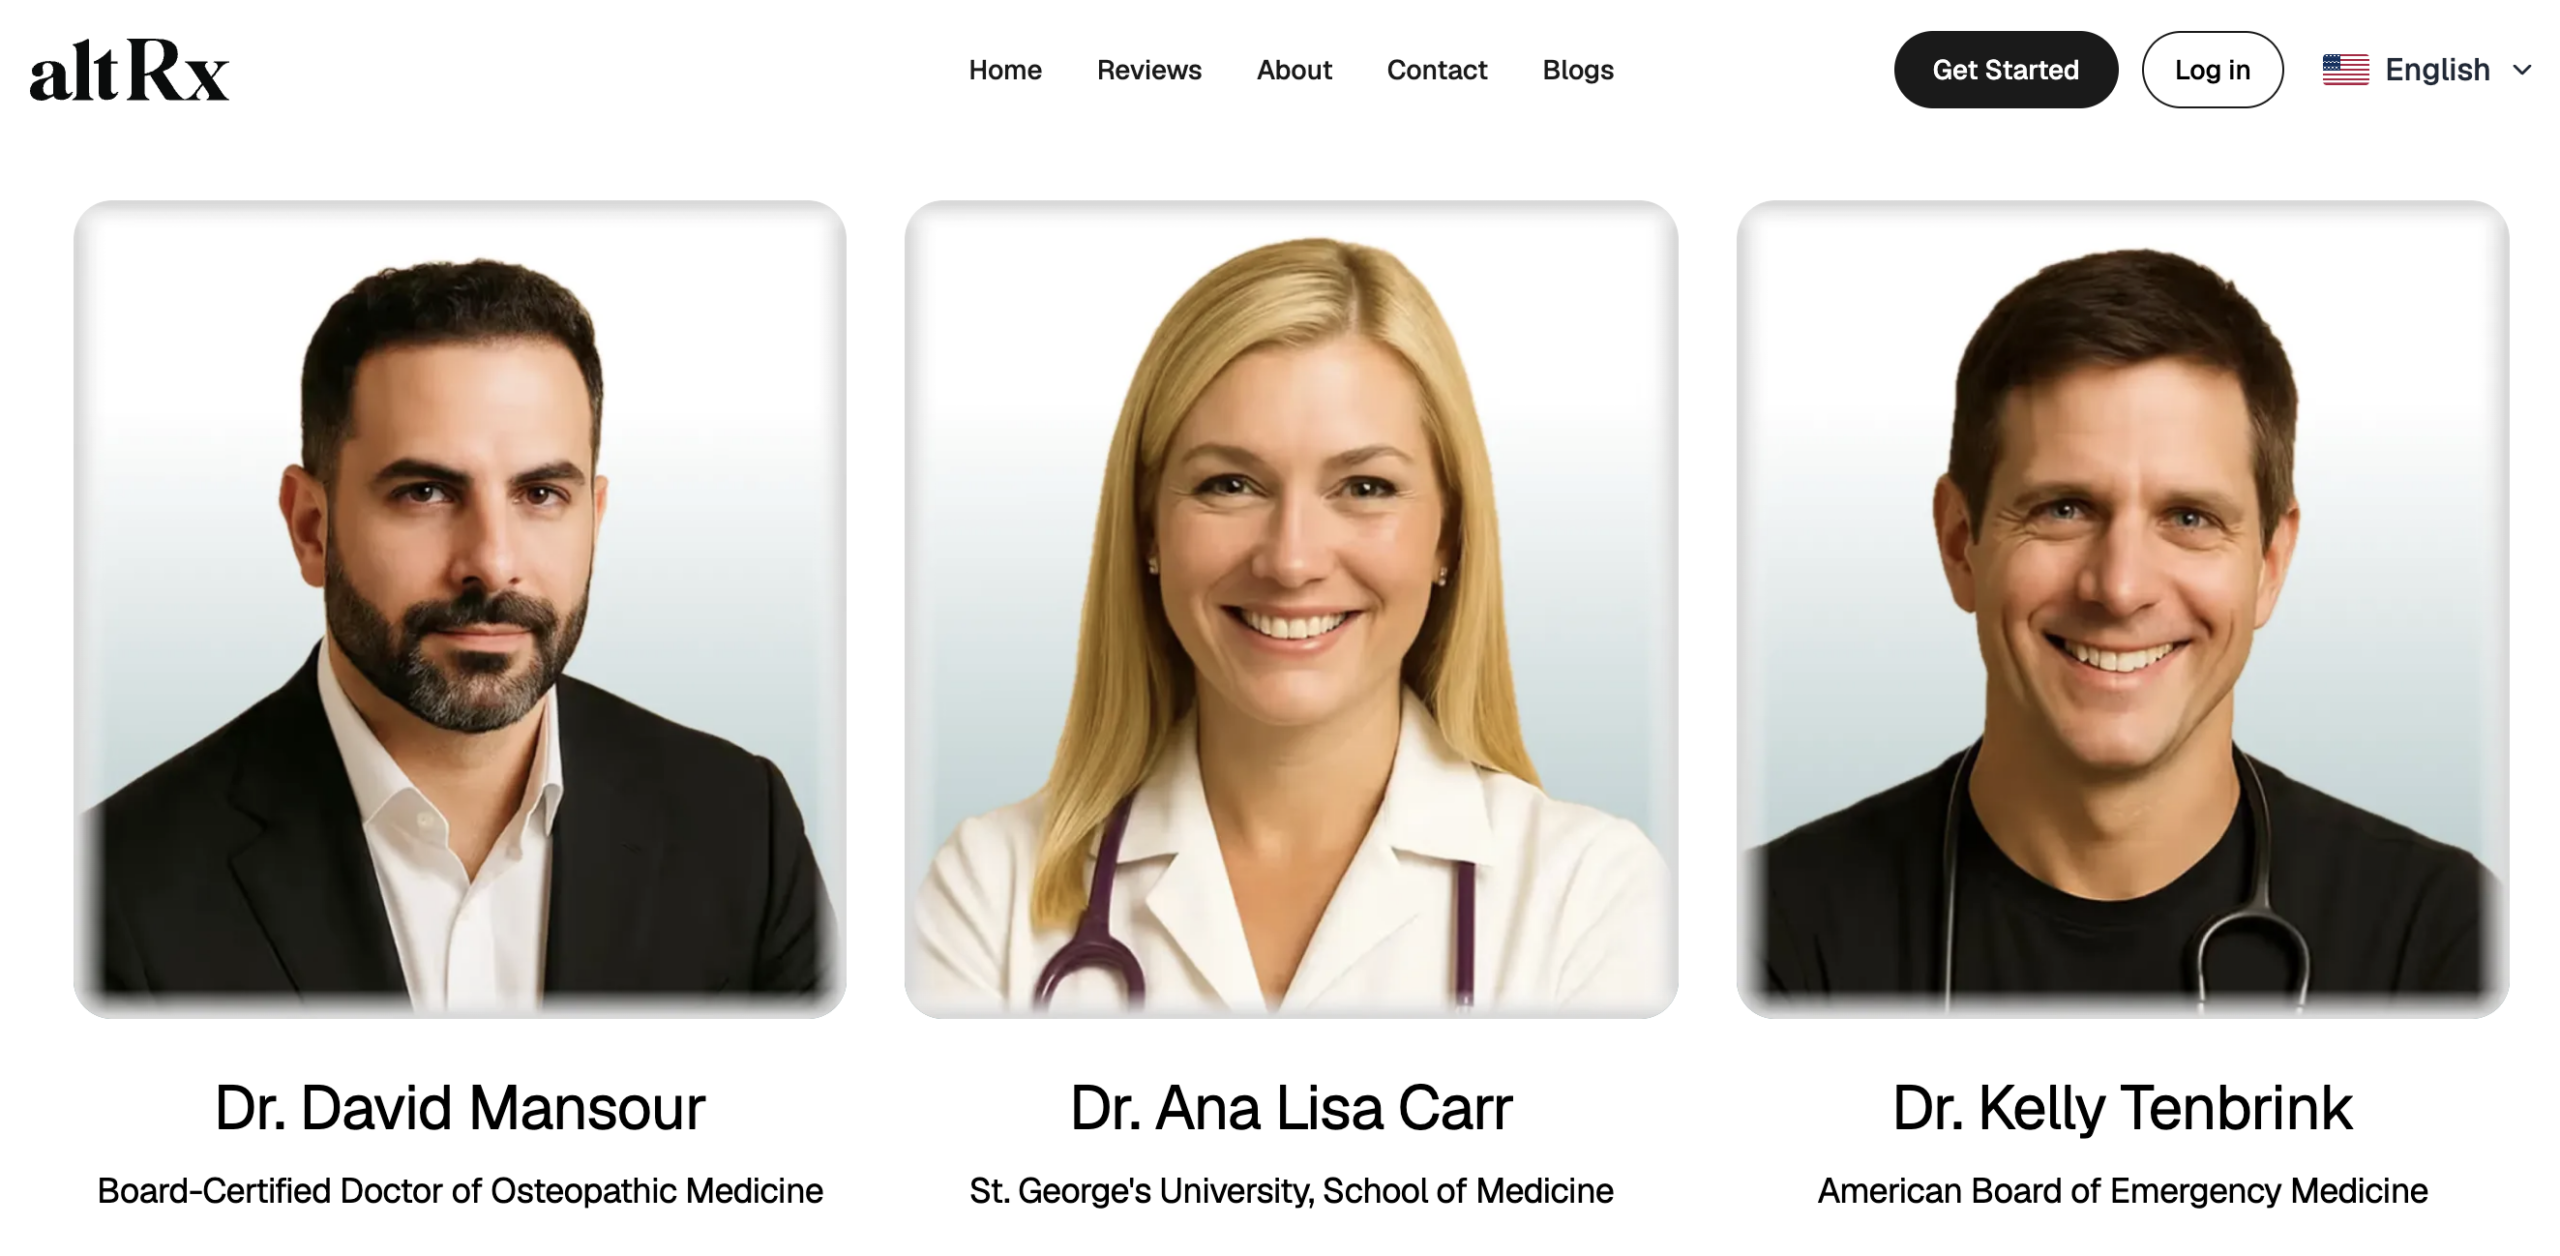
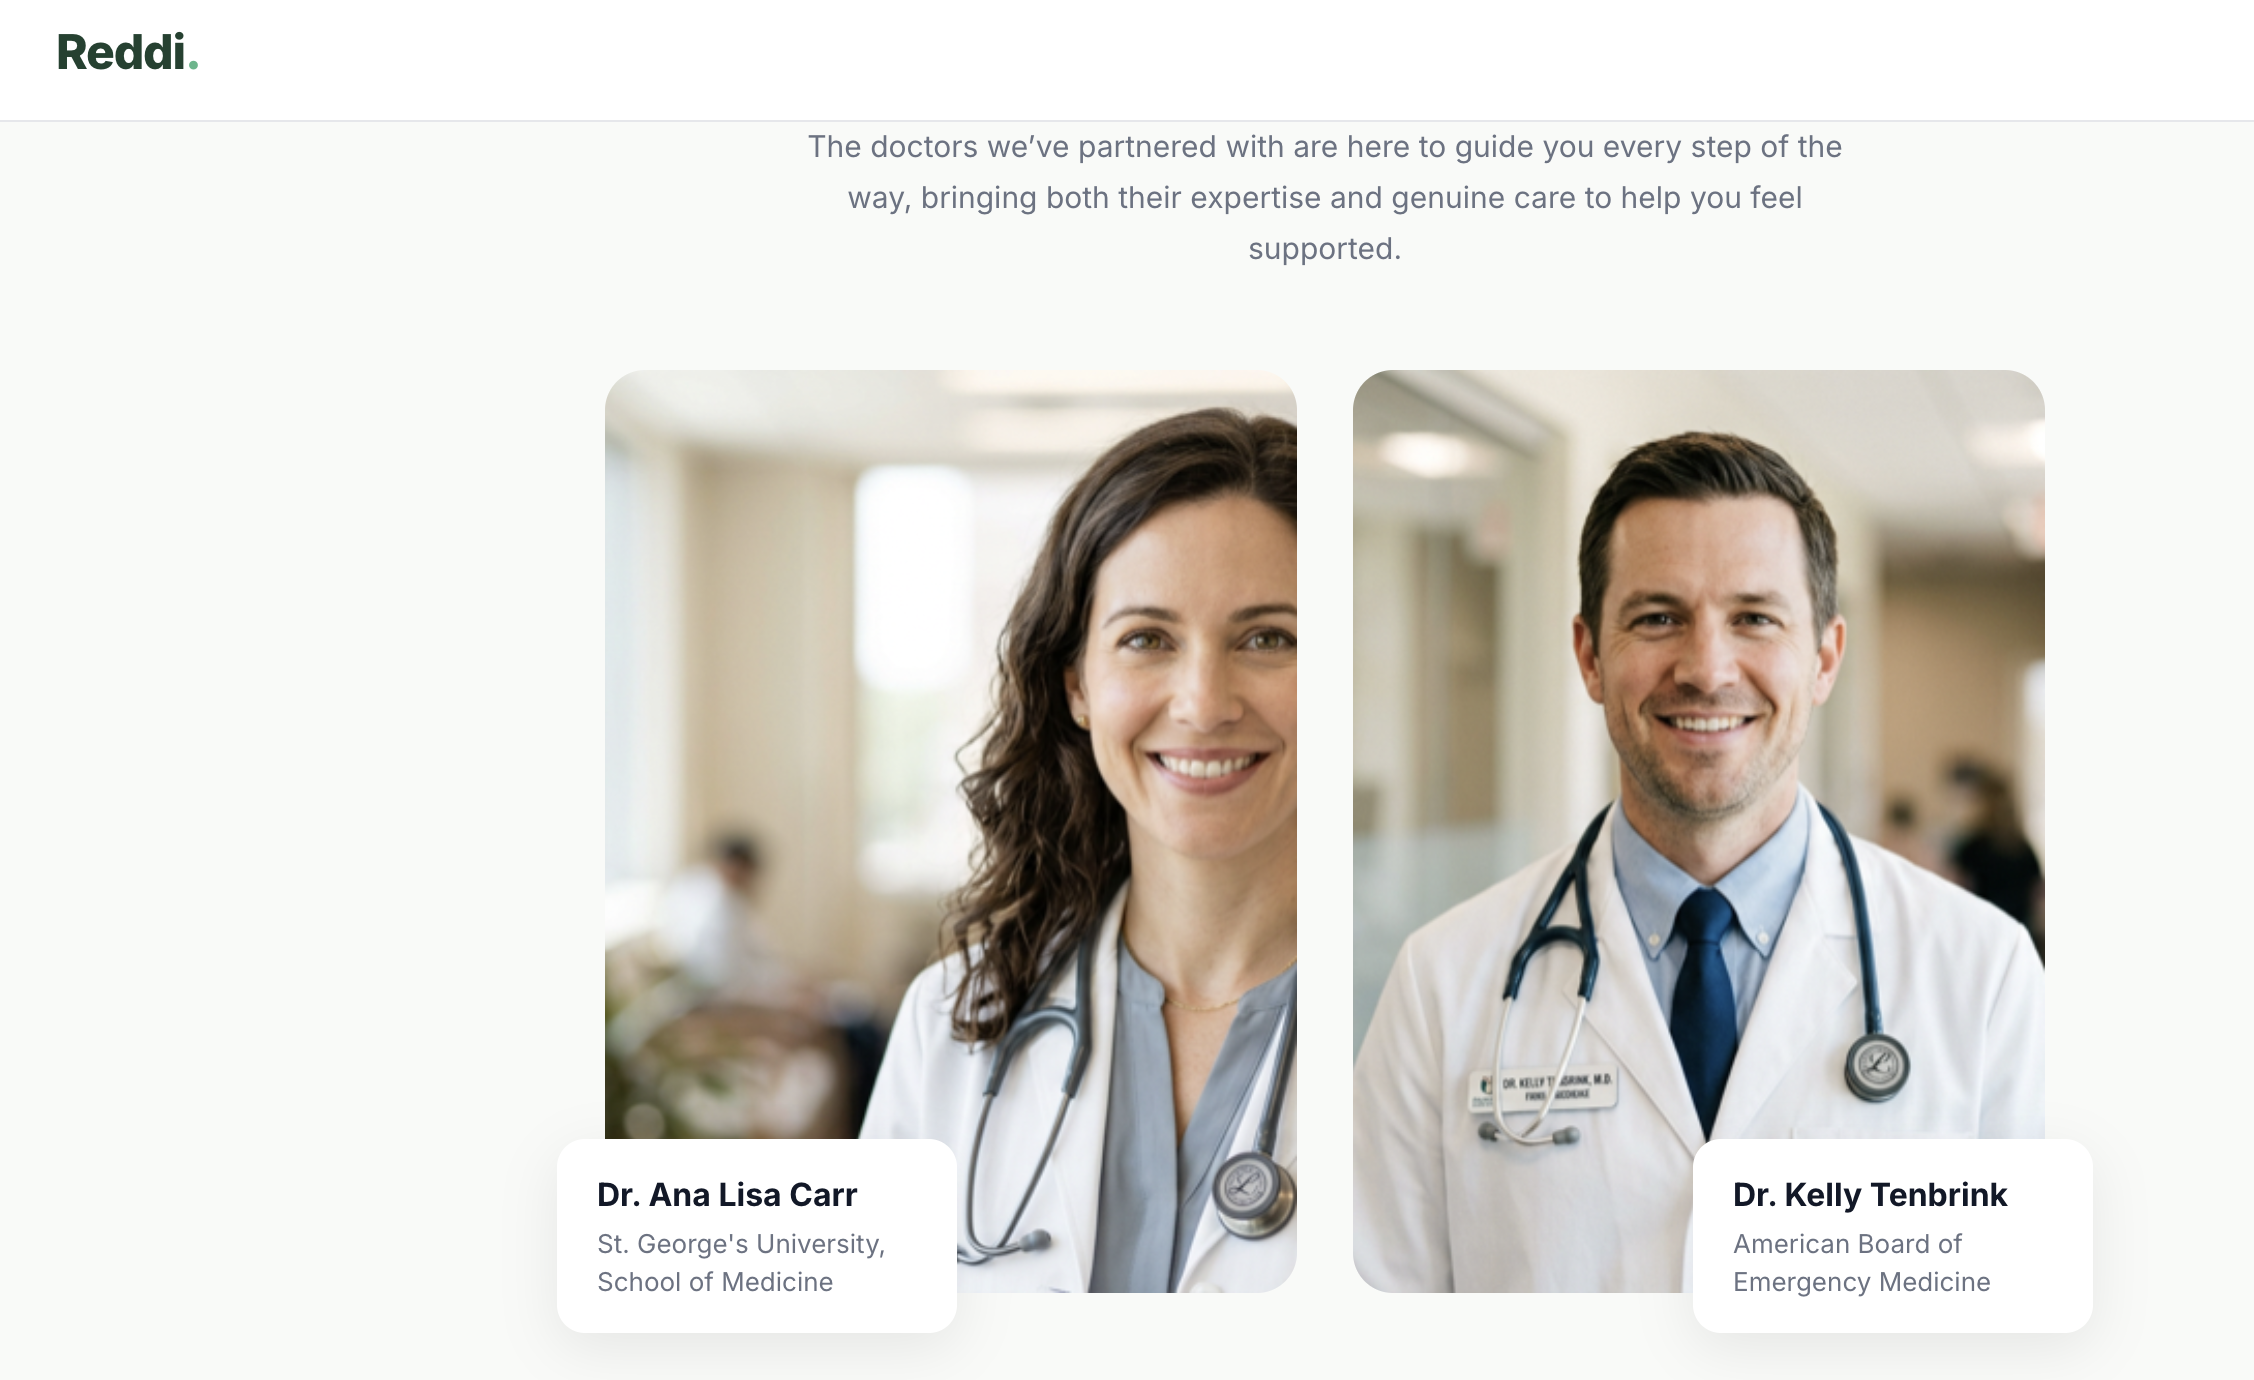
This "playbook"—using overlapping clinicians, shared pharmacy networks, and recycled website templates—is not unique to MEDVi. It appears to be an industry-wide standard. Investigative findings show that several platforms, including VitalSlim and MDRxLabs, have featured the same physicians previously utilized by MEDVi. This incestuous network of providers and pharmacy partners, such as Triad Rx and OpenLoop Health, suggests a centralized infrastructure operating behind a fragmented array of front-facing storefronts.
Supporting Data: The Rising Toll on Patient Safety
The public health implications of this unregulated proliferation are stark. America’s Poison Centers have reported an alarming 1,500% increase in GLP-1 exposure cases between 2019 and 2025. While many of these instances involve accidental therapeutic errors with legitimate, FDA-approved pens, the compounded market introduces a far more dangerous variable: human error in the compounding and administration process.
Dosing Errors and Beyond
Compounded products are often shipped in vials, requiring patients to draw their own doses using syringes. This transition from the auto-injector pens used in name-brand medications to manual syringes has led to 10-fold dosing errors. Patients, often confused by unit conversions, have inadvertently administered massive overdoses, leading to severe gastrointestinal distress, hypoglycemia, and, in some cases, hospitalization.
Furthermore, the FDA has warned that the labels on these products are frequently unreliable. Investigations have uncovered instances where the stated pharmacy of origin does not exist, or where the drug contains substances not listed on the label.
The Institutional Pushback: Pharma vs. The Compounders
Pharmaceutical giants Novo Nordisk and Eli Lilly have transitioned from defensive market management to an aggressive litigation strategy. Novo Nordisk has filed over 130 lawsuits across 40 states, securing dozens of permanent injunctions against compounding entities. Eli Lilly has taken a similar route, targeting telehealth platforms and compounders alike for patent infringement and the dissemination of "copycat" medications.
The industry pushback is not merely legal; it is economic. Compounding pharmacies have enjoyed explosive growth, with some entities seeing their revenue triple in a single year. The Houston Chronicle reported that Empower Pharmacy alone generated $311 million in a 10-month period, with 66% of that revenue tied directly to GLP-1s. For these entities, the legislative and legal threats represent an existential challenge to a multi-billion-dollar revenue stream.
Implications: The Legislative Future
The current legislative landscape is defined by the SAFE Drugs Act of 2025. This bipartisan bill seeks to clamp down on the compounding of "essentially copied" products by limiting their production to 20 units per month, unless a specific clinical necessity is documented.
The debate over this bill has created strange bedfellows. The Alliance for Pharmacy Compounding and the National Community Pharmacists Association are fiercely lobbying against the 20-unit limit, arguing that it threatens the viability of legitimate compounding pharmacies that serve patients with rare allergies or specific medical needs. However, proponents of the bill argue that without such guardrails, the "Wild West" era of telehealth GLP-1s will continue to endanger the public.
Conclusion: A Systemic Failure of Oversight
The rise of the compounded GLP-1 market is a cautionary tale of how technological innovation—in this case, AI-driven telehealth—can outpace the regulatory frameworks designed to protect public health. The ease with which consumers can obtain potent metabolic drugs through a few clicks and a digital questionnaire has created a environment where profit motives often override clinical safety.
As the legal battles continue and Congress weighs the SAFE Drugs Act, the core issue remains the lack of transparency in the supply chain. Whether it is a class-action suit alleging RICO violations against telehealth infrastructure providers or the FDA’s ongoing struggle to shutter illegal storefronts, the message is clear: the era of unchecked, "off-the-books" weight loss is coming to a close.
For the millions of Americans currently using these medications, the next phase of this crisis will likely be defined by a shift toward more stringent clinical oversight, the closure of high-risk telehealth platforms, and a long-overdue reckoning with the realities of pharmaceutical manufacturing and patient safety in the digital age. The promise of an easy fix for obesity has proven to be a double-edged sword, and the medical community, along with federal regulators, is now tasked with picking up the pieces.
About the Author