For decades, the diagnosis of metastatic cancer was synonymous with a shift in clinical focus: from curative intervention to palliative care. The medical community long operated under the "seed and soil" hypothesis, which assumed that once cancer cells had escaped the primary tumor and seeded distant organs, the disease had become systemic and, by definition, incurable.
However, a paradigm shift is underway. Recent clinical research and technological advancements in precision radiotherapy have illuminated a middle ground: oligometastatic disease (OMD). Characterized by a limited number of metastatic lesions, this state suggests that for a subset of patients, cancer may not be a ubiquitous systemic threat but a manageable, localized challenge.
A newly released comprehensive eBook, The Oligometastatic Frontier, synthesizes the latest clinical evidence, economic evaluations, and multidisciplinary perspectives, arguing that the time has come to treat select metastatic patients with curative intent.
Main Facts: Challenging the Incurability Dogma
The fundamental premise of the oligometastatic framework is that there exists a biological "window" between localized disease and widespread, polymetastatic progression. In this state, the tumor burden is sufficiently low—typically defined as one to five lesions—that it may be amenable to aggressive local therapies, such as stereotactic ablative radiotherapy (SABR) or focal surgery.
The Biological Rationale
The primary driver behind this shift is the recognition of tumor heterogeneity. Not all metastases possess the same aggressive phenotypes. Some lesions may be indolent, while others are highly metastatic. By identifying the "oligometastatic state," clinicians can intervene before the disease transitions into a state of high-volume, systemic progression.
The Role of Technology
The clinical viability of this approach rests on the precision of modern technology. Stereotactic Radiotherapy (SRT) and Stereotactic Radiosurgery (SRS) allow clinicians to deliver ablative doses of radiation to small, specific targets with millimeter-scale accuracy, sparing the surrounding healthy tissue. This has transformed the risk-benefit analysis, making it possible to target lesions in sensitive areas—such as the brain, lung, or liver—without the debilitating systemic side effects associated with traditional chemotherapy.
Chronology: The Evolution of the Oligometastatic Concept
To understand why the medical community is moving toward curative intent, one must look at the historical trajectory of oncological treatment.
- 1995: The Hellman-Weichselbaum Hypothesis: The concept was first introduced by Samuel Hellman and Ralph Weichselbaum, who proposed that metastasis is a spectrum rather than a binary state. Their work suggested that some patients possess a limited metastatic burden that could potentially be cured if the metastatic foci were eradicated.
- 2000s–2010s: The Rise of Precision Imaging: The advent of PET/CT scans and advanced MRI allowed for the earlier detection of smaller metastatic lesions, providing the diagnostic foundation necessary to identify oligometastatic patients.
- 2015–2020: The "SABR" Revolution: Randomized clinical trials, such as the SABR-COMET trial, began to provide the first high-level evidence that aggressive local treatment of metastatic sites could lead to significant improvements in overall survival compared to standard-of-care systemic therapy alone.
- 2024: Integration into Clinical Practice: Current guidelines and multidisciplinary tumor boards are now actively incorporating oligometastatic management strategies, moving from anecdotal success to standardized treatment pathways.
Supporting Data: Site-Specific Nuance
The efficacy of treating oligometastatic disease is not uniform; it is highly dependent on the primary tumor site and the biological behavior of the specific cancer. The latest research highlights the importance of tailoring treatment to the site of the lesion.
Pulmonary Perspective: Lung Cancer
Pulmonologists and thoracic surgeons are increasingly aligned on the importance of early intervention. In the context of lung cancer, "oligometastatic" status is often a critical juncture. The eBook features expert discourse on how surgery and radiotherapy can be used to treat limited spread to the brain or contralateral lung, potentially extending survival by years rather than months.
Renal Cell Carcinoma: Focal Therapy Strategies
Renal cell carcinoma (RCC) often presents with a unique pattern of metastasis. Unlike aggressive, rapidly proliferating cancers, RCC metastases can sometimes be managed with focal therapies—such as cryoablation or radiofrequency ablation—when surgery is not an option. This "narrative review" approach emphasizes that, for the renal patient, local control is often the key to delaying the need for systemic, toxic immunotherapy.
Breast Cancer: Stereotactic Radiotherapy
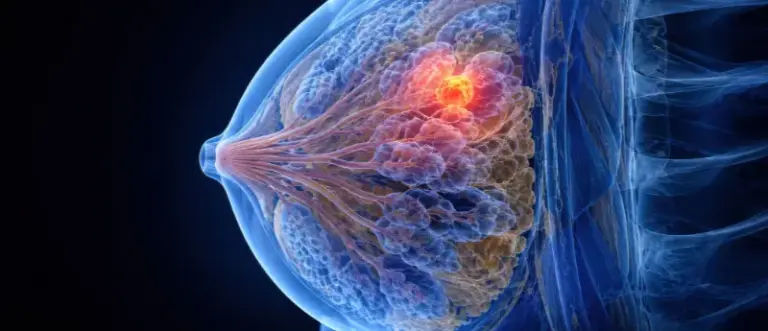
In breast cancer, the role of stereotactic radiotherapy is gaining traction for patients who have developed isolated metastases in the bone or liver. By controlling these lesions, clinicians can maintain the patient on their current systemic therapy (such as hormone therapy) for a longer duration, avoiding the need to cycle through more aggressive, later-line chemotherapies.
Economic Evaluation: The Case for Value-Based Care
One of the most compelling chapters in the current discourse is the economic argument. Critics often point to the high upfront costs of stereotactic technologies. However, a systematic review featured in the research demonstrates a different reality.
When evaluating the cost-effectiveness of SRS and SABR, the analysis shifts from the cost of the procedure to the "cost of the patient journey." By successfully managing oligometastases, clinicians can:
- Delay Systemic Therapy: Postponing the need for expensive, long-term immunotherapy or chemotherapy.
- Reduce Hospitalizations: Minimizing complications related to uncontrolled metastatic growth.
- Improve Quality of Life: Allowing patients to return to work and daily activities, which carries a significant societal economic benefit.
The data suggests that while the technology is sophisticated and carries an initial premium, it provides high-value care by potentially "buying time" for patients and preventing the high costs associated with end-of-life systemic crisis management.
Official Responses and Clinical Implications
Leading oncology organizations, including the American Society for Radiation Oncology (ASTRO) and the European Society for Radiotherapy and Oncology (ESTRO), have begun issuing consensus statements on the management of oligometastatic disease.
The Shift in Multidisciplinary Care
The primary implication of these findings is the necessity of the Multidisciplinary Tumor Board (MTB). The management of OMD cannot be handled by a single specialist. It requires a synergy between:
- Medical Oncologists: To manage systemic disease and determine if the patient is a candidate for local treatment.
- Radiation Oncologists: To deliver the precise, ablative doses required for local control.
- Radiologists/Nuclear Medicine Physicians: To identify the precise extent of the disease using high-sensitivity imaging.
- Surgeons: To determine if surgical resection offers a better long-term outcome than radiation.
Moving Forward
The medical community is now moving toward a more nuanced classification system. It is no longer enough to label a patient as "Stage IV." Future protocols will likely require a "molecular subtyping" of the oligometastatic state—determining which patients are likely to respond to local therapy versus those whose genetic profile suggests rapid, widespread progression.
Conclusion: A New Era of Hope
The move toward curative intent for oligometastatic disease represents one of the most significant advancements in modern oncology. It challenges the fatalistic view of metastatic cancer and replaces it with a strategy of precise, localized intervention.
As the perspectives outlined in The Oligometastatic Frontier suggest, the "shared promise" of this field lies in our ability to distinguish between patients who require systemic management and those for whom local intervention can change the course of their lives. While the field remains complex and site-specific, the integration of economic analysis, technological precision, and surgical/radiological expertise is paving the way for a future where Stage IV cancer is no longer an automatic terminal diagnosis, but a condition that can be managed, contained, and—for an increasing number of patients—conquered.
Summary of Resource Highlights
- Podcast Insight: A deep dive into the practical application of stereotactic radiotherapy for breast cancer patients, focusing on patient selection and treatment timing.
- Thoracic Review: An investigation into the evolving role of pulmonologists and surgeons in the "oligometastatic" diagnostic pathway.
- Economic Analysis: A systematic review validating the cost-benefit ratio of high-tech radiotherapy platforms.
- Renal Focus: A narrative review on how focal therapy serves as a bridge for patients with limited renal cell carcinoma progression.
For clinicians and stakeholders, these resources serve as a blueprint for the next generation of cancer care—where precision replaces palliation, and local control serves as the cornerstone of survival.
About the Author