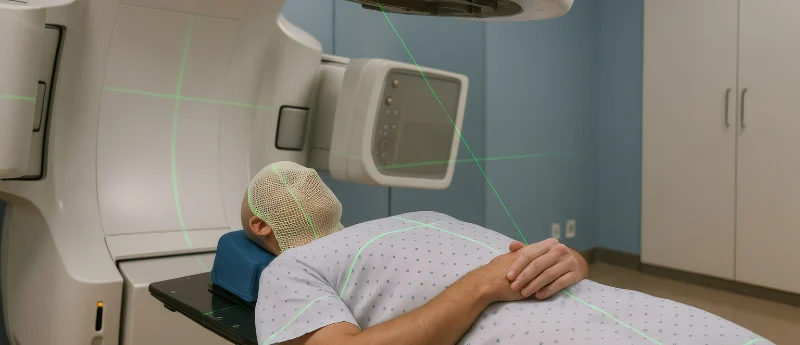
For decades, the standard of care for patients with small cell lung cancer (SCLC) and brain metastases has been whole-brain radiotherapy (WBRT). While stereotactic radiosurgery (SRS) has become the gold standard for managing brain metastases in most other solid tumor histologies due to its ability to spare neurocognitive function and maintain quality of life, patients with SCLC were historically excluded from the pivotal trials that cemented SRS as a preferred modality.
However, a landmark Phase III trial, NRG-CC009, has challenged this long-standing clinical dogma. Presented during the Plenary Session of the 2026 American Society for Radiation Oncology (ASTRO) Annual Meeting in Boston, the results suggest that while SRS may not offer the anticipated neurocognitive protection over hippocampal-avoidant WBRT (HA-WBRT), it provides a statistically significant survival benefit that could fundamentally alter how oncologists approach brain-metastasized SCLC.
Main Facts: A New Frontier for SCLC Management
The NRG-CC009 study sought to address a critical knowledge gap: whether SRS could serve as a safer, more effective alternative to HA-WBRT with memantine in patients diagnosed with SCLC and brain metastases. The trial randomized 151 eligible patients in a 1:1 ratio, comparing SRS directly against HA-WBRT with memantine.
While the primary endpoint—time to neurocognitive failure—was not met, the trial yielded a surprise finding that has sent ripples through the oncology community: a significant improvement in overall survival (OS) for those treated with SRS. Median survival for the SRS cohort reached 17.4 months, nearly doubling the 8.6-month survival observed in the HA-WBRT arm.
Perhaps most importantly, the trial debunked the long-held fear that SRS would lead to widespread, uncontrollable intracranial progression. The study demonstrated that intracranial disease control was comparable between the two arms, providing clinicians with the necessary evidence to reconsider SRS as a viable, front-line standard of care.
Chronology of the NRG-CC009 Trial
The path to these results was meticulous, spanning several years of rigorous clinical investigation supported by the National Cancer Institute (NCI).
- Trial Design and Recruitment: The study was designed to enroll patients across multiple centers, stratifying them by their disease-specific graded prognostic assessment (GPA) scores and the total number of brain metastases. The goal was to ensure a diverse cohort that accurately reflected the clinical reality of SCLC brain involvement.
- The Enrollment Phase: Over the course of the study, 151 patients were enrolled. The baseline characteristics of the study population were well-balanced, with a median of two brain metastases per patient, though the range was wide—spanning from one to as many as 26 lesions.
- Data Collection and Monitoring: The trial utilized a rigorous monitoring schedule, tracking neurocognitive failure as the primary metric, with secondary endpoints including overall survival, intracranial disease progression, and the incidence of adverse events.
- The 2026 Plenary Presentation: The culmination of this research occurred in Boston at the 2026 ASTRO Annual Meeting, where the lead investigators unveiled the data that would prompt a re-evaluation of the standard of care for this patient population.
Supporting Data: Dissecting the Findings
The trial’s statistical power was robust. With 91 documented events, the study possessed 85% power to detect a 17% absolute reduction in neurocognitive failure between the two treatment arms. Despite this power, the results showed no significant difference in neurocognitive outcomes (p=0.66). The adjusted hazard ratio (HR) for the SRS arm was 0.83 (95% CI, 0.53–1.28; p=0.39).
The Survival Advantage
The most striking figure to emerge from the trial was the survival disparity. The adjusted hazard ratio for the SRS arm was 0.60 (95% CI, 0.39–0.91; p=0.016), favoring SRS over HA-WBRT. This 0.60 HR indicates a profound reduction in the risk of death, marking a significant advancement in therapeutic outcomes for a condition often associated with a grim prognosis.
Safety and Intracranial Control
A primary concern regarding SRS in SCLC has been the potential for "distal" brain failure—the development of new metastases outside the treated areas. However, NRG-CC009 reported no statistically significant differences in intracranial progression between the SRS and HA-WBRT arms. Furthermore, there was no disparity in neurological mortality or treatment-related Grade 3–5 adverse events. This suggests that the survival benefit of SRS does not come at the cost of increased toxicity or compromised intracranial disease control.
Official Responses: Insights from Lead Investigators
The researchers behind NRG-CC009 view these results as a watershed moment for patient-physician dialogue.
Chad Rusthoven, MD, of the University of Colorado Anschutz and the lead author of the abstract, addressed the persistent anxiety surrounding SRS:
"One of the fundamental concerns with upfront SRS alone for SCLC is that patients might develop diffuse CNS progression leading to worse neurologic and survival outcomes. However, that is not what we observed in NRG-CC009. Although there were no differences in neurocognitive failure, treatment with SRS was associated with superior overall survival compared to HA-WBRT. These findings support SRS as a reasonable standard of care option for patients with SCLC brain metastases."
Vinai Gondi, MD, of the Northwestern University Feinberg School of Medicine, the lead Principal Investigator of the trial, emphasized the practical utility of these findings for clinicians:
"NRG-CC009 provides results that will help physicians better counsel their patients on treatment approaches for SCLC brain metastases. The overall survival difference is an important factor to be discussed with patients."
The investigators agree that while neurocognitive preservation remains an important goal, the objective survival gain seen with SRS provides a compelling argument for its inclusion in the treatment algorithm.
Implications: A Shift in Clinical Practice
The implications of NRG-CC009 are immediate and far-reaching. By providing evidence that SRS is not only safe but potentially superior in terms of survival, the trial invites a transition away from the "WBRT-by-default" approach for SCLC patients with brain metastases.
Impact on Patient Counseling
The data empowers oncologists to have more nuanced conversations with their patients. When discussing treatment, the potential for an extended survival benefit—as demonstrated by the 17.4-month median in the SRS group—must now be weighed alongside the risks and benefits of radiation modalities. For patients and their families, the shift represents hope for both longevity and a potential reduction in the side effects associated with whole-brain irradiation.
Future Research Directions
While NRG-CC009 has provided a vital piece of the puzzle, questions remain. Researchers are now looking at how to integrate these findings with emerging systemic therapies, such as immunotherapy, which have begun to change the landscape of SCLC treatment as a whole. The role of SRS in patients with high tumor burdens or specific genetic profiles will likely be the subject of subsequent studies.
Financial and Logistical Considerations
Beyond the clinical metrics, the trial’s reliance on NCI-supported grants (including U10CA180822 and others) underscores the importance of large-scale, federally funded clinical trials. As the medical community digests these results, institutions will need to evaluate the accessibility and implementation of SRS, ensuring that patients across different geographic and economic regions can benefit from these refined treatment standards.
Conclusion
The NRG-CC009 trial stands as a testament to the necessity of testing entrenched practices. By challenging the exclusion of SCLC patients from SRS trials, the investigators have uncovered a survival benefit that may redefine the standard of care for a challenging disease.
While the trial did not reach its primary endpoint regarding neurocognitive failure, the unexpected, statistically significant improvement in overall survival represents a major win for patients. As the oncology community moves forward, the results of NRG-CC009 serve as a reminder that the best path to progress is often found by questioning the status quo and letting clinical data, rather than historical assumption, guide the way toward better patient outcomes.
Disclaimer: This project was supported by various grants from the National Cancer Institute (NCI). The content is the responsibility of the authors and does not necessarily represent the official views of the National Institutes of Health.
About the Author