Medicaid, the cornerstone of the American public health safety net, has long been defined by a unique tension: the balance between federal standardization and state-level innovation. At the heart of this balance lies the Section 1115 demonstration waiver. These authorities grant the Secretary of the Department of Health and Human Services (HHS) the power to waive certain federal Medicaid requirements, allowing states to experiment with delivery models that "promote the objectives" of the program.
However, as the political winds shift in Washington, so too does the interpretation of what those "objectives" entail. The current landscape is defined by a distinct transition: from the expansive, social-needs-focused initiatives of the Biden administration to a more restrictive, work-focused agenda under the second Trump administration.
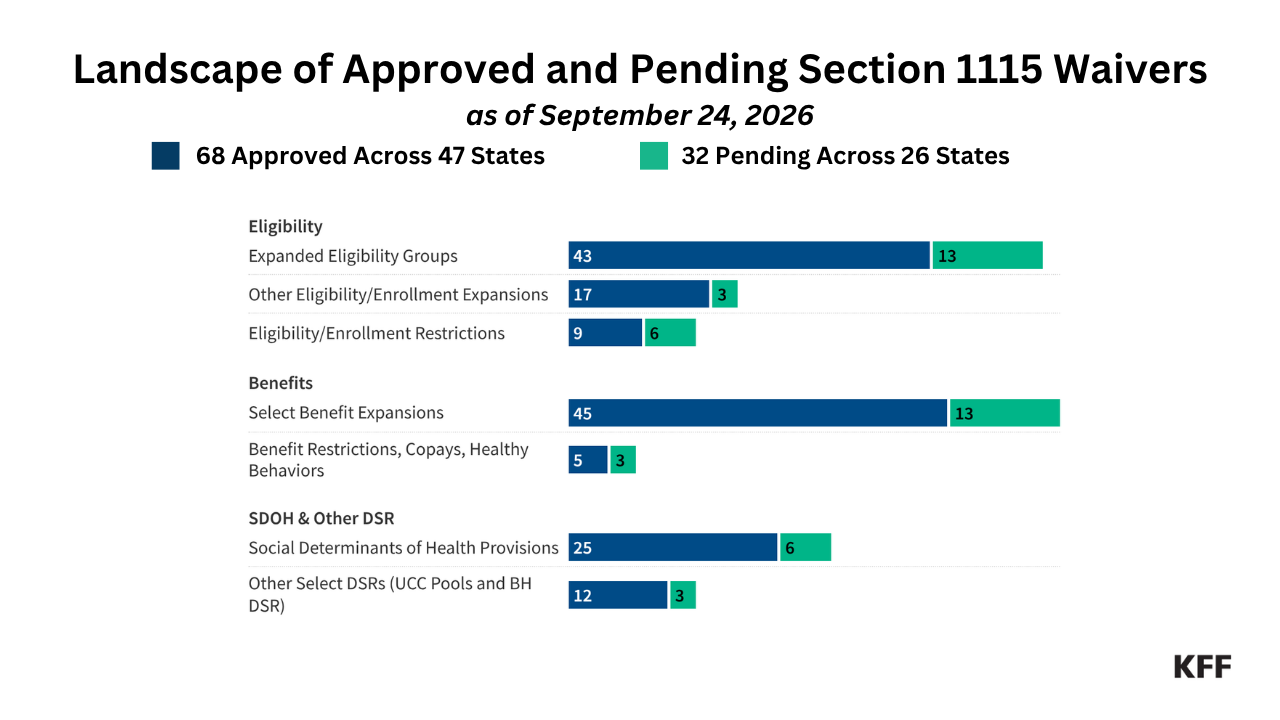
The Mechanism of Flexibility: What are Section 1115 Waivers?
Section 1115 waivers are not merely administrative tools; they are the primary vehicles through which states reshape the scope, eligibility, and delivery of health coverage for millions of low-income Americans. By allowing states to bypass statutory mandates—provided the programs are "budget neutral" to the federal government—these waivers have become the ultimate barometer of national health policy.
Whether it is addressing the social determinants of health (SDOH), implementing complex work requirements, or managing the transition of incarcerated individuals back into society, these waivers represent the laboratory of American democracy. Yet, because these approvals are subject to the executive discretion of the HHS Secretary, they are inherently fragile, vulnerable to reversal the moment a new administration takes the oath of office.
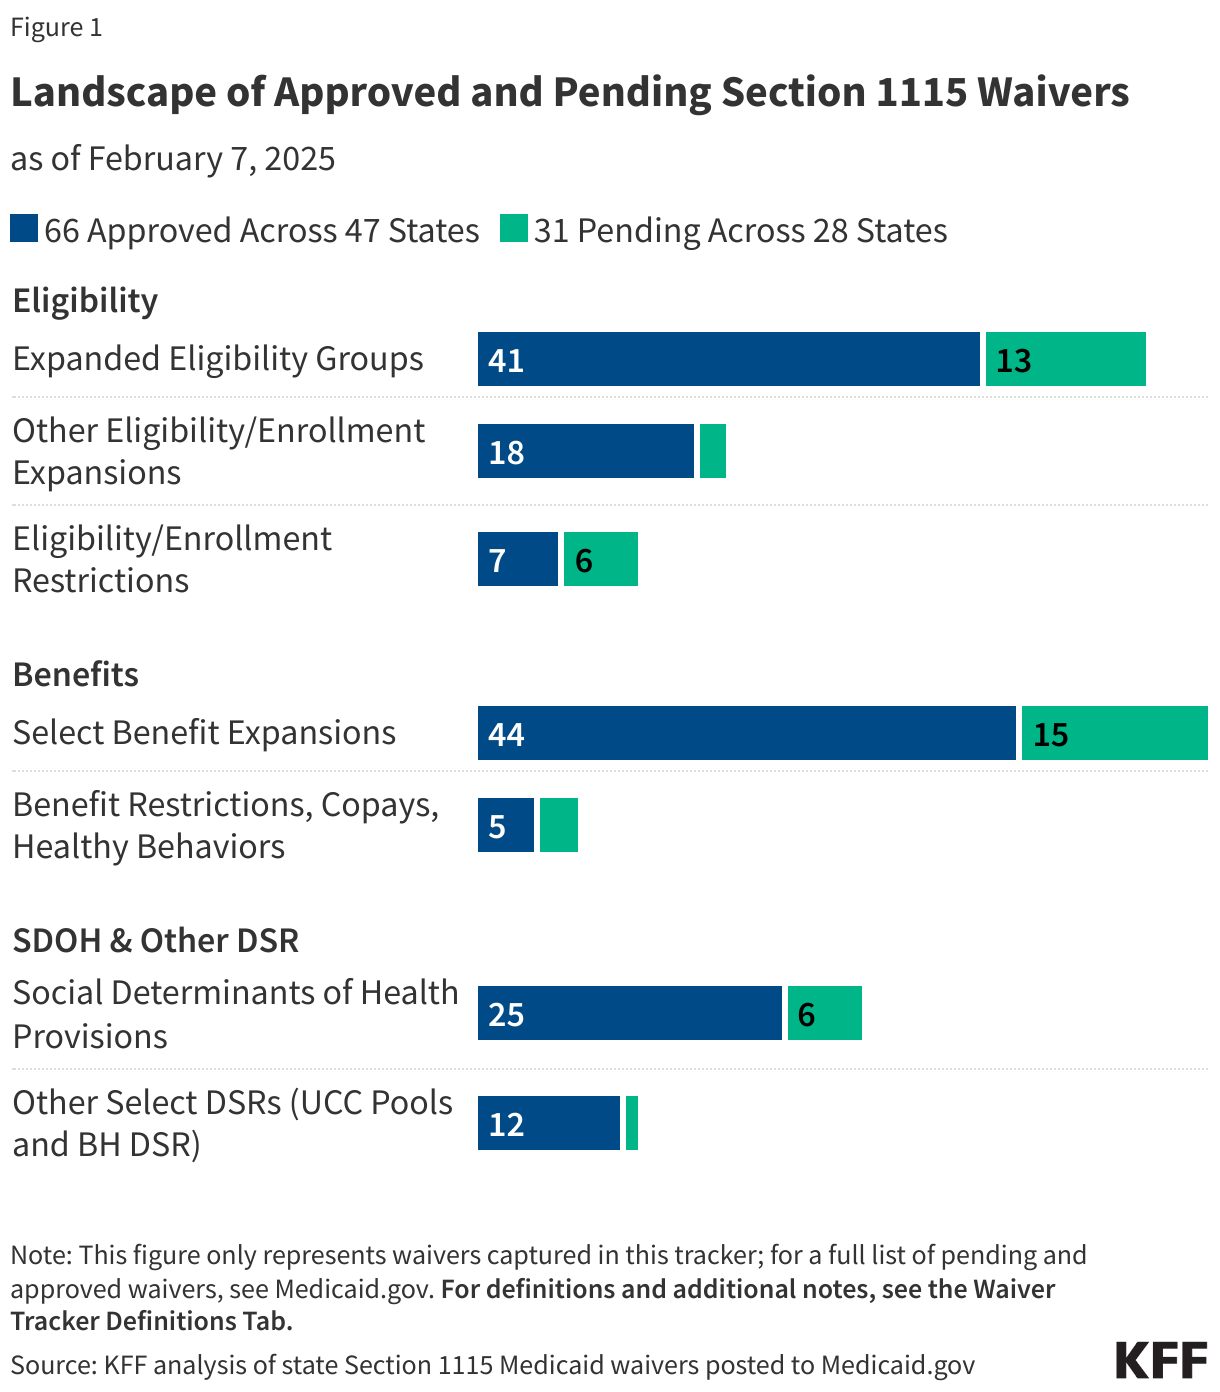
Chronology of Change: A Policy Pivot
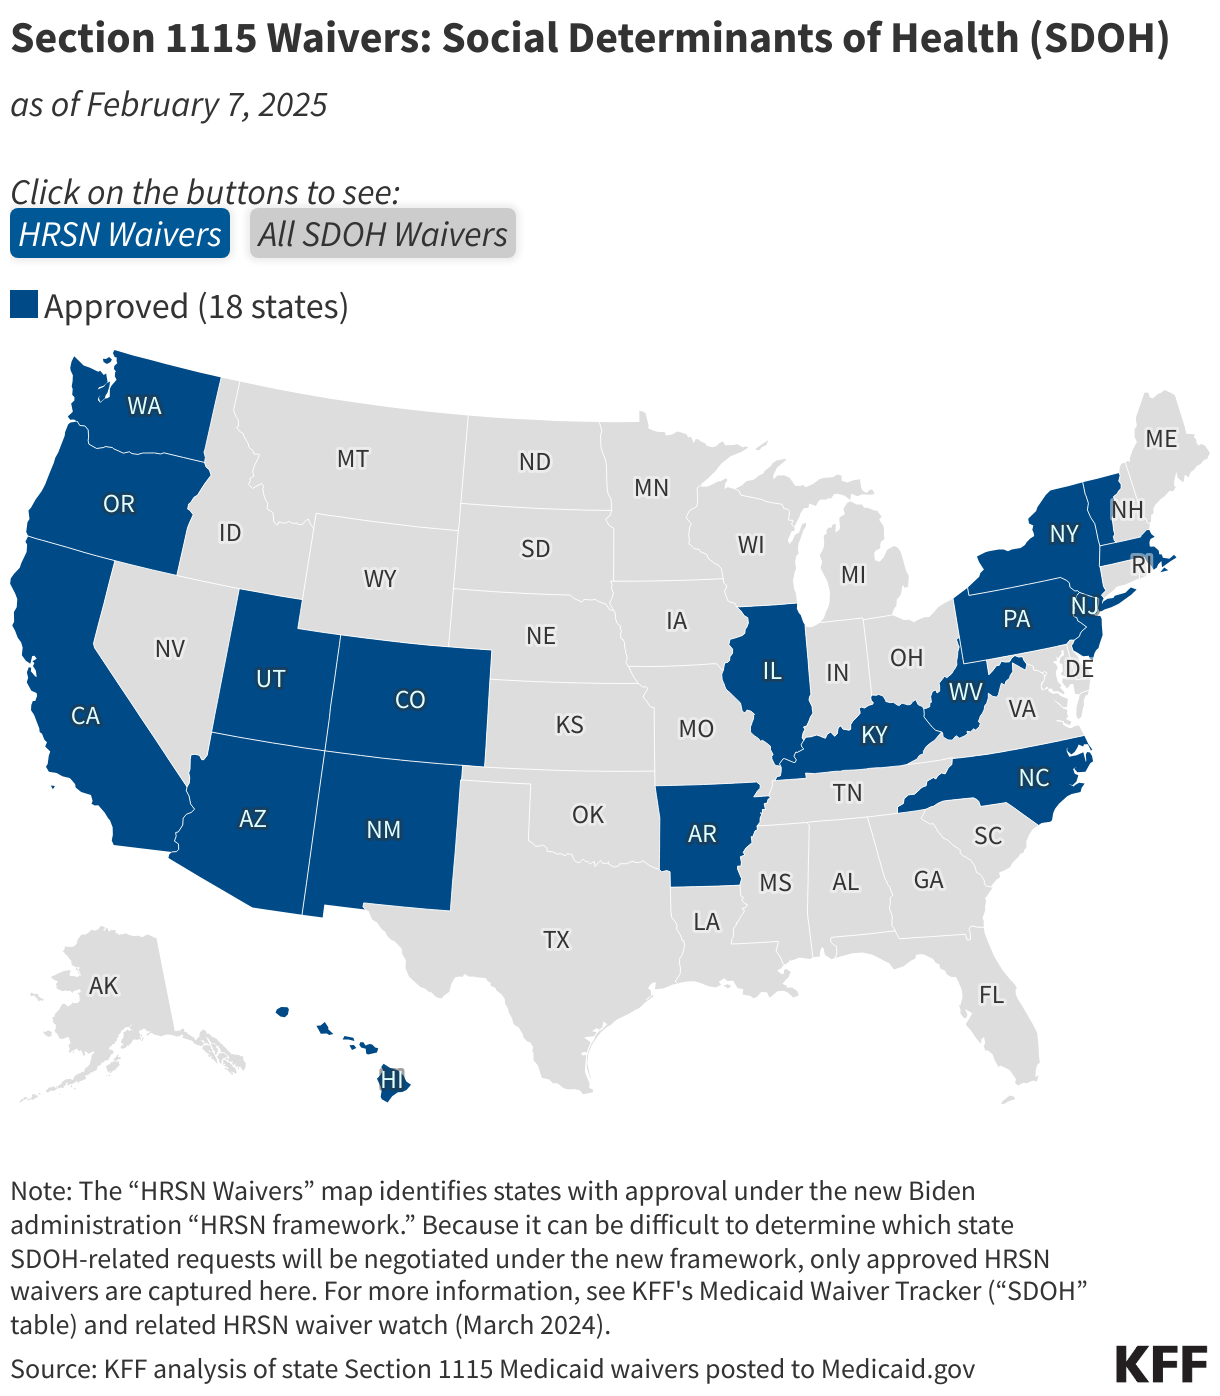
The last several years have seen a rapid succession of policy pivots. Under the Biden-Harris administration, the focus was heavily weighted toward "Health-Related Social Needs" (HRSN). CMS encouraged states to use 1115 authority to fund housing supports, nutritional services, and community-based interventions designed to address the upstream causes of poor health.
By contrast, the landscape changed significantly following the inauguration of the second Trump administration. In early 2025, the new leadership at CMS began a systematic unwinding of several key Biden-era priorities:
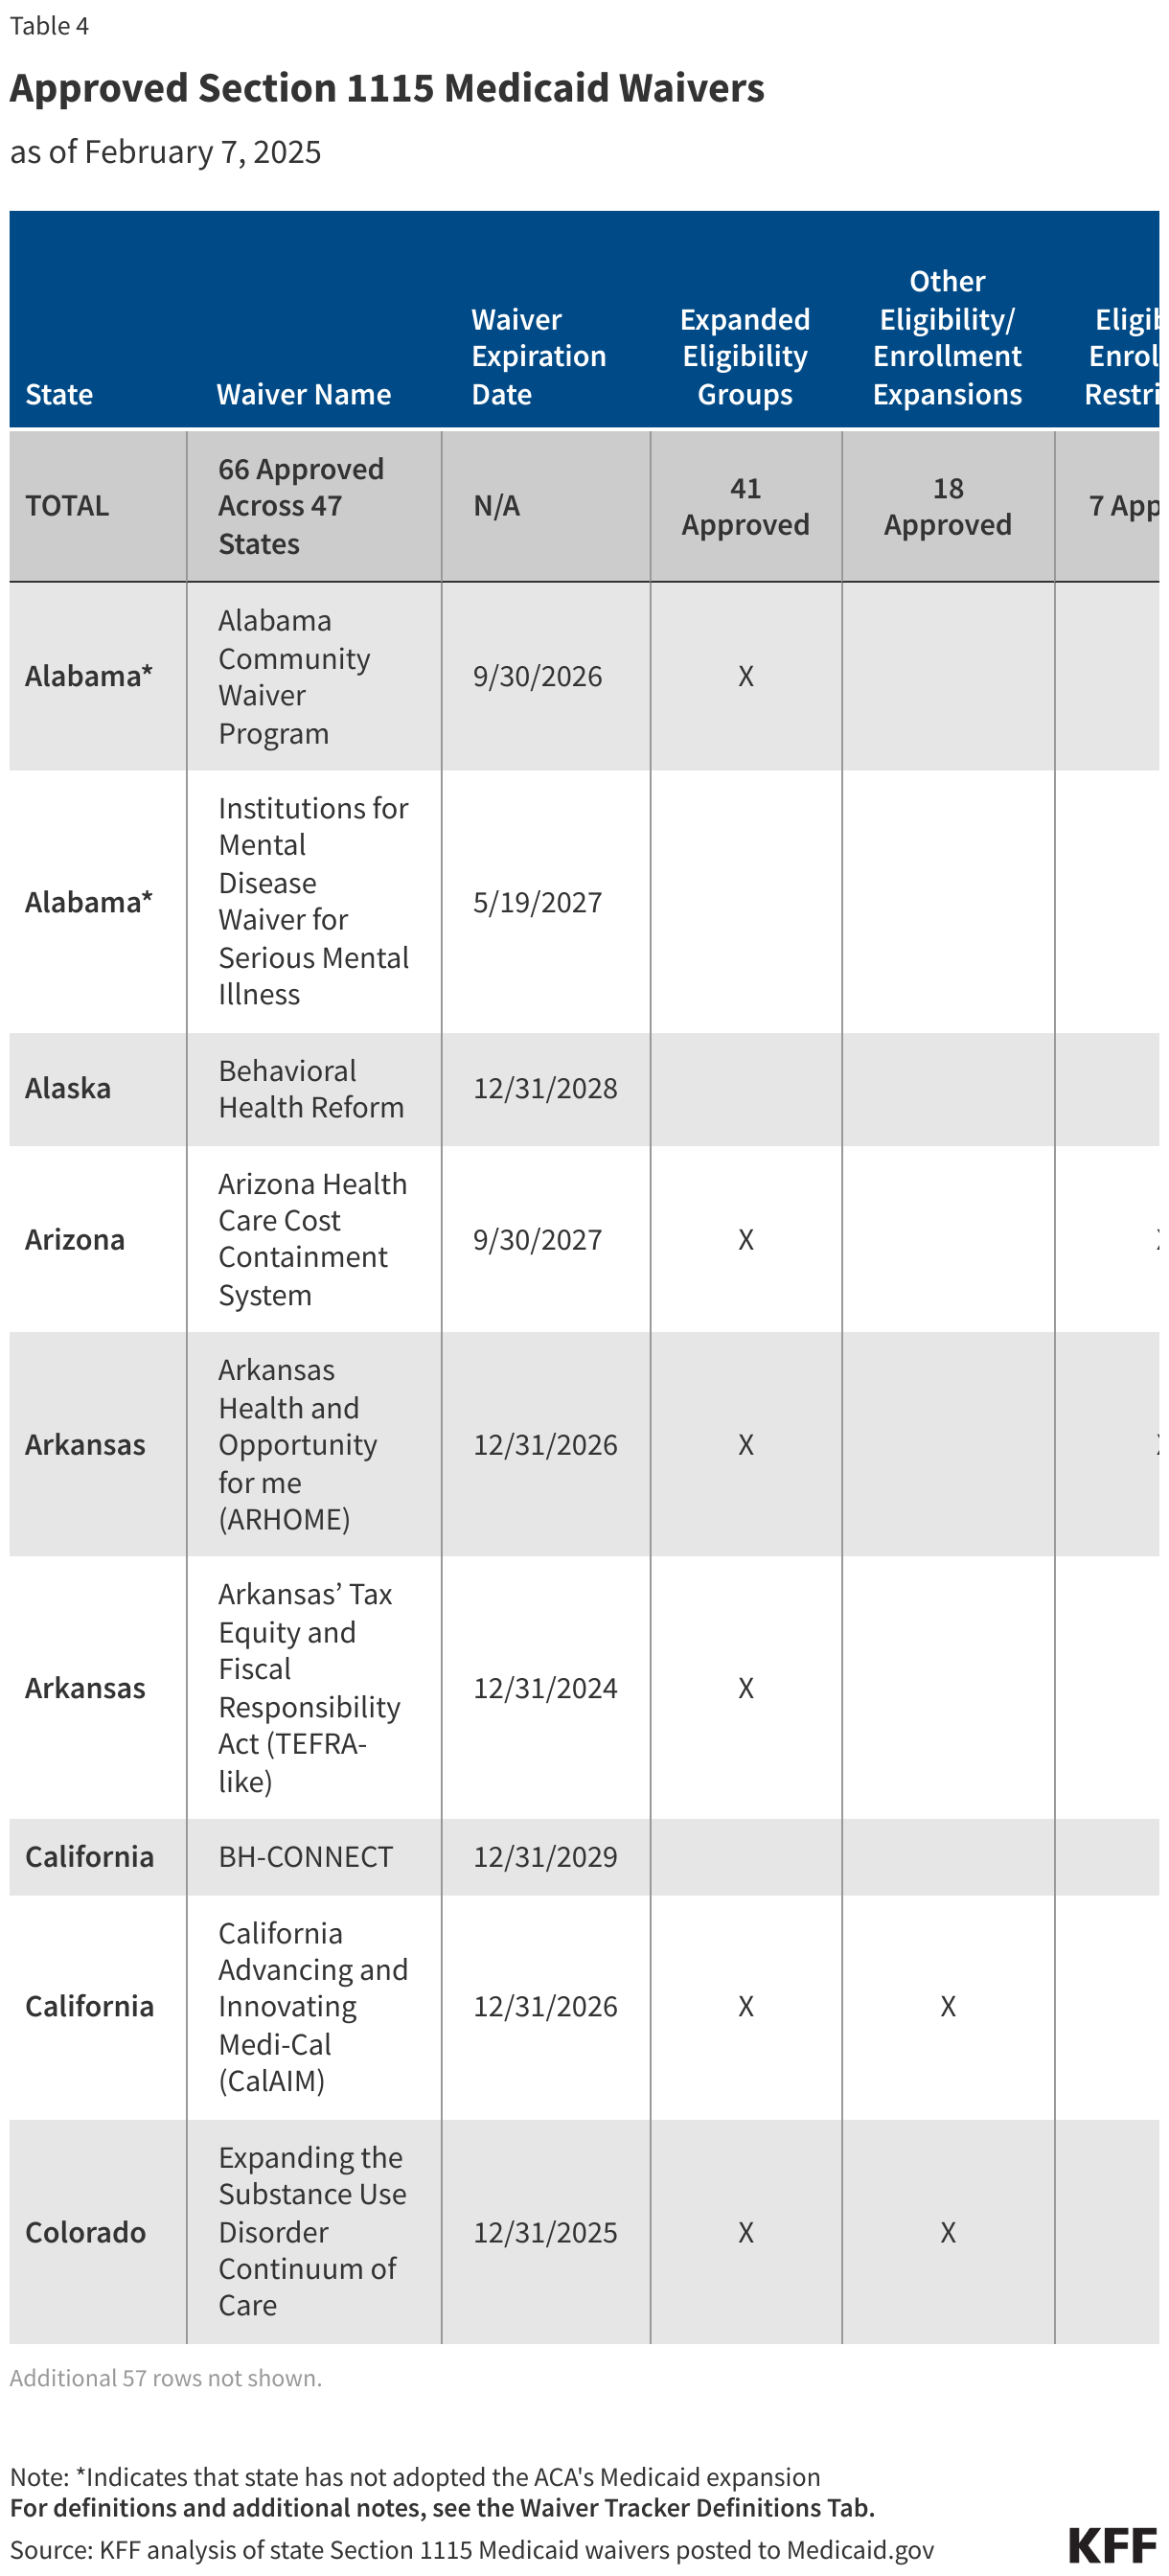
- March 2025: The administration rescinded the guidance that had facilitated broad HRSN waivers. While existing programs were not immediately nullified, the federal government signaled a pivot toward a strict "case-by-case" review process, effectively chilling new investment in social determinants.
- April 2025: CMS announced the phase-out of federal funding for "Designated State Health Programs" (DSHP), which had served as a financial backbone for many state-level innovation efforts.
- July 2025: The administration issued guidance indicating it would no longer approve or extend continuous eligibility waivers for children or adults—a move designed to curb the reach of enrollment protections that were once viewed as essential for maintaining coverage stability.
- July 2025: A further announcement marked the end of federal support for initiatives aimed at strengthening the Medicaid workforce across primary care, behavioral health, and home-based services.
The Return of Work Requirements
Perhaps the most significant shift in the current policy environment is the renewed emphasis on work requirements. The 2025 reconciliation law serves as the legislative anchor for this change, mandating that states condition Medicaid eligibility for adults in the Affordable Care Act (ACA) expansion group on meeting specific work-related criteria by January 1, 2027.
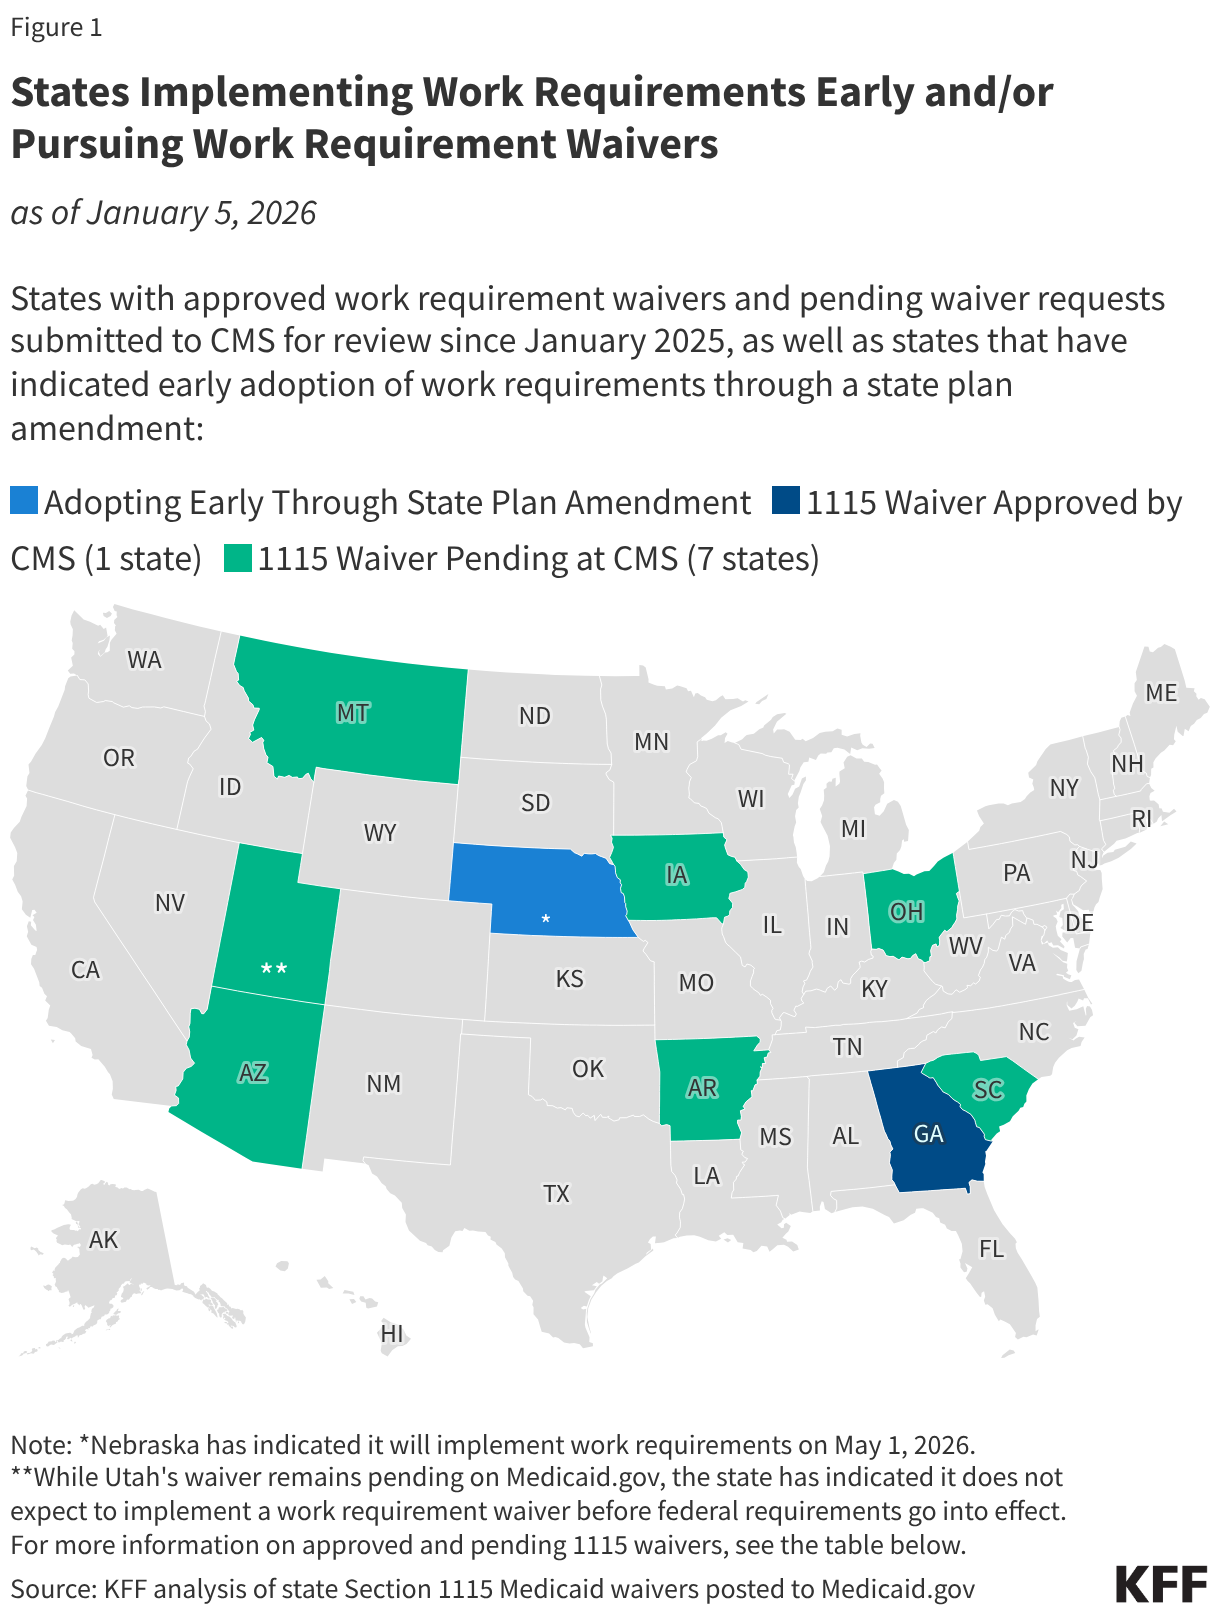
While federal law sets the deadline, states are already racing to implement these requirements early via State Plan Amendments (SPAs).
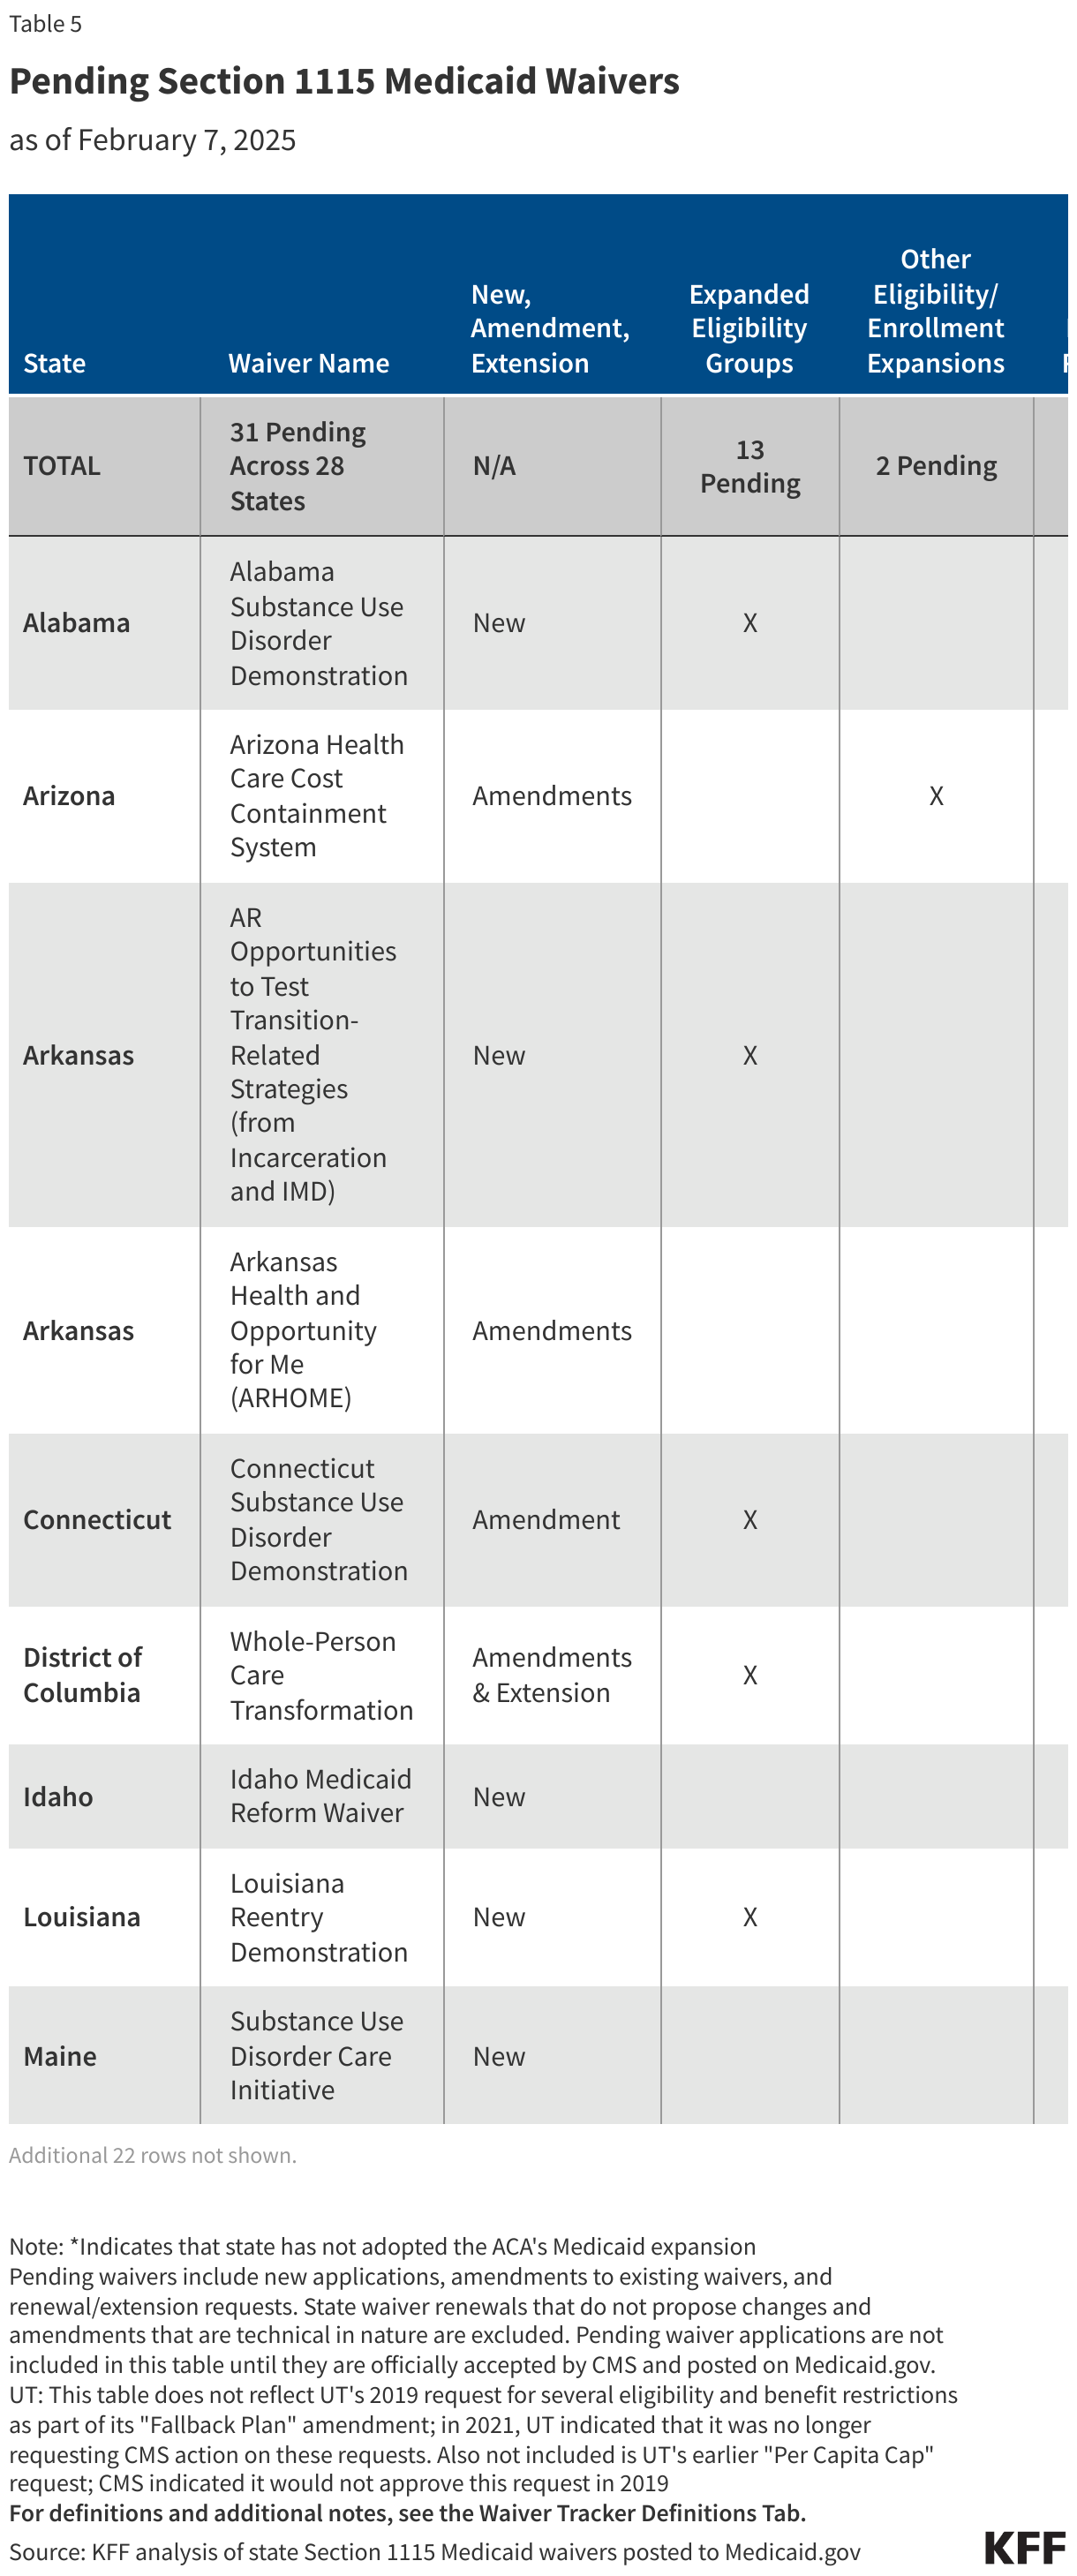
- Nebraska has taken the lead, announcing that it will begin enforcing federal work requirements starting May 1, 2026.
- Montana (July 1, 2026) and Iowa (December 1, 2026) are following suit with early implementation plans.
- Arkansas has adopted a "soft landing" approach, announcing a July 2026 launch that will focus on compliance without immediate disenrollment until the federal deadline of January 2027.
Georgia remains a unique case study in this arena. Having successfully navigated litigation regarding its work requirement waiver during the previous administration, it stands as the only state currently operating such a program under 1115 authority. However, even Georgia must pivot; its current waiver expires at the end of 2026, forcing the state to align with the new federal mandate by the start of 2027.
Supporting Data: Mapping the Trends
The current data landscape illustrates a stark dichotomy between the past three years and the emerging trajectory.
Social Determinants of Health (SDOH)
The Biden-era HRSN framework allowed states to target non-clinical barriers to health. The data shows that while many states were granted these approvals, the current administration’s decision to move to "case-by-case" review means that the pipeline for these programs is effectively stalled. States that were hoping to use federal Medicaid funds to address homelessness or food insecurity now face a significantly higher bar for approval.
Medicaid Pre-release Coverage
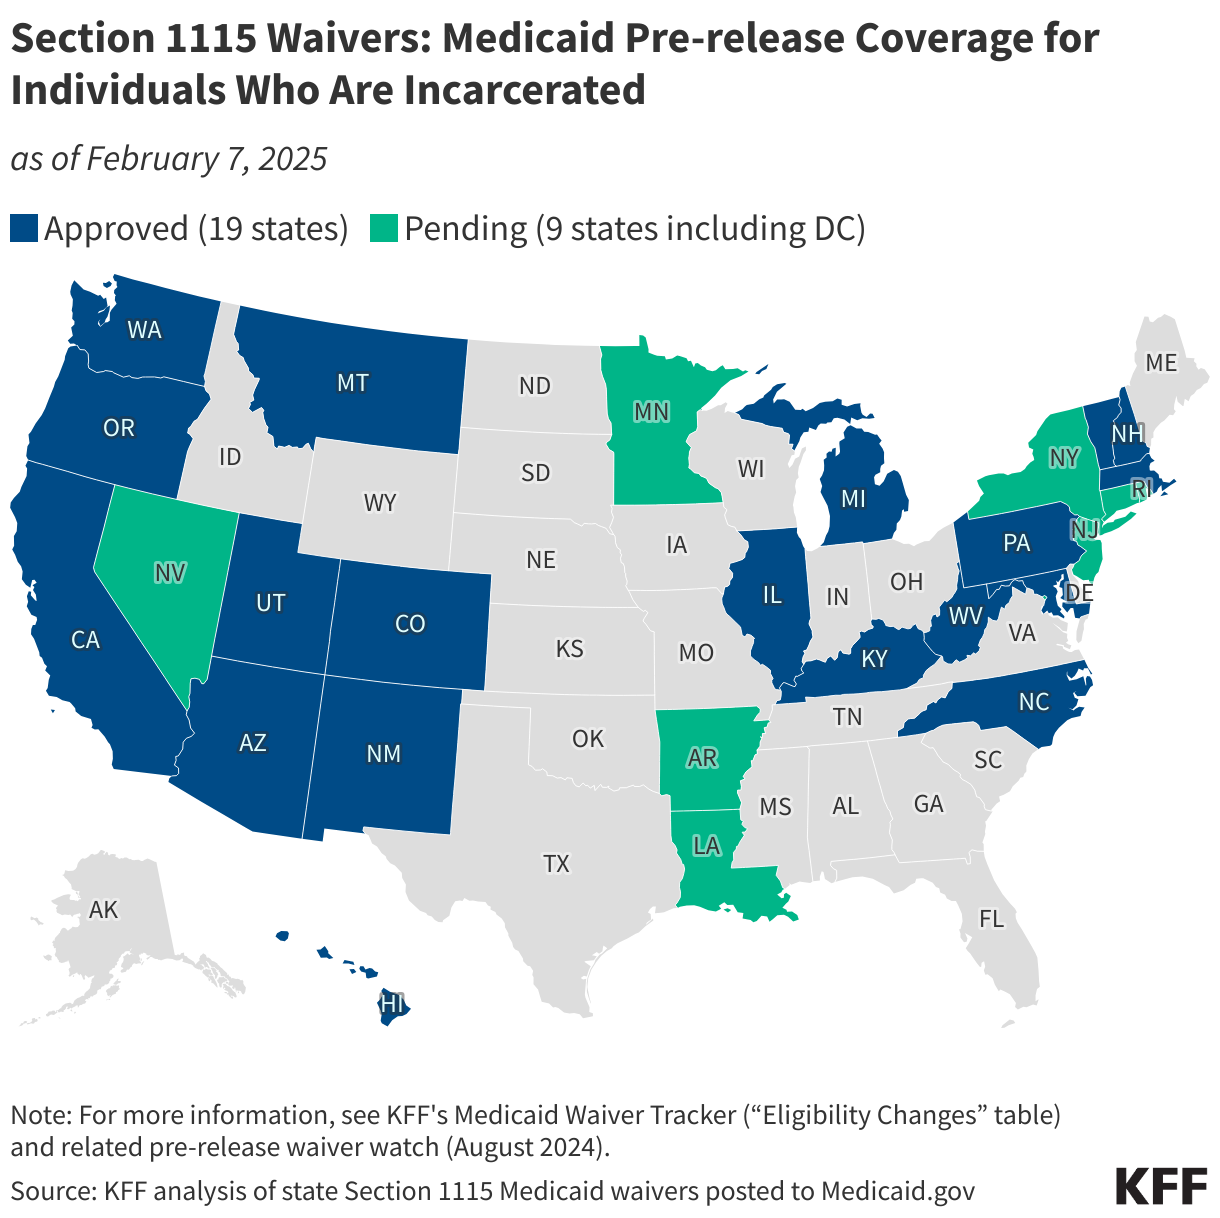
One of the most bipartisan successes of recent years has been the movement to provide Medicaid coverage to individuals shortly before they are released from incarceration. Nineteen states received approval under the Biden administration for these reentry services. In September 2026, the Trump administration signaled a potential continuation of this trend by approving four additional reentry waivers, though it also noted that new, updated guidance would be forthcoming. This suggests that while other social programs are being cut, reentry services may retain some level of federal support due to their potential to reduce recidivism—a goal that resonates across the political spectrum.

Continuous Eligibility for Children
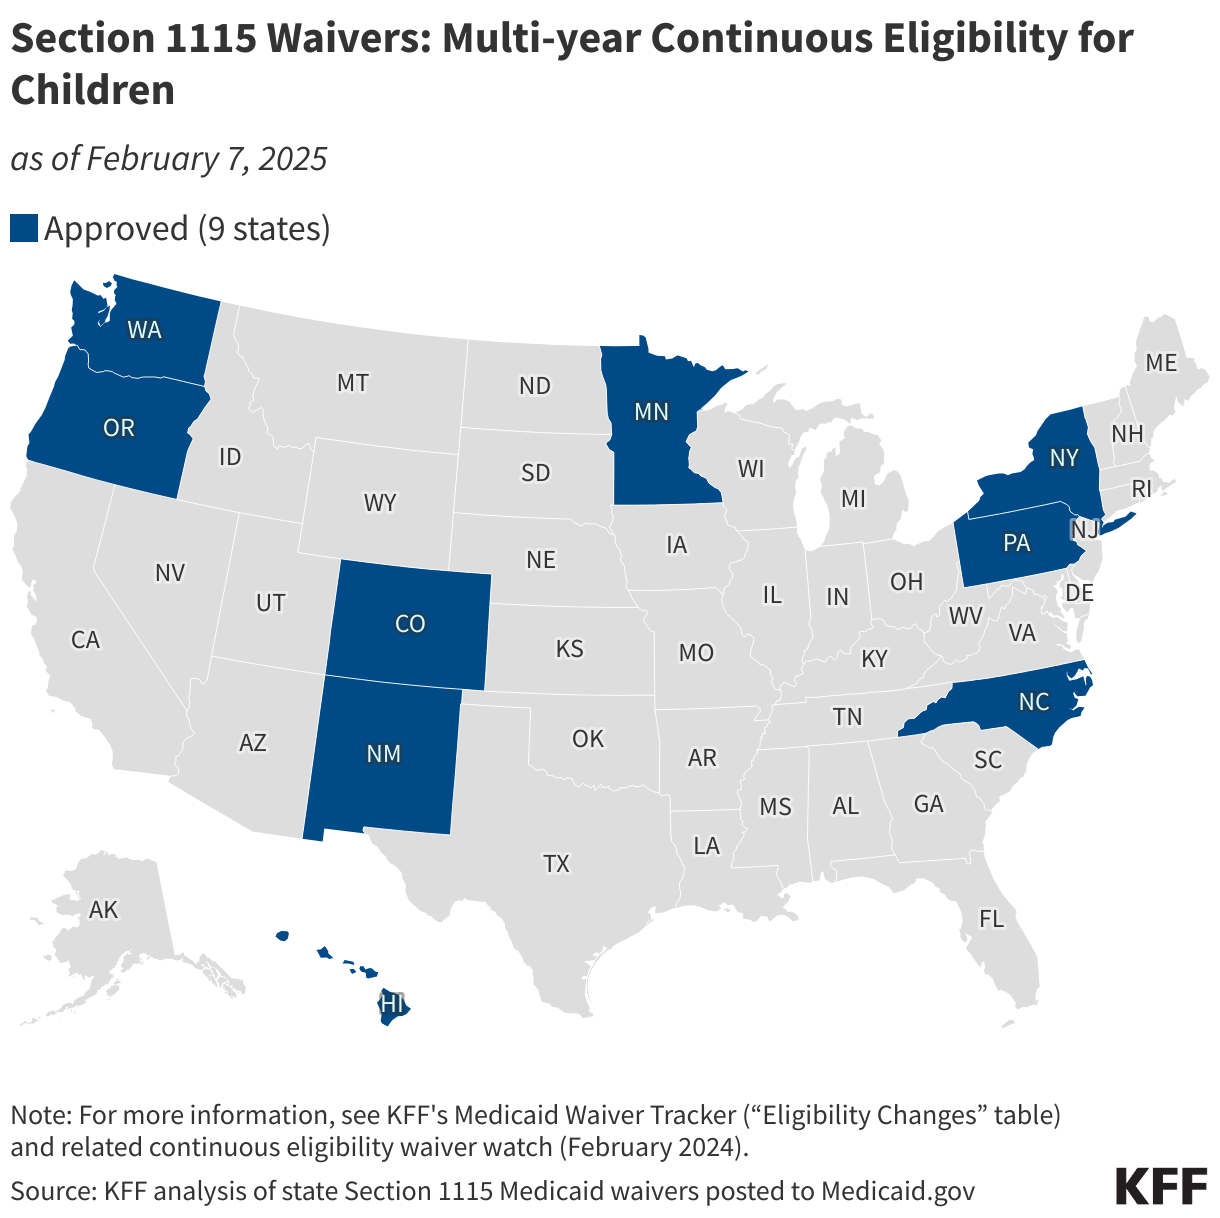
The move toward multi-year continuous eligibility for children was designed to reduce "churn," where children lose coverage due to administrative hurdles and are forced to re-apply. Despite evidence that these policies improve health outcomes and reduce administrative costs, the current administration’s July 2025 guidance creates a hard stop, effectively ending the expansion of these protections.
Official Responses and Administrative Stance
The official position of the current administration, as outlined in recent CMS communications, emphasizes "fiscal responsibility" and a return to the "core purposes" of Medicaid. Officials argue that by phasing out DSHP funding and continuous eligibility waivers, they are ensuring that the program remains sustainable and focused on direct medical service delivery rather than broader social support.
Conversely, public health advocates and state Medicaid directors in more liberal-leaning states have expressed concern. They argue that the removal of SDOH and continuous eligibility supports will lead to increased health disparities, higher long-term costs due to unmanaged chronic conditions, and an administrative burden on states that are forced to pivot their systems on short notice.
Implications for the Future of Medicaid
The implications of this shift are profound. By moving away from social determinants and continuous eligibility, the federal government is effectively narrowing the definition of what Medicaid "does."
1. The Financial Impact on States
States that relied on DSHP funding or federal matching for social support programs now face a fiscal cliff. Those that cannot cover these costs with state-only funds will likely have to terminate programs that have, in some cases, been operational for years.
2. The Health Equity Gap
The rescission of the HRSN guidance is expected to widen the gap in health outcomes for marginalized populations. Without targeted support for housing and nutrition, high-need Medicaid beneficiaries are at a higher risk of cycling through expensive emergency departments, undermining the very goals of "budget neutrality" that these waivers are supposed to achieve.
3. Increased Complexity for Beneficiaries
The push for early implementation of work requirements introduces significant complexity for the beneficiary population. The burden of proof for "exempt" status—or for meeting the required hours—often falls on the individual. Without the support of robust outreach and enrollment assistance, there is a substantial risk of unintended coverage loss among eligible individuals who struggle to navigate the new, more restrictive administrative requirements.
Conclusion
The Section 1115 waiver remains a powerful, if volatile, instrument. As it stands in late 2026, the program is undergoing a significant contraction in scope, characterized by a move toward traditional medical service focus and stricter work requirements. For states, the path forward requires agility. As the federal government transitions toward a more restrictive policy framework, the ability of states to innovate within the Medicaid program will increasingly depend on their capacity to secure "case-by-case" approvals and navigate the complexities of the new federal work mandate. The next few years will test whether these changes fulfill the promise of a more efficient system, or whether they fundamentally weaken the safety net for the nation’s most vulnerable.
About the Author