On May 1, 2026, Nebraska took a pioneering—and controversial—step into the national spotlight, becoming the first state in the union to enforce rigorous work requirements for Medicaid eligibility. This shift, spurred by the federal 2025 reconciliation law, signals a fundamental change in the philosophy of the American safety net. While the federal mandate requires states to implement these standards by January 1, 2027, Nebraska’s decision to fast-track the process has provided a critical, real-time laboratory for policymakers, healthcare advocates, and social scientists to observe the potential impacts of conditioning health coverage on employment.
The Chronology of Implementation
The road to Nebraska’s current policy began in the wake of the 2025 reconciliation budget bill, which codified new national standards for the ACA Medicaid expansion population and certain waiver program enrollees. Under this federal framework, states are required to mandate that non-elderly, non-disabled adults either engage in qualifying work activities or meet specific exclusion criteria to maintain their benefits.
Nebraska’s legislative and administrative path to implementation moved with notable speed:
- May 1, 2026: Nebraska officially commences the enforcement of work requirements, becoming the first state to do so ahead of the federal deadline.
- July 2026: The state begins processing renewals for existing enrollees under the new criteria.
- September 17, 2026: The Nebraska Medicaid Advisory Committee (MAC) meets to review the first wave of data, providing the public with its first glimpse into the policy’s impact on enrollment and application outcomes.
While the state has opted for a flexible, self-attestation-based verification process for the initial implementation phase, the federal government has already signaled that these allowances are temporary. By January 2028, federal rules will mandate more stringent documentation, marking a significant transition point in how beneficiaries will interact with the system.
The Verification Mechanism: A Hybrid Approach
Nebraska has implemented a "combination" verification model designed to balance administrative efficiency with the need for individual compliance. The state primarily utilizes existing electronic databases to verify employment status automatically. When the state’s data indicates that a beneficiary meets the work requirements, an approval notice is sent automatically.
However, for a significant portion of the population, the state lacks sufficient electronic data. In these instances, the state sends a formal notice requesting additional information. Beneficiaries are required to submit a "declaration form" within 30 days. This form allows individuals to attest to their qualifying activities—such as full-time or part-time employment, vocational training, or community service—or to claim an exclusion.
Hardship Exceptions
Recognizing that the labor market is not monolithic, Nebraska has adopted short-term hardship exceptions. These are critical for enrollees experiencing extenuating circumstances, including:
- Geographic Factors: Residing in counties with high unemployment rates.
- Environmental Crises: Being impacted by natural disasters.
- Medical Necessities: Being admitted to a hospital or nursing facility, or traveling extensively for specialized medical care for oneself or a dependent.
These exceptions serve as a vital, if narrow, safety valve intended to prevent the loss of coverage for those who are unable to work due to systemic or acute personal challenges.
Supporting Data: Early Outcomes and Trends
The data presented at the September 2026 Medicaid Advisory Committee meeting offers a nuanced, if incomplete, picture of the policy’s initial impact.
Application Outcomes (May–August 2026)
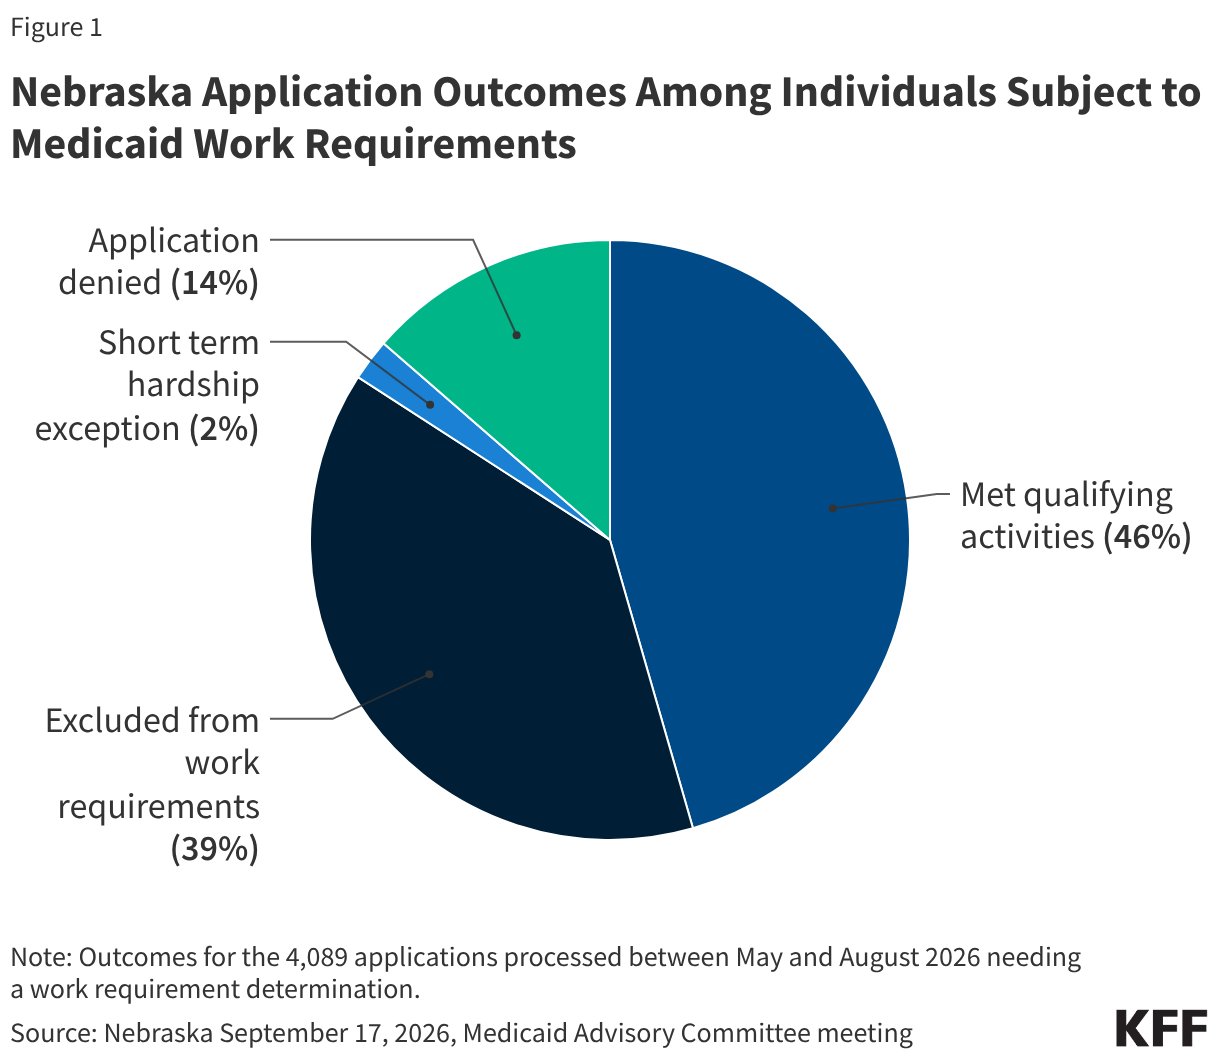
Between May and August 2026, the state processed 9,614 applications. After accounting for those not subject to the requirements and those denied for traditional reasons (such as income exceeding eligibility thresholds), the data focuses on 4,089 applications subject to the new mandate.
- The Success Rate: 86% of applicants were successfully enrolled, having met either the work requirements, exclusion criteria, or qualifying for a hardship exception.
- The Denial Rate: 14% of applicants saw their applications denied, triggering significant questions about the nature of these denials—specifically whether they stem from administrative hurdles or a genuine inability to meet the new criteria.
Renewal Outcomes (July–August 2026)
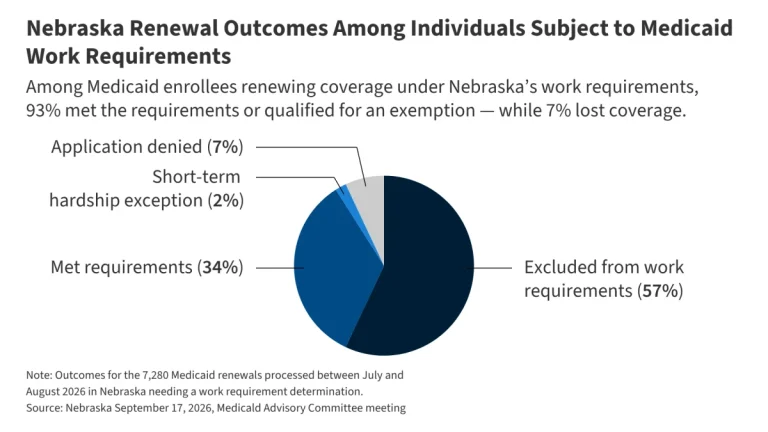
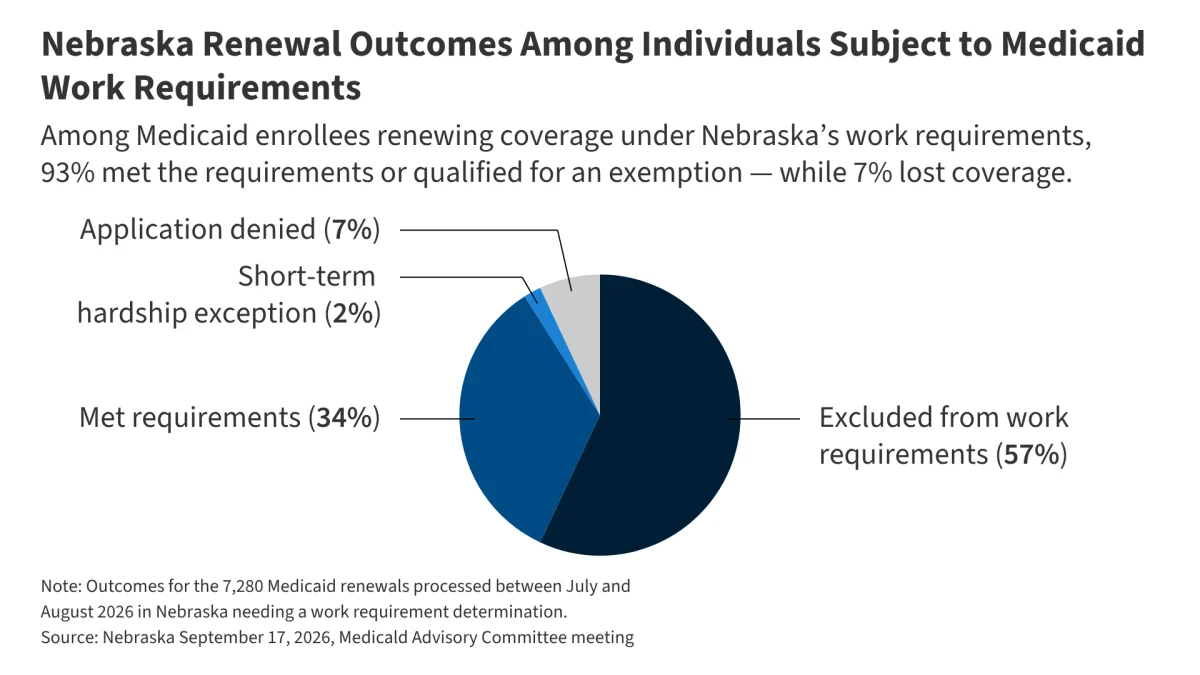
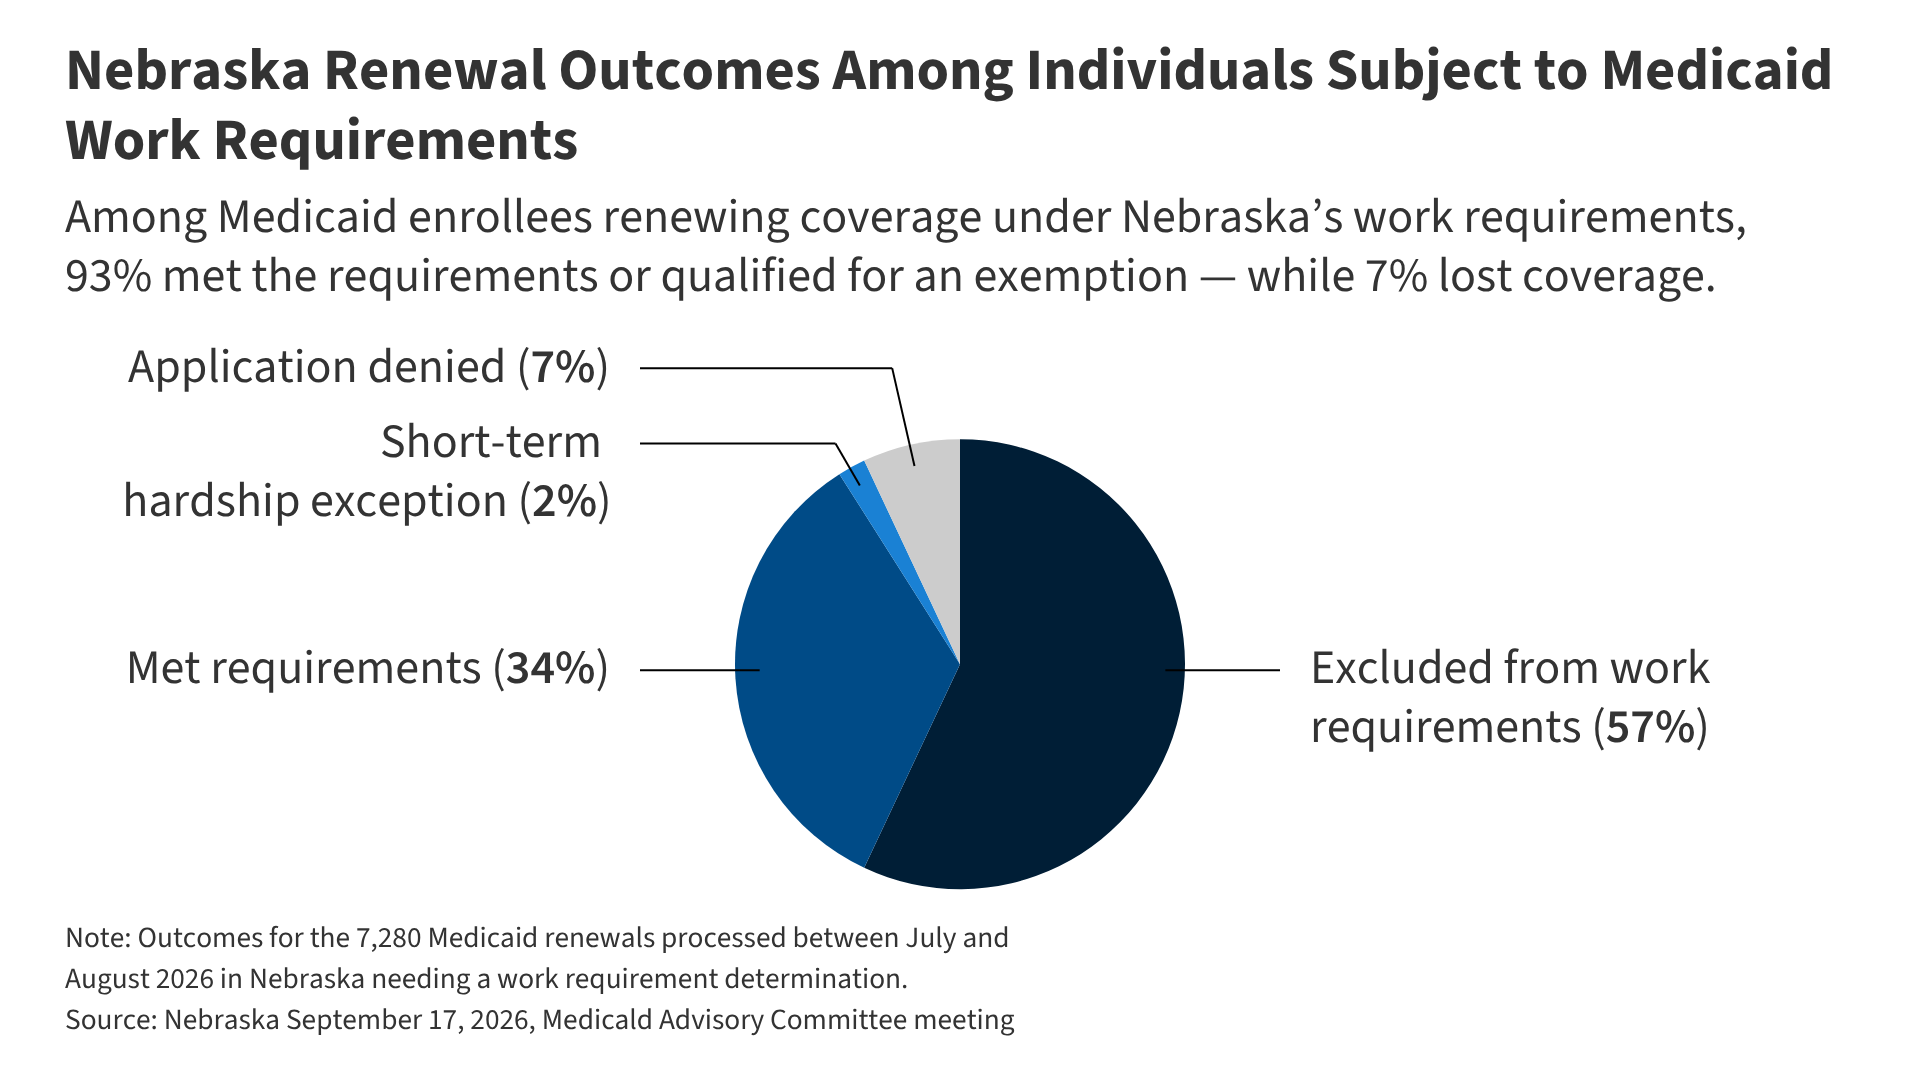
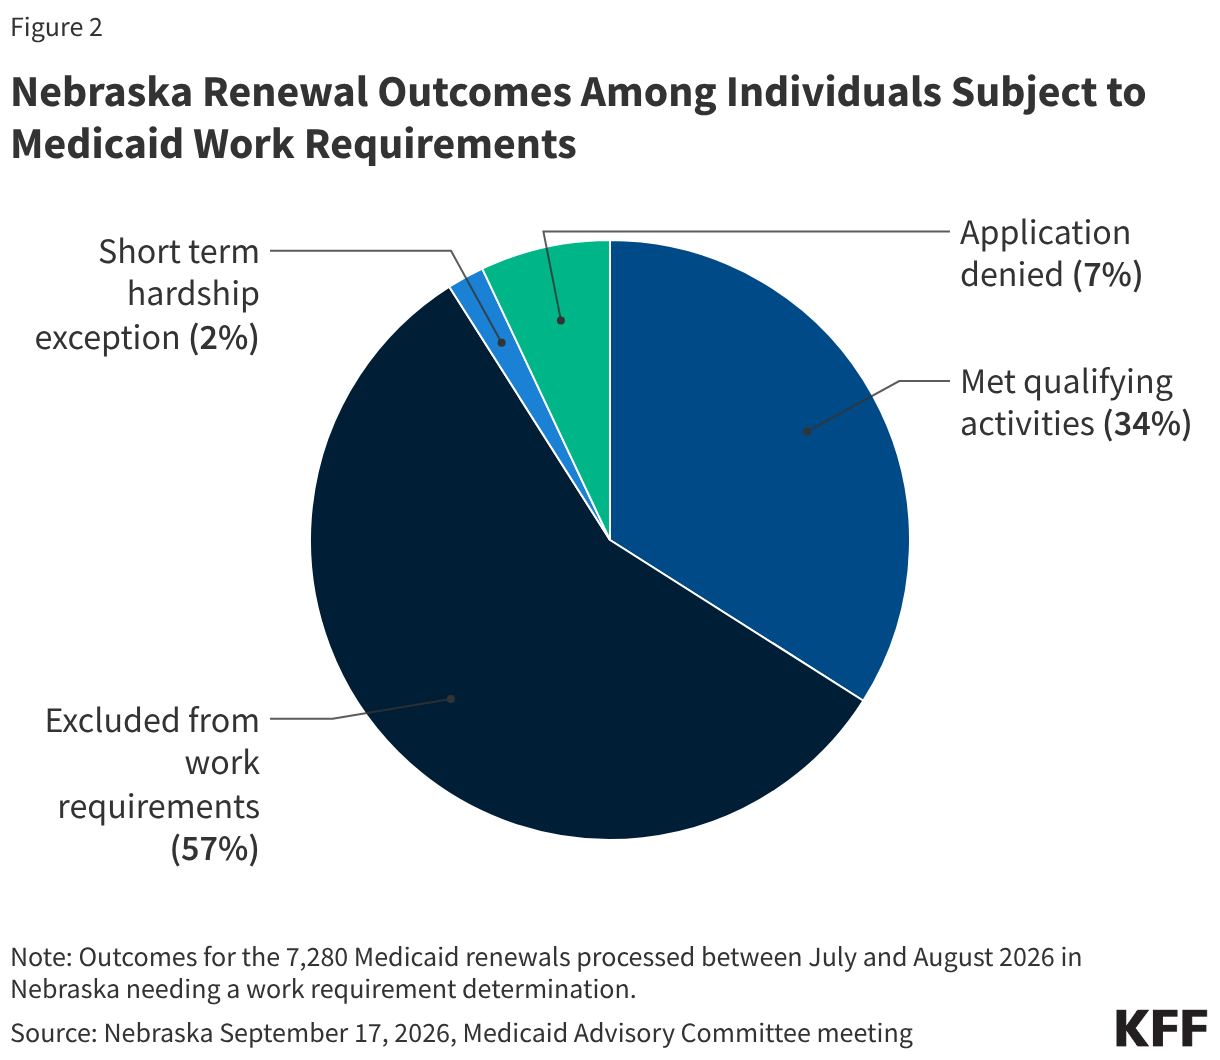
The renewal process presents a different set of challenges. Of the 7,280 renewals processed for individuals subject to the requirements:
- The Retention Rate: 93% of enrollees successfully maintained their coverage.
- The Disenrollment Rate: 7% of enrollees lost their coverage.
While these percentages suggest that the vast majority of the population is successfully navigating the new rules, the 7% who lost coverage represent thousands of individuals now potentially lacking a critical health resource.
Official Responses and Administrative Pressures
The federal government, through the Centers for Medicare & Medicaid Services (CMS), remains an active participant in Nebraska’s rollout. Recently, CMS notified the Nebraska Department of Health and Human Services (DHHS) that the state’s medical frailty verification process requires refinement.
This is a point of significant contention. Advocates argue that if the state is forced to tighten its verification process—moving away from self-attestation toward a more document-heavy, bureaucratic model—the number of individuals qualifying for medical frailty exclusions will likely shrink. This could lead to a "chilling effect," where vulnerable individuals who are unable to navigate complex documentation requirements are disenrolled, despite being theoretically eligible for an exemption.
State officials, conversely, emphasize that the goal of these requirements is to foster economic self-sufficiency. They maintain that the early data shows the system is working for most, and that the "denial" rates are often tied to a failure to engage with the administrative process rather than an inability to work.
The Broader Implications for Healthcare Policy
As Nebraska navigates this transition, the implications for the rest of the nation are profound. The state’s experience provides several key takeaways for policymakers:
1. The "Administrative Burden" Gap
One of the most pressing questions is whether the 7–14% who lost coverage or were denied are truly ineligible, or if they were simply unable to clear the "administrative hurdle." For gig workers, those with multiple part-time jobs, or individuals with limited digital literacy, the requirement to verify work status every few months can be insurmountable. If the state cannot distinguish between these populations, it risks cutting off coverage to those who need it most.
2. The 2028 Cliff
The reliance on self-attestation is currently masking the potential for higher disenrollment. By 2028, when states are generally required to demand hard documentation for all but the most obvious cases of medical frailty, the bureaucratic friction will increase significantly. Nebraska’s current experience suggests that as documentation requirements tighten, disenrollment rates will likely climb unless the state invests heavily in navigation assistance for beneficiaries.
3. Impact on Health Equity
Early data does not yet break down disenrollment by race, income, or disability status. However, public health experts warn that work requirements disproportionately affect marginalized groups who are more likely to work in irregular, low-wage, or unstable labor sectors. Monitoring whether this policy exacerbates existing health disparities will be a critical task for the Medicaid Advisory Committee in the coming years.
Conclusion: A Work in Progress
Nebraska’s foray into mandatory work requirements is more than just a policy change; it is a test of the fundamental purpose of the Medicaid program. While the state has successfully maintained coverage for the vast majority of its enrollees, the "denial" and "disenrollment" figures suggest a segment of the population is falling through the cracks.
As the state moves toward 2027 and the impending federal mandate for stricter documentation in 2028, the data will become increasingly significant. Whether this policy succeeds in its stated goal of encouraging workforce participation, or whether it ultimately functions as a barrier to healthcare for the state’s most vulnerable, will depend on the state’s willingness to adapt its verification processes. For now, Nebraska remains the bellwether, and the rest of the country is watching closely to see if this model can be sustained without compromising the foundational promise of health security.
About the Author