Editorial Note: Originally published on July 16, 2025, this analysis has been updated to reflect the evolving landscape of the Rural Health Transformation Program (RHTP) as state-level implementation gains momentum in 2026.
Executive Summary: A New Paradigm for Rural Care
On July 4, 2025, the landscape of American healthcare underwent a seismic shift. President Trump signed a landmark budget reconciliation bill—the legislative vehicle widely known during its drafting as the “One Big Beautiful Bill”—which introduced a dual reality for the nation’s healthcare system: historic, multi-billion-dollar reductions in federal Medicaid spending alongside the creation of the $50 billion Rural Health Transformation Program (RHTP).
The RHTP, administered by the Centers for Medicare & Medicaid Services (CMS) through its newly established Office of Rural Health Transformation, is designed as a five-year, $50 billion grant initiative. Its stated mission is to stabilize and modernize rural healthcare delivery. However, as the program moves into its second year, questions persist regarding its ability to bridge the widening chasm created by the concurrent reductions in Medicaid and the expiration of pandemic-era federal support.
Chronology: From Legislative Compromise to Implementation
The RHTP was not an original pillar of the reconciliation package; it emerged as a critical political compromise during intense Senate negotiations in June 2025. Facing pressure from lawmakers concerned that the bill’s austerity measures would trigger a wave of rural hospital closures, GOP leadership carved out this fund to serve as a buffer.
- July 2025: The reconciliation bill is signed into law.
- September 2025: CMS releases the Notice of Funding Opportunity (NOFO). States are given a narrow two-month window to submit comprehensive transformation plans.
- December 2025: CMS announces the first-year awards, totaling $10 billion.
- 2026–2030: The primary operational window for the $50 billion fund.
- November 2026: States are required to submit the first round of quarterly reports detailing how they have obligated their initial funding to downstream recipients.
- September 2032: The final sunset date; all remaining RHTP funds must be fully expended.
Supporting Data: The Math of Transformation
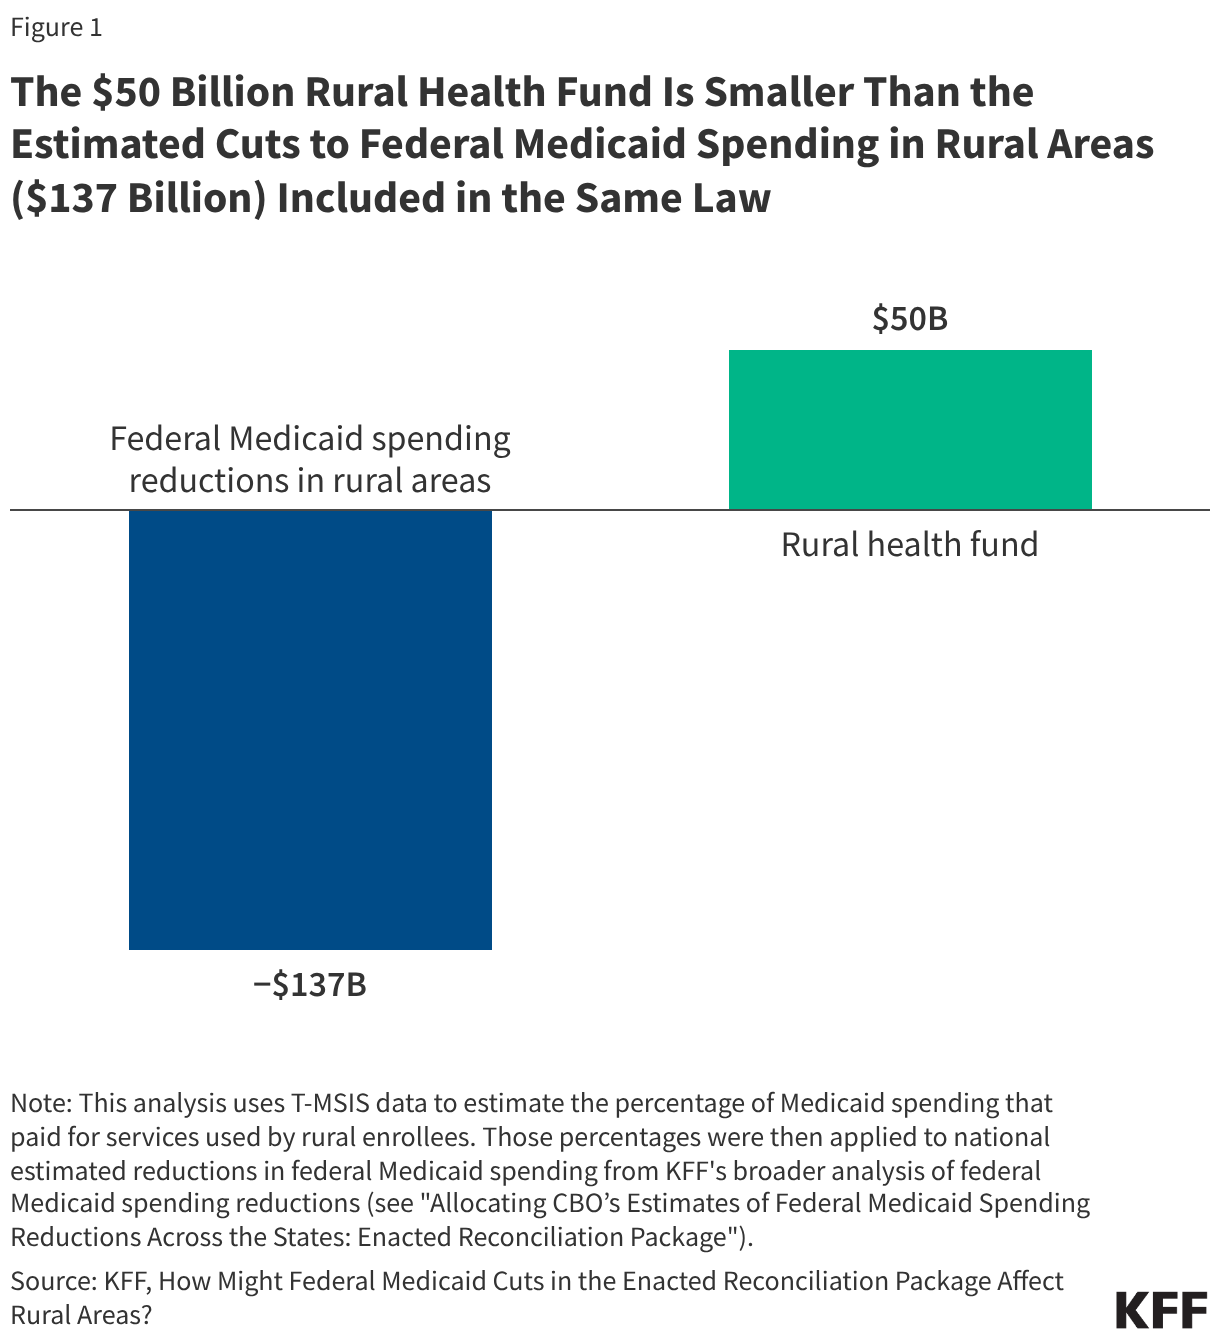
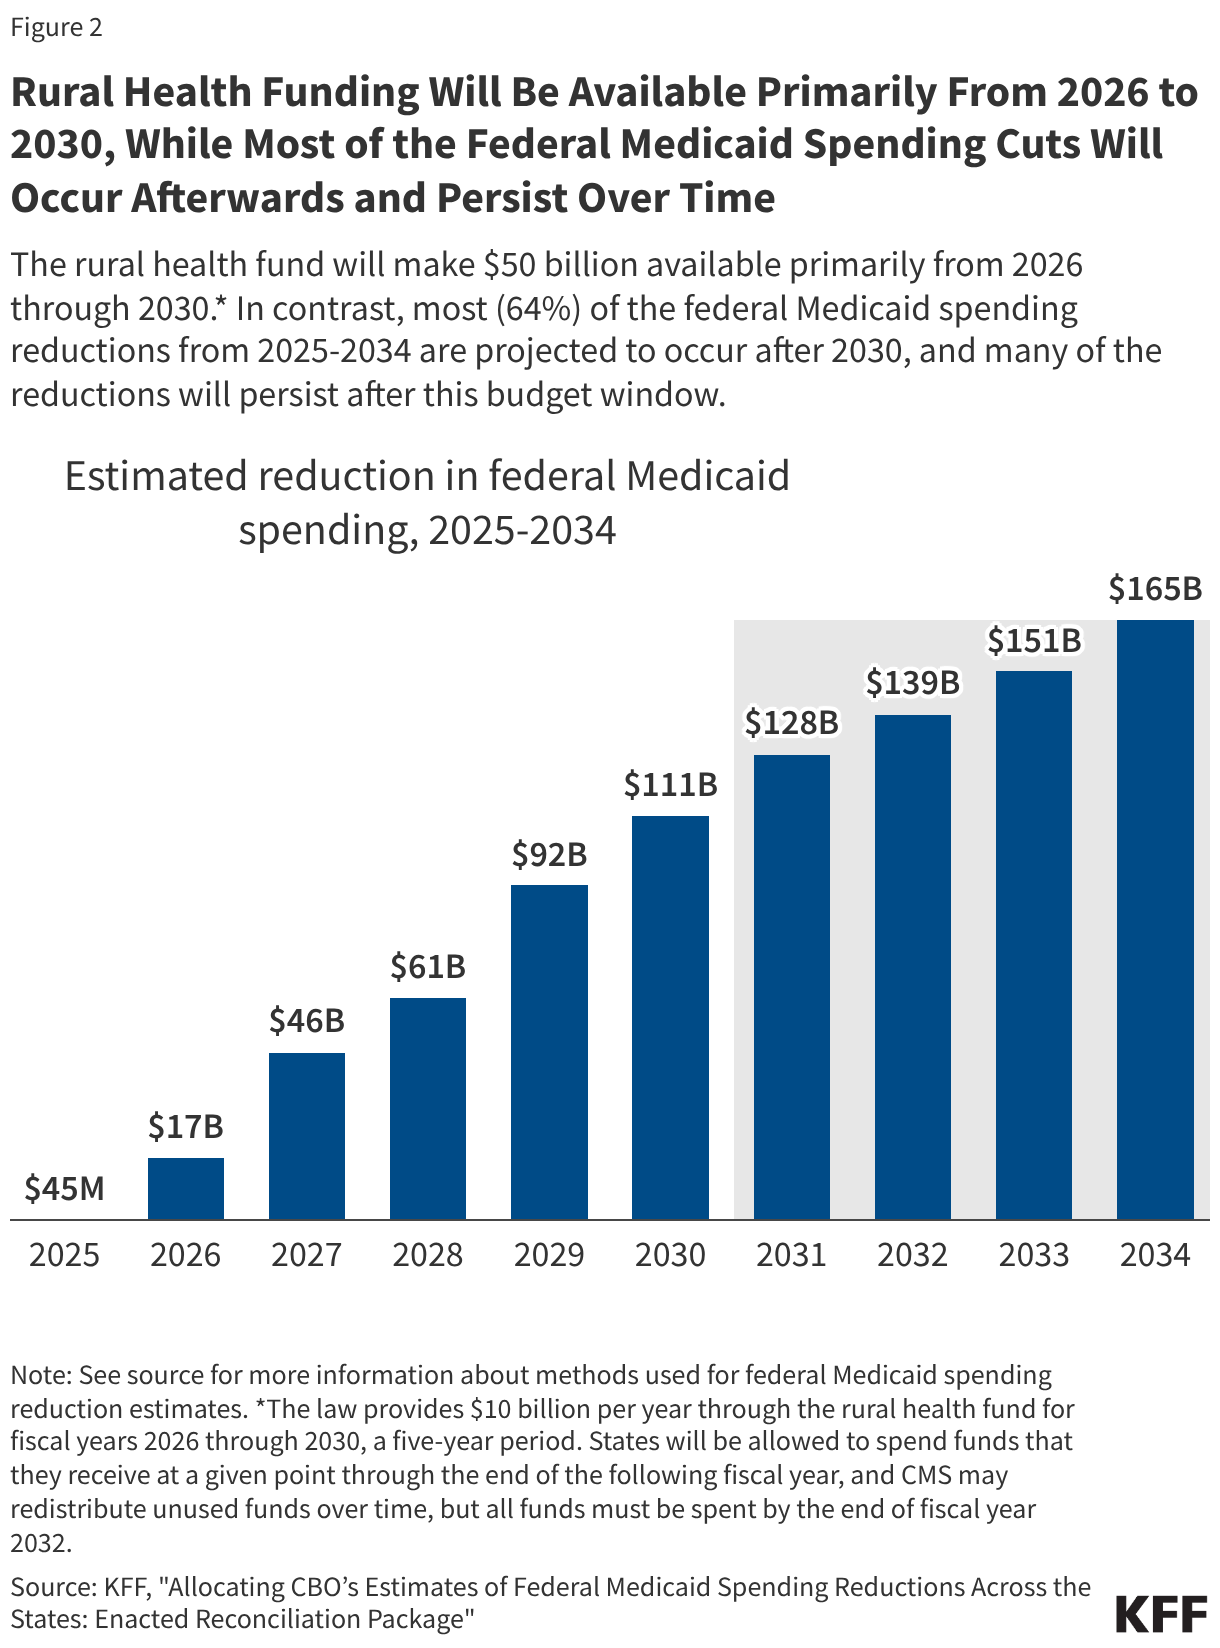
The RHTP’s $50 billion investment is significant, yet it faces the mathematical challenge of offsetting a much larger fiscal contraction. KFF analysis projects the reconciliation law will reduce federal Medicaid spending by approximately $911 billion over ten years, with an estimated $137 billion of those cuts falling directly on rural areas.
The Funding Structure
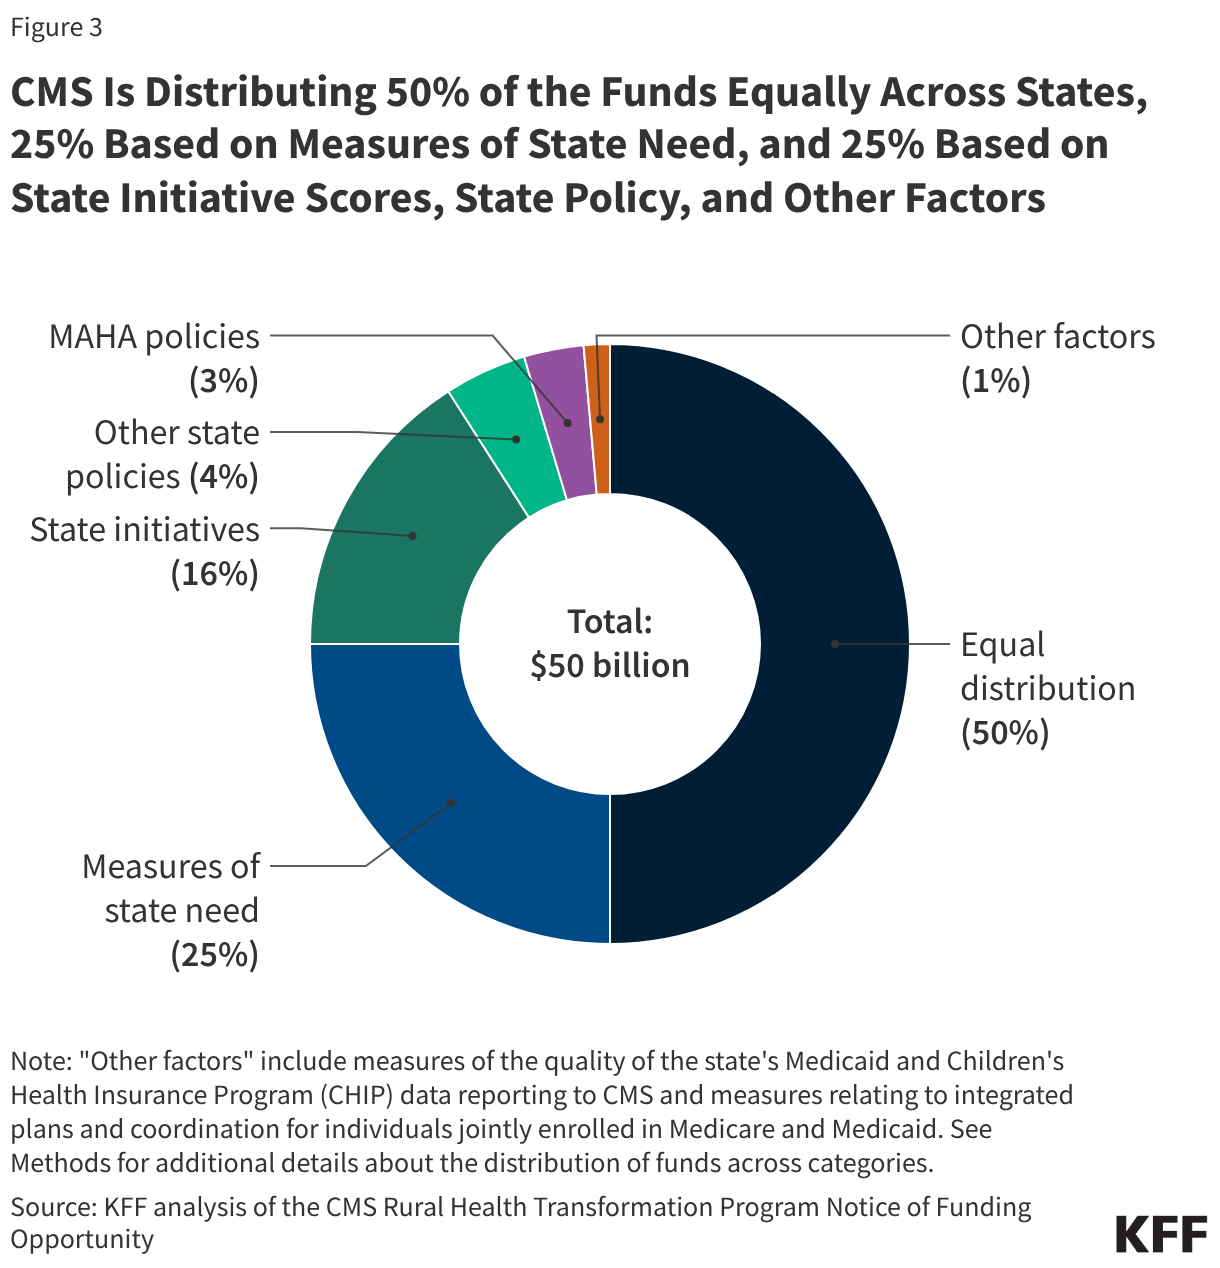
CMS employs a tripartite distribution model for the $50 billion:
- Baseline Funding (50%): $25 billion is distributed equally among all 50 states, ensuring a guaranteed floor of support regardless of population size.
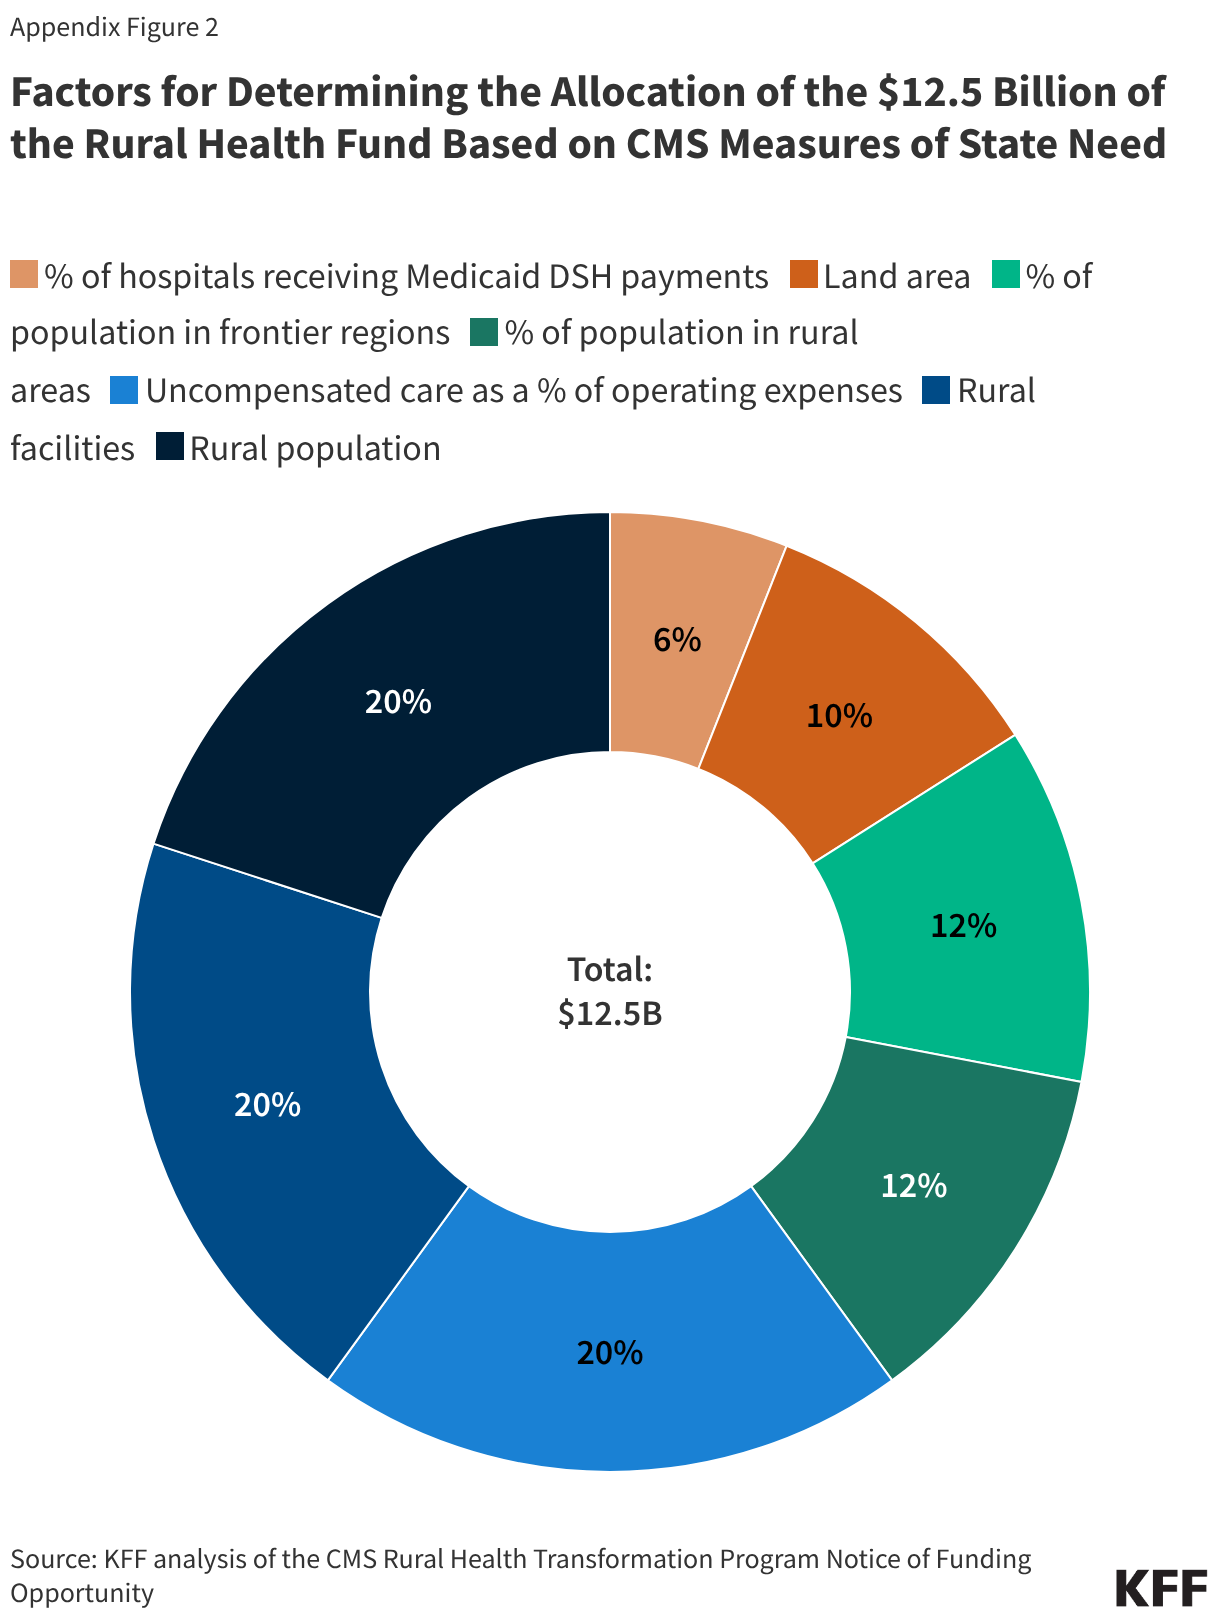
- Need-Based Funding (25%): $12.5 billion is allocated based on 23 weighted factors, including health outcomes, dual-eligibility rates, and, notably, land area.
- Performance/Policy Funding (25%): $12.5 billion is awarded based on state-specific initiatives, policy innovation, and compliance with CMS’s strategic goals.
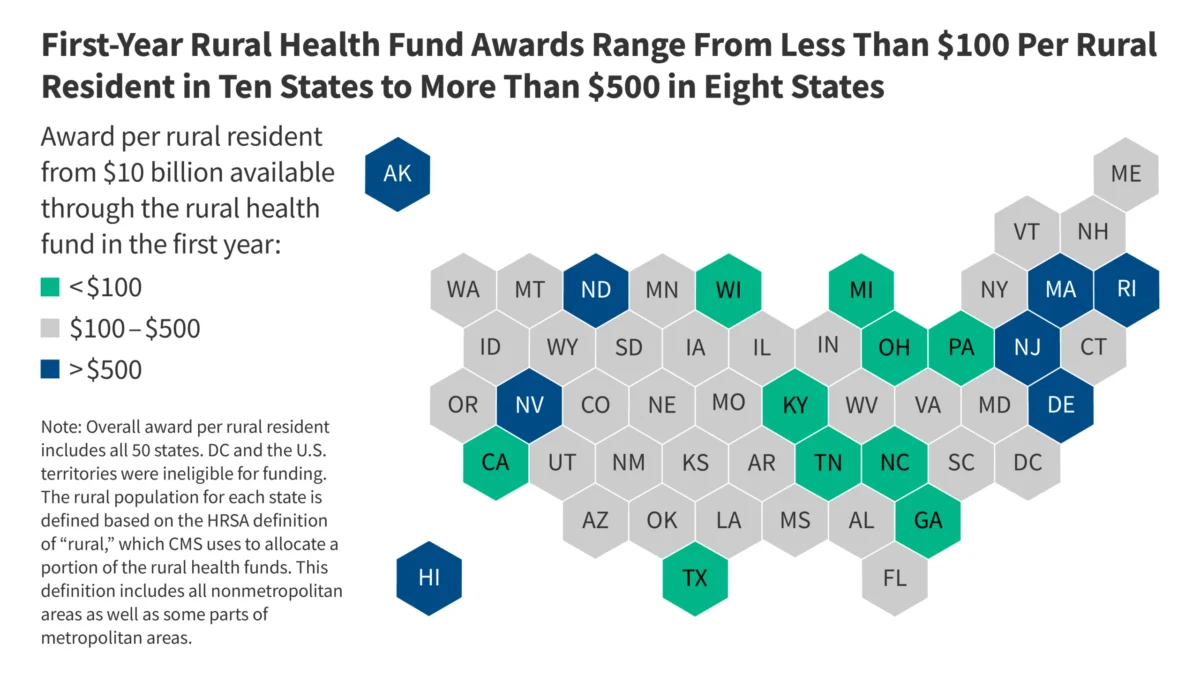
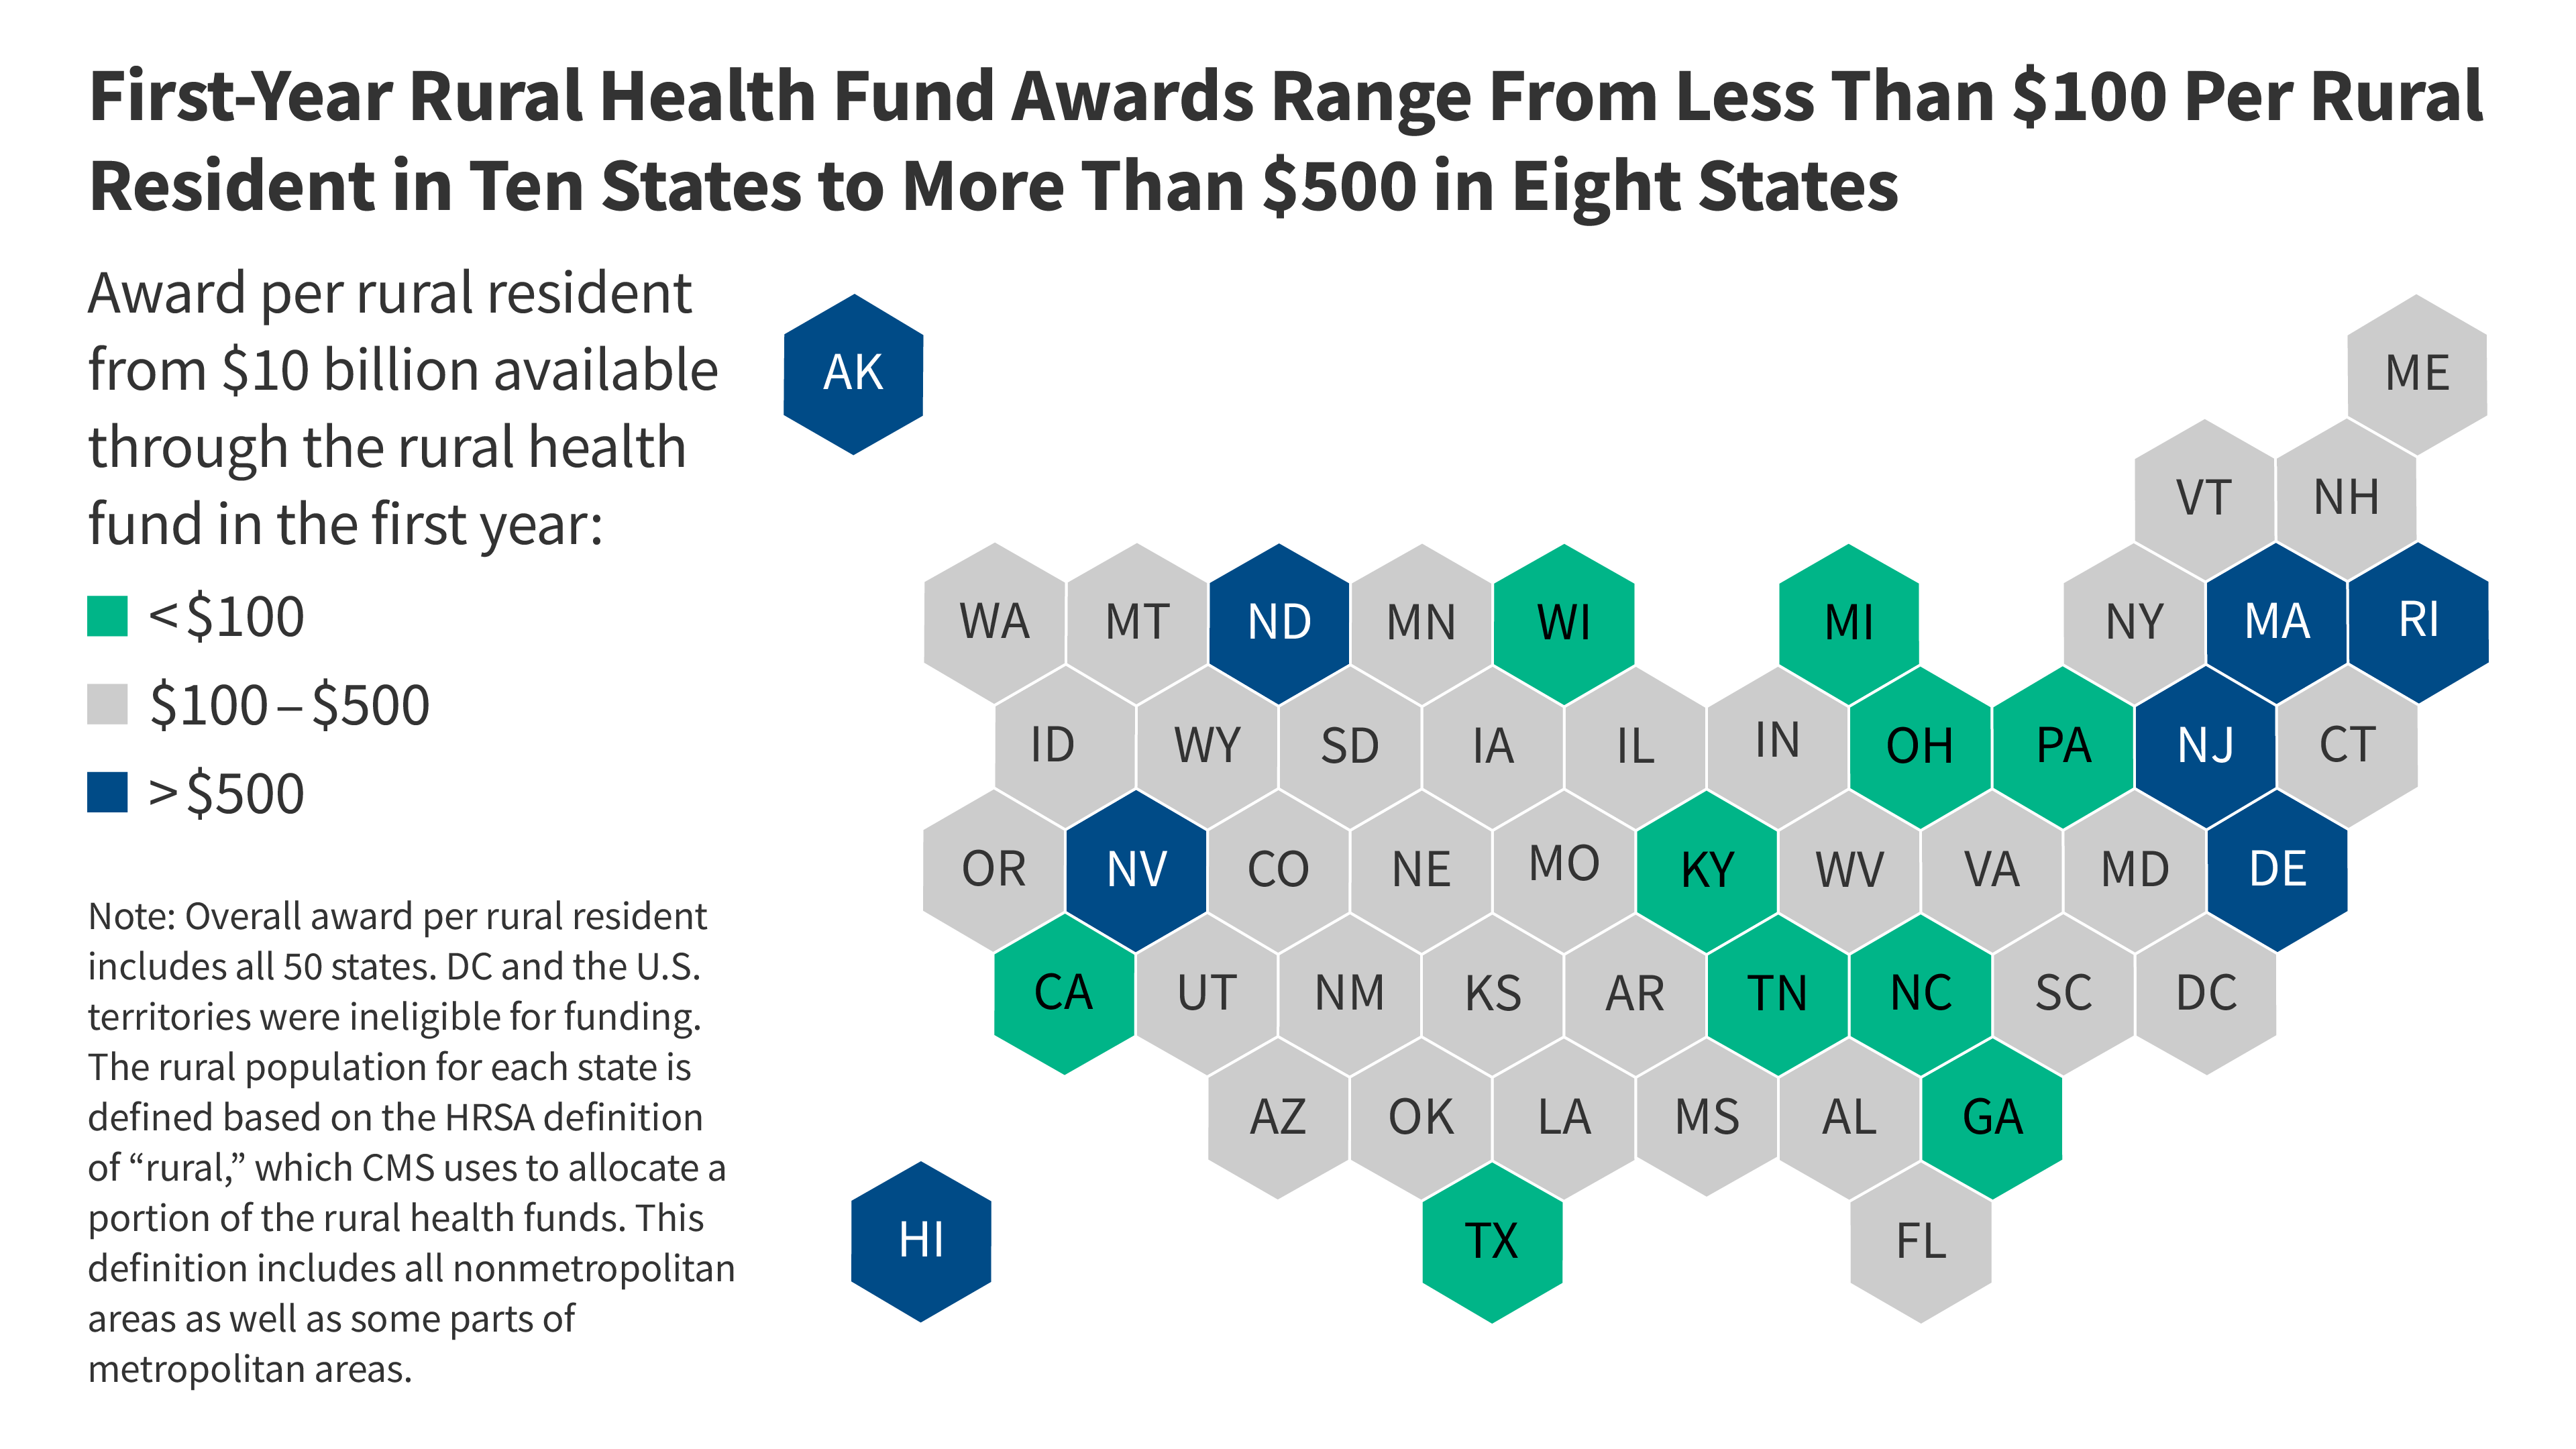
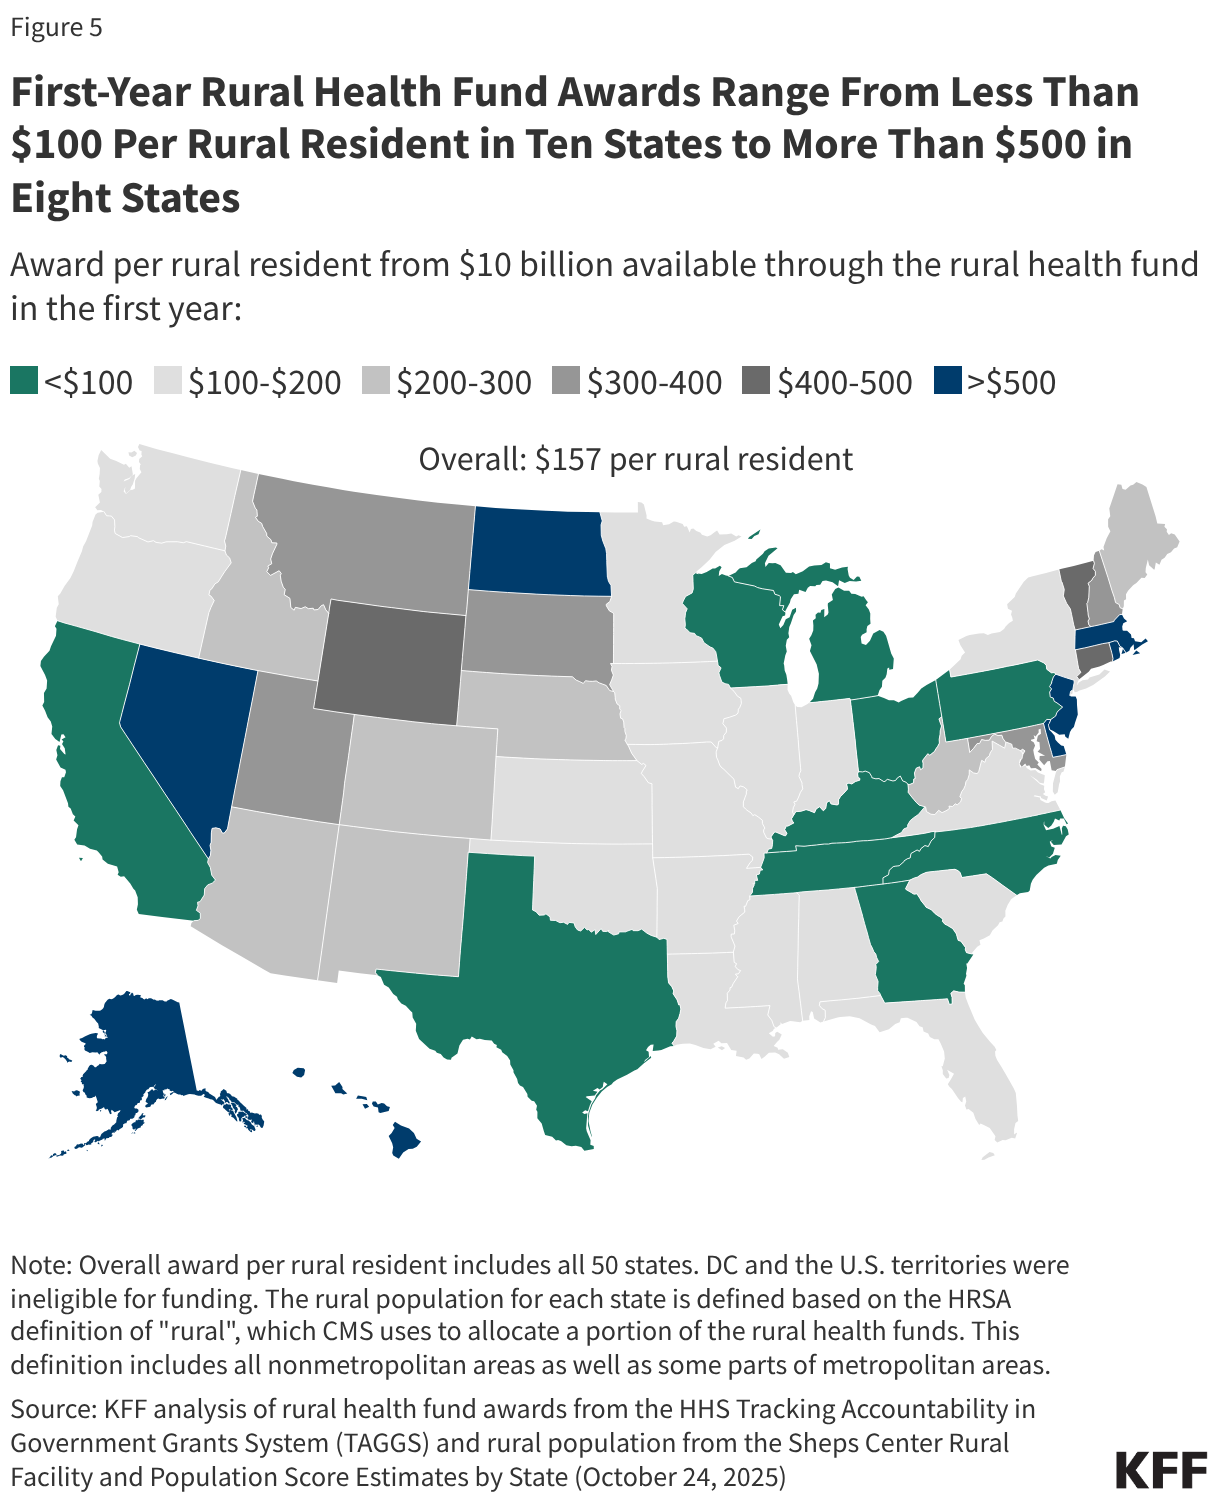
This structure has led to significant disparities in per-capita funding. For example, in 2026, Texas—home to the nation’s largest rural population—received roughly $281 million, translating to approximately $66 per rural resident. Conversely, states with smaller rural footprints, such as Rhode Island, received disproportionately higher per-capita funding due to the equal-distribution “baseline” requirement.
Official Responses and Strategic Goals
Dr. Mehmet Oz, in his capacity at CMS, has underscored that the RHTP is not intended to be a perpetual subsidy for operating expenses. Instead, the agency expects states to utilize the funds for "long-term, sustainable improvements."
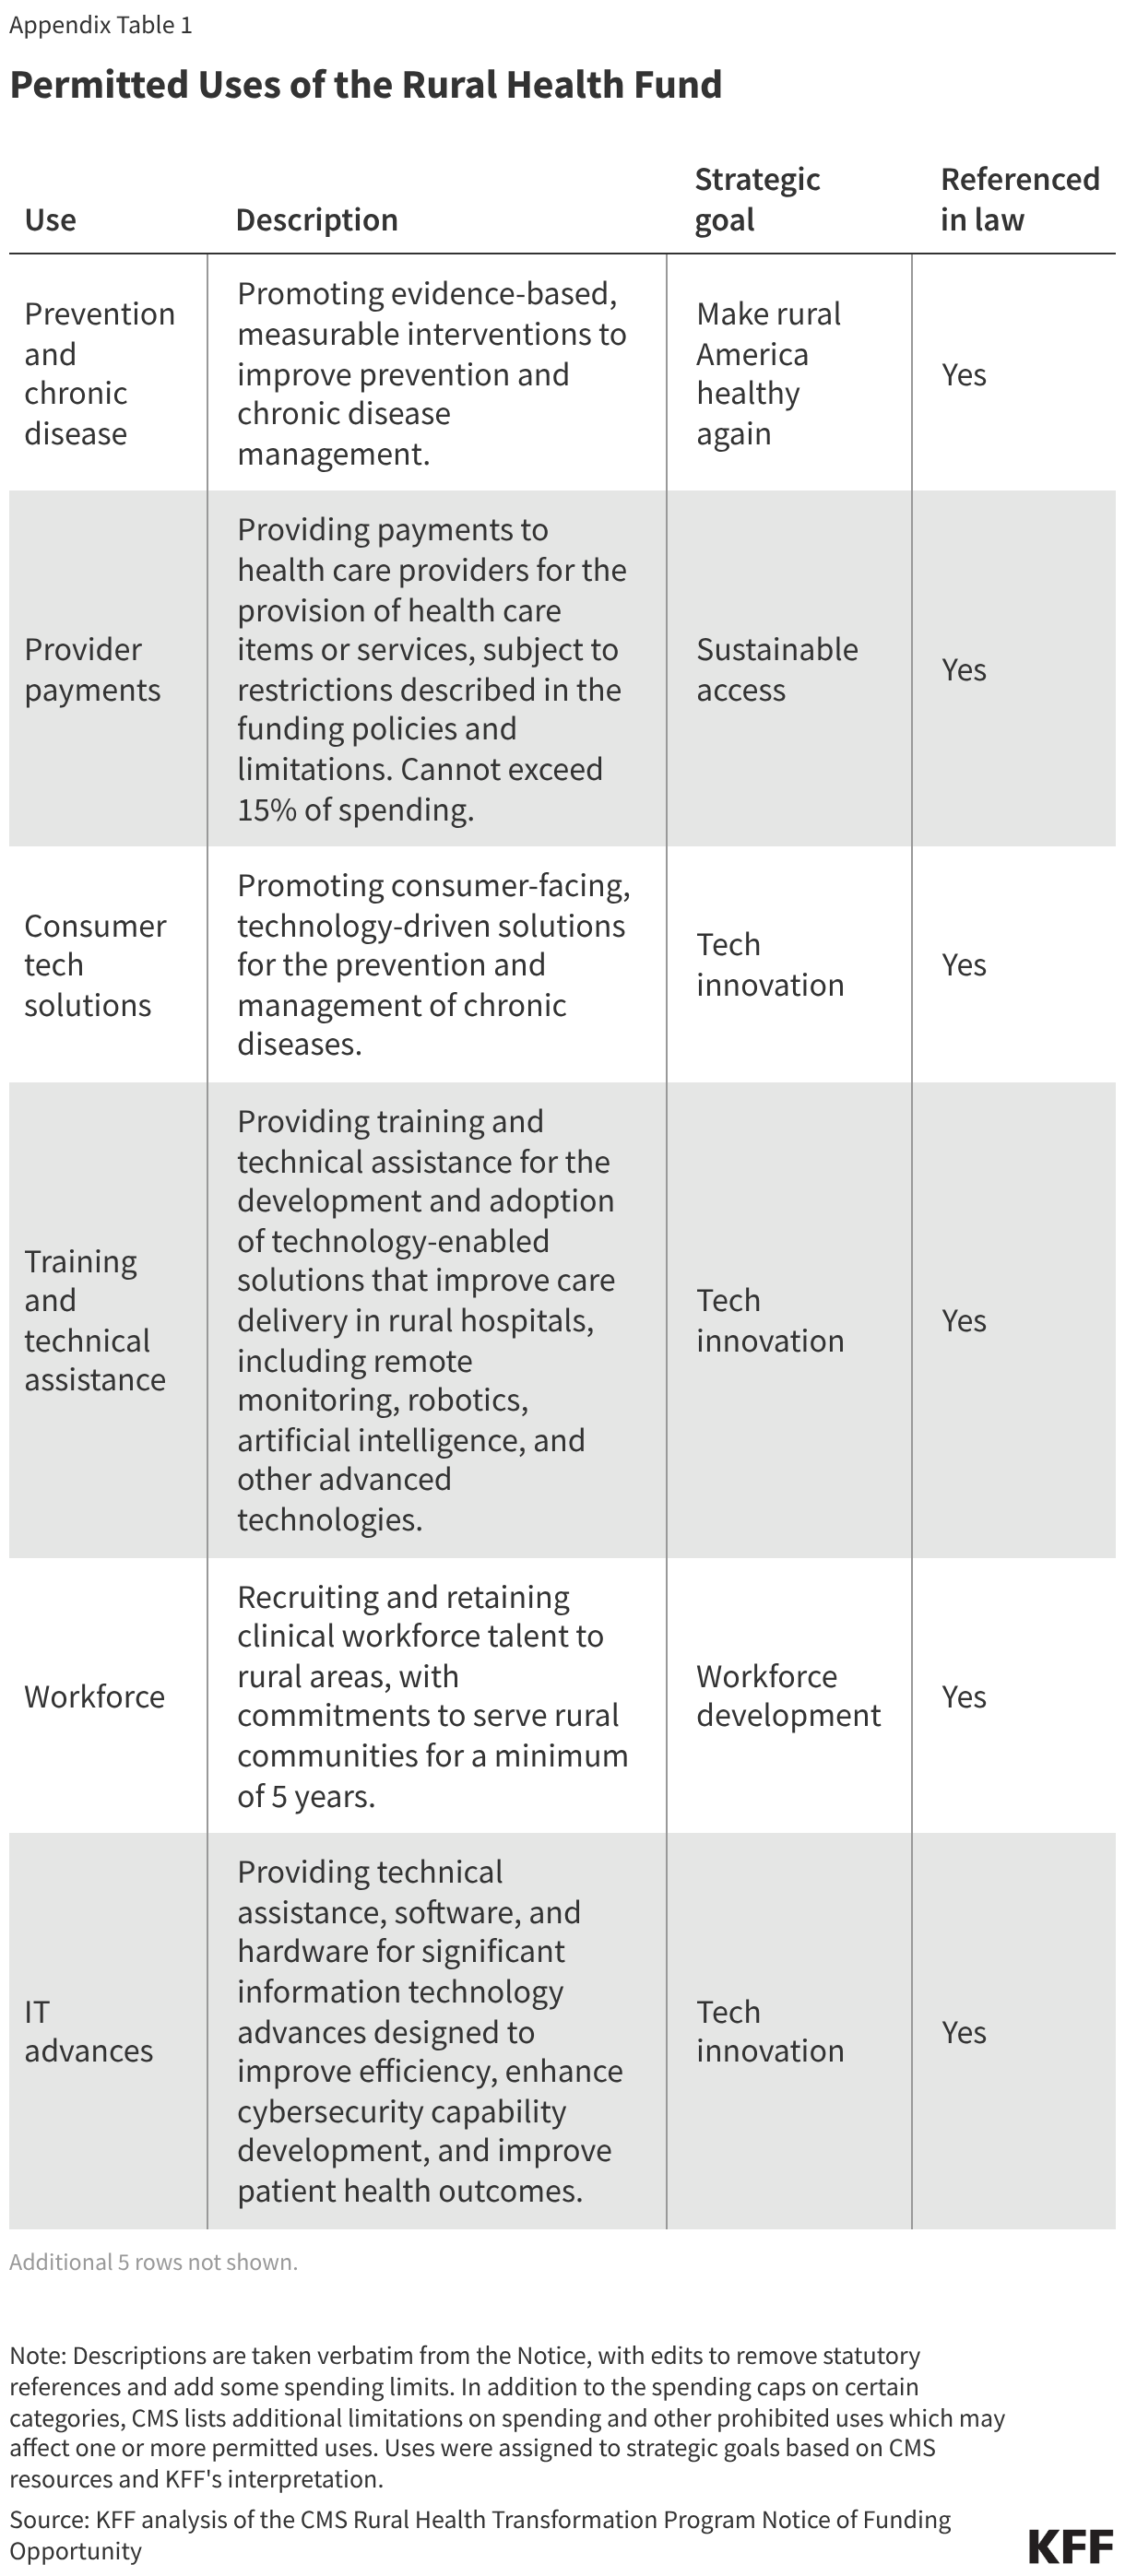
The Five Strategic Pillars:
- "Make Rural America Healthy Again": Focusing on prevention and chronic disease management.
- Sustainable Access: Redesigning service delivery to keep vital functions local.
- Workforce Development: Incentives to recruit and retain clinical staff in underserved areas.
- Innovative Care: Promoting value-based care and alternative payment models.
- Tech Innovation: Expanding telehealth infrastructure and AI-driven diagnostic tools.
Despite these goals, the "cooperative agreement" mechanism—which mandates substantial CMS oversight—has drawn scrutiny. The American Hospital Association (AHA) and other industry stakeholders have urged CMS to provide greater flexibility, particularly in lifting restrictions on capital investments and provider payments, arguing that the current rules may favor large health systems over the struggling, isolated rural facilities that need support the most.
Implications: A Race Against Time
The core tension of the RHTP lies in the timing of the fiscal cliff. The $50 billion in funding is "front-loaded," with the bulk of the money flowing between 2026 and 2030. In contrast, the most severe Medicaid spending reductions are "back-loaded," with nearly two-thirds of the total ten-year cuts projected to occur after 2030.
The Uninsured Rate and Hospital Solvency
The expiration of enhanced Affordable Care Act (ACA) premium tax credits, coupled with the new Marketplace integrity rules, is expected to drive an increase in the uninsured rate. For rural hospitals, this creates a "double-jeopardy" scenario:
- Reduced Revenue: Fewer patients with private or Medicaid coverage.
- Increased Uncompensated Care: A higher volume of patients unable to pay for services, which the RHTP is explicitly forbidden from covering as a routine operating expense.
Transparency and Accountability
The public’s ability to monitor these funds remains limited. While CMS is collecting granular data on how states distribute funds to hospitals, contractors, and IT vendors, there is no proactive, public-facing dashboard. Journalists and researchers are currently reliant on Freedom of Information Act (FOIA) requests, a process often described as "arduous."
Advocacy groups, including the Bipartisan Policy Center, have called for a more transparent reporting portal to ensure that the $50 billion achieves its promise of systemic transformation rather than disappearing into administrative overhead or ineffective pilot programs.
Conclusion: The Road Ahead
The Rural Health Transformation Program represents a bold, if untested, attempt to use federal grants to restructure the healthcare delivery model in America’s heartland. While the funding provides a temporary lifeline, the program’s success will ultimately be judged by its ability to foster resilience in an environment defined by shrinking federal safety nets.
As states move into the second year of the program, the focus will shift from application and procurement to impact. Whether this $50 billion experiment will permanently stabilize rural healthcare or merely delay an inevitable consolidation remains the most pressing question in national health policy. With the program’s sunset date set for 2032, lawmakers will likely face the necessity of additional, permanent legislation to ensure that the "transformation" envisioned today does not evaporate once the grant money runs dry.
About the Author