As the annual Medicare Open Enrollment period approaches, beneficiaries across the United States are bracing for changes to their prescription drug coverage. The Centers for Medicare & Medicaid Services (CMS) has officially released data regarding Medicare Part D plans for the 2027 calendar year. While federal regulators are touting a sense of market stability, a deeper look into the data—compiled by KFF—reveals a complex, shifting landscape characterized by a contraction in plan availability and a wide disparity in how premium adjustments will impact individual enrollees.
For the millions of seniors and individuals with disabilities who rely on Medicare for their pharmaceutical needs, understanding these shifts is not merely a matter of administrative curiosity—it is a critical component of financial and health planning for the coming year.
The Main Facts: What Beneficiaries Need to Know
The core message from CMS is one of equilibrium. Despite the volatility often associated with the pharmaceutical market, the agency expects the Part D prescription drug plan (PDP) marketplace to remain stable through 2027, mirroring the conditions observed in 2026. CMS projects a very modest average monthly premium increase, rising from $35 to $36—an average uptick of just $1.
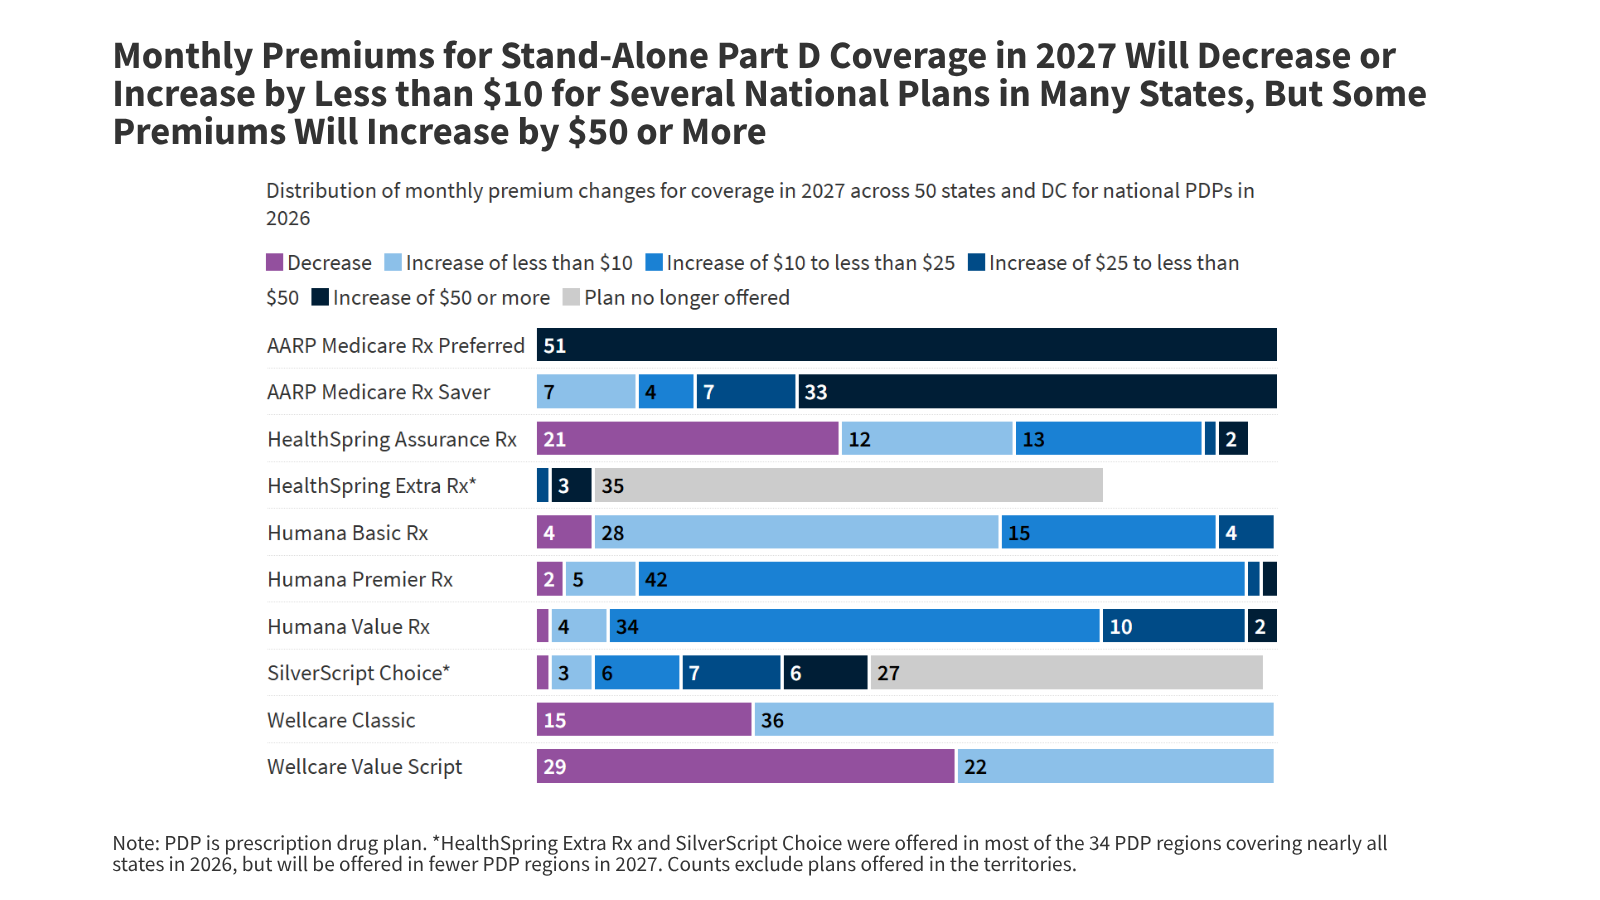
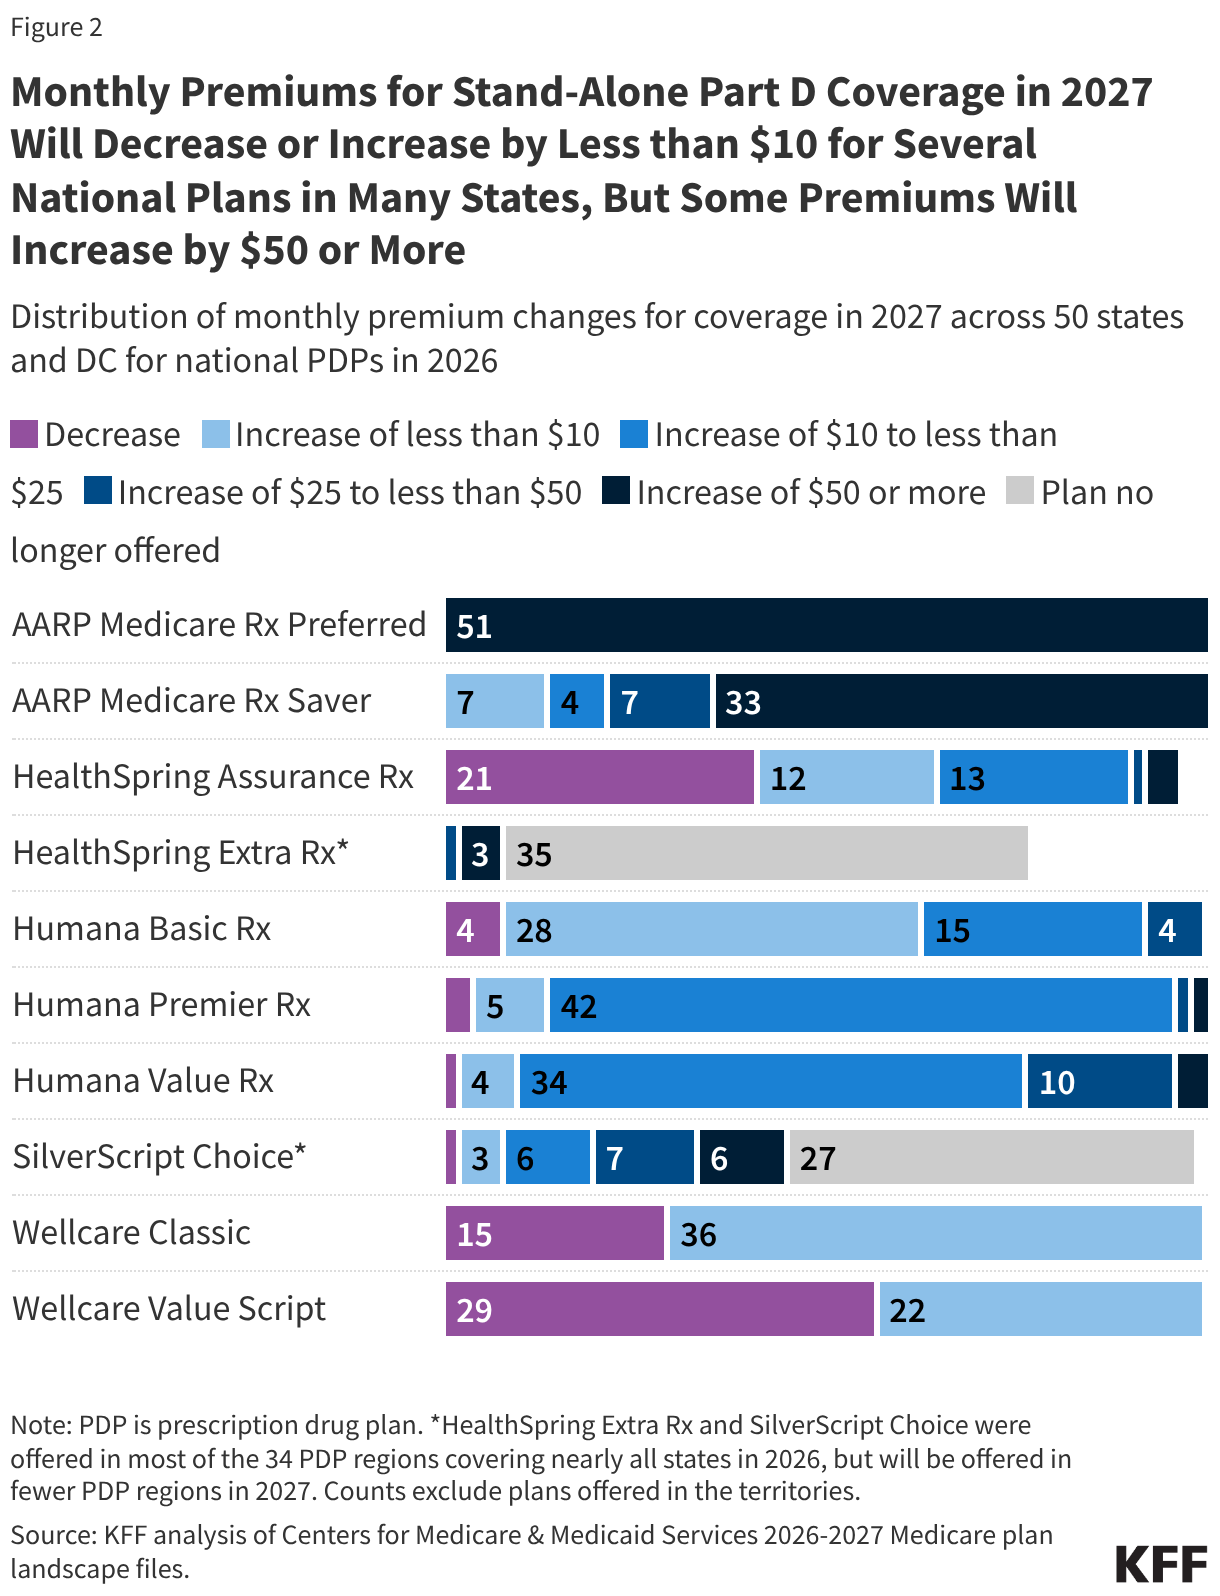
However, averages can be deceiving. While the national "average" suggests a period of calm, the reality for the average beneficiary is more nuanced. The number of stand-alone prescription drug plans (PDPs) available to the typical enrollee is set to decline for the fourth consecutive year. Furthermore, while some enrollees will see their premiums decrease or remain flat, others may face significant, double-digit increases if they remain in their current plans without conducting a thorough annual review.
A Chronology of Market Contraction
The decline in plan choices is not a sudden event, but rather the continuation of a multi-year trend of consolidation within the insurance sector.
- 2024-2025: The market began to see a gradual reduction in the number of insurers participating in the stand-alone PDP space, as companies consolidated their offerings to streamline operations and comply with evolving federal guidelines.
- 2026: The trend accelerated as major players began withdrawing from specific geographic regions. The number of plans available to the average beneficiary dropped to 11.
- 2027: The trend persists. The number of stand-alone PDPs available to the average beneficiary will fall to nine. Nationwide, the total number of plans offered by parent organizations will drop from 360 in 2026 to 316 in 2027, with the number of participating parent organizations shrinking from 17 to 15.
The primary drivers of this year’s contraction are two major industry players: Health Care Service Corporation, which is withdrawing its "HealthSpring Extra Rx" plan from 22 regions, and CVS Health, which is pulling its "Silverscript Choice" plan from 13 regions. Humana currently stands as the only insurer maintaining three distinct PDP offerings across all 34 national PDP regions, highlighting the increasing concentration of the market.
Supporting Data: The Geography of Coverage
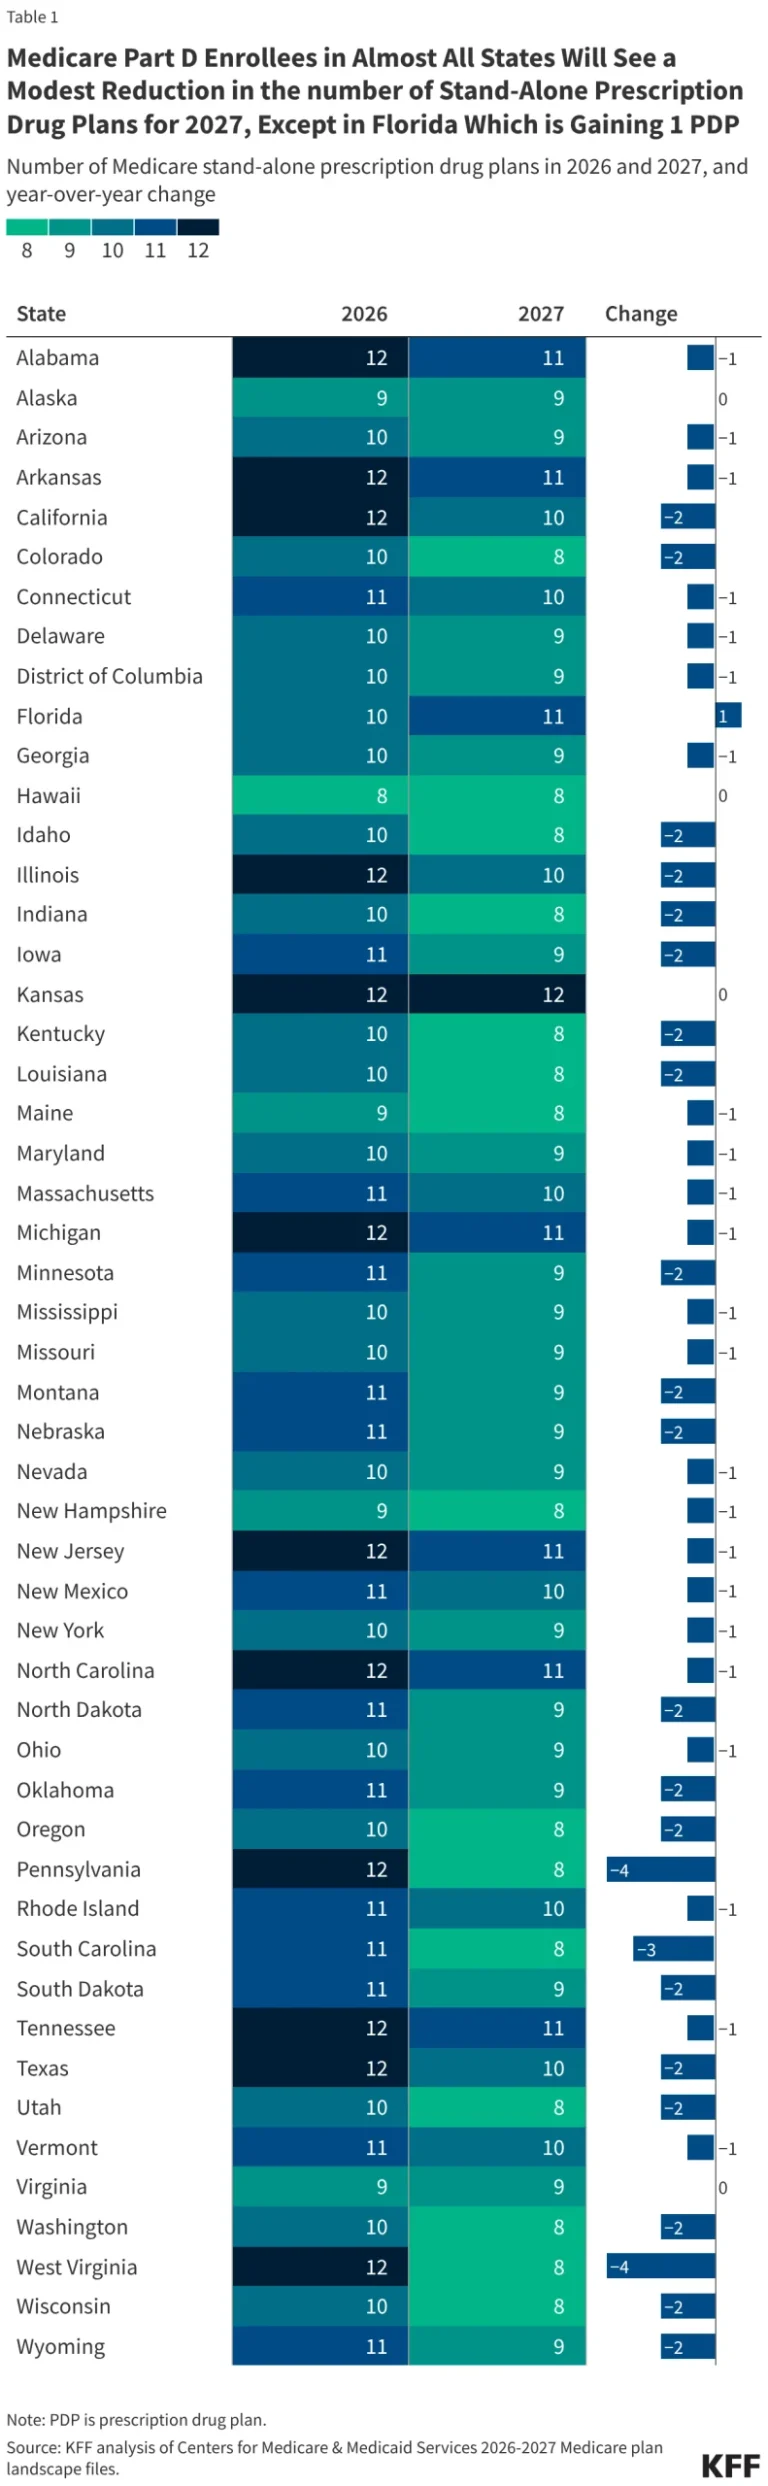
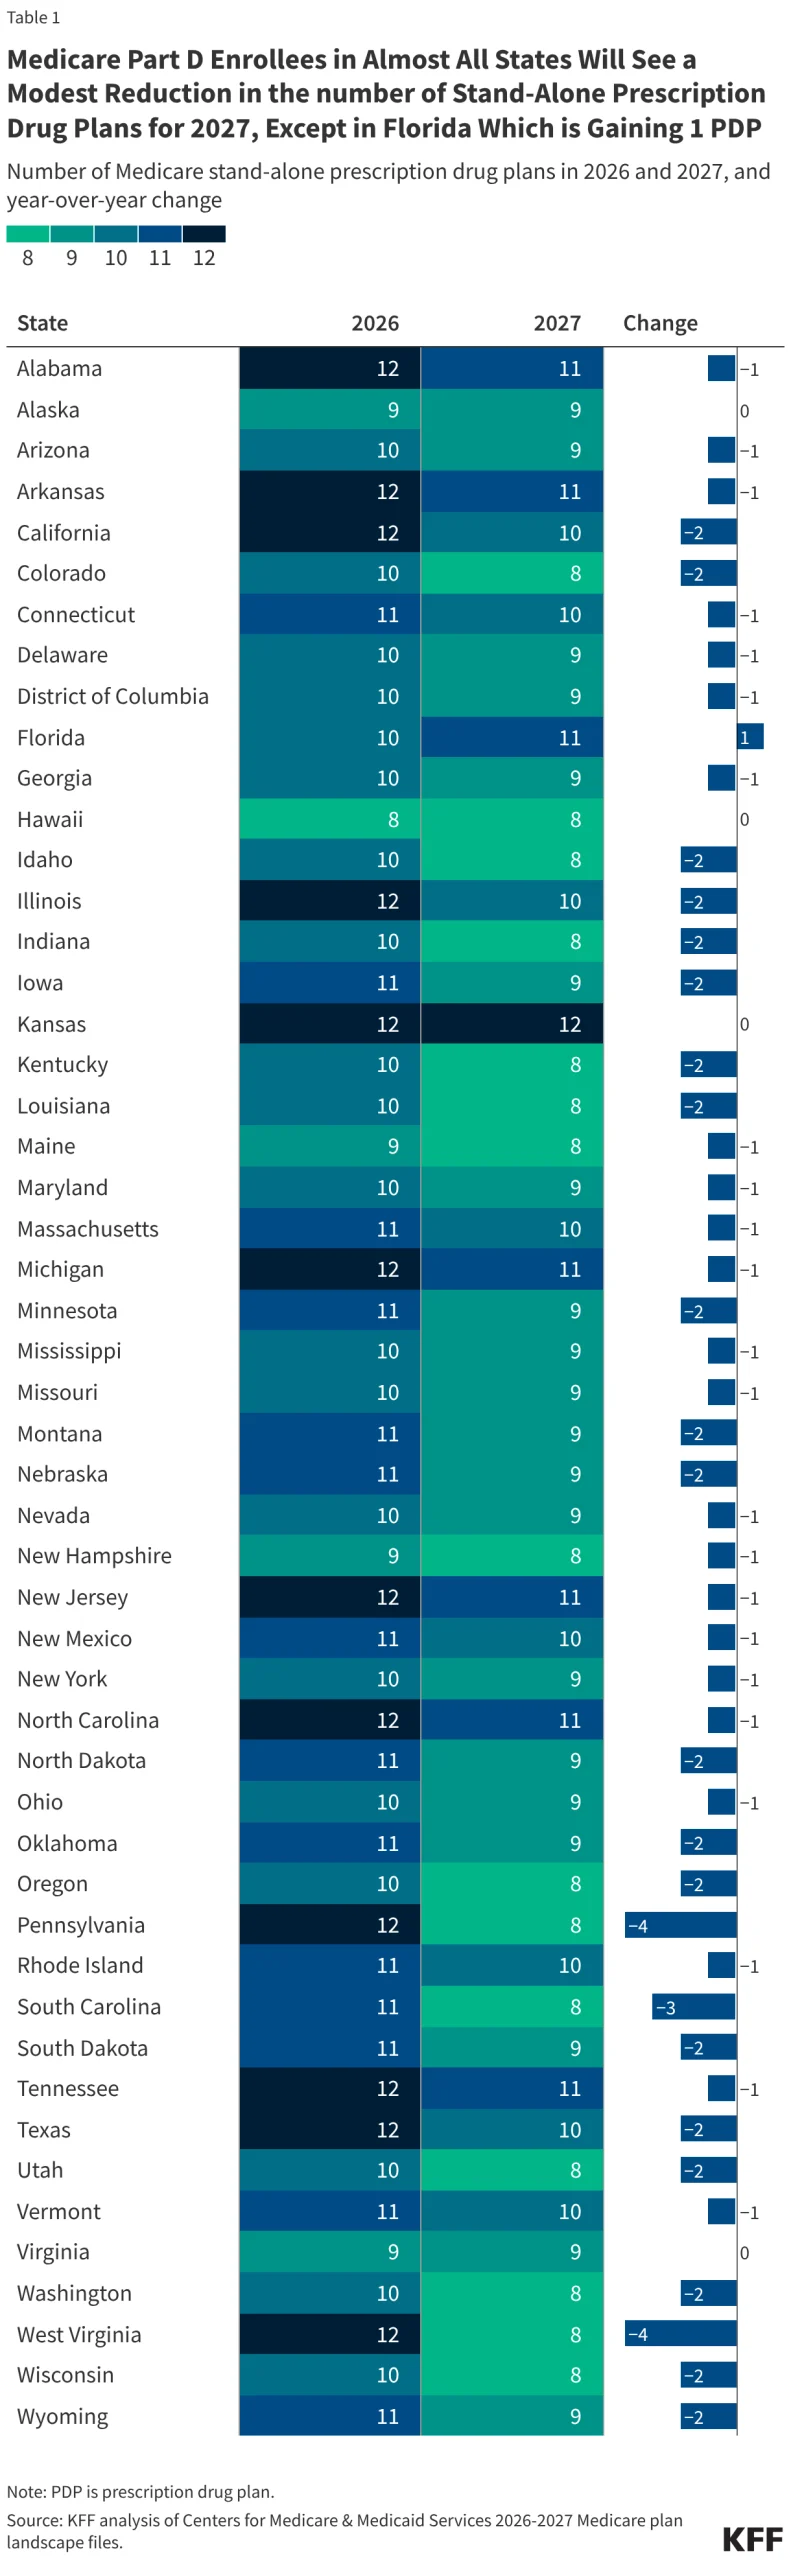
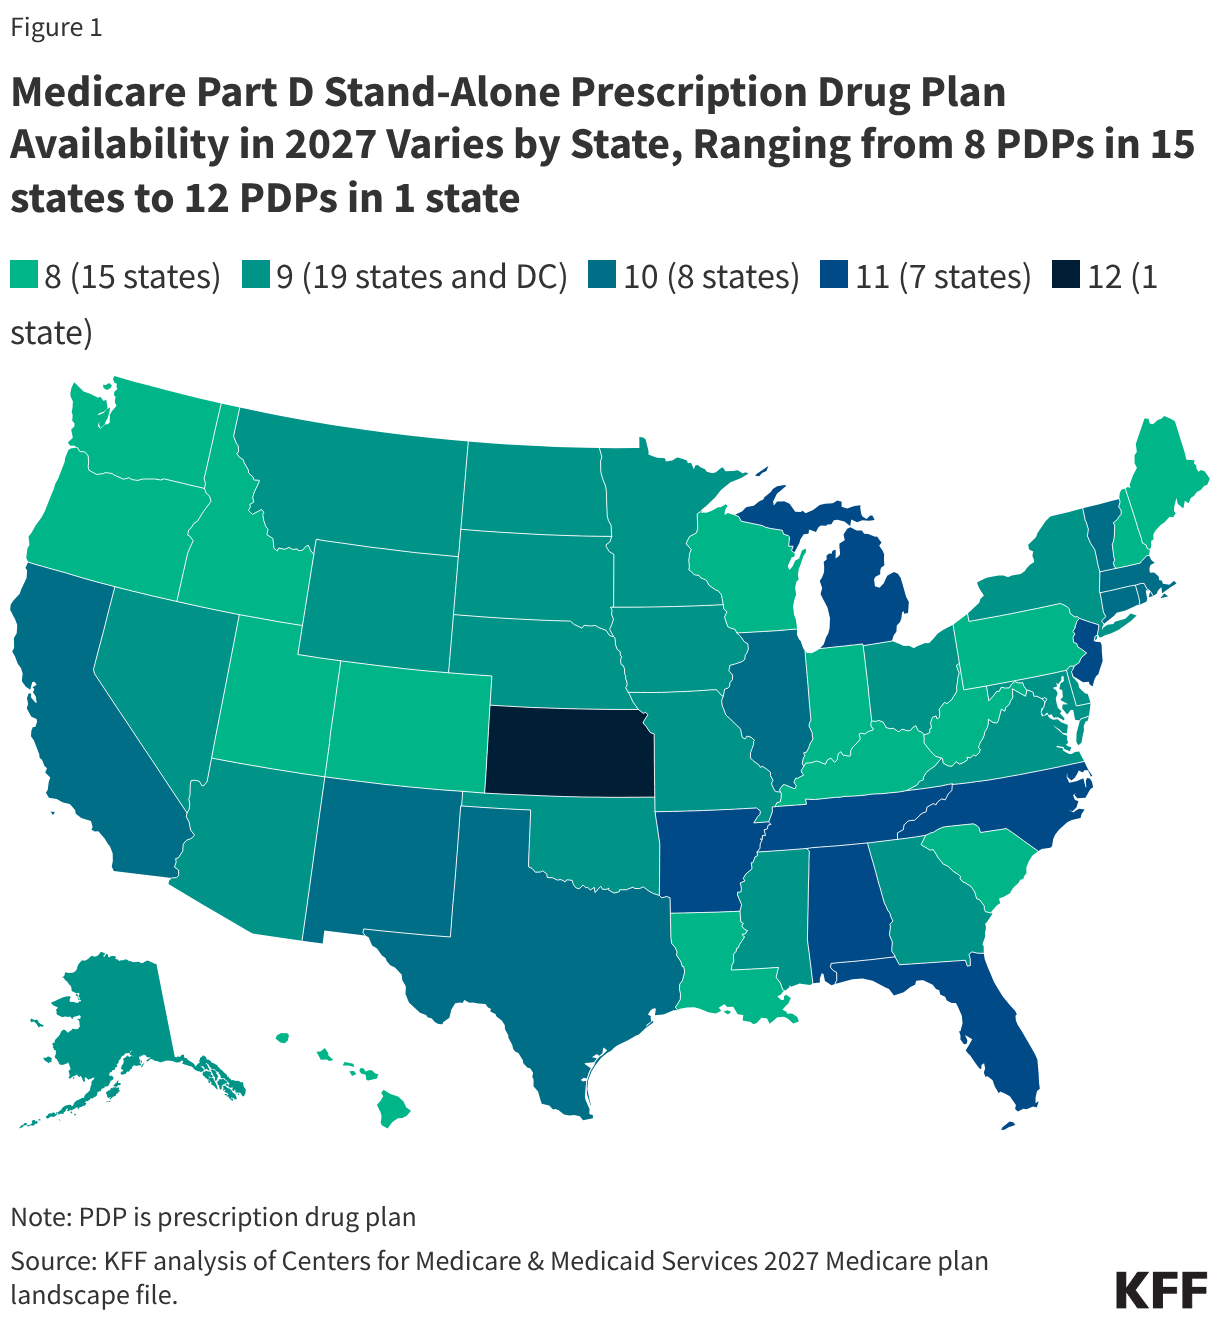
The availability of plans for 2027 remains highly dependent on geography. According to KFF analysis, beneficiaries in 15 states will have access to only eight PDPs, while at the other end of the spectrum, residents in one state will have access to 12.
Most states are seeing a modest reduction in the number of options available compared to the previous year. Florida stands as a notable exception, gaining one additional plan option, while four other states will see no change in their available roster. This geographical disparity means that a senior in one state may find themselves with significantly fewer choices than a peer in another, reinforcing the necessity of localized research during the enrollment window.
The Medicare Advantage Divergence
It is vital to distinguish between stand-alone PDPs and Medicare Advantage Prescription Drug (MA-PD) plans. As of 2026, 56% of all Part D enrollees were already in Medicare Advantage plans. These beneficiaries are largely insulated from the fluctuations of the stand-alone market.
Because Medicare Advantage plans can leverage federal rebate dollars to subsidize prescription drug coverage, they are frequently able to offer plans with $0 monthly premiums. This structural advantage—which is unavailable to stand-alone PDP sponsors—ensures that the majority of MA-PD enrollees will likely continue to pay nothing for their drug coverage in 2027, creating a two-tiered system where stand-alone plan members bear the brunt of market-driven premium adjustments.
Official Responses and the "Stabilization" Demonstration
CMS’s decision to terminate the "Part D Premium Stabilization Demonstration" for 2027 has been a focal point of industry analysis. The demonstration, which had been in place for two years, was designed to provide extra subsidies to PDP sponsors, effectively capping the year-over-year increase in monthly premiums and lowering the base beneficiary premium.
When CMS announced the termination of this program, many analysts predicted a sharp, industry-wide spike in costs. However, that "across-the-board" increase did not materialize. Instead, the market absorbed the loss of these subsidies with the modest $1 average increase cited by the agency.
Despite this, the end of the demonstration is not without consequence. The removal of the premium cap means that some beneficiaries who stay in their current plans could see monthly premium increases exceeding $50. Furthermore, the era of "zero-premium" stand-alone PDPs for those without low-income subsidies appears to be drawing to a close, as the safety net provided by the demonstration has been pulled back.
Implications: Beyond the Premium Price Tag
While the monthly premium is the most visible number for a Medicare beneficiary, experts caution that it is a dangerous metric to use in isolation. A plan with a low premium can often mask high costs elsewhere, such as:
- Formulary Changes: A plan may lower its premium by removing expensive or specialized drugs from its list of covered medications (the formulary).
- Tier Placement: Insurers may move commonly used medications to higher cost-sharing tiers, effectively increasing the out-of-pocket price for the enrollee at the pharmacy counter.
- Utilization Management: Plans are increasingly utilizing "prior authorization" or "step therapy" protocols. These restrictions require beneficiaries to jump through additional administrative hoops or try cheaper, alternative medications before the insurer will cover a more expensive, doctor-recommended drug.
- Deductibles: Even if the premium is stable, an increase in the annual deductible can result in a significant financial burden at the start of the calendar year.
As Part D costs continue to rise nationwide, there is an inherent trade-off. Insurers struggling to keep premiums "in check" are often forced to tighten their coverage parameters. For the consumer, this means that a plan that was ideal in 2026 may be entirely inadequate for their health needs in 2027.
A Call to Action for Enrollees
The evidence is clear: the "set it and forget it" approach to Medicare Part D is increasingly risky. With the reduction in plan availability and the potential for significant shifts in formulary coverage, beneficiaries must engage in a rigorous review of their current plan.
When evaluating coverage for 2027, beneficiaries should:
- Review the Annual Notice of Change (ANOC): This document, mailed by the current plan provider, outlines exactly what is changing regarding premiums, drug tiers, and coverage rules.
- Utilize the Plan Finder Tool: The official Medicare website (Medicare.gov) provides tools to input current medications and compare the total annual cost—not just the monthly premium—across all available plans in their zip code.
- Consult Local Resources: State Health Insurance Assistance Programs (SHIPs) offer free, unbiased counseling to help seniors navigate these complex choices.
In summary, while the 2027 Medicare Part D market maintains a facade of stability, the underlying currents of consolidation and shifting costs demand that every enrollee takes an active role in their healthcare future. The cost of complacency may be higher than the monthly premium increase suggests.
About the Author