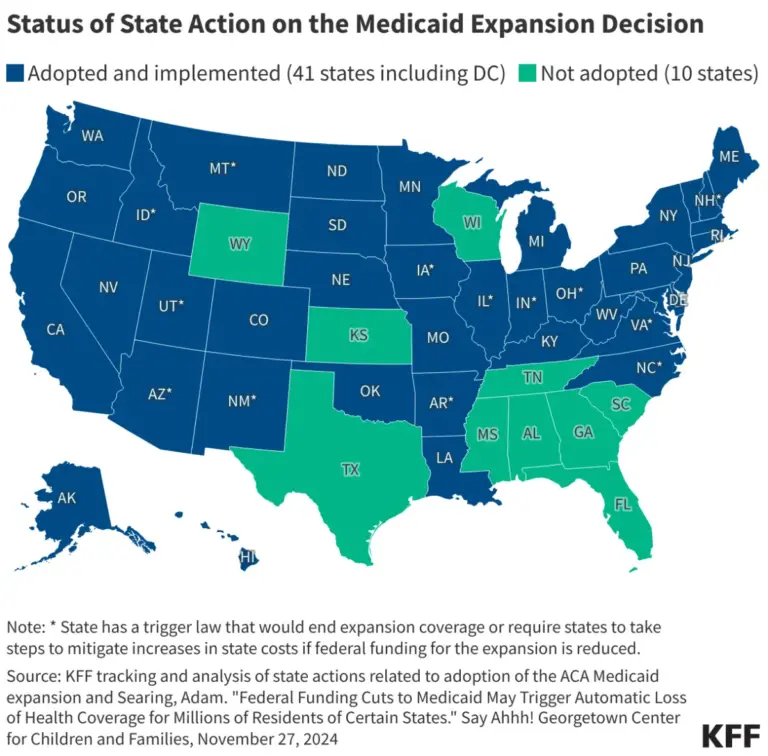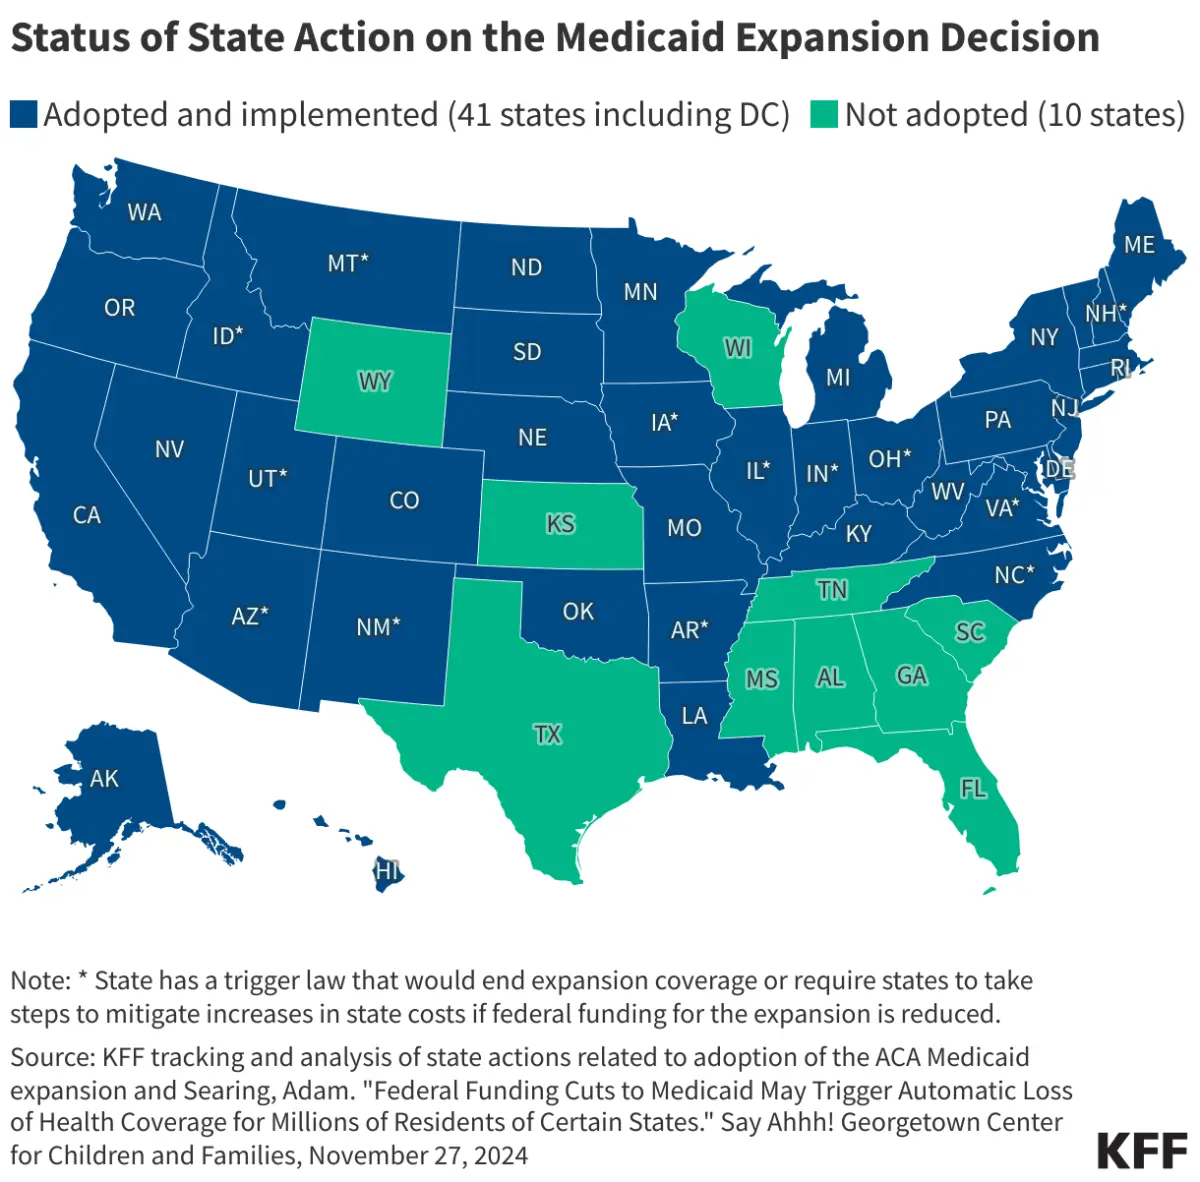
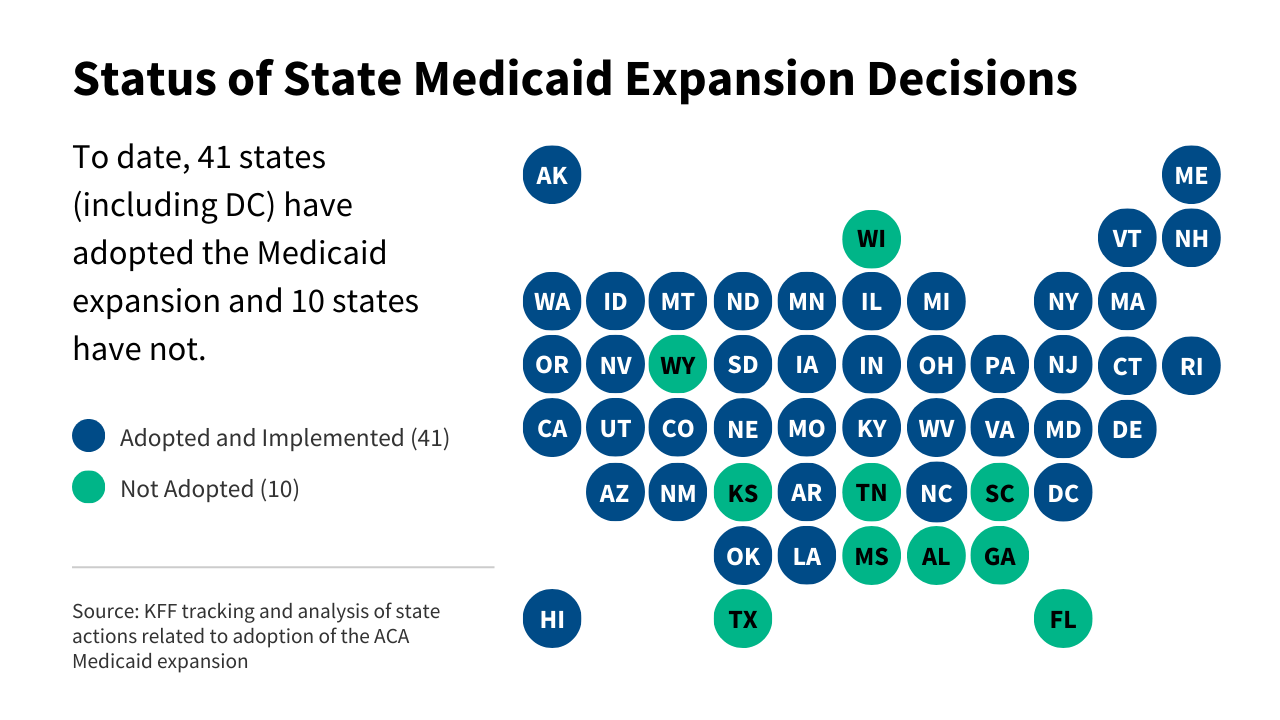
More than a decade after the Affordable Care Act (ACA) was signed into law, the landscape of American public health coverage remains defined by a stark, persistent geographic divide. At the heart of this divide is the Medicaid expansion—a policy cornerstone designed to provide a safety net for low-income adults. While 41 states and the District of Columbia have embraced the program, a core group of 10 states continues to resist, leaving millions of vulnerable citizens in a "coverage gap."
The Mechanics of Expansion: Defining the Policy
The ACA’s Medicaid expansion was designed to fundamentally alter the eligibility requirements for public health insurance. Prior to the ACA, Medicaid was largely restricted to specific categories of people: the elderly, the disabled, children, and pregnant women. The expansion dismantled these categorical requirements, extending coverage to nearly all adults with incomes up to 138% of the Federal Poverty Level.
In 2025, for a single individual, that income threshold stands at $21,597. To incentivize state participation, the federal government offered an enhanced Federal Medical Assistance Percentage (FMAP), which covers the vast majority of the costs associated with the newly eligible population. Despite these fiscal incentives, the decision to expand remains a matter of intense political, social, and economic debate, turning the Medicaid program into a barometer for regional health policy priorities.
Chronology: From Landmark Legislation to Current Deadlock
The journey of the Medicaid expansion has been marked by constitutional challenges, political shifts, and evolving state-level strategies.
2010–2012: The Foundation and the First Hurdle
When the ACA was passed in 2010, the expansion was initially framed as a mandatory requirement for all states. However, the 2012 Supreme Court ruling in National Federation of Independent Business v. Sebelius shifted the trajectory of the policy. The Court ruled that the federal government could not compel states to expand their Medicaid programs, effectively turning the expansion into a voluntary "opt-in" policy for state governments.
2013–2019: The Initial Wave of Adoption
Following the Supreme Court’s decision, the country split. Early adopters, primarily Democratic-leaning states, moved quickly to implement the expansion. By 2015, the benefits of expanded coverage—ranging from reduced uncompensated care costs for hospitals to improved health outcomes for patients—began to manifest in data, fueling further interest.
2020–Present: The "Holdout" Era
In recent years, the movement has slowed. The remaining 10 states that have not adopted the expansion are predominantly located in the South and the Midwest. These states often cite concerns over long-term fiscal sustainability and philosophical opposition to the expansion of government-funded healthcare programs. Meanwhile, states that have already expanded are now grappling with the administrative complexities of maintaining these programs, with some legislatures exploring "trigger laws" that would automatically scale back coverage if federal matching rates were ever reduced.
Supporting Data: Mapping the Geographic Divide
According to the latest tracking data from KFF, the current status of the nation is as follows:
- Expansion States: 41 (including DC).
- Non-Expansion States: 10.
The disparity is not merely a matter of numbers; it is a matter of demographics. The populations in non-expansion states often suffer from higher rates of chronic illness and lower access to primary care providers. For these individuals, the "coverage gap"—the space between earning too much to qualify for traditional Medicaid but too little to afford marketplace subsidies—remains a significant barrier to health equity.
The Role of "Trigger" Laws
A notable recent development in the discourse is the rise of "trigger" legislation. Several states, including South Dakota and West Virginia, have either implemented or debated laws that would automatically terminate their Medicaid expansion if the federal government were to lower the FMAP. This creates a climate of uncertainty for enrollees. In Virginia, for example, debates over budget amendments highlighted the tension between maintaining the expansion and preparing for potential federal funding volatility. These legislative maneuvers reflect a broader anxiety regarding the federal government’s long-term commitment to subsidizing state-level healthcare expansions.
Official Responses and Political Maneuvering
The debate over Medicaid expansion is rarely purely clinical; it is deeply political.
Proponents’ Arguments
Advocates of the expansion, including organizations like the Georgetown Center for Children and Families, emphasize the "human cost" of non-adoption. They point to data showing that expanded coverage leads to earlier cancer diagnoses, better management of diabetes, and lower maternal mortality rates. Furthermore, proponents argue that the economic benefits—such as federal funds flowing into state healthcare systems—provide a necessary stimulus to rural hospitals that are otherwise at risk of closure.
Critics’ Arguments
Opponents, including many state-level conservative lawmakers, argue that the expansion fosters dependency on federal aid. There is also a persistent concern regarding the "crowding out" of private insurance, where individuals move from employer-sponsored coverage to government-funded programs. Furthermore, the fiscal argument remains paramount: even with a 90% federal match, states are responsible for 10% of the costs, which opponents argue could divert funds from other critical state priorities like education or infrastructure.
The Implications: A System in Flux
The implications of the current Medicaid expansion landscape are profound and reach into every corner of the American healthcare system.
1. The Financial Impact on Providers
Hospitals, particularly those in rural or underserved urban areas, rely on Medicaid payments to sustain operations. In states that have not expanded, these facilities often absorb the cost of treating uninsured patients, leading to financial instability and, in some cases, total closure. This creates "healthcare deserts" that further exacerbate existing health disparities.
2. The Impact on Health Equity
The geographic variation in access to care means that one’s zip code is a primary determinant of their health. A low-income worker in a state like New York has access to a robust safety net, while a worker with identical income in a non-expansion state must navigate the system without the benefit of subsidized coverage. This inequity persists despite the clear evidence that Medicaid expansion improves the financial health of low-income families by preventing medical bankruptcies.
3. The Future of Section 1115 Waivers
As the political debate continues, states are increasingly turning to Section 1115 waivers to customize their Medicaid programs. These waivers allow states to test new models of coverage, sometimes including work requirements or premiums for certain populations. While these efforts are framed as a way to make Medicaid more "market-oriented," they often serve as a middle ground for states that are ideologically opposed to full expansion but face pressure to address their citizens’ healthcare needs.
Conclusion: A Long Road Ahead
The status of Medicaid expansion in the United States is a testament to the complexities of federalism. While the ACA established a national framework for reform, the implementation remains deeply fragmented by state-level politics. The existence of 10 non-expansion states is not a static reality; it is a dynamic political environment where ballot initiatives, legislative sessions, and executive orders continue to shape the outcome.
As we move deeper into the next decade, the pressure on these 10 states will likely continue to mount. Factors such as the aging of the population, the rising costs of medical technology, and the ongoing advocacy for equitable healthcare access will force a re-evaluation of the current status quo. Whether through voter-led ballot initiatives—a mechanism that has successfully bypassed legislative resistance in several states—or through shifting political tides, the expansion of the American safety net remains an unfinished project.
For the millions of individuals currently caught in the coverage gap, the data provided by organizations like KFF and the Georgetown Center for Children and Families is more than just a map or a spreadsheet; it is a map of the obstacles between them and a healthier, more secure life. Until a consensus is reached, the divide will continue to be one of the most significant challenges facing the American public health infrastructure.
About the Author