Published: October 8, 2025

Medicare, the bedrock of American health security for seniors and individuals with disabilities, stands at a critical juncture in 2025. Established in 1965 under Title XVIII of the Social Security Act, the program has evolved from a basic hospital insurance scheme into a multifaceted, trillion-dollar enterprise covering 68 million Americans. As the U.S. population ages and health care delivery models shift, the program faces unprecedented financial, structural, and demographic pressures.

The Evolution of Medicare: A Chronology
The trajectory of Medicare reflects the changing landscape of American medicine:
- 1965: Medicare is signed into law, providing universal health coverage for Americans aged 65 and older.
- 1972: Eligibility is expanded to include individuals under 65 with long-term disabilities, as well as those with End-Stage Renal Disease (ESRD).
- 2003: The Medicare Modernization Act (MMA) is passed, introducing Part D—the voluntary prescription drug benefit that fundamentally changed how beneficiaries access medications.
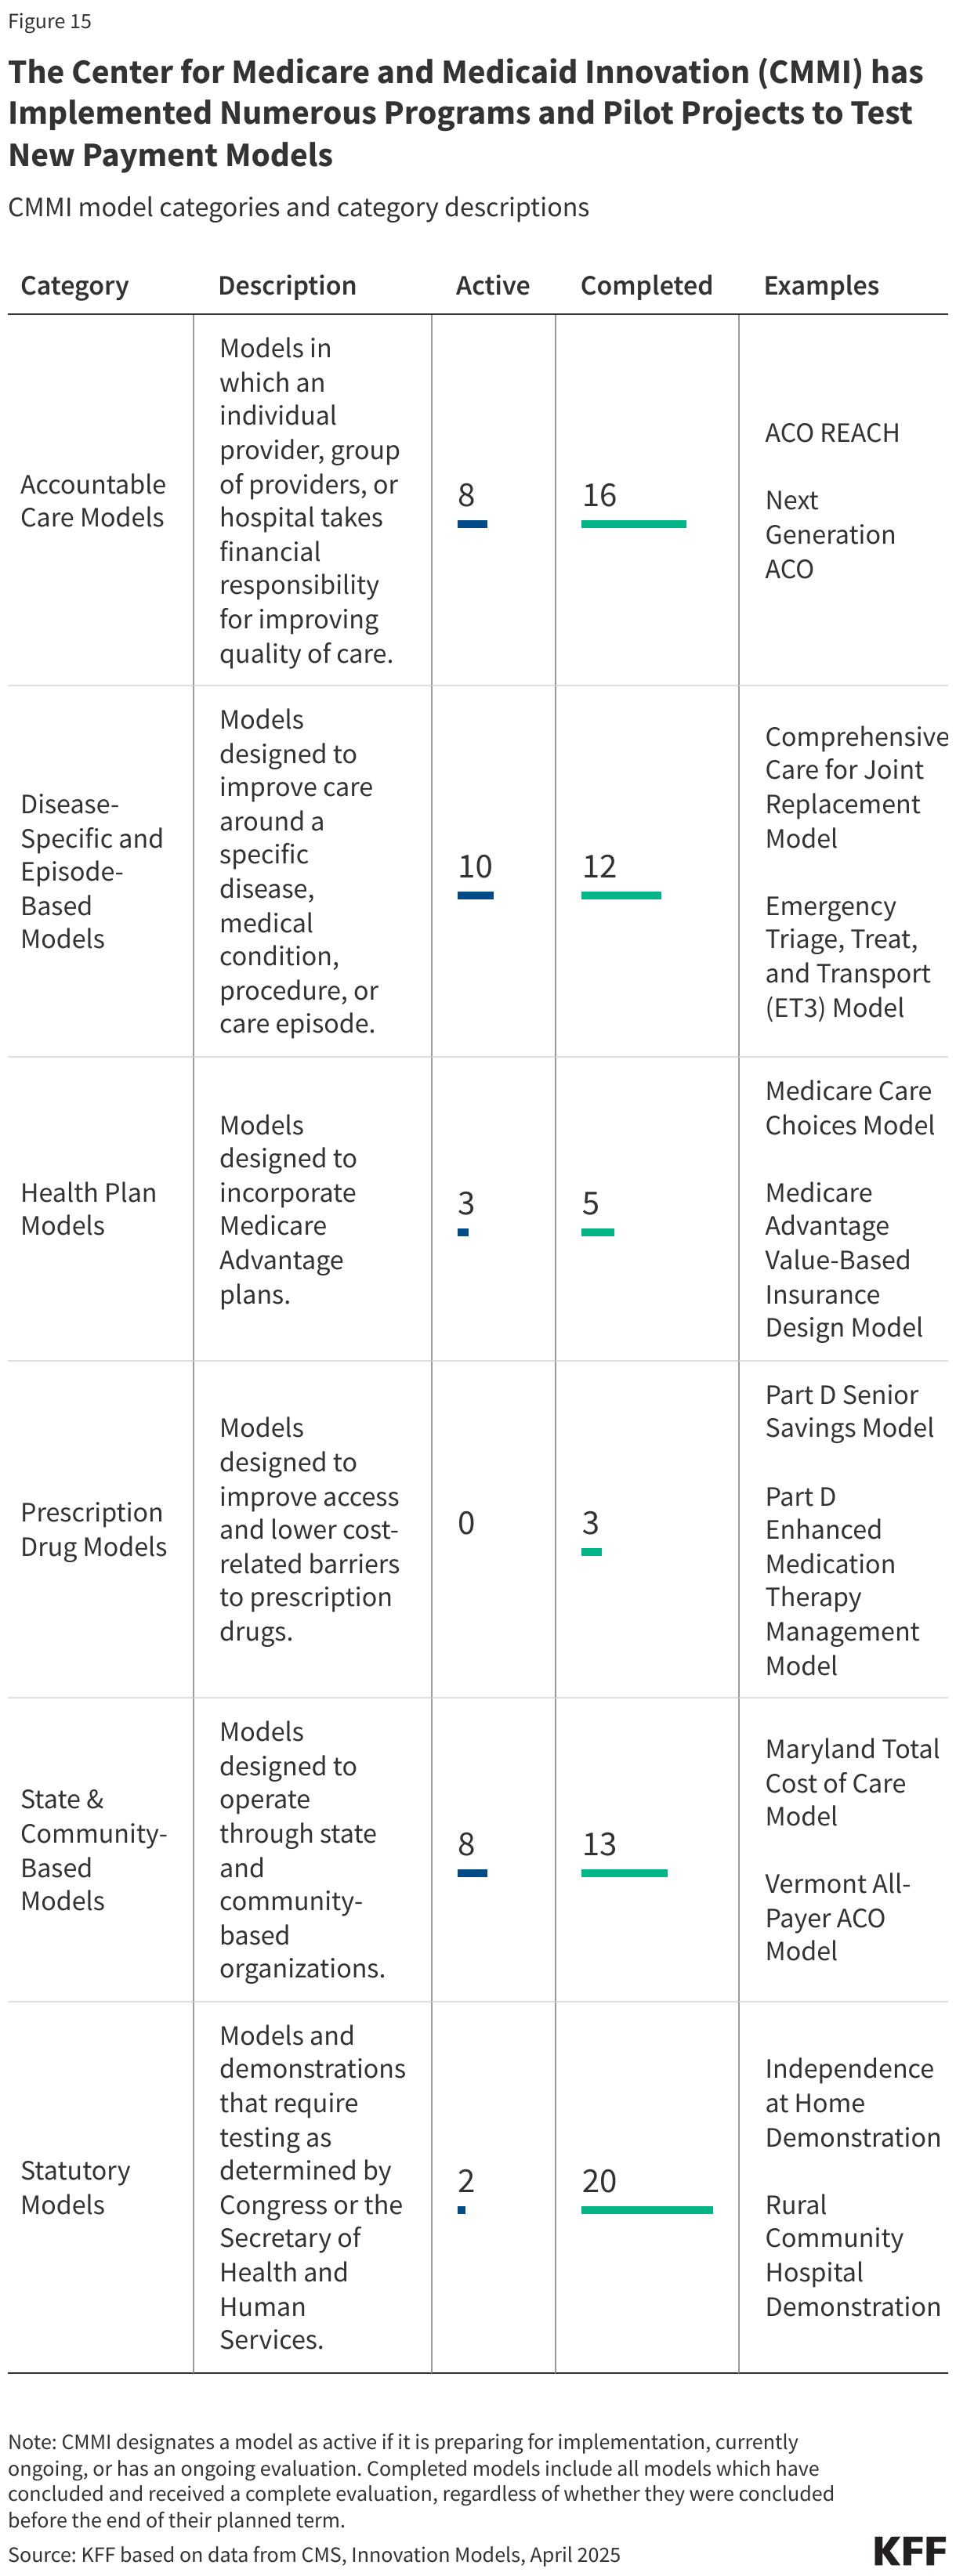
- 2010: The Affordable Care Act (ACA) establishes the Center for Medicare and Medicaid Innovation (CMMI) to test new payment models aimed at curbing costs while improving quality.
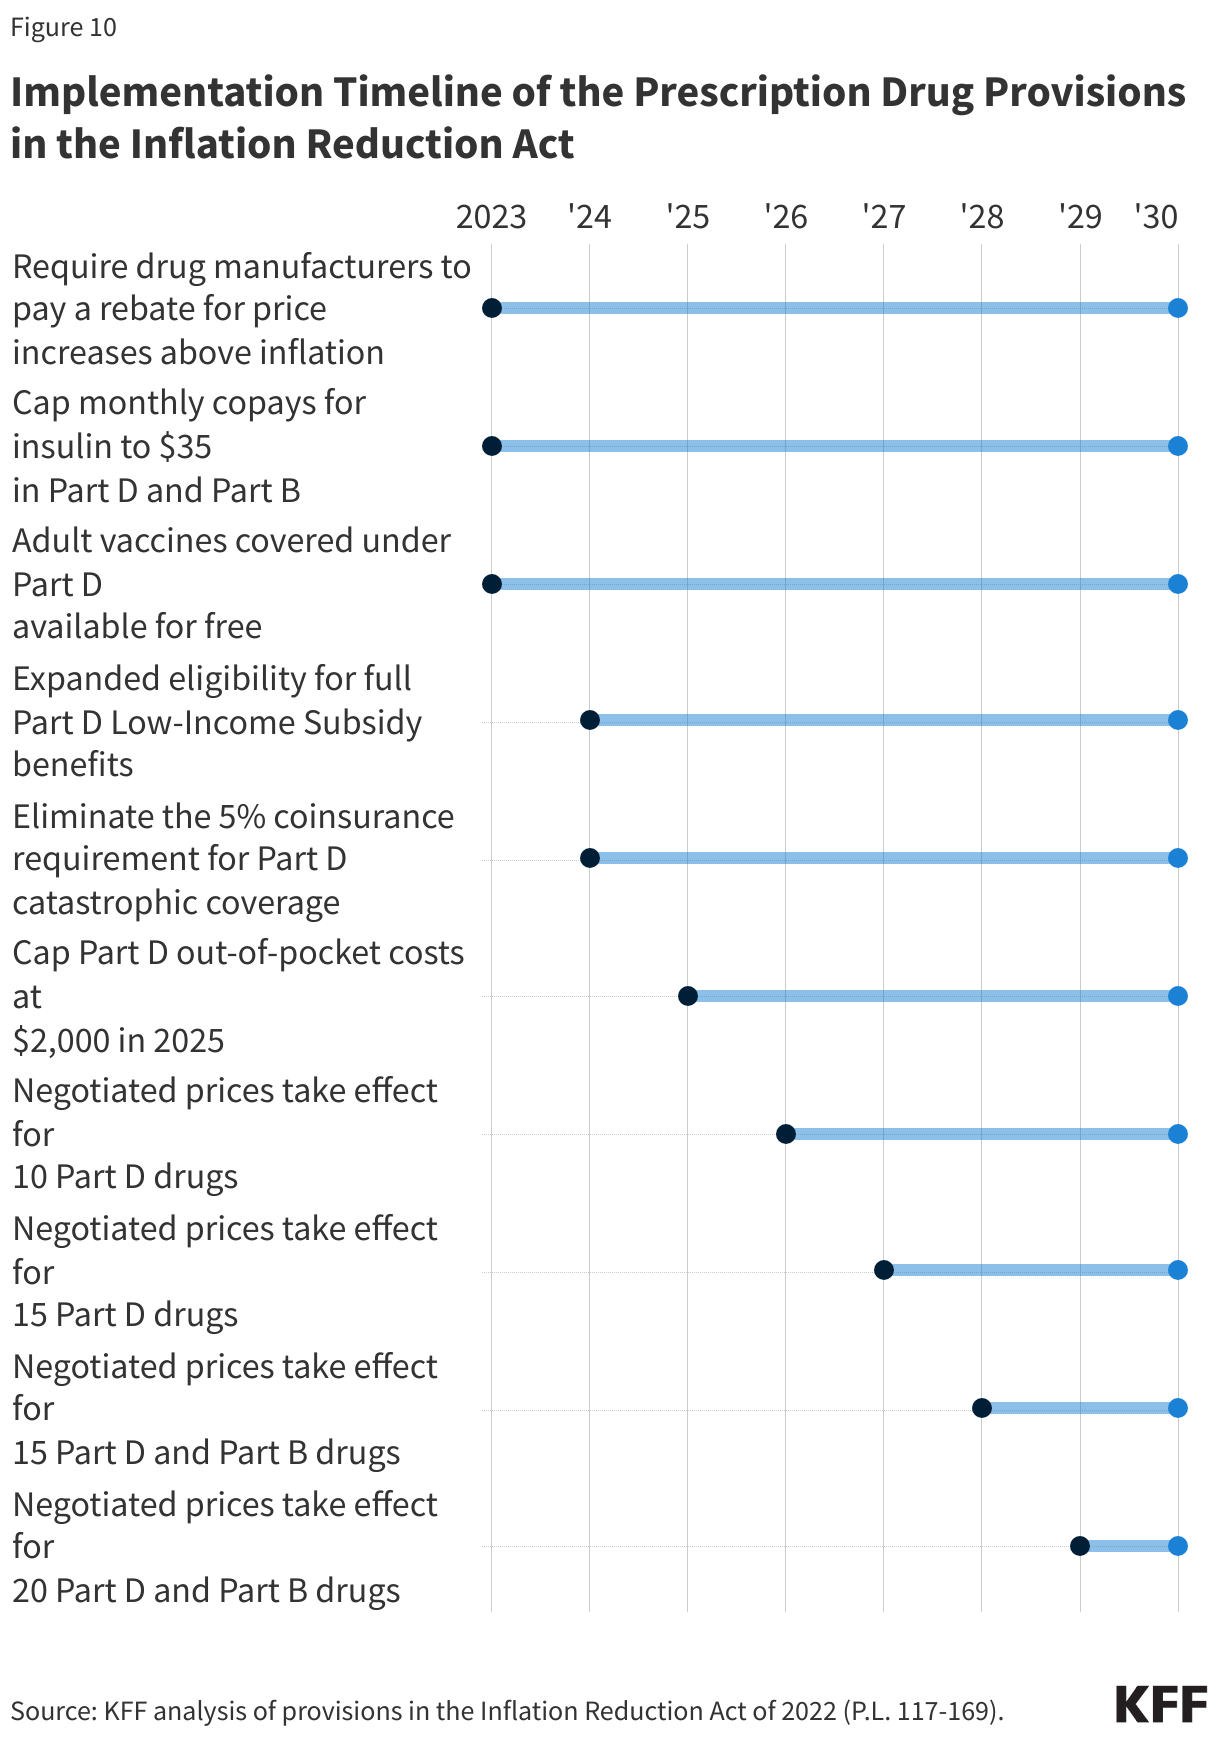
- 2022: The Inflation Reduction Act (IRA) introduces landmark drug pricing reforms, including the $2,000 out-of-pocket cap for Part D enrollees and new government negotiation powers.
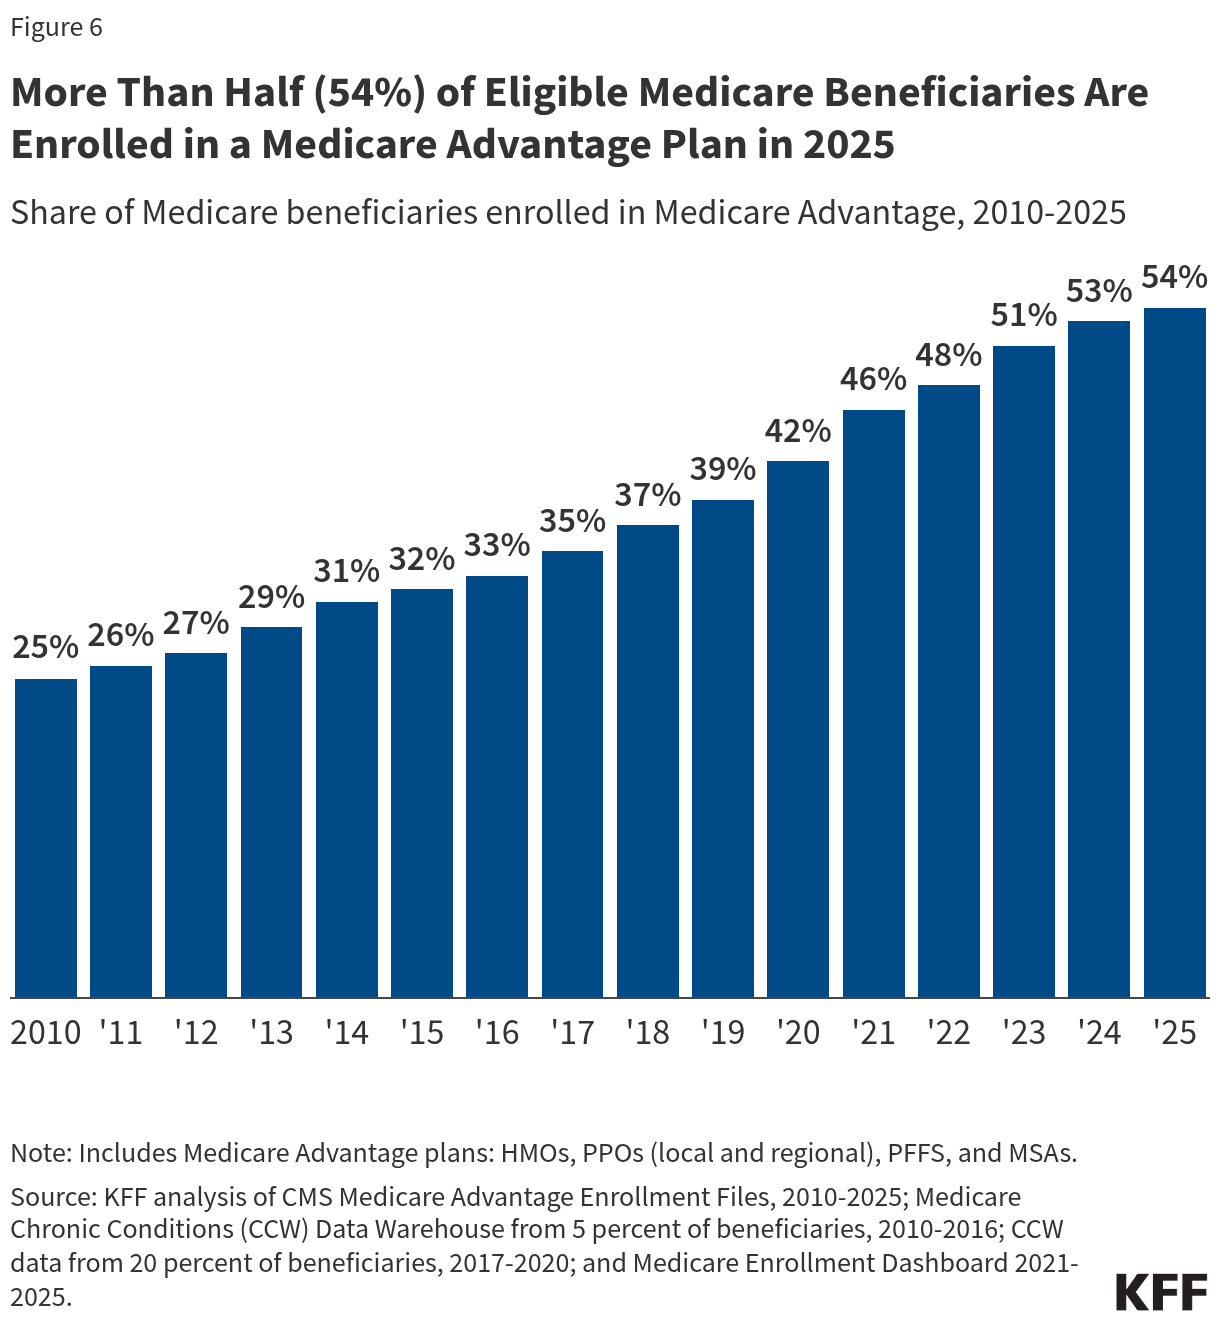
- 2025: Medicare Advantage (MA) enrollment reaches a historic high, with 54% of eligible beneficiaries opting for private plans over traditional fee-for-service Medicare.
Core Facts: Who Is Covered and What Is Provided?
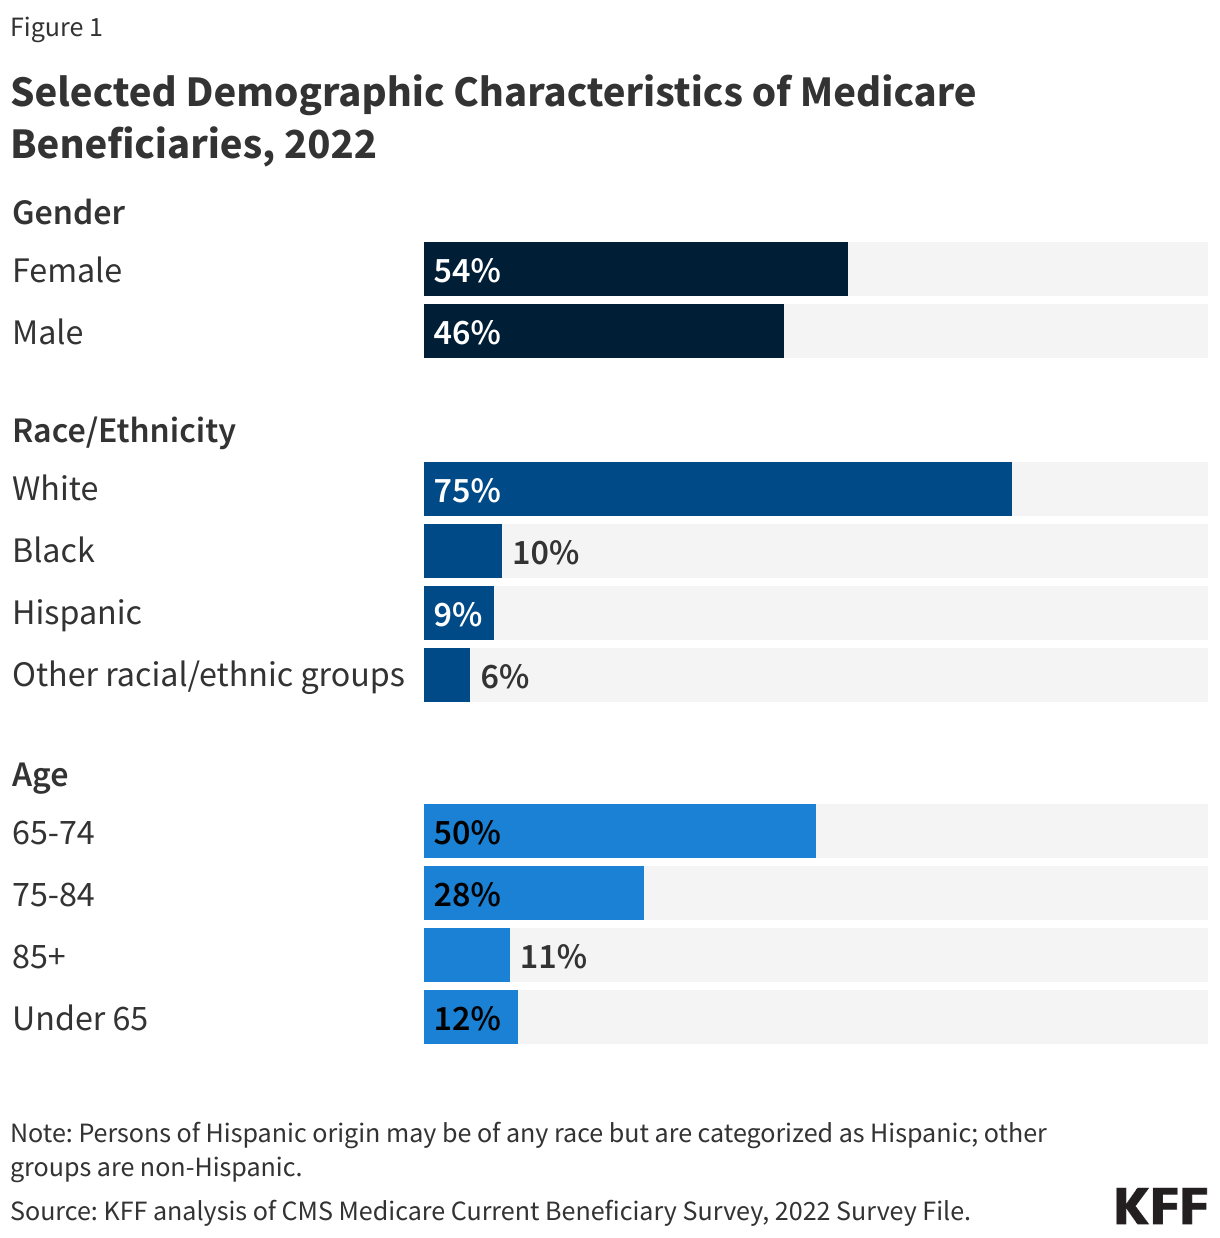
Medicare today is a diverse, massive ecosystem. Of its 68 million beneficiaries, 61 million are aged 65 or older, while 7 million are younger individuals with disabilities. Despite its ubiquity, the program is not a monolithic entity.
The Benefit Structure
Medicare is divided into four distinct components:
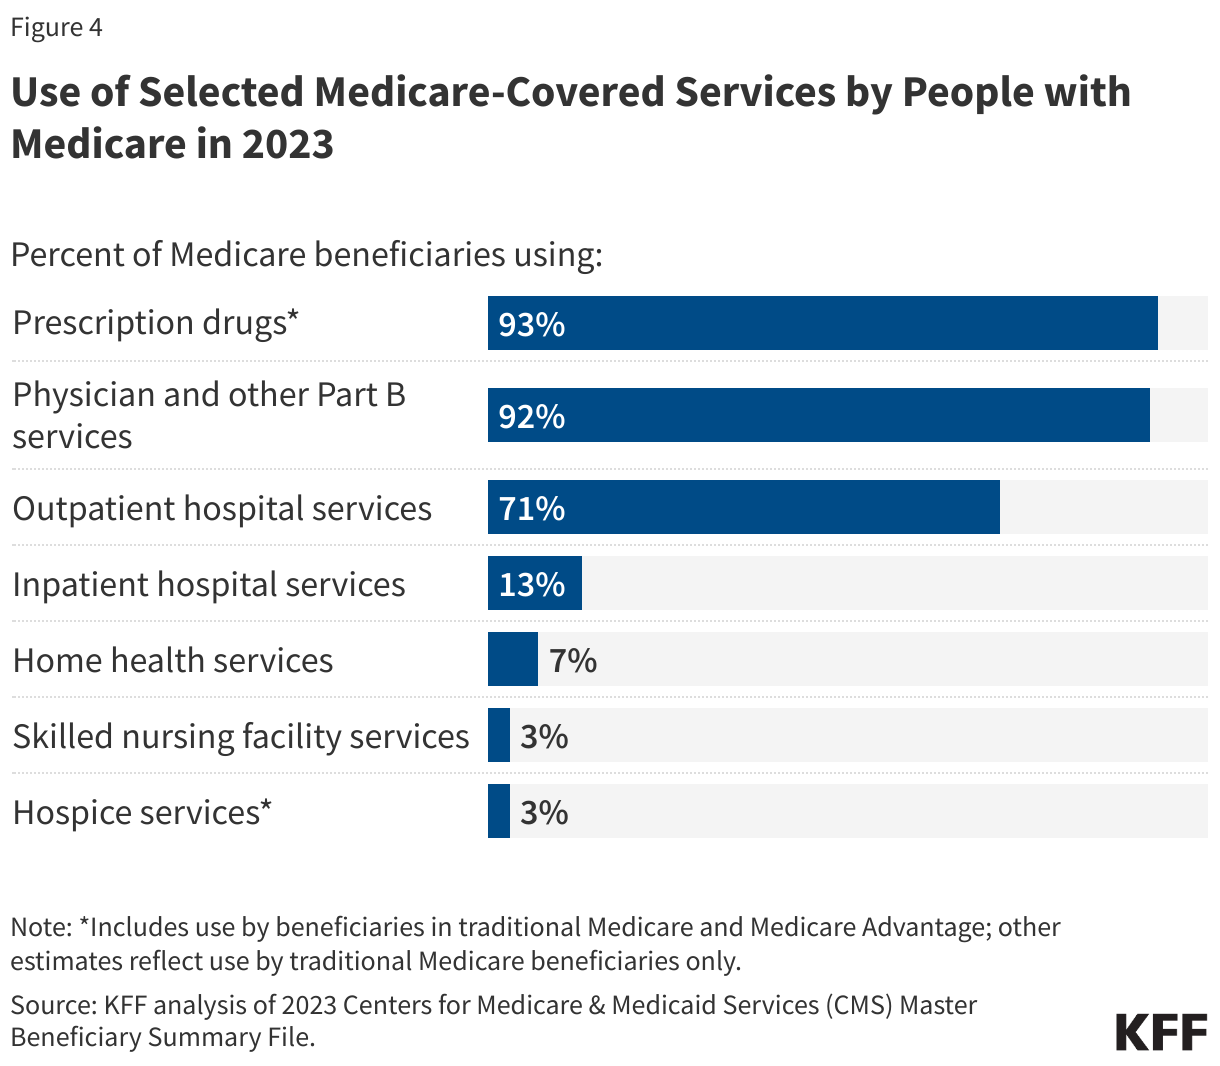
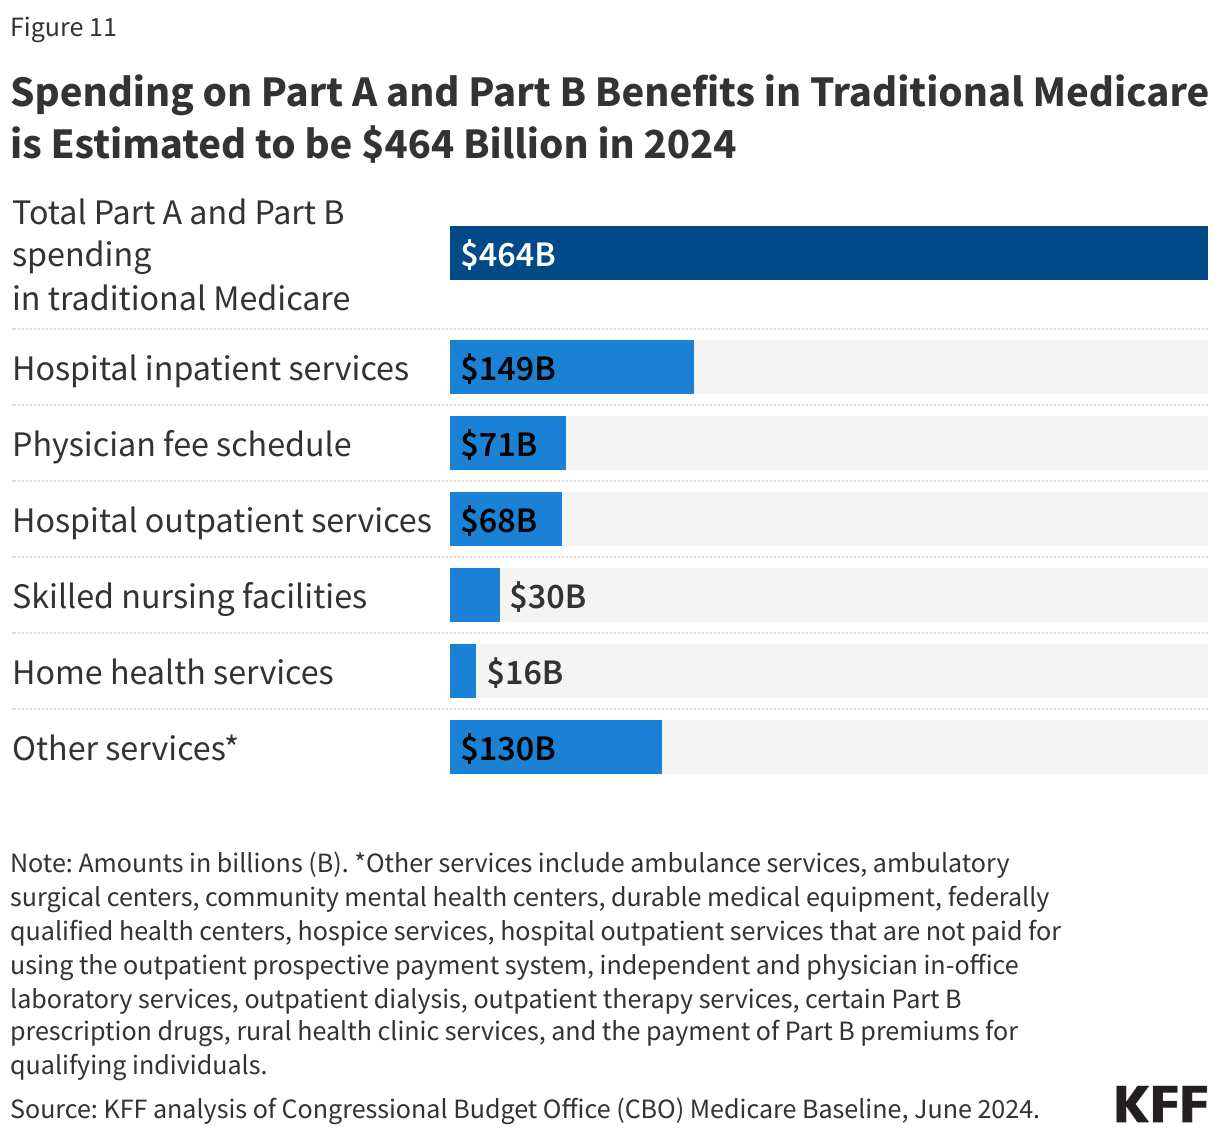
- Part A (Hospital Insurance): Covers inpatient hospital stays, skilled nursing facility care, hospice, and some home health care.
- Part B (Medical Insurance): Covers physician visits, outpatient care, medical supplies, and preventive services.
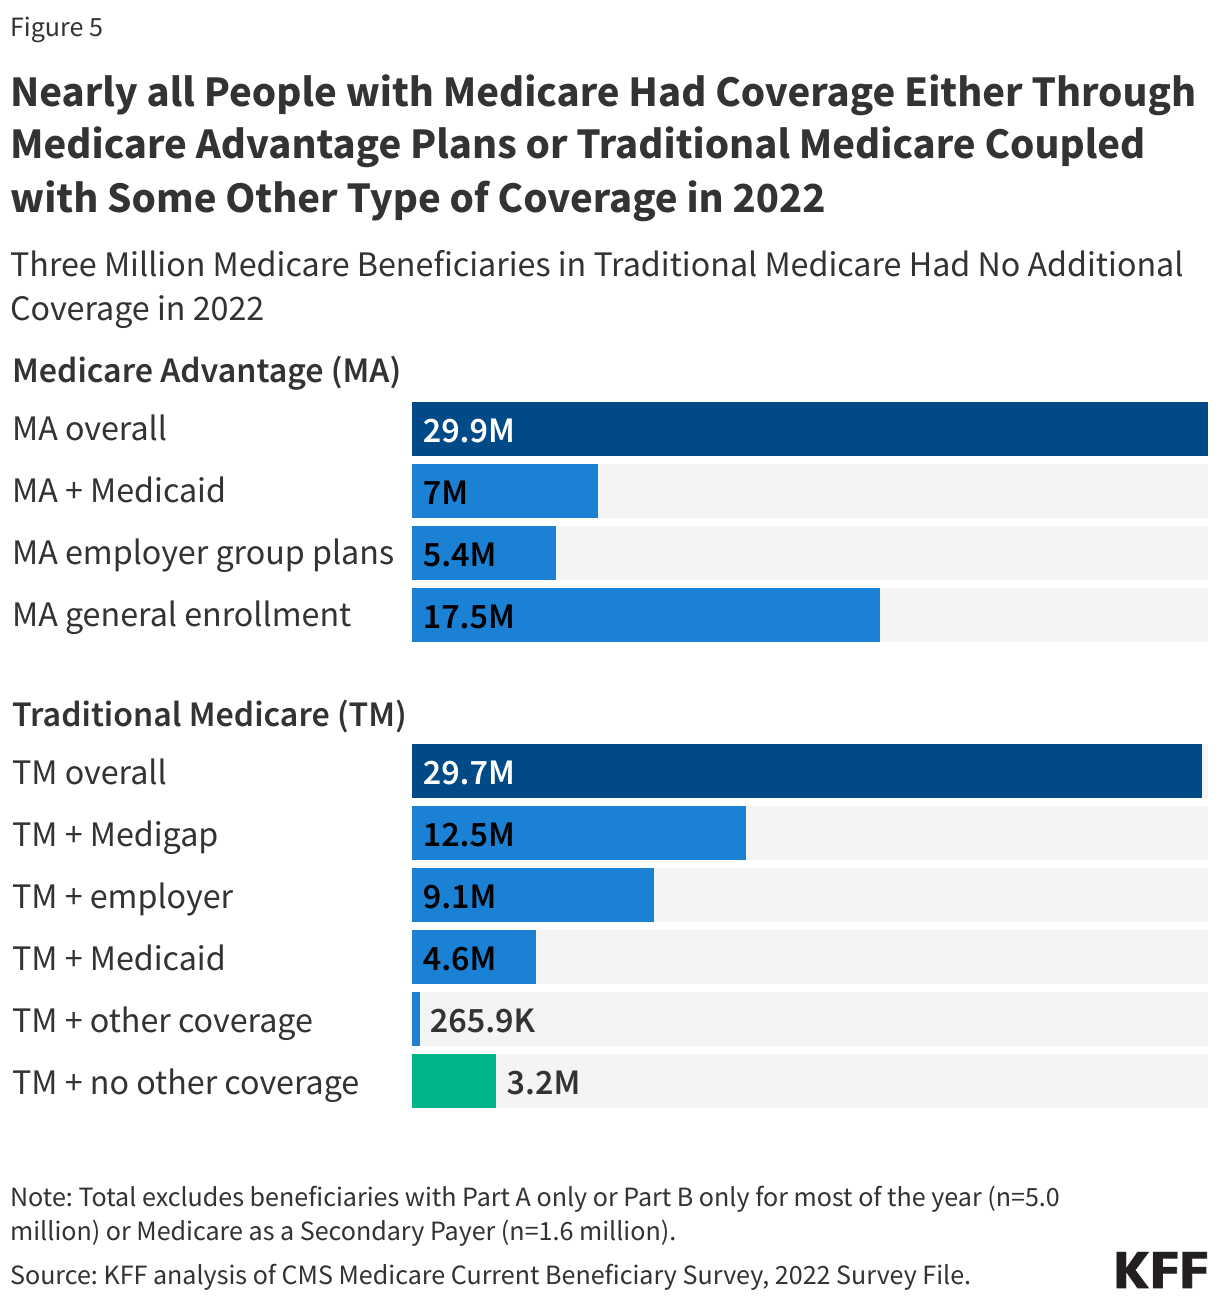
- Part C (Medicare Advantage): Private plans that provide all Part A and B benefits, often bundled with Part D.
- Part D (Prescription Drugs): A voluntary benefit providing outpatient drug coverage through private insurance.
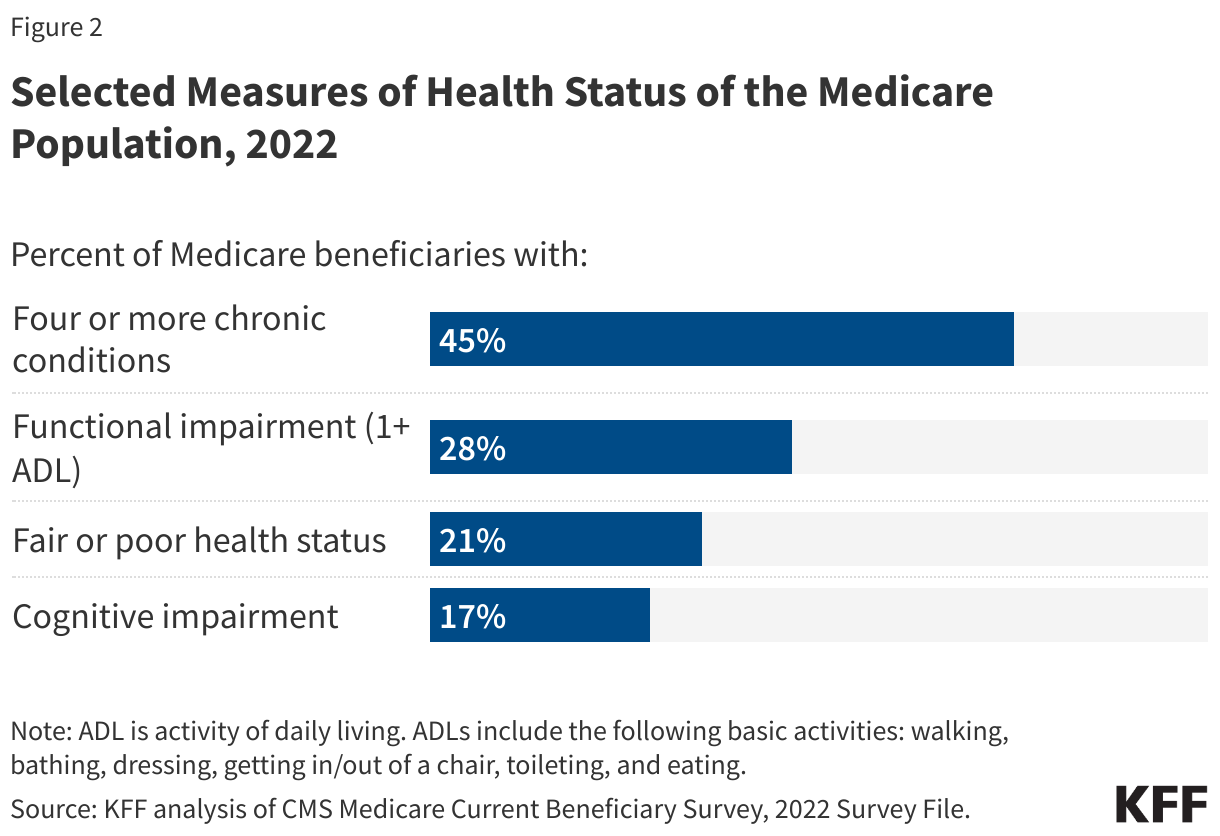
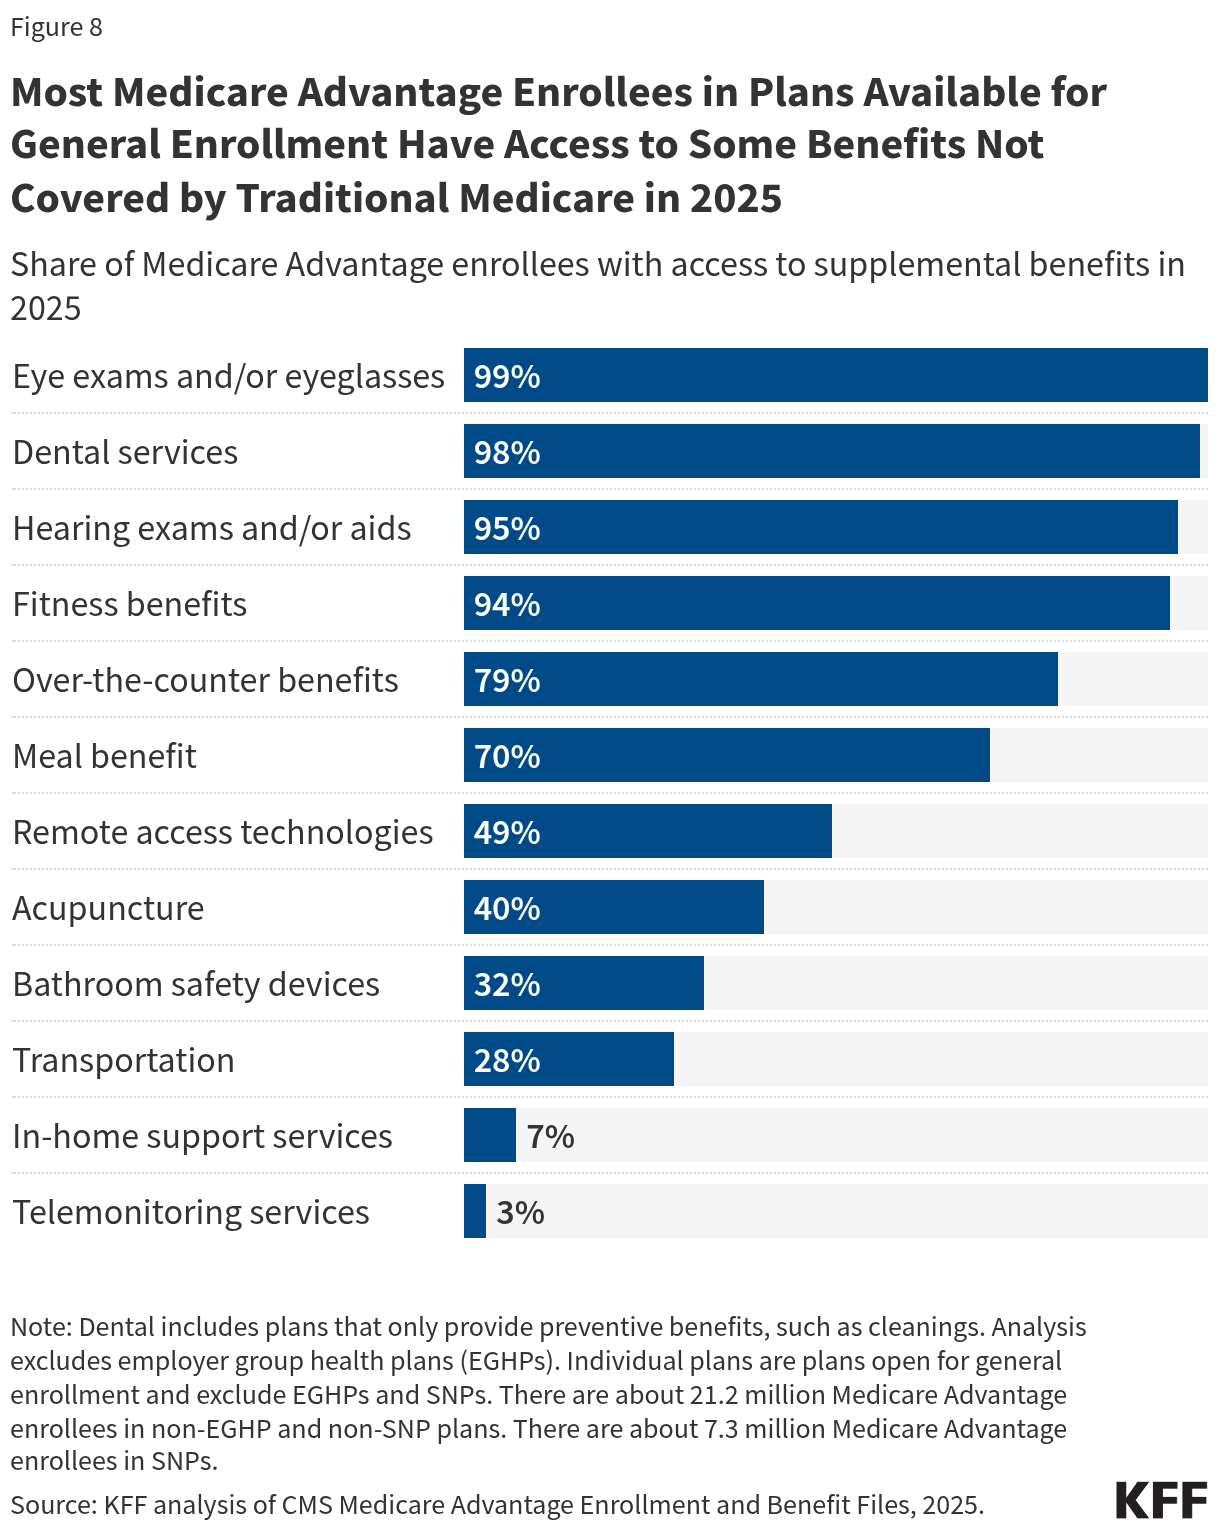
Despite this coverage, Medicare famously lacks a standard benefit for long-term care, dental, hearing, or vision services, leading many to seek supplemental coverage through Medigap or Medicare Advantage plans.
Supporting Data: The Financial and Demographic Landscape
The financial viability of Medicare is tethered to the health of the U.S. economy and the demographic reality of an aging "Baby Boomer" generation.
Enrollment Projections
By 2060, the share of the U.S. population aged 65 and older is expected to climb to 24%. Consequently, the number of Medicare beneficiaries is projected to surge from 68 million today to over 93 million. This population is also becoming increasingly diverse; by 2060, people of color will constitute 44% of the Medicare-eligible demographic, up from 25% in 2022.
Economic Burden
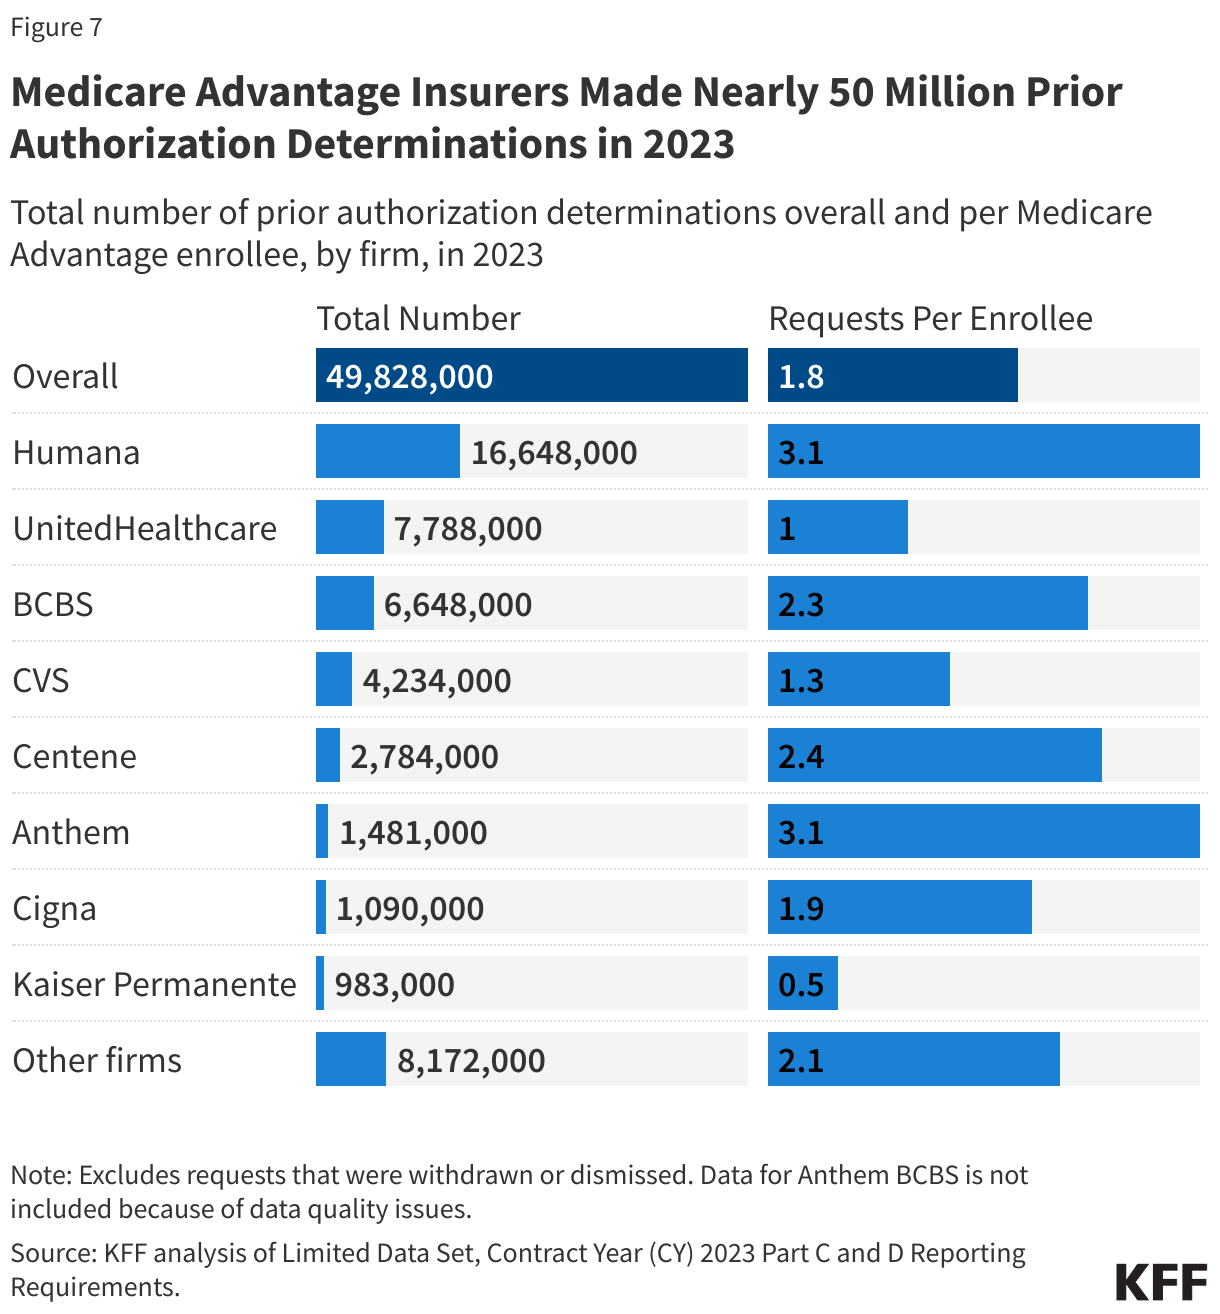
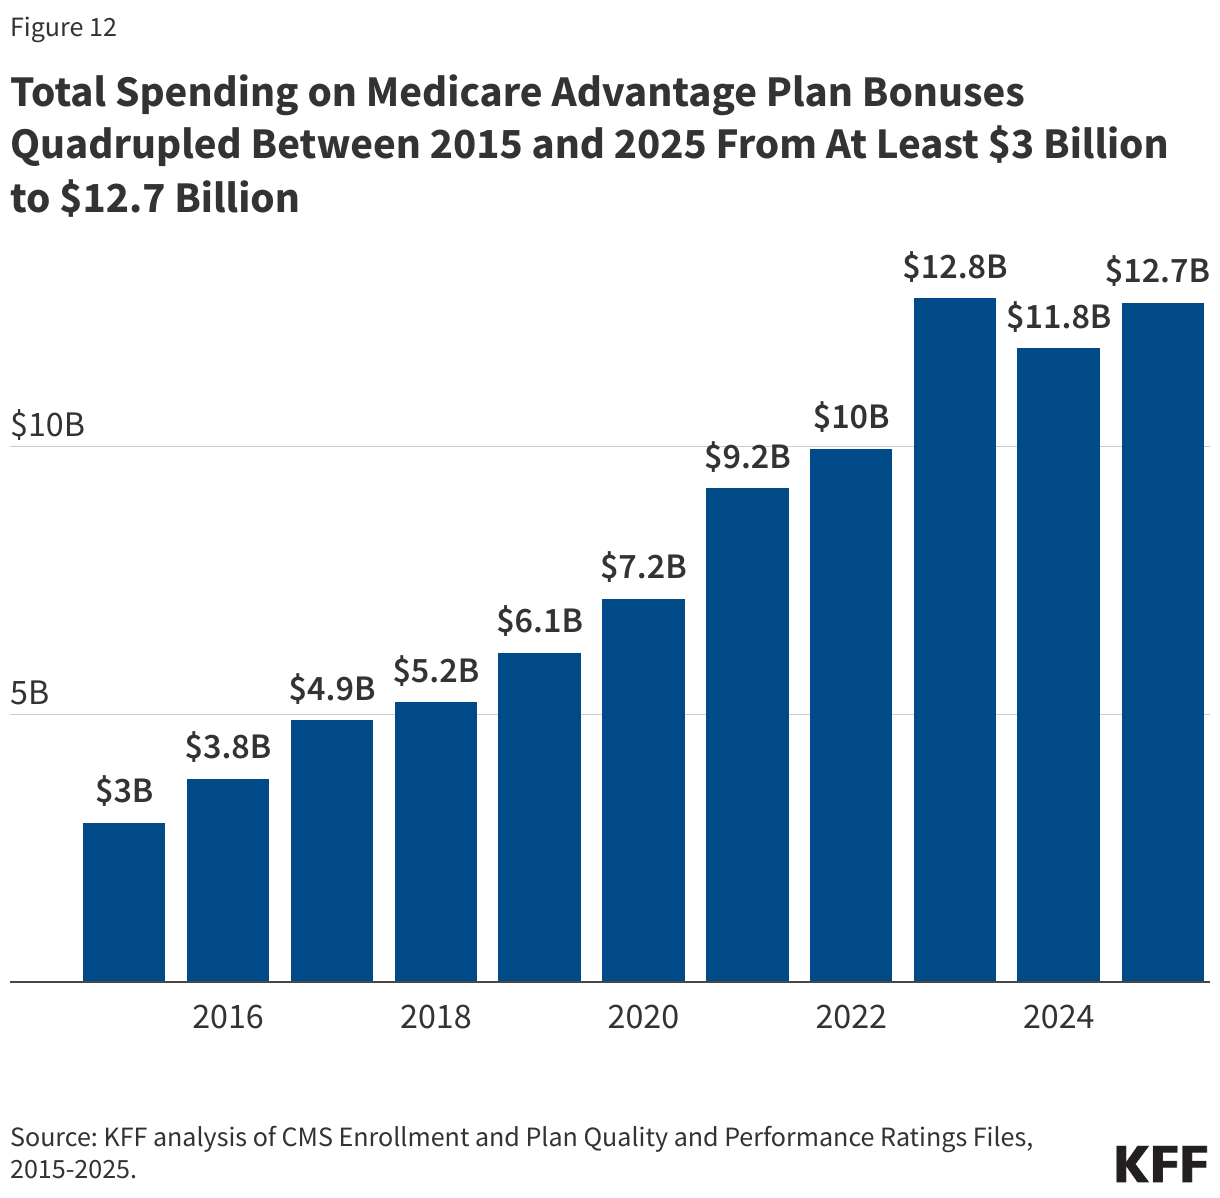
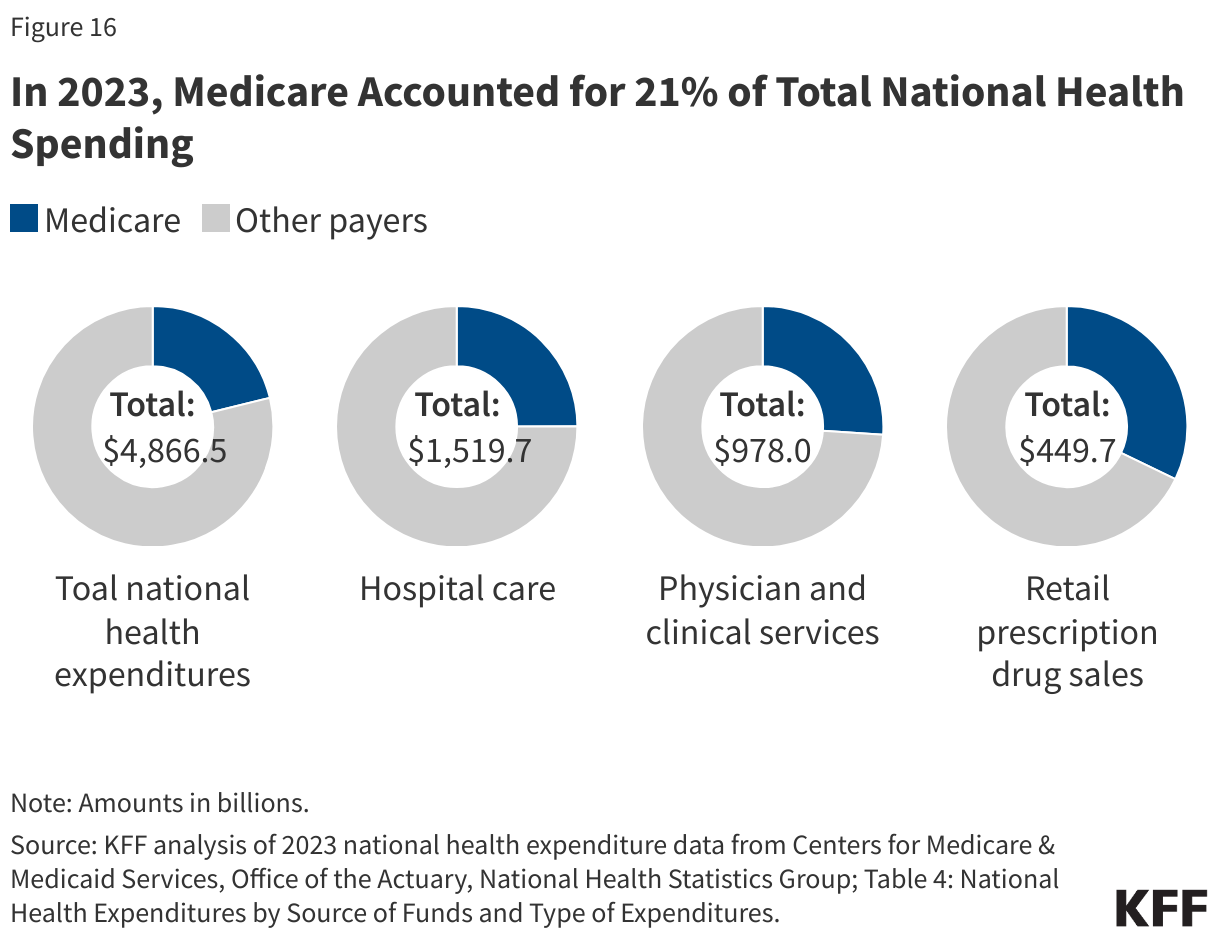
Medicare spending in 2024 accounted for 13.5% of the total federal budget. As the program grows, spending per capita has risen from $5,800 in 2000 to $16,700 in 2023. A significant portion of this growth is driven by the rise of Medicare Advantage. While proponents argue that MA plans offer better coordination, the Medicare Payment Advisory Commission (MedPAC) reports that the government pays MA plans roughly 120% of what it would cost to cover similar beneficiaries in traditional fee-for-service Medicare. These "excess" payments, totaling an estimated $84 billion in 2025 due to coding intensity, contribute to higher Part B premiums for all beneficiaries and strain the Hospital Insurance Trust Fund.
The Part A Trust Fund Crisis
The Hospital Insurance (HI) Trust Fund, which funds Part A, remains a primary concern for policymakers. As of 2025, Medicare actuaries project that reserves will be depleted by 2033. At that point, without legislative intervention, the program would only be able to cover approximately 89% of costs through payroll tax revenue.
The Shift Toward Alternative Payment Models
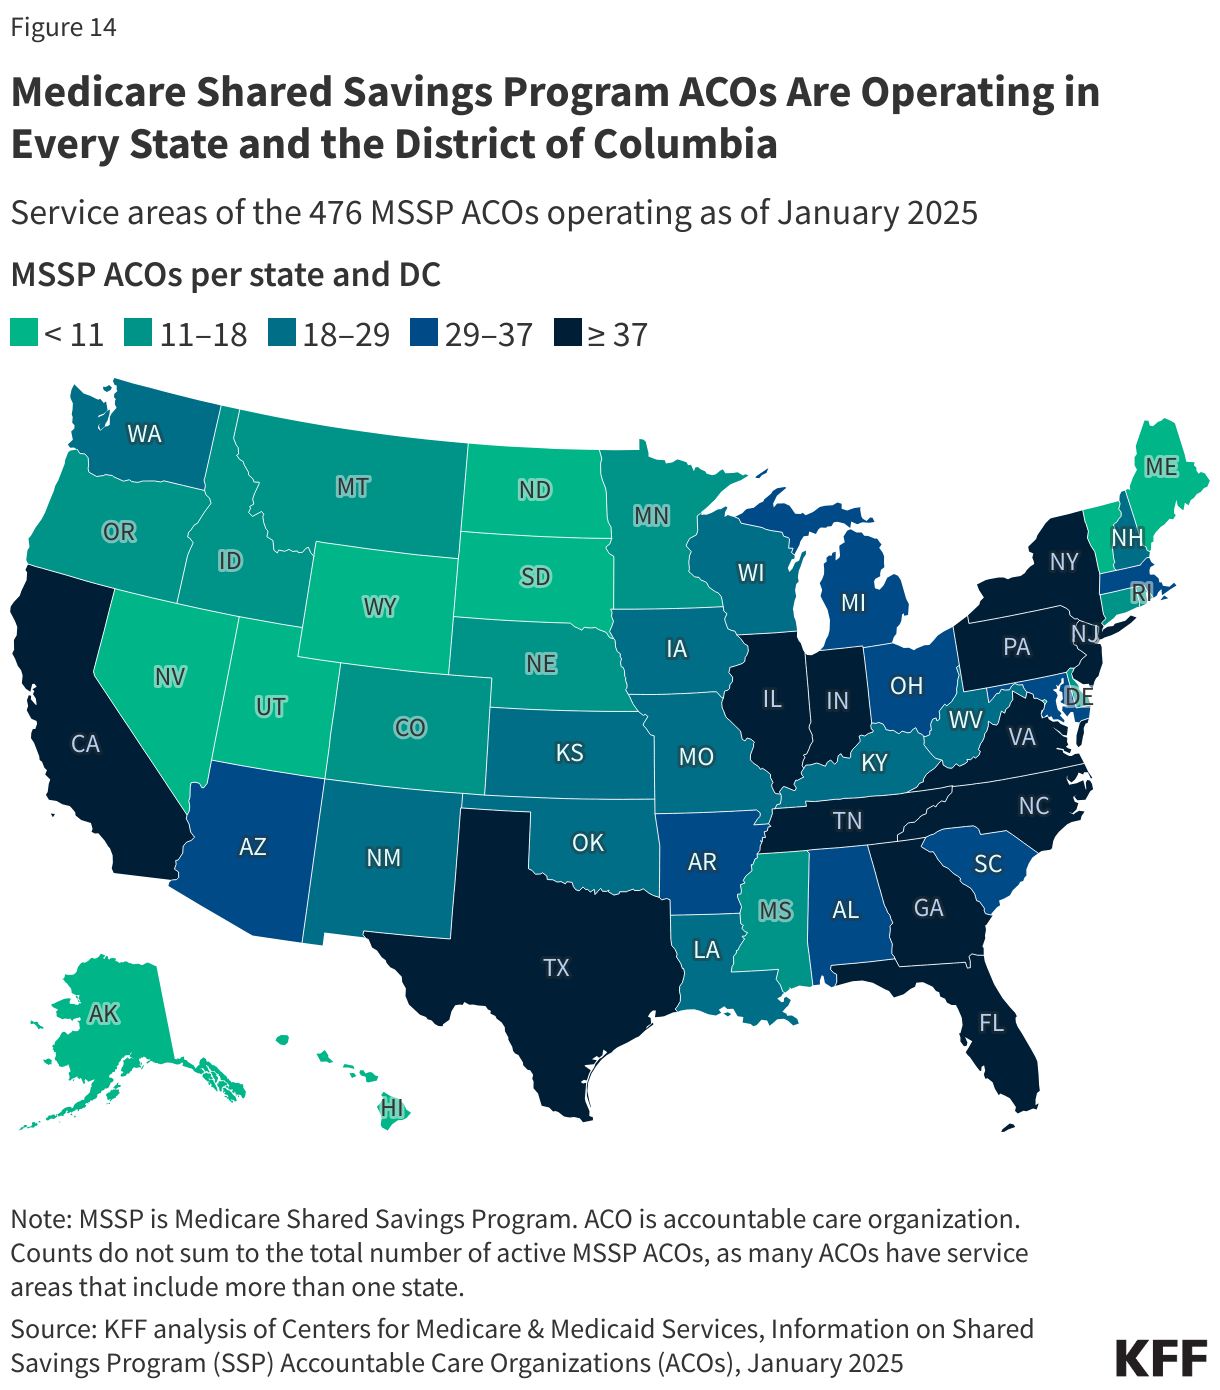
In an effort to move away from the "volume-based" fee-for-service model, Medicare has increasingly turned to "value-based" care. The Medicare Shared Savings Program (MSSP) and the Center for Medicare and Medicaid Innovation (CMMI) are at the forefront of this transition.
In 2023, the MSSP saved the program $2.1 billion. These models encourage providers to form Accountable Care Organizations (ACOs), where they share in the financial risk and reward of managing patient health. While CMMI has launched over 80 models since 2010, the Congressional Budget Office (CBO) notes that their success in generating net savings has been mixed, with high upfront implementation costs often offsetting initial gains.
Official Responses and Strategic Directions
The management of Medicare is highly sensitive to shifts in federal leadership. The current administration has prioritized:
- Health Equity: Ensuring that CMMI models address disparities in care for minority populations.
- Preventive Care: Emphasizing evidence-based interventions to reduce chronic disease prevalence.
- Market Competition: Encouraging the growth of private plan alternatives while attempting to curb "excess" payments through updated risk-adjustment methodologies.
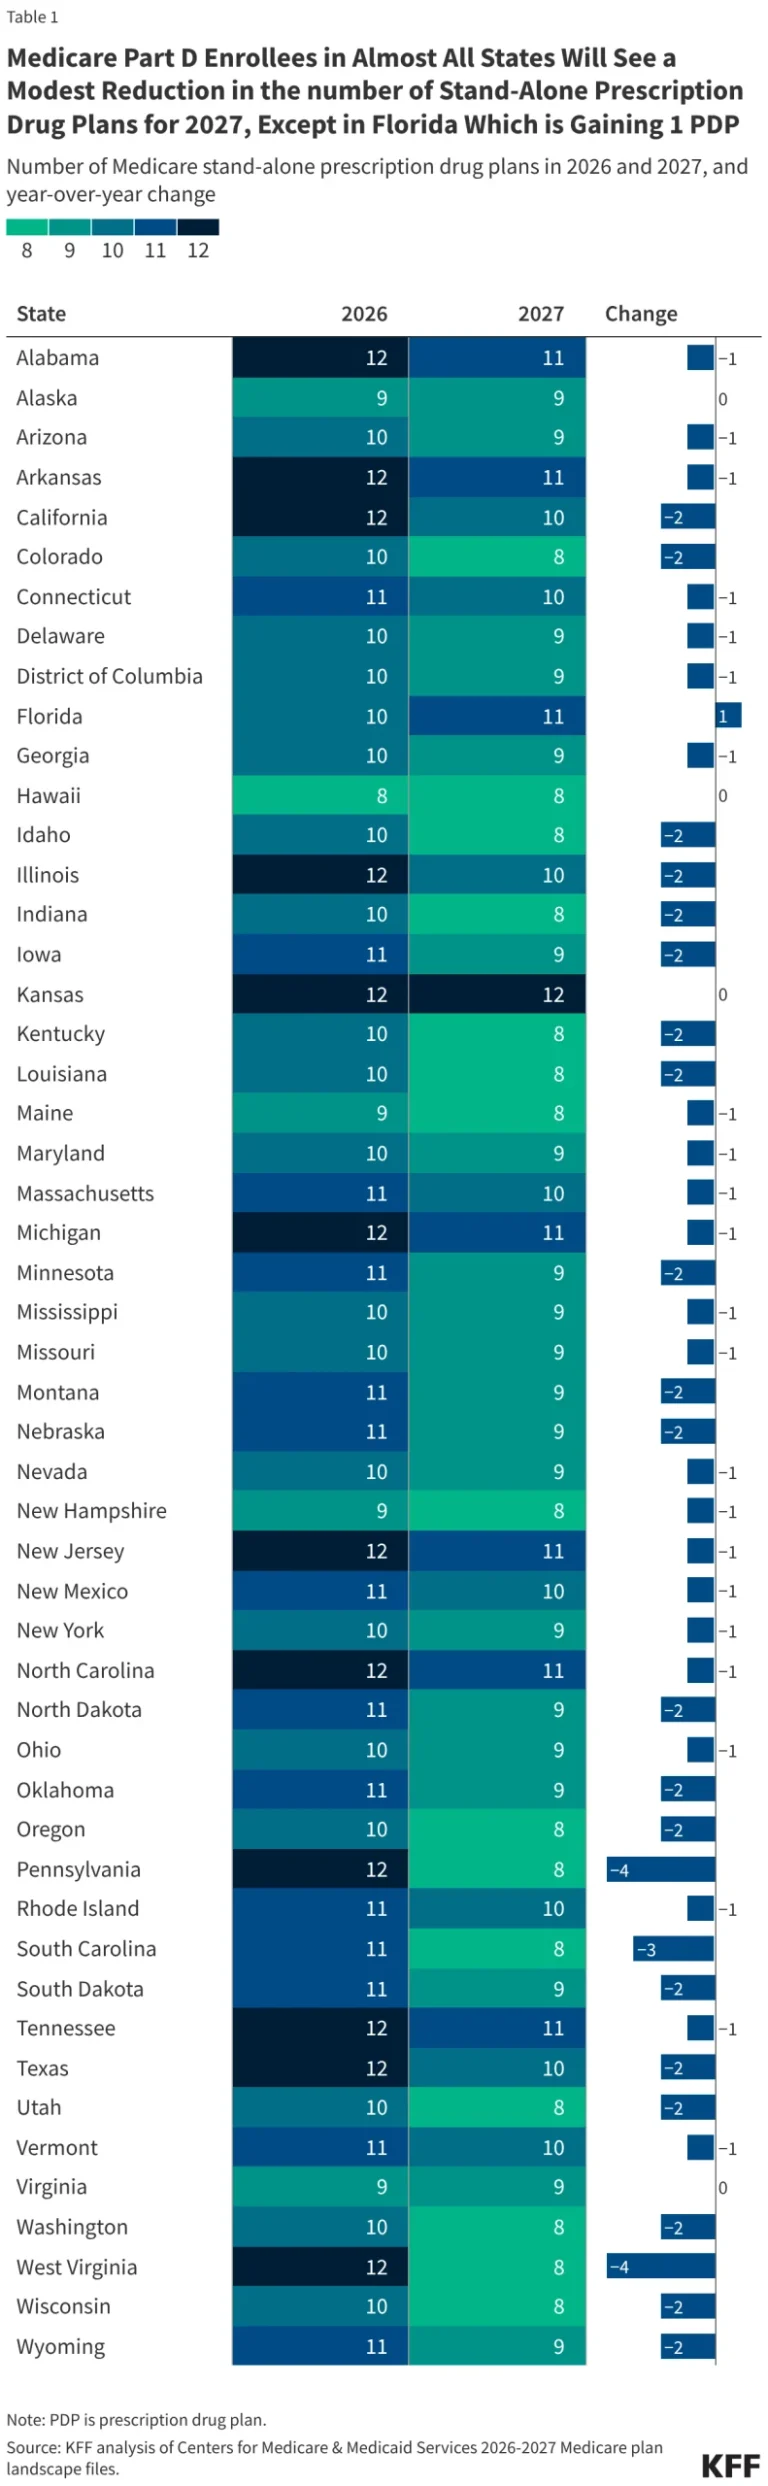
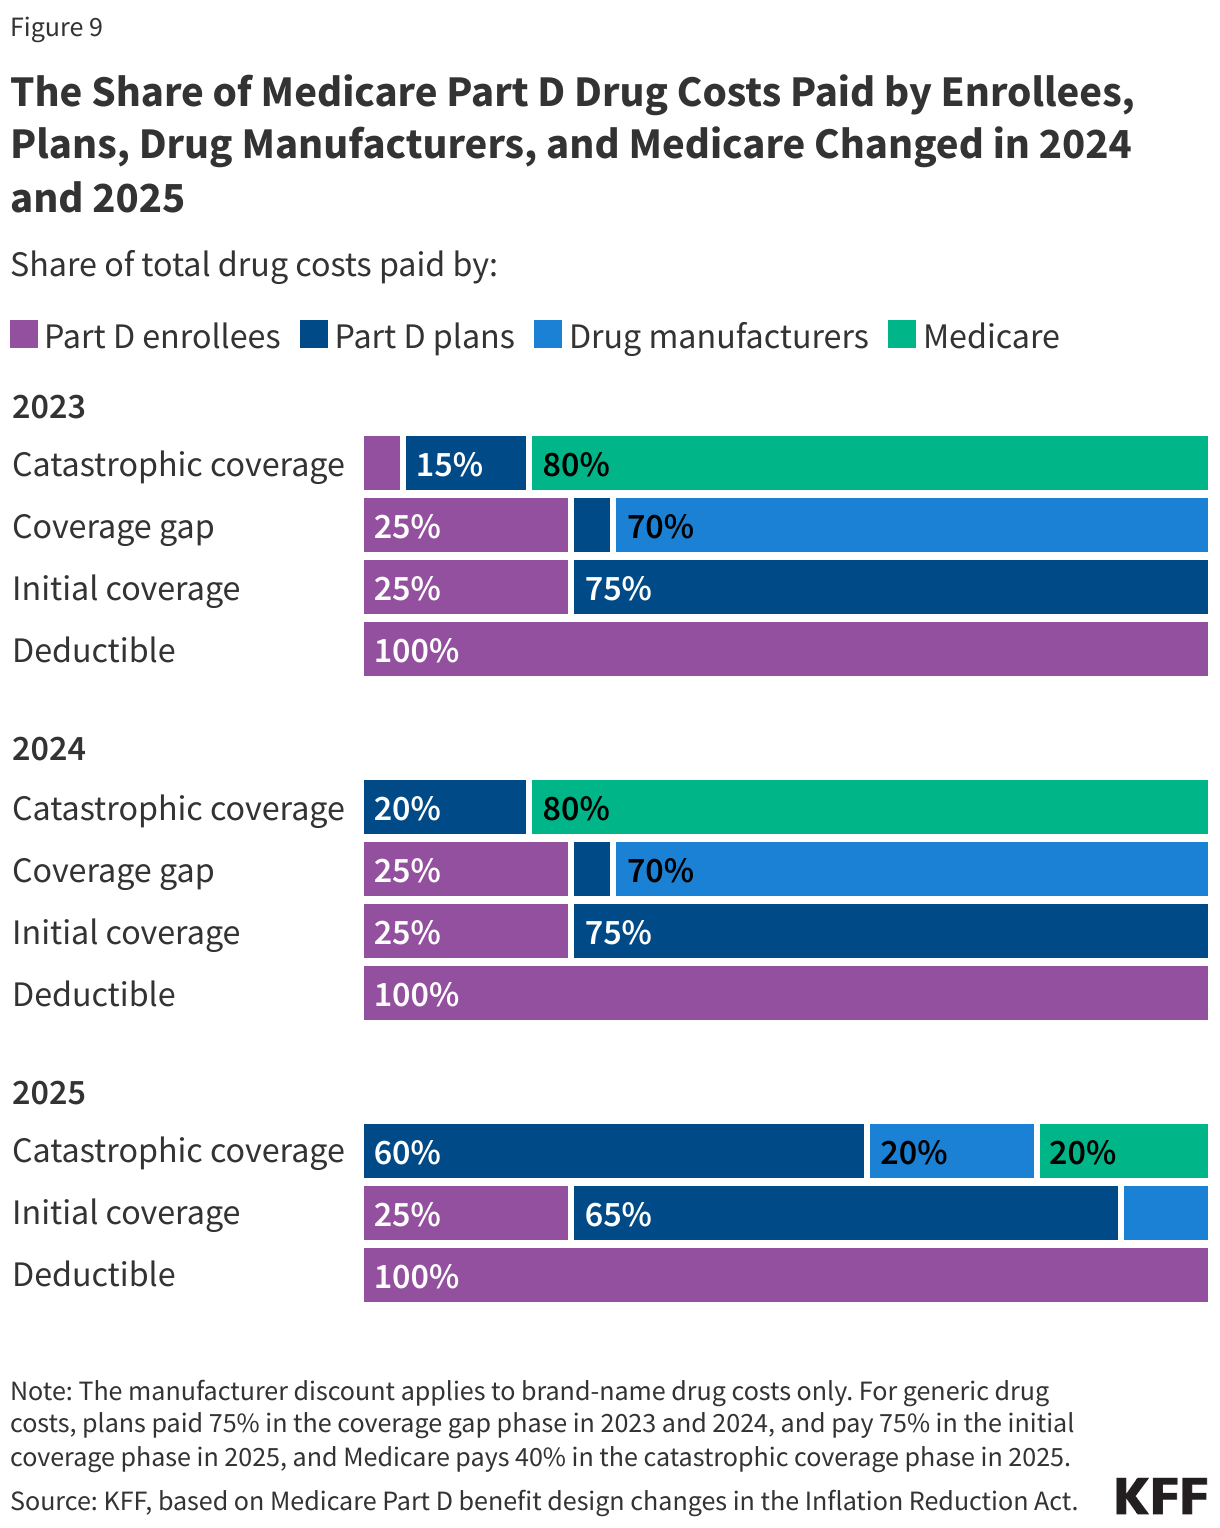
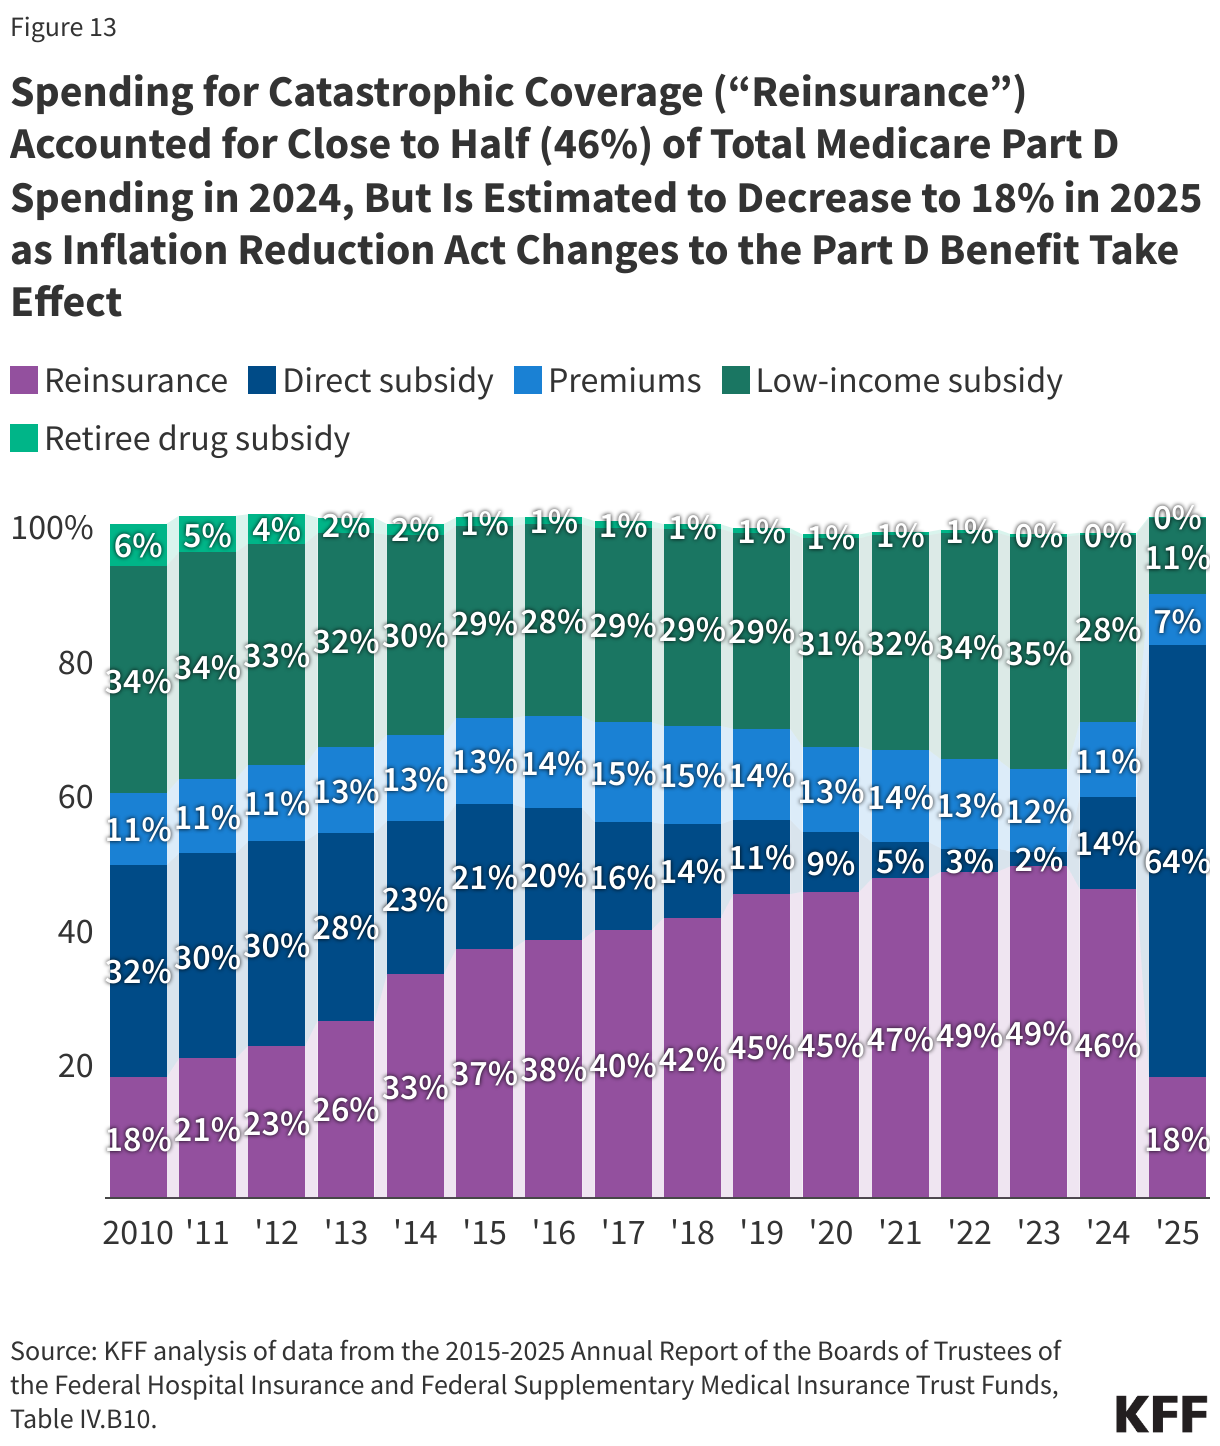
The Inflation Reduction Act remains the most significant legislative intervention in recent years. By capping out-of-pocket drug costs at $2,000 for 2025, the law has provided immediate relief to 11 million enrollees. Furthermore, the shift of reinsurance costs from Medicare to drug manufacturers and plans is forcing a restructuring of the Part D market, as insurers adapt to lower government subsidies.
Implications for the Future
The path forward for Medicare is fraught with difficult trade-offs. The program’s challenges can be distilled into three core categories:
1. Fiscal Solvency
The gap between incoming payroll taxes and outgoing benefits for an aging population is widening. Policymakers face the choice of increasing taxes, reducing benefits, or implementing more aggressive cost-containment measures—all of which carry political risks.
2. Access and Affordability
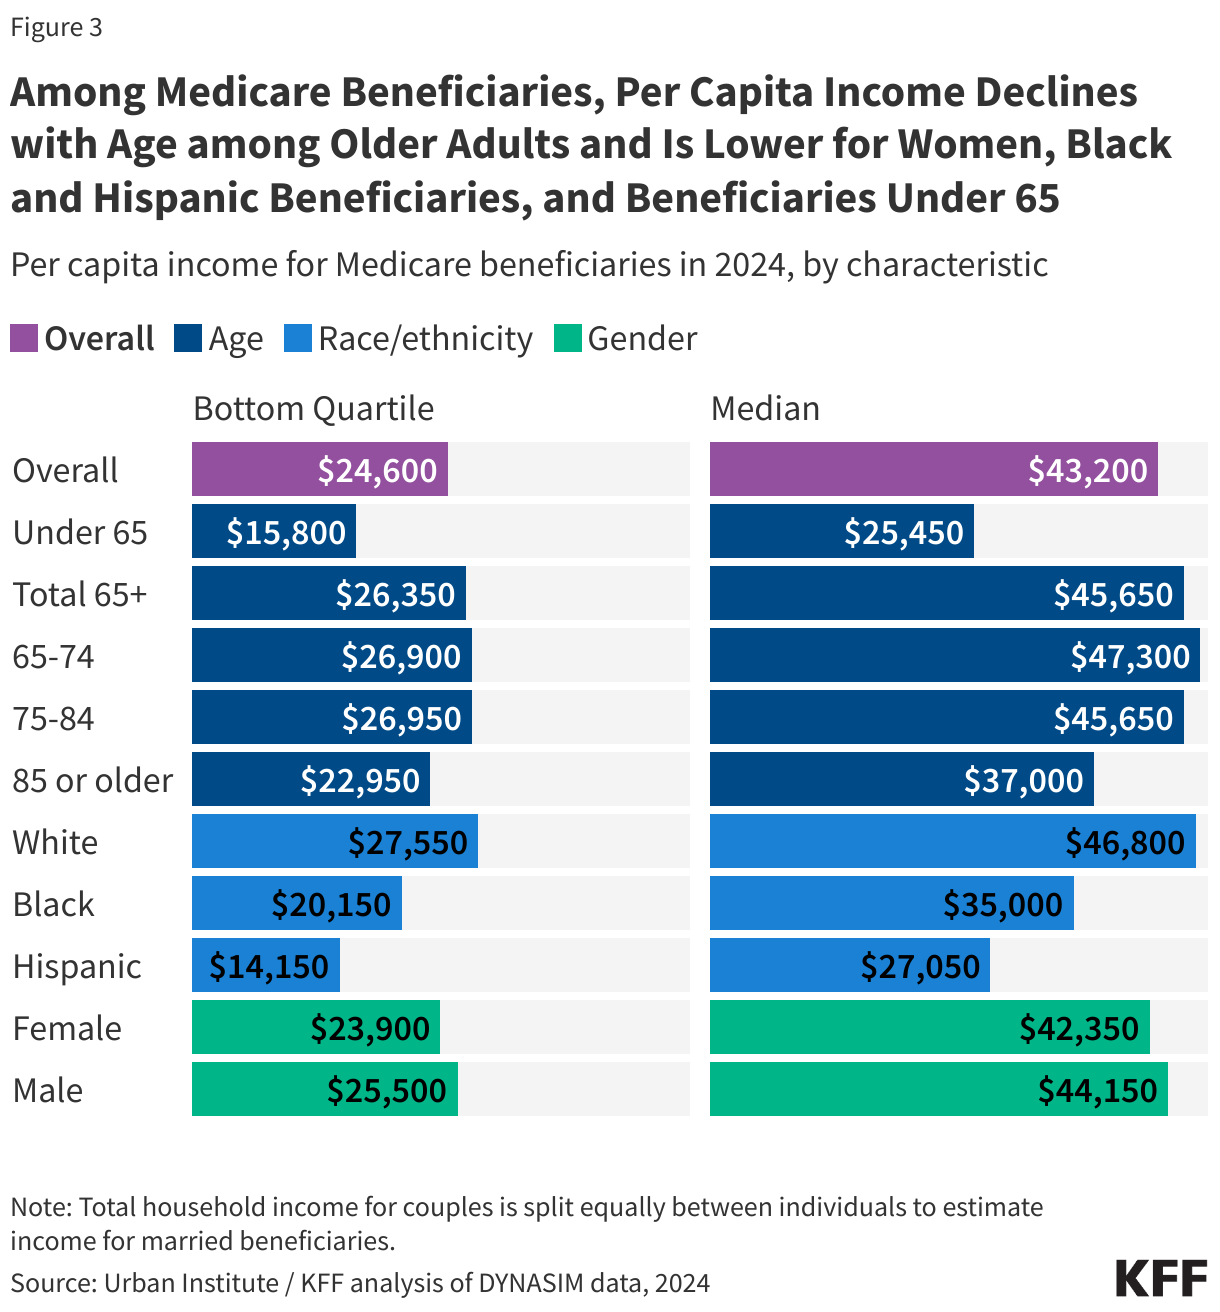
With 25% of beneficiaries living on annual incomes below $24,600, cost-sharing remains a major barrier. Even with the new $2,000 drug cap, many seniors struggle with the "hidden" costs of vision, dental, and hearing care, which remain largely excluded from the standard benefit package.
3. The Role of Private Plans
Medicare Advantage has become the dominant delivery vehicle, yet its long-term impact on the federal budget and the quality of care remains a subject of intense debate. If payments to private plans continue to exceed those of traditional Medicare, the fiscal pressure on the entire system will mount, potentially requiring a fundamental reassessment of the payment formula.
Conclusion
Medicare is more than just a federal insurance program; it is the primary safeguard for the health and dignity of millions of older and disabled Americans. As we look toward 2034 and beyond, the success of the program will depend on the ability of Congress and the Centers for Medicare & Medicaid Services (CMS) to balance the need for fiscal sustainability with the imperative of providing high-quality, accessible care in a rapidly changing medical and demographic environment. The decisions made today regarding payment reforms, drug pricing, and the role of private versus traditional Medicare will define the health security of the American public for the next generation.
About the Author