Breast cancer remains one of the most significant health challenges for women globally, yet a specific and particularly aggressive form of the disease often flies under the radar of public awareness: postpartum breast cancer (PPBC). Defined as breast cancer diagnosed in the years following childbirth, PPBC presents a unique set of biological challenges, diagnostic hurdles, and prognostic concerns that distinguish it from breast cancer diagnosed at other stages of life.
Recent research highlights a sobering reality: PPBC accounts for nearly half of all breast cancer cases in women under the age of 45. Despite its prevalence, the intersection of maternal health and oncology remains a complex field where symptoms are frequently dismissed as the "normal" physiological changes of new motherhood. Understanding the mechanics of this disease is essential for both patients and clinicians to ensure early detection and improved survival outcomes.
Main Facts: The Biological Paradox of Postpartum Breast Cancer
Postpartum breast cancer is not a separate "type" of cancer like Triple-Negative or HER2-positive in terms of its initial classification, but rather a category defined by the timing of its onset—specifically within five to ten years after giving birth. The highest window of risk occurs within the first five years postpartum.
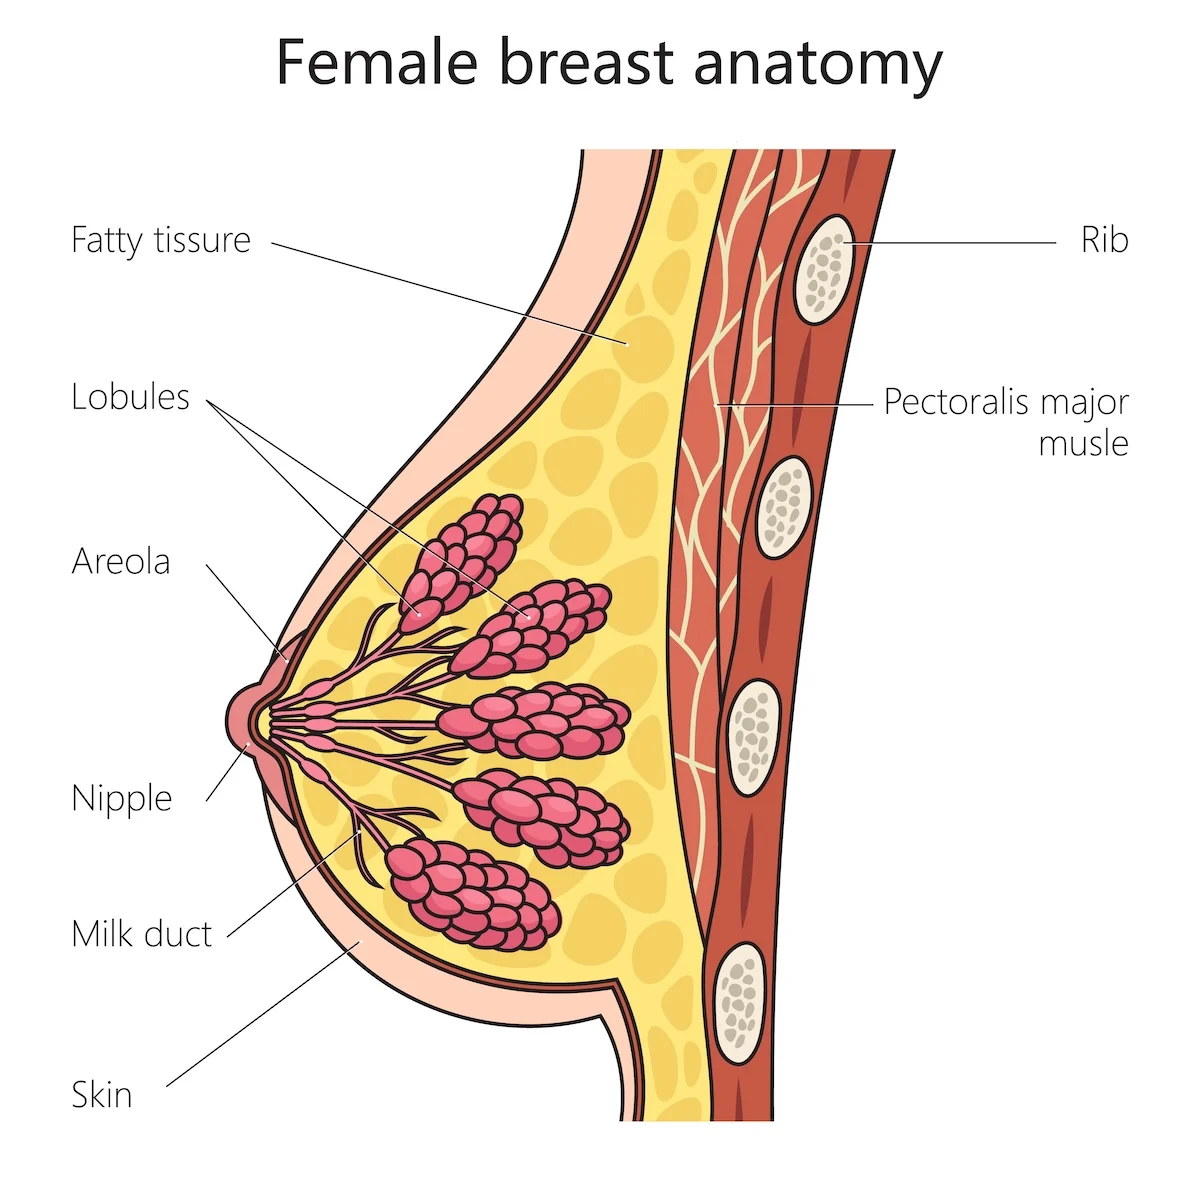
The primary driver behind PPBC is a biological process known as involution. After a woman stops breastfeeding, the breast must undergo a massive structural remodeling to return to its pre-pregnancy state. This process involves the death of milk-producing cells and the removal of excess tissue.
Clinically, involution resembles a state of chronic inflammation or wound healing. The body releases a cascade of enzymes and inflammatory markers to "clear out" the lactation machinery. While this is a healthy and necessary process, research suggests that if abnormal or dormant cancer cells are already present in the breast, this inflammatory environment acts as "fertilizer," encouraging those cells to grow, invade surrounding tissue, and eventually metastasize.
Key Statistics at a Glance:
- Annual Incidence: Approximately 18,000 women in the United States are diagnosed with PPBC annually.
- Demographic Impact: PPBC is estimated to account for 25% to 50% of all breast cancer diagnoses in women under age 45.
- The Survival Gap: Women diagnosed in the postpartum period generally have poorer survival rates compared to women of the same age who have not recently given birth, regardless of the cancer subtype.
Chronology: From Lactation to the Ten-Year Risk Window
The relationship between pregnancy and breast cancer is often described as a "dual effect." In the long term, pregnancy and breastfeeding are protective; however, in the short term, the risk of a diagnosis spikes.
1. The Protective Phase (Pregnancy and Lactation)
During pregnancy, breast cells undergo terminal differentiation to prepare for milk production. Breastfeeding further reduces risk by delaying the return of the menstrual cycle, thereby reducing the lifetime exposure to estrogen—a hormone known to fuel certain types of breast cancer.
2. The Trigger: Weaning and Involution
The risk profile shifts the moment breastfeeding ends. As the breast begins the involution process, the "wound-healing" environment begins. This transition period is the biological catalyst that distinguishes PPBC from other forms of the disease.
3. The Peak Risk Period (0–5 Years Postpartum)
Studies indicate that the five years immediately following childbirth represent the highest period of vulnerability. During this time, the breast tissue is still settling from the inflammatory changes of involution, and the immune system’s local environment may still be suppressed or altered.
4. The Extended Window (5–10 Years Postpartum)
While the risk begins to decline after five years, it remains elevated for up to a decade. By the ten-year mark, the long-term protective benefits of pregnancy usually begin to outweigh the short-term risks associated with the postpartum period.
Supporting Data: Why PPBC is More Aggressive
The clinical data surrounding PPBC paints a challenging picture. It is not merely that these cancers are caught later; they appear to be biologically more inclined to spread.
Metastatic Tendencies
Research has established that PPBC carries a significantly higher risk of metastasis (spreading to distant organs) than breast cancer in non-postpartum women. Specifically, PPBC has a noted tendency to spread to the liver. Liver metastasis is traditionally associated with poorer outcomes and more difficult treatment pathways. Scientists believe the systemic inflammatory signals generated during involution may "prime" the liver and other organs, making them more receptive to circulating tumor cells.
The Subtype Factor
While Triple-Negative Breast Cancer (TNBC)—an aggressive subtype that lacks hormone receptors—is more common in younger women and postpartum patients, the "postpartum effect" is seen across all subtypes. Even Estrogen Receptor-positive (ER+) tumors, which are generally considered more "manageable" in older populations, behave with uncharacteristic aggression when diagnosed in the postpartum window.
The Diagnostic Delay
Data shows that PPBC is more likely to be diagnosed at Stage III or IV. This is attributed to several factors:
- Tissue Density: Lactating or recently lactating breasts are denser and more engorged, making manual lumps harder to feel.
- Symptom Overlap: Symptoms like redness, pain, or lumps are often mistaken for mastitis (infection) or clogged milk ducts.
- Screening Gaps: Routine mammograms typically do not begin until age 40, leaving most postpartum women without a standard screening protocol.
Official Responses: Clinical Guidance and Diagnostic Protocols
Medical organizations and oncology experts are increasingly calling for a "high index of suspicion" when treating breast changes in postpartum women. Because the stakes are higher and the biology is more aggressive, the medical community has established specific protocols for evaluation.
The "Two-Week Rule"
Clinicians advise that any breast change—be it a lump, skin dimpling, or persistent redness—that does not resolve within one to two weeks should be treated as suspicious. While mastitis is common, it should respond to antibiotics or warm compresses quickly. If it doesn’t, imaging is mandatory.
Imaging Strategies
For women who are pregnant or breastfeeding, ultrasound is the gold standard for initial imaging. Mammography is often less effective in these patients because the milk-producing tissue appears "white" or dense on the X-ray, potentially masking a tumor. However, if an ultrasound shows a suspicious mass, a mammogram or MRI may still be used to gather more detail, followed by a core needle biopsy for a definitive diagnosis.
Expert Recommendations for High-Risk Groups
For women with known genetic mutations (such as BRCA1 or BRCA2) or a strong family history, the postpartum period requires even more vigilance. Experts suggest that these women discuss a tailored screening schedule with their doctors, which might include earlier-than-average mammograms or annual MRIs to bridge the gap during the high-risk postpartum years.
Implications: The Future of Maternal Health and Survivorship
The implications of postpartum breast cancer extend far beyond the operating room. Because this disease strikes women during their peak reproductive and career years, the ripple effects on families and society are profound.
Fertility Preservation
One of the most critical implications of a PPBC diagnosis is the impact on future family planning. Many treatments, particularly chemotherapy, can impair ovarian function. Modern clinical guidelines now mandate that fertility preservation (such as egg or embryo freezing) be discussed with patients before treatment begins. This adds a layer of complexity to an already stressful period, as patients must make rapid decisions about future children while facing a life-threatening illness.
The Need for Specialized Survivorship
Survivorship for a woman in her 30s is vastly different than for a woman in her 60s. PPBC survivors face decades of potential long-term side effects, including early menopause, bone density loss, and cardiovascular risks associated with certain chemotherapies. There is a growing movement toward "Young Women’s Breast Cancer Programs" that integrate oncology with reproductive health, cardiology, and psychological support.
Research and Policy Shifts
The fact that PPBC accounts for up to 50% of cases in young women suggests that "age-based" screening may need to be supplemented with "life-event-based" screening. Researchers are currently investigating whether the "inflammatory signature" of involution can be detected through blood tests or if anti-inflammatory interventions could eventually be used to lower the risk in high-risk postpartum women.
A Call for Awareness
The most immediate implication is the need for education. Many women are told that breastfeeding "prevents" breast cancer, which can lead to a false sense of security when they find a lump a year after weaning. Public health messaging must evolve to explain that while breastfeeding is protective in the long run, the years immediately following it require heightened awareness.
Conclusion
Postpartum breast cancer is a reminder that the biological miracles of pregnancy and childbirth come with complex physiological costs. While the 5-to-10-year window after giving birth is a time of intense focus on the child, it is a period where mothers must remain equally attentive to their own bodies.
The aggressive nature of PPBC is not a reason for despair, but a call to action. With 18,000 women affected annually, the medical community and the public must move past the misconception that young mothers are "too young" for breast cancer. Early detection remains the most powerful tool in the arsenal, turning a daunting biological challenge into a manageable and survivable journey. By understanding the role of involution and the specific symptoms to watch for, women and their doctors can work together to ensure that the years following childbirth are defined by health and longevity rather than a delayed diagnosis.
About the Author