In a landmark decision that promises to reshape the therapeutic landscape for breast cancer patients across England, the National Institute for Health and Care Excellence (NICE) has officially recommended the use of Enhertu® (trastuzumab deruxtecan) for patients with HER2-low metastatic breast cancer. This approval marks the conclusion of a prolonged, high-stakes negotiation process and offers a lifeline to thousands of patients who have been awaiting access to this life-extending treatment.
The decision, which brings an end to a period of uncertainty for clinicians and patient advocacy groups alike, follows the successful resolution of complex pricing negotiations between the pharmaceutical manufacturers and the National Health Service (NHS). By integrating the therapy into the NHS portfolio, England has taken a definitive step toward addressing the unmet needs of a specific sub-population of breast cancer patients who previously had limited options.
The Clinical Landscape: Understanding HER2-Low Breast Cancer
Historically, breast cancer treatment has been categorized primarily by the presence or absence of the human epidermal growth factor receptor 2 (HER2) protein. Traditionally, patients were classified as either HER2-positive (high levels of the protein) or HER2-negative. However, recent scientific advancements have identified a distinct intermediate group: HER2-low.
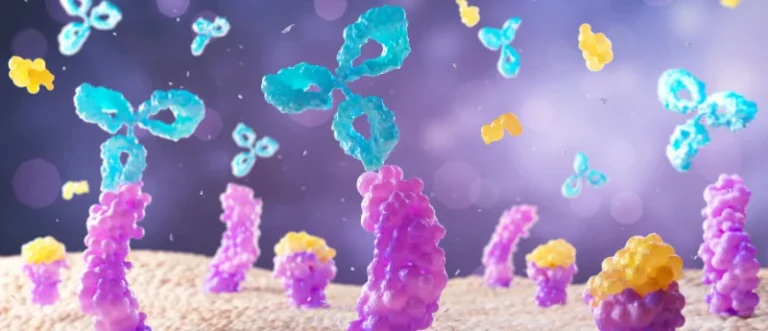
HER2-low metastatic breast cancer refers to tumors that express low, yet detectable, levels of the HER2 protein. Previously, these patients were treated under the "HER2-negative" umbrella, meaning they were ineligible for targeted therapies specifically designed for HER2-positive cancers. Instead, they were typically relegated to standard-of-care chemotherapy, which often yields shorter periods of progression-free survival and can carry significant toxicities. The arrival of Enhertu—a sophisticated antibody-drug conjugate (ADC)—represents a paradigm shift, as it acts like a "guided missile," delivering chemotherapy directly to cells expressing even low levels of the HER2 protein while sparing healthy tissue.
Chronology of the Negotiation Process
The road to this approval was neither short nor simple. The journey began with the release of the landmark DESTINY-Breast04 clinical trial results, which provided the clinical justification for the drug’s efficacy.
The Initial Rejection
Following the initial submission of clinical data, NICE’s independent appraisal committee found itself in a stalemate. Despite recognizing the clear clinical benefits of the treatment, the committee initially issued a draft recommendation against the routine use of Enhertu on the NHS. The primary hurdle was cost-effectiveness. In the eyes of the committee, the price proposed by the manufacturers—AstraZeneca and Daiichi Sankyo—was deemed too high relative to the health outcomes achieved, falling outside the standard thresholds for value-for-money in the English healthcare system.
The Turning Point: Pricing and Policy Reform
For over two years, patient advocacy groups, including Breast Cancer Now, campaigned tirelessly, highlighting the disparity between the scientific evidence and the lack of patient access. During this period, two critical factors converged to break the deadlock:
- Commercial Realignment: The manufacturers entered into complex, confidential discussions with NHS England to find a sustainable pricing model. These negotiations were facilitated by the UK/US Pharmaceutical Pricing Agreement, which allowed for a flexible commercial solution.
- Methodological Evolution: Simultaneously, NICE underwent a strategic review of its appraisal methods. Recent changes to the organization’s cost-effectiveness thresholds, combined with the implementation of more robust, patient-centric methods for measuring "quality-of-life," allowed the committee to view the benefits of Enhertu through a more comprehensive lens.
By aligning these two factors, the parties were able to draft a deal that ensured clinical accessibility while maintaining the financial integrity of the NHS budget.
Supporting Data: The DESTINY-Breast04 Trial
The clinical efficacy that forced this reconsideration is grounded in the results of the DESTINY-Breast04 Phase III trial, a study that has been widely hailed as a landmark in oncology.
Progression-Free Survival (PFS)
In the trial, patients treated with Enhertu experienced a median progression-free survival of 9.9 months. This stands in stark contrast to the 5.1 months observed in the cohort of patients who received the physician’s choice of standard chemotherapy. By nearly doubling the time that patients remained stable without their disease progressing, the drug provided a significant window of relief for those living with metastatic disease.
Overall Survival (OS)
The survival benefits were equally compelling. The study demonstrated a median overall survival of 23.4 months for the Enhertu group, compared to 16.8 months in the control group. This 6.6-month extension in life expectancy represents a significant gain in the context of metastatic breast cancer, where every additional month of quality life is profoundly meaningful to patients and their families.
Official Responses and Stakeholder Perspectives
The announcement has been met with a mixture of professional relief and emotional validation from those who have spent years navigating the healthcare system.
The Regulatory View: NICE
Helen Knight, director of medicines evaluation at NICE, provided clarity on the systemic shifts that facilitated the approval. "I’m pleased that a commercial solution, alongside recent changes to NICE’s cost-effectiveness thresholds and the use of new methods for assessing quality-of-life, has meant this treatment can now be provided on the NHS," Knight noted. Her comments underscore the importance of the evolving appraisal framework in ensuring that innovative, high-cost therapies can find a place in public healthcare.
The Patient Advocacy View: Breast Cancer Now
For Claire Rowney, chief executive of Breast Cancer Now, the news is a culmination of a long, arduous journey. "After more than 2 years of relentless campaigning, Enhertu has been recommended by NICE for use on the NHS in England for people with HER2-low metastatic breast cancer," she stated.
Rowney emphasized the human element of this victory, framing it as a triumph of patient persistence. "This milestone victory belongs to every person who refused to accept that access to a life-extending treatment was out of reach. For people in England, the wait for Enhertu is finally over."
However, Rowney’s remarks also carried a note of caution and a call to action. She reminded stakeholders that the healthcare system is not yet uniform across the United Kingdom. "We must now also see Wales and Northern Ireland make Enhertu available for use on the NHS for those who need more time to live," she added, highlighting the fragmented nature of healthcare access across the devolved nations.
Implications for the Future of Oncology
The approval of Enhertu for HER2-low breast cancer has far-reaching implications for both the pharmaceutical industry and the NHS.
Shifting Treatment Paradigms
The success of this drug challenges the traditional "binary" classification of breast cancer. By creating a new category of "HER2-low," clinicians are now empowered to look beyond the standard HER2-positive/negative markers. This encourages a more nuanced approach to molecular diagnostics, which is the cornerstone of personalized medicine. We are likely to see increased investment in diagnostic testing to identify more patients who fall into this "low" category, potentially expanding the pool of candidates for ADC therapies.
The Economics of Innovation
The case of Enhertu serves as a blueprint for future high-cost drug appraisals. The interplay between NICE’s willingness to update its assessment framework and the industry’s willingness to engage in creative commercial solutions suggests a new era of cooperation. As medicine becomes increasingly specialized and costly, the ability of governments and pharmaceutical companies to find middle ground will determine the speed at which innovation reaches the bedside.
The Equity of Access
While this decision is a cause for celebration, it also shines a light on the "postcode lottery" that still exists within the UK. Patients in England will now have access to a therapy that could significantly improve their prognosis, yet patients in other parts of the UK remain in a state of limbo. The advocacy efforts seen in England are likely to intensify in Wales and Northern Ireland, as patient groups leverage this precedent to demand equal access.
Long-term Impact on Patient Quality of Life
Ultimately, the primary implication of this approval is the improved quality of life for those living with a terminal diagnosis. By providing a therapy that is more effective than standard chemotherapy and potentially less burdensome in terms of treatment cycles, the NHS is not just extending life, but improving the experience of those living with metastatic cancer.
Conclusion
The recommendation of Enhertu for HER2-low metastatic breast cancer in England is a definitive victory for clinical science, patient advocacy, and evidence-based policy. It underscores the vital role that robust clinical trials play in driving medical progress and highlights the necessity of flexible, adaptive healthcare governance. As the NHS prepares to integrate this therapy into its standard practice, the focus must shift to ensuring that the implementation is swift, equitable, and supported by the necessary diagnostic infrastructure to ensure that the right patients receive this life-extending treatment at the right time. For thousands of patients and their families, the "wait" is finally over—a testament to the power of collective action and the relentless pursuit of medical innovation.
About the Author