The pharmaceutical industry is currently navigating a period of unprecedented data complexity. As clinical trials—particularly in the high-stakes realm of oncology—grow in size and technical demand, the burden of data management has shifted from a manageable task to a significant operational bottleneck. A new collaborative analysis between the Tufts Center for the Study of Drug Development (CSDD) and clinical trial platform specialist Medable has provided the first concrete economic blueprint for how "Agentic AI" can resolve these bottlenecks, projecting staggering returns on investment (ROI) and millions in added financial value.
The study, which specifically examined the deployment of Medable’s Clinical Monitoring Agent, indicates that the integration of artificial intelligence into oncology trials could deliver an 82x ROI for Phase 3 studies and a 64x ROI for Phase 2. In terms of expected net present value (eNPV), these figures translate to approximately $21 million in additional value for Phase 3 trials and $7.5 million for Phase 2. These findings represent a turning point in the pharmaceutical sector’s adoption of generative AI, moving the conversation from speculative pilot programs to validated financial strategy.
A Chronology of Clinical Transformation
The path to this moment has been paved by a steady, albeit cautious, integration of machine learning into clinical workflows.
- The Early Years (2012–2020): Clinical trials began to face an explosion in data volume. According to a landmark study by Tufts CSDD and TransCelerate, the average Phase 3 protocol ballooned from roughly 929,000 data points in 2012 to over 5.9 million by the mid-2020s. This created a "data wrangling" crisis for Clinical Research Associates (CRAs).
- The AI Awakening (2023–2025): As large language models (LLMs) matured, the industry shifted toward "Agentic AI"—systems capable of not just processing information, but performing discrete tasks and suggesting workflows.
- The Pilot Phase (2025): Tufts CSDD released a comprehensive analysis of 36 AI/ML use cases, demonstrating an average 18% reduction in cycle time. This provided the proof-of-concept necessary for the industry to begin taking AI seriously as an operational lever.
- The Quantification Milestone (2026): The current Tufts-Medable analysis represents the culmination of this trend, finally attaching hard financial metrics to operational performance. By modeling the impact on oncology, the industry now has a framework to justify the capital expenditure required to move from manual monitoring to AI-augmented oversight.
Supporting Data: The Cost of Complexity
To understand the magnitude of this shift, one must look at the "failure rate" crisis. Small-molecule oncology drug candidates have struggled with a persistent 95% failure rate for three decades. While success rates in Phase 3 have improved—reaching roughly 43.4% for oncology trials between 2007 and 2023—the cost of failure remains catastrophic.
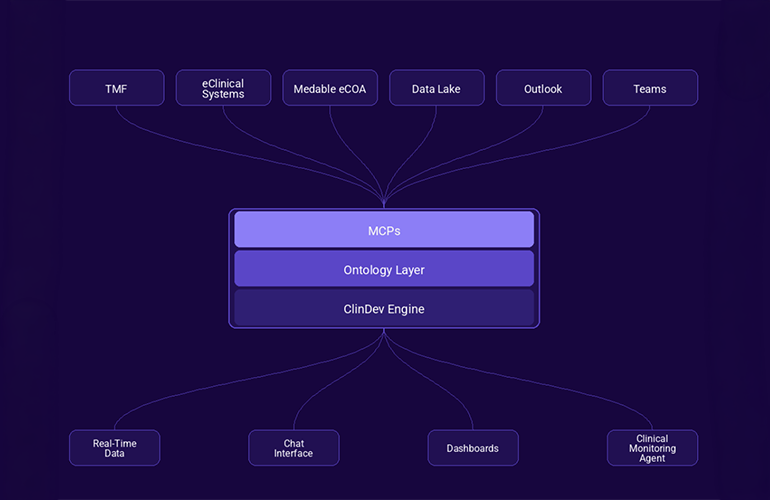
The Tufts/Medable model highlights how AI agents mitigate these risks by processing the "mountains of data" that human CRAs struggle to synthesize. By connecting to clinical data systems like Medidata Rave, Oracle InForm, and various CTMS (Clinical Trial Management Systems), these agents act as an early-warning system. They identify patterns that are statistically significant but humanly invisible in the short term, such as site-specific deviations in adverse-event reporting or inconsistent concomitant medication logging.
Scaling the Value
The financial impact scales exponentially with the size of a company’s clinical portfolio. For a sponsor managing 20 active indications, the model projects an incremental portfolio eNPV of $226 million. For larger organizations managing 50 indications, that number jumps to $565 million. These projections assume a consistent application of AI agents across each trial, highlighting that for big pharma, the "cost of inaction" is now officially measured in hundreds of millions of dollars.
Official Responses and Strategic Perspectives
The collaboration was born out of a desire to move beyond the "hype cycle." Ken Getz, Executive Director of the Tufts CSDD, noted that while the industry has been enthusiastic about AI, it has been notably starved of rigorous economic validation.
"We’ve known for some time that companies have been piloting AI enablement tools, but what they’ve often been lacking is any kind of quantification of the actual ROI," Getz stated. "We were really interested in doing a study where we could put some hard numbers around a specific AI enablement solution."
Dr. Pamela Tenaerts, Chief Medical Officer at Medable, emphasized that the configuration of these agents is not a "plug-and-play" scenario. "A lot of those agents still need about 20% tweaking," she explained, noting that the diversity of enterprise systems requires a customized approach. Despite this, the potential to clear the path for better decision-making is immense. "The agent has the ability to see things slightly earlier than a human would. That likely happens faster than a human can make that connection, so the person can intervene on that issue."
The "Human-in-the-Loop" Reality
Despite the promise of autonomous systems, both Medable and industry experts are tempering expectations with a pragmatic view of current technology. There is a distinct difference between "autonomous" agents and "assistive" agents.

Currently, Medable’s agents follow a "recommend-and-review" architecture. While they can perform tasks like drafting queries for missing data or flagging protocol deviations, they do not operate in a vacuum. "The agent doesn’t suspend the CRA from thinking," Dr. Tenaerts emphasized. "The CRA still needs to be there."
This sentiment is echoed by Venu Mallarapu, Chief Transformation and AI Officer at eClinical Solutions. Mallarapu notes that while the industry is making great strides, we have yet to see fully autonomous, self-governing agents. "There’s nobody that is running fully autonomous agents that not only process the data but also make decisions without human involvement," he said. Instead, the current state-of-the-art involves reengineering clinical workflows so that humans spend less time on data entry and more time on high-level interpretation.
Implications for the Future of Drug Discovery
The shift toward agentic workflows implies a fundamental change in the role of the clinical professional. By automating the "mundane" tasks—query generation, site-to-site data comparison, and TMF filing—the industry is effectively freeing up its most valuable human resources to handle the complex, non-algorithmic aspects of clinical research.
1. Improved Site Relationships
One of the most significant implications is the potential to reduce the burden on clinical sites. By identifying issues sooner and reducing the "noise" of manual, repetitive queries, sponsors can foster more collaborative relationships with investigators. However, as Dr. Tenaerts warned, sponsors must be careful not to create a new bottleneck: if an agent identifies 100 issues that a human would have only found 10 of, the sites may be overwhelmed unless the entire ecosystem is re-optimized.
2. The Shift to Other Therapeutic Areas
While the Tufts/Medable model focused exclusively on oncology, the logic is highly transferable. The industry is already looking toward applying these agents to rare diseases, neurology, and cardiovascular trials. The high unmet need in oncology made it the perfect proving ground, but the economic efficiency found there is expected to cascade into every major therapeutic category.

3. A New Standard for Investment
Perhaps the most lasting implication of this research is that it changes the conversation in boardrooms. When considering whether to invest in an AI platform, executives no longer have to rely on vague promises of "efficiency." They can now look at a standardized model for eNPV. This move toward quantitative justification will likely accelerate the adoption of AI-enabled platforms, as companies that fail to adopt these efficiencies may find themselves unable to compete with the speed and lower costs of their AI-augmented peers.
Conclusion
The Tufts and Medable analysis provides a critical anchor for the future of clinical research. By proving that AI agents are not merely technological curiosities but powerful financial instruments, the study establishes a new benchmark for operational success. As the industry moves forward, the focus will likely transition from "can we use AI?" to "how quickly can we scale these agents across our entire portfolio?" For the clinical trial sector, the era of the "agent-augmented" study has officially arrived, promising a future where data complexity is no longer an obstacle, but a competitive advantage.
About the Author