As of October 2025, the Medicare program stands as the bedrock of health security for 68 million Americans. Established six decades ago, the program has evolved from a targeted initiative for seniors into a sprawling, multi-faceted system that accounts for over one-fifth of national health care spending. As the U.S. population ages and health care costs continue to climb, Medicare faces a pivotal moment, balancing the promise of universal coverage for the elderly and disabled against mounting financial pressures and a fundamental shift in how care is delivered and financed.

The Pillars of Medicare: A Historical Chronology
Medicare’s journey began on July 30, 1965, when President Lyndon B. Johnson signed the Social Security Act Amendments into law, creating Title XVIII. At its inception, the program was designed to provide basic hospital and medical insurance for individuals aged 65 and older, regardless of their medical history or financial status.

- 1965: Title XVIII of the Social Security Act establishes Medicare.
- 1972: Eligibility is expanded to include individuals under 65 with long-term disabilities and those with end-stage renal disease (ESRD).
- 2003: The Medicare Modernization Act (MMA) is signed, creating Medicare Part D, the first federal outpatient prescription drug benefit, which launched in 2006.
- 2010: The Affordable Care Act (ACA) introduces payment reforms, including the Medicare Shared Savings Program, and creates the Center for Medicare and Medicaid Innovation (CMMI).
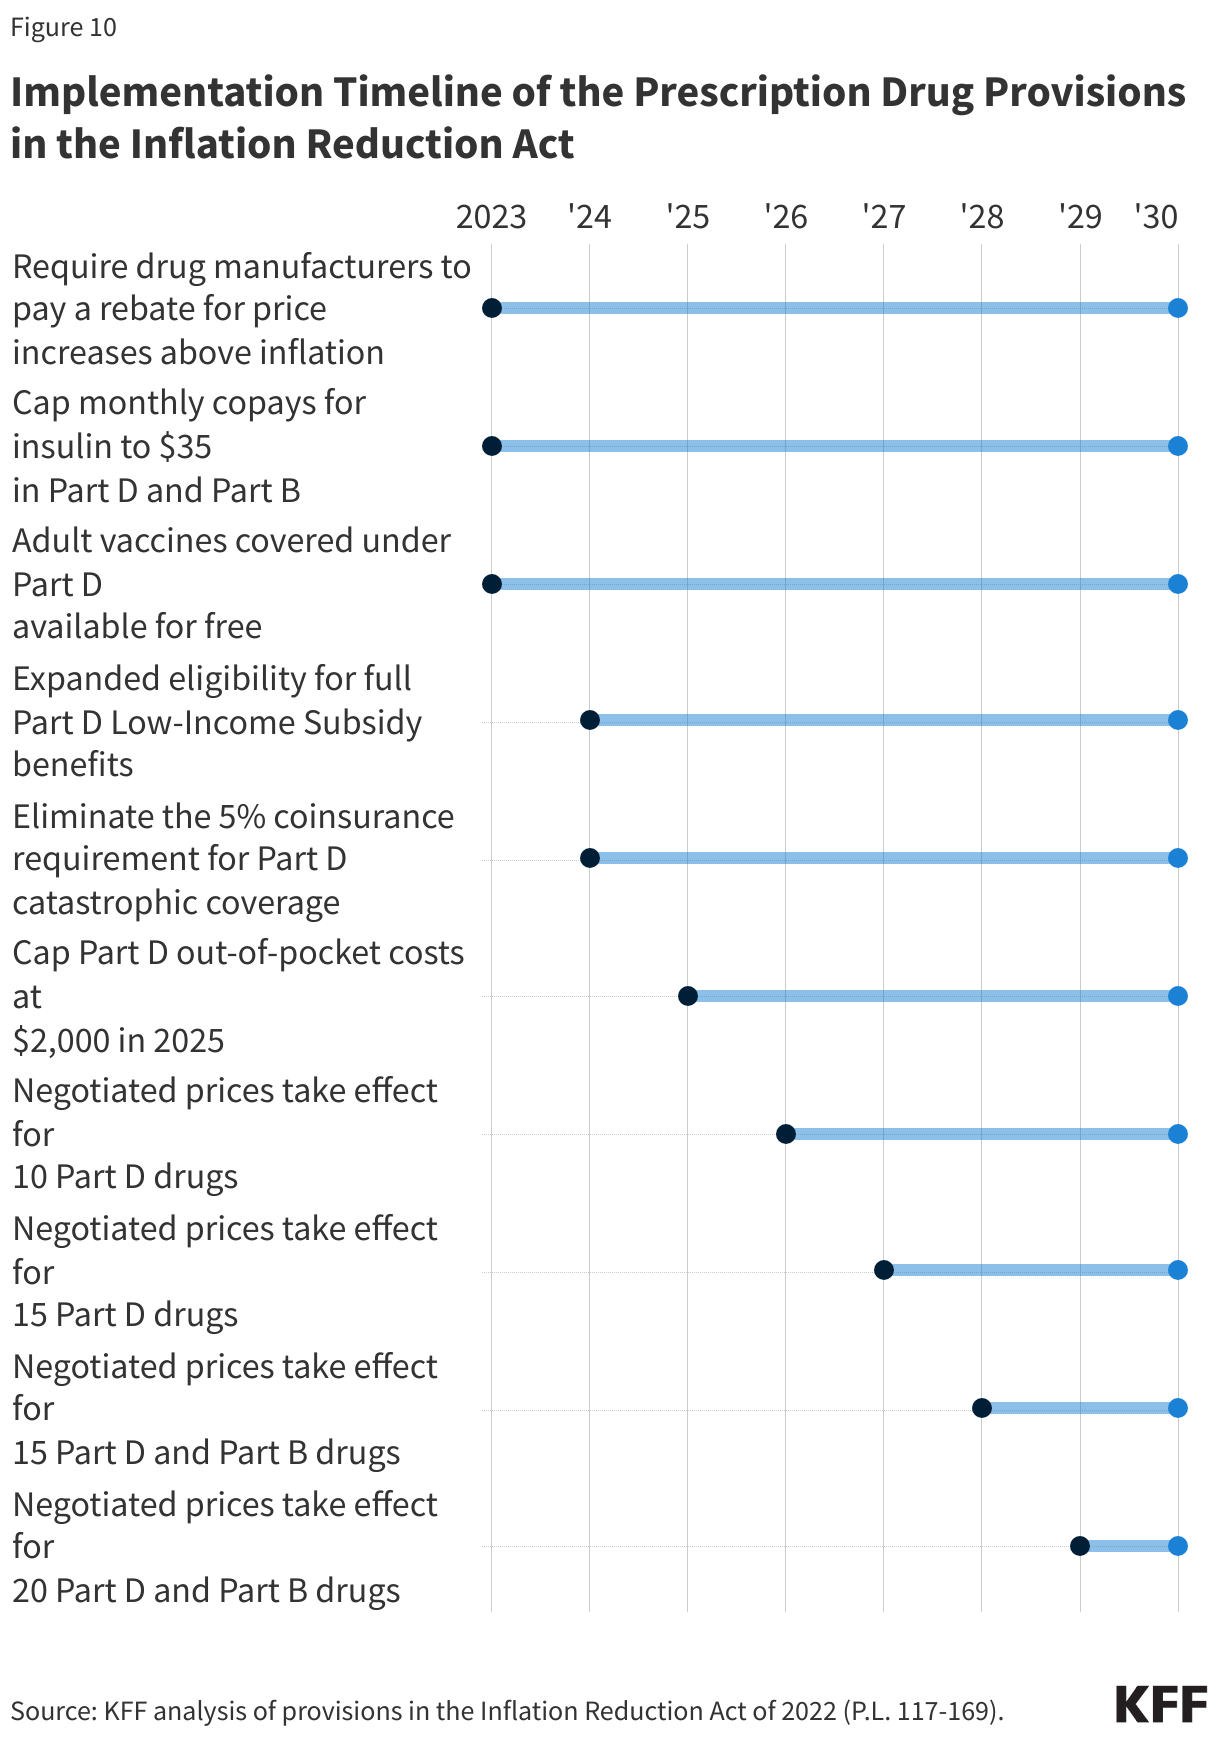
- 2022: The Inflation Reduction Act (IRA) introduces landmark changes to Part D, including the first-ever out-of-pocket spending caps and Medicare’s authority to negotiate prices for certain high-cost drugs.
- 2025: Medicare enters an era where over half of all beneficiaries are enrolled in private Medicare Advantage plans, marking a significant departure from the traditional "fee-for-service" model.
Main Facts: The Scope of Modern Medicare
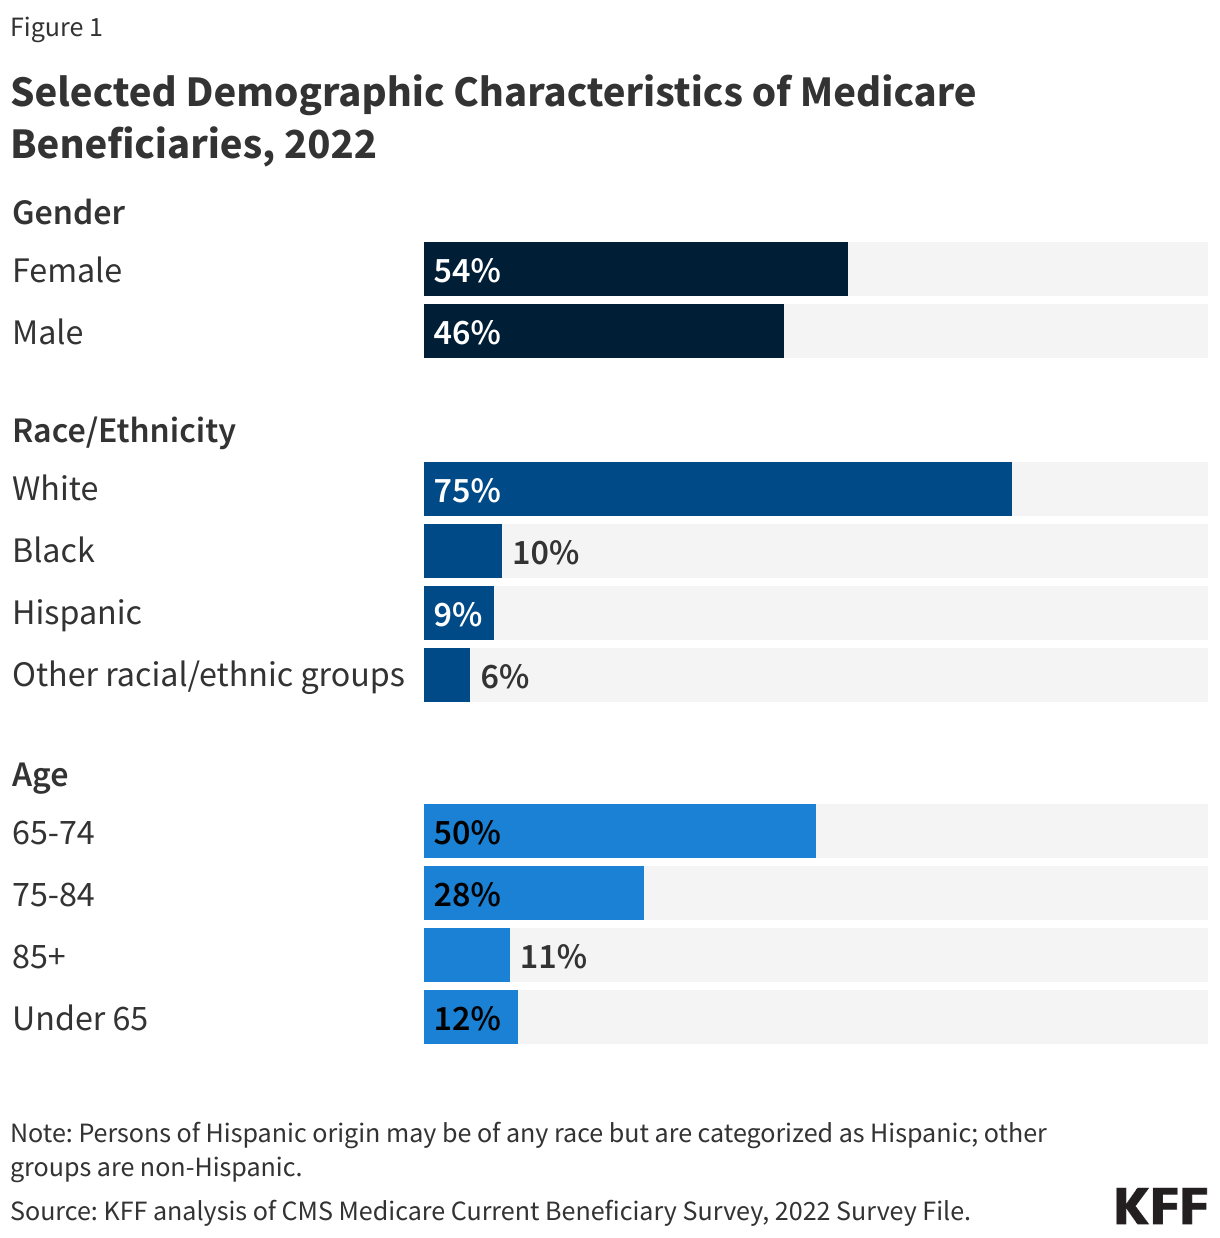
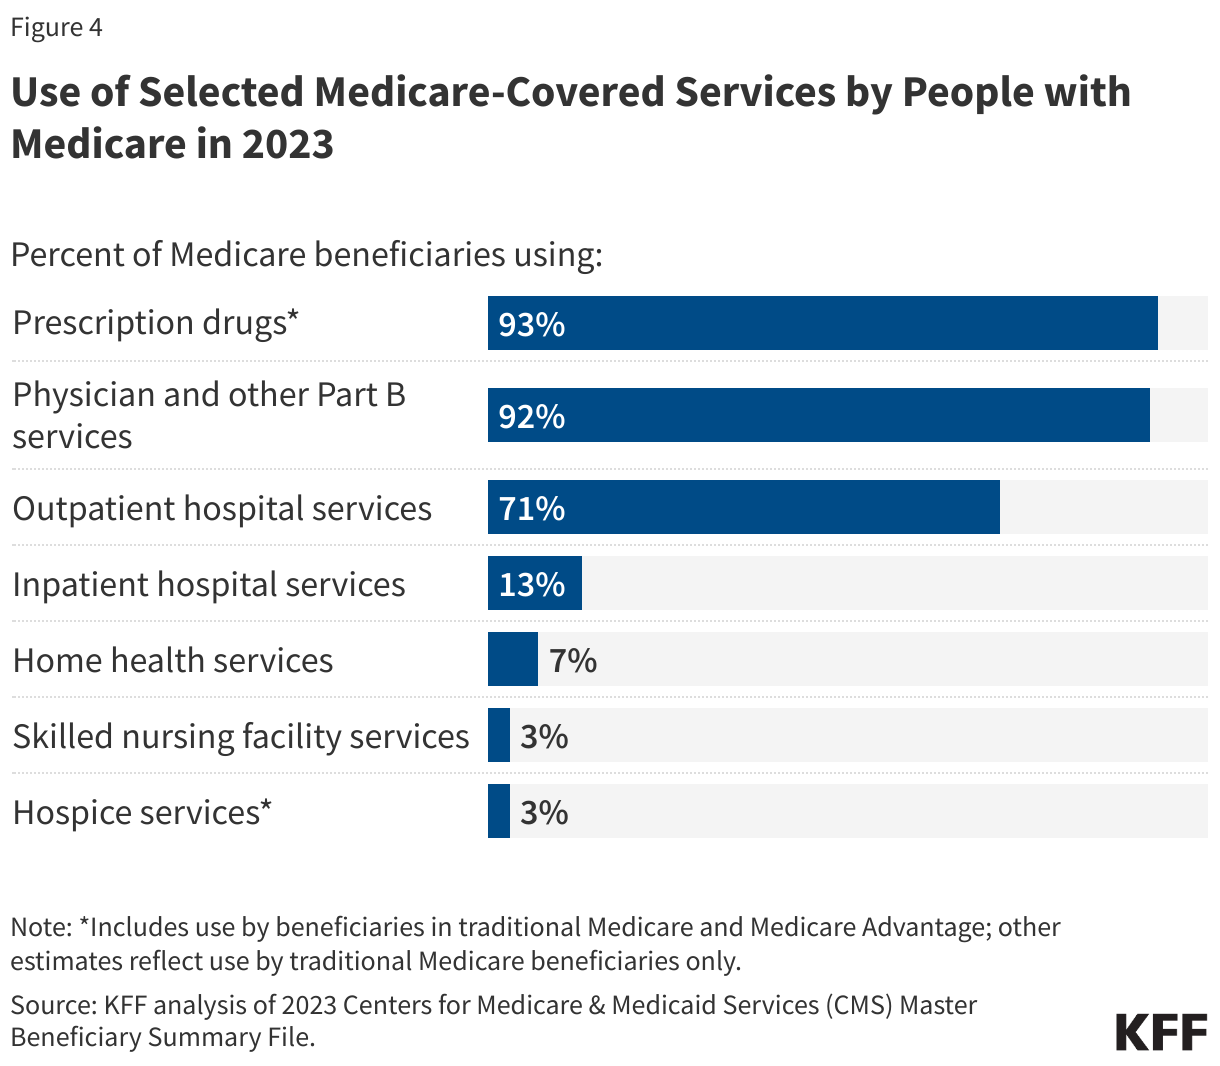
Today, Medicare serves 61 million seniors and 7 million younger people with disabilities. The program is not a monolith but a complex structure divided into four primary parts:
- Part A (Hospital Insurance): Covers inpatient hospital stays, skilled nursing, hospice, and some home health care.
- Part B (Medical Insurance): Covers physician visits, outpatient care, preventive services, and medical equipment.
- Part C (Medicare Advantage): A private-plan alternative to traditional Medicare, often bundling Parts A, B, and D.
- Part D (Prescription Drug Benefit): The outpatient drug coverage provided through private plans.
Despite the program’s reach, it is not comprehensive. Medicare does not cover long-term custodial care, and traditional coverage for dental, vision, and hearing services remains limited—a gap that many Medicare Advantage plans have sought to fill to attract enrollees.
Supporting Data: Demographics and Financial Strain
The demographic profile of the Medicare population is shifting. In 2022, approximately 17% of the U.S. population was aged 65 or older; this figure is projected to reach 24% by 2060. As the population grows, it also becomes more diverse, with people of color expected to comprise 44% of the Medicare-eligible age group by 2060.
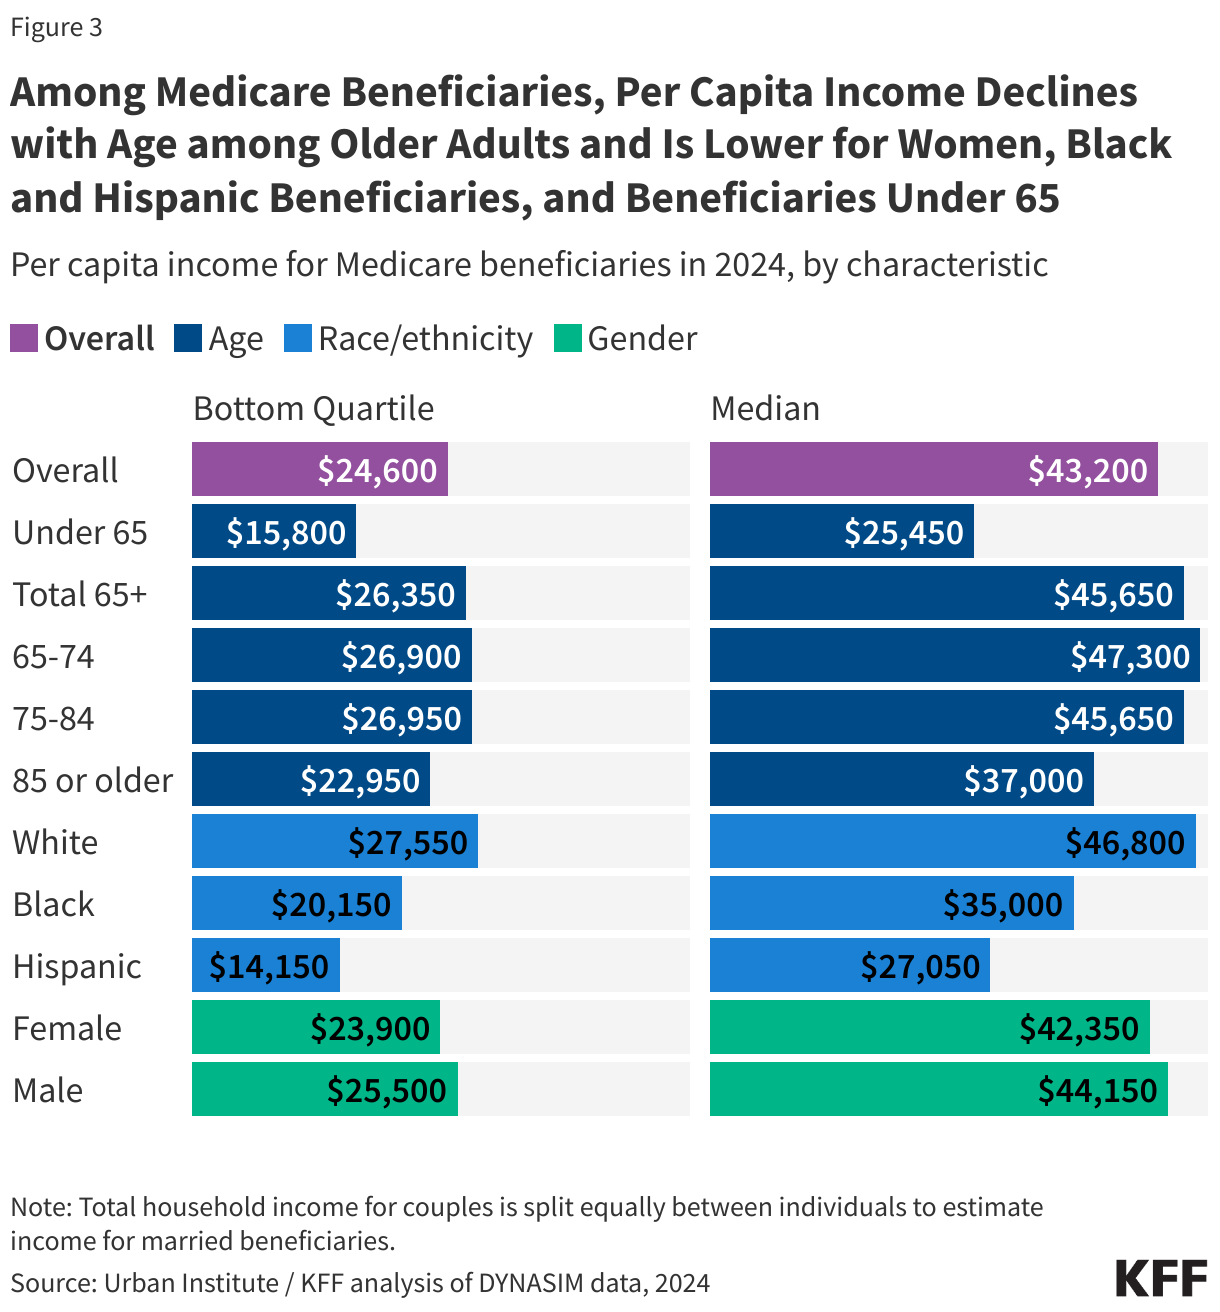
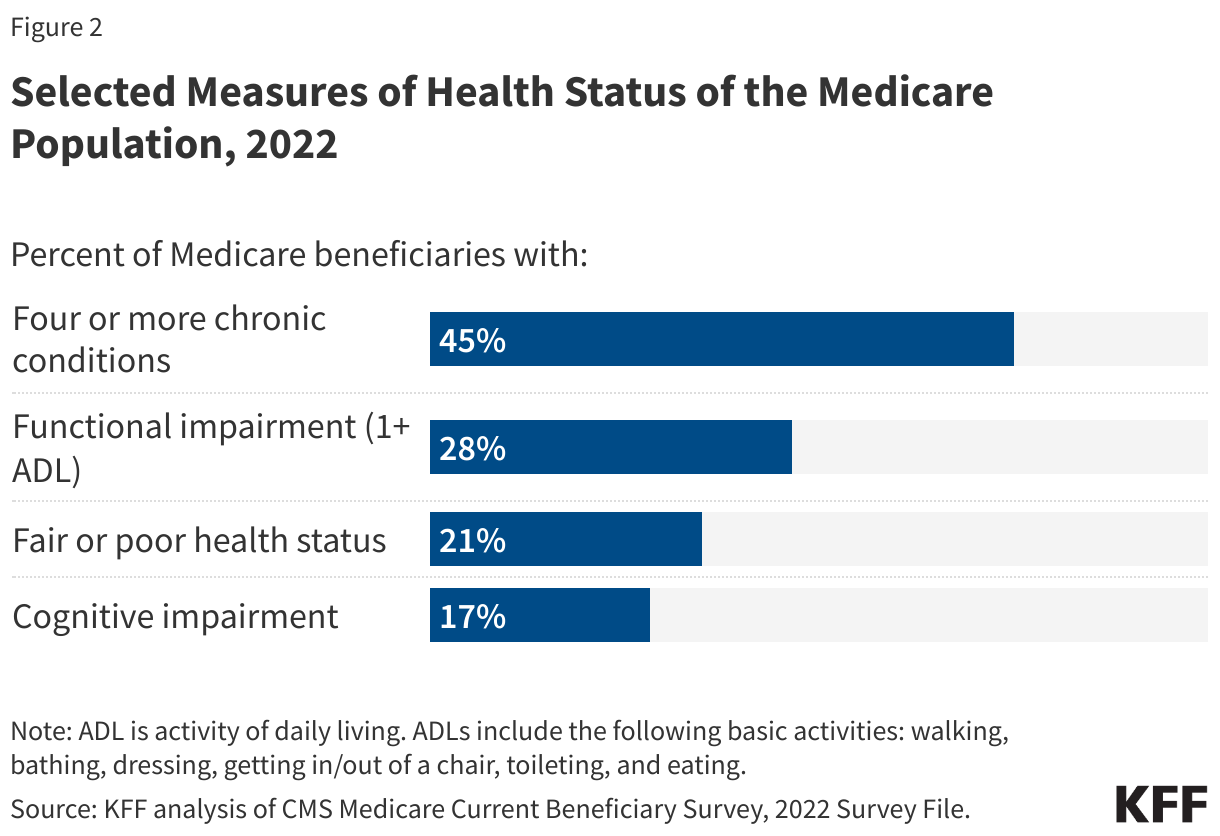
This aging population brings with it significant health needs. In 2022, 45% of beneficiaries lived with four or more chronic conditions, and 17% suffered from cognitive impairment. Financial vulnerability remains a persistent concern: in 2024, half of all Medicare beneficiaries lived on incomes below $43,200 per year, and many have limited savings to buffer against unexpected medical costs.
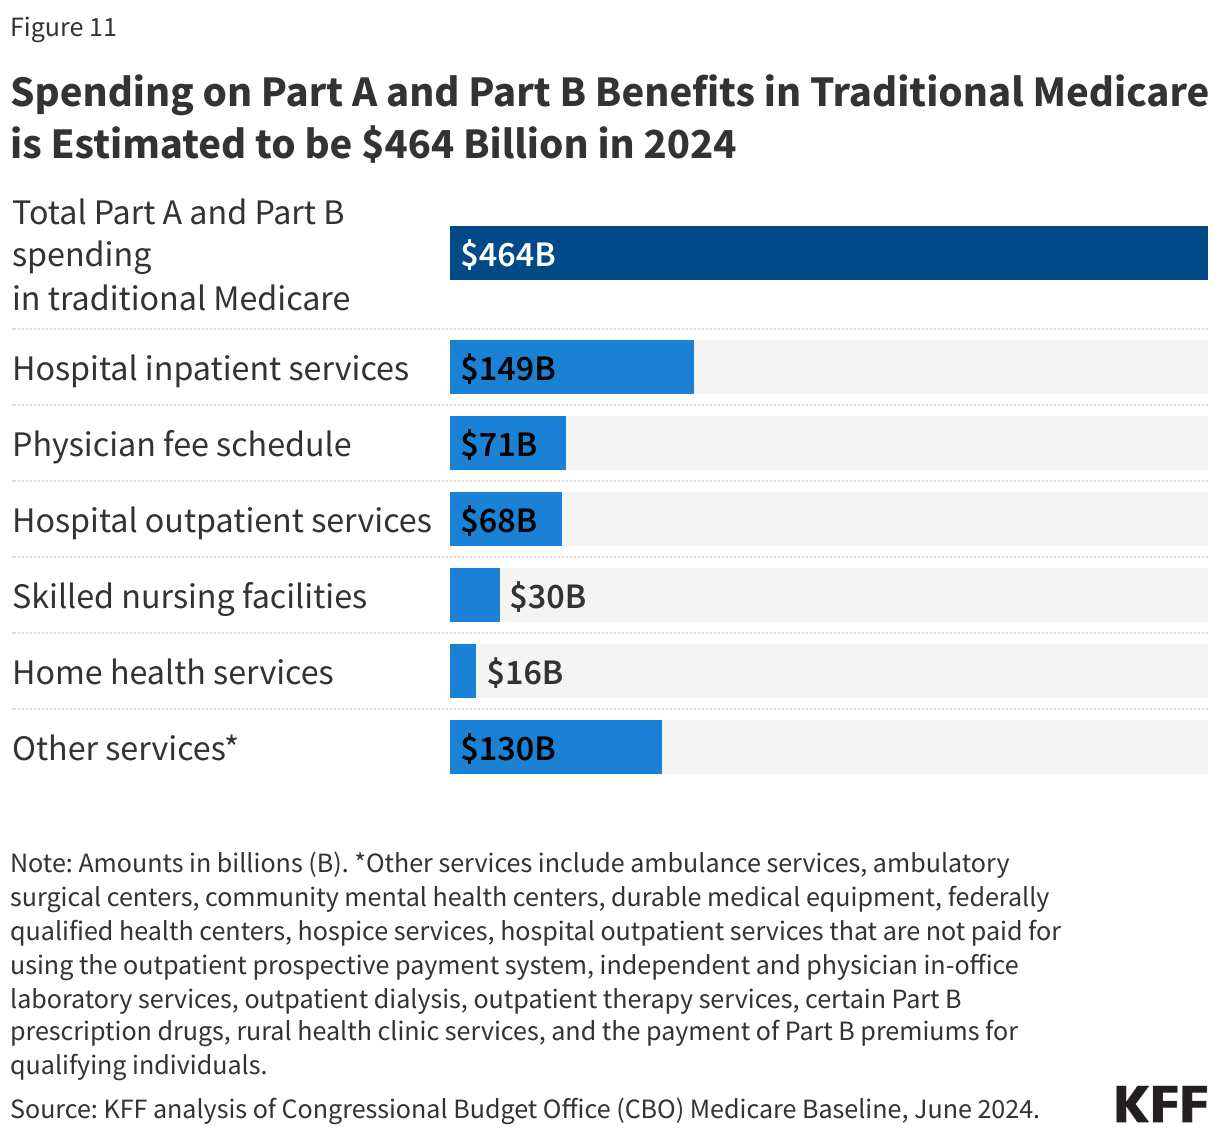
Financially, the program is massive. In 2024, Medicare spending totaled roughly $910 billion, accounting for 13% of the federal budget. The primary funding sources are government contributions (44%), payroll taxes (35%), and beneficiary premiums (15%).
The Rise of Medicare Advantage and Private Contracting
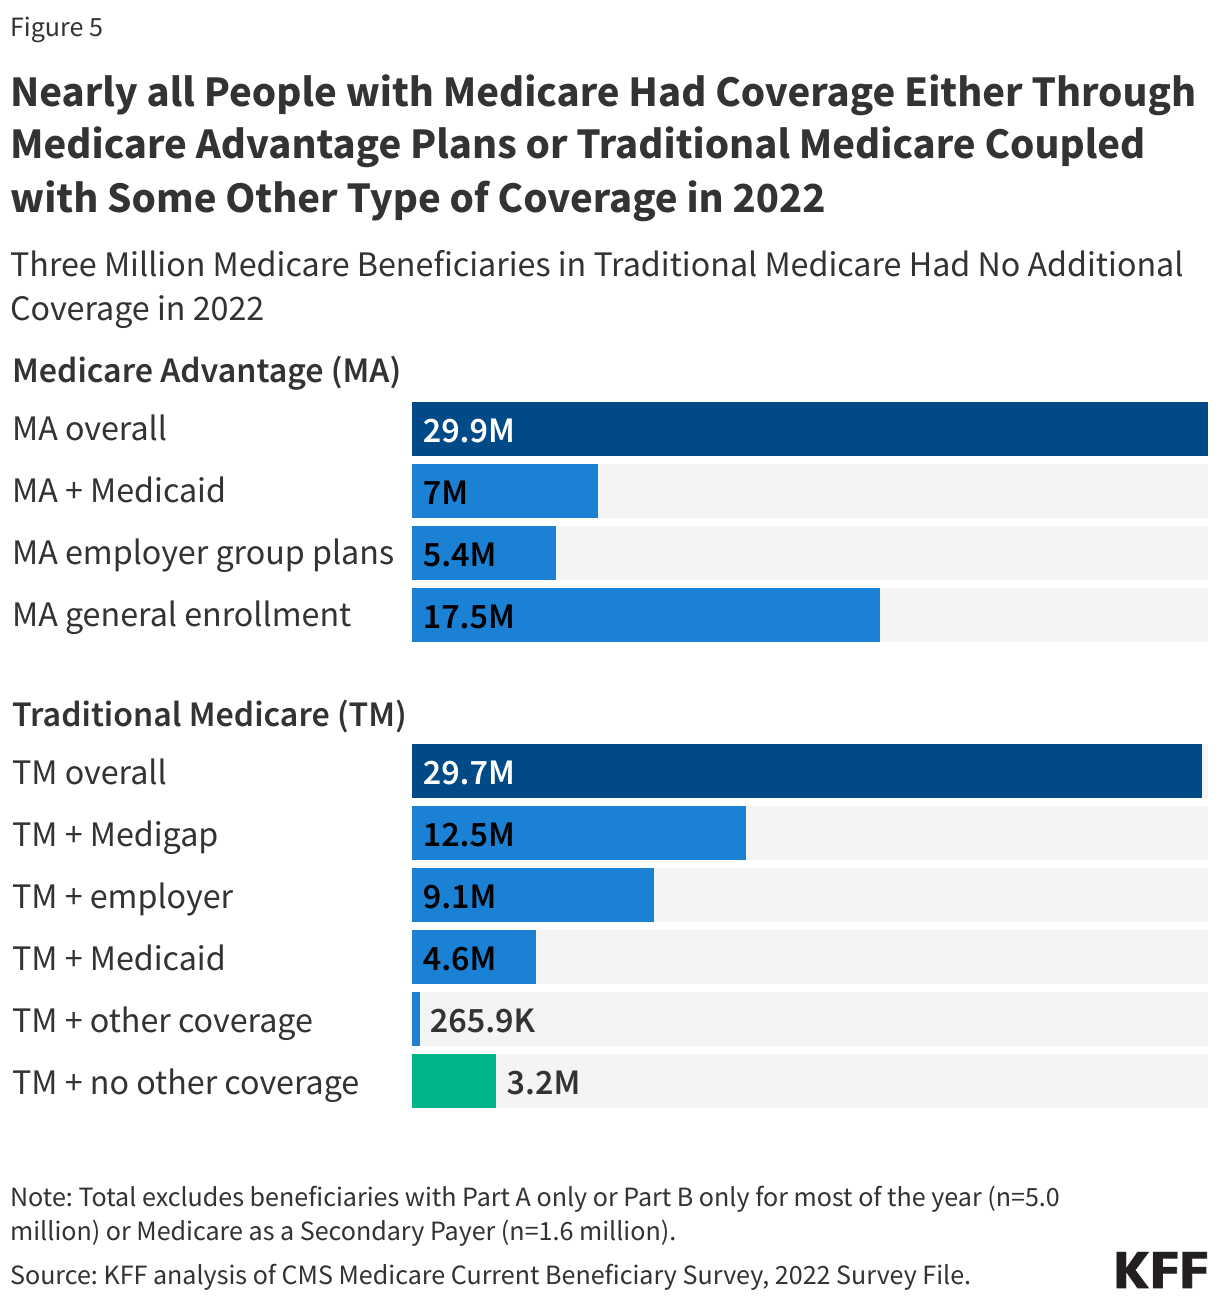
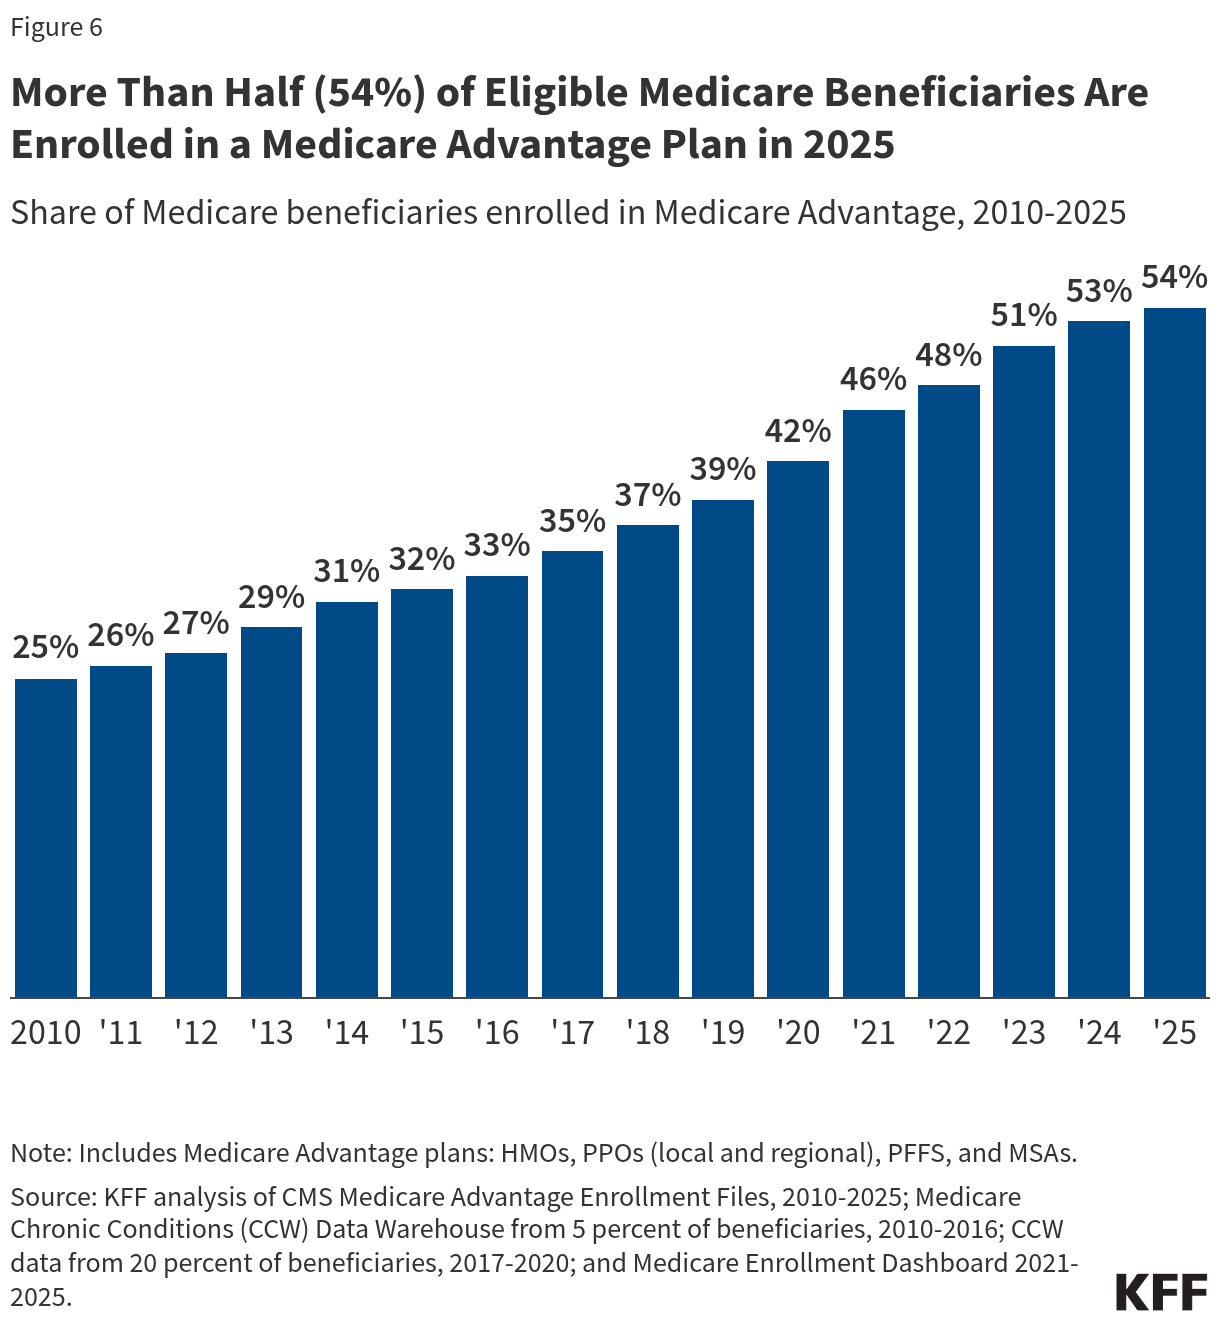
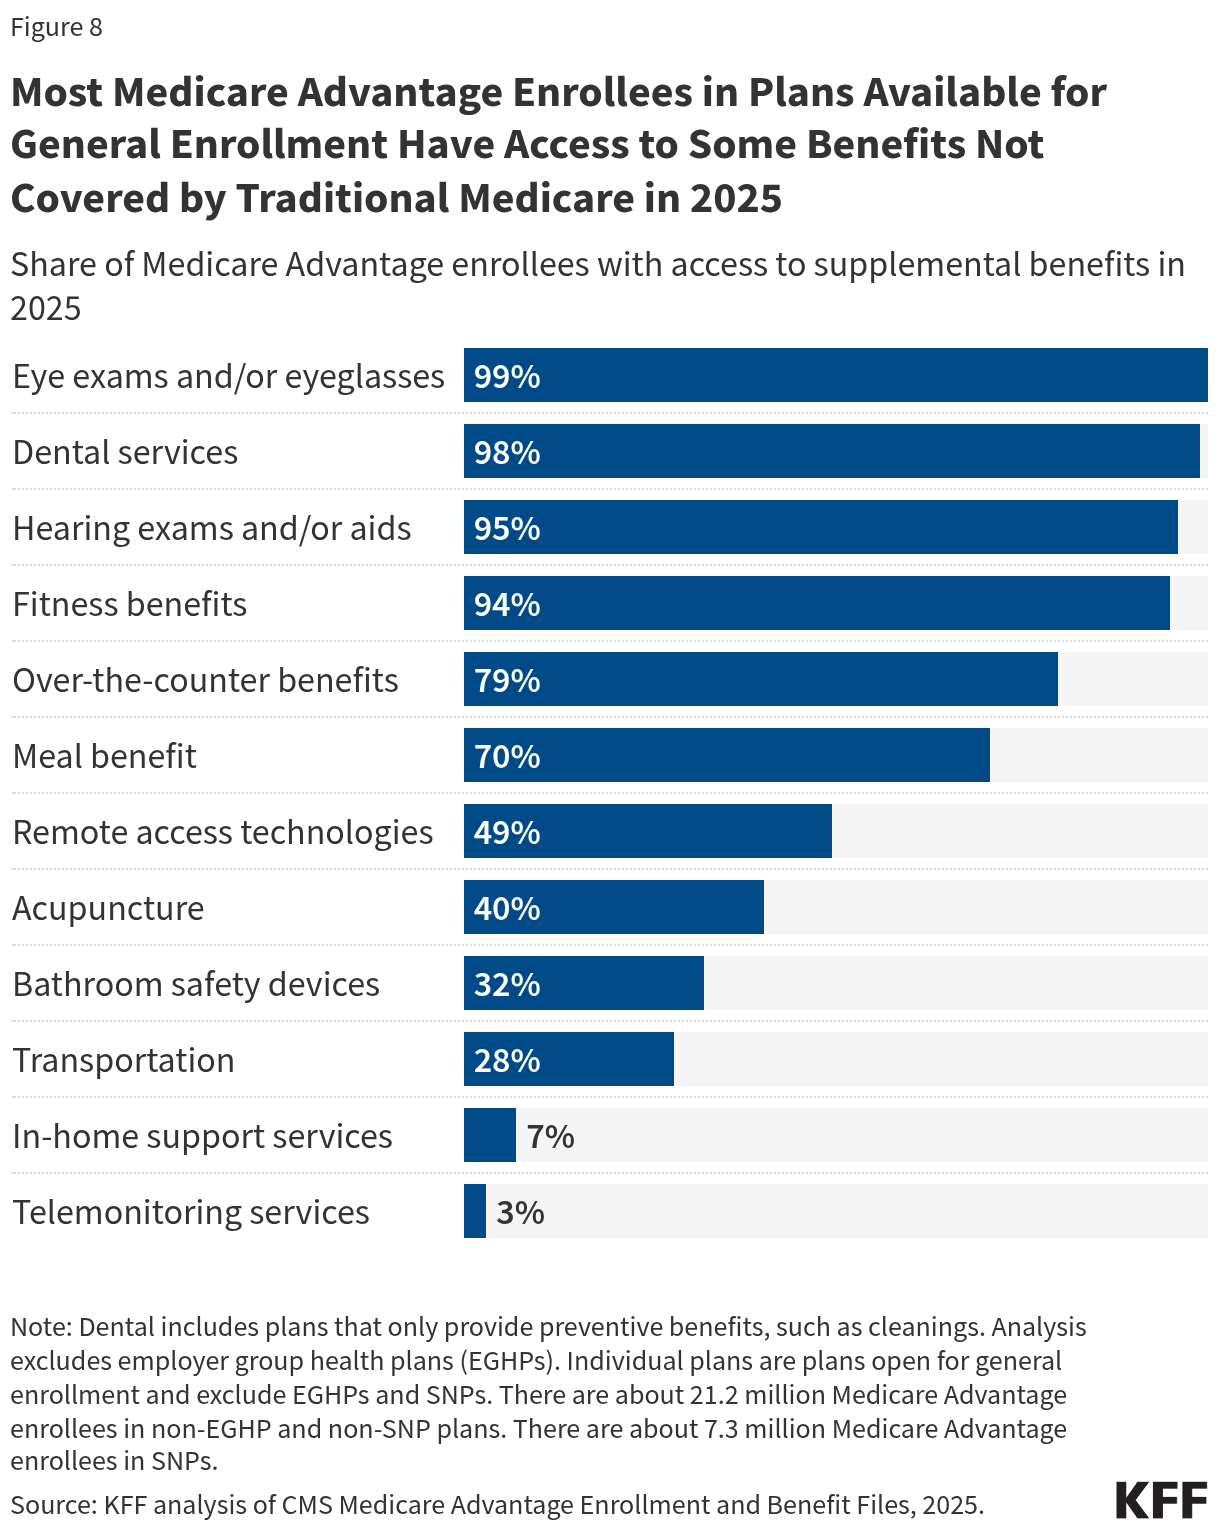
Perhaps the most significant trend in the last decade is the rapid growth of Medicare Advantage (MA). As of 2025, 54% of eligible beneficiaries are enrolled in private plans. This growth is driven by the "one-stop-shop" nature of these plans, the inclusion of supplemental benefits like gym memberships and vision care, and aggressive marketing campaigns.
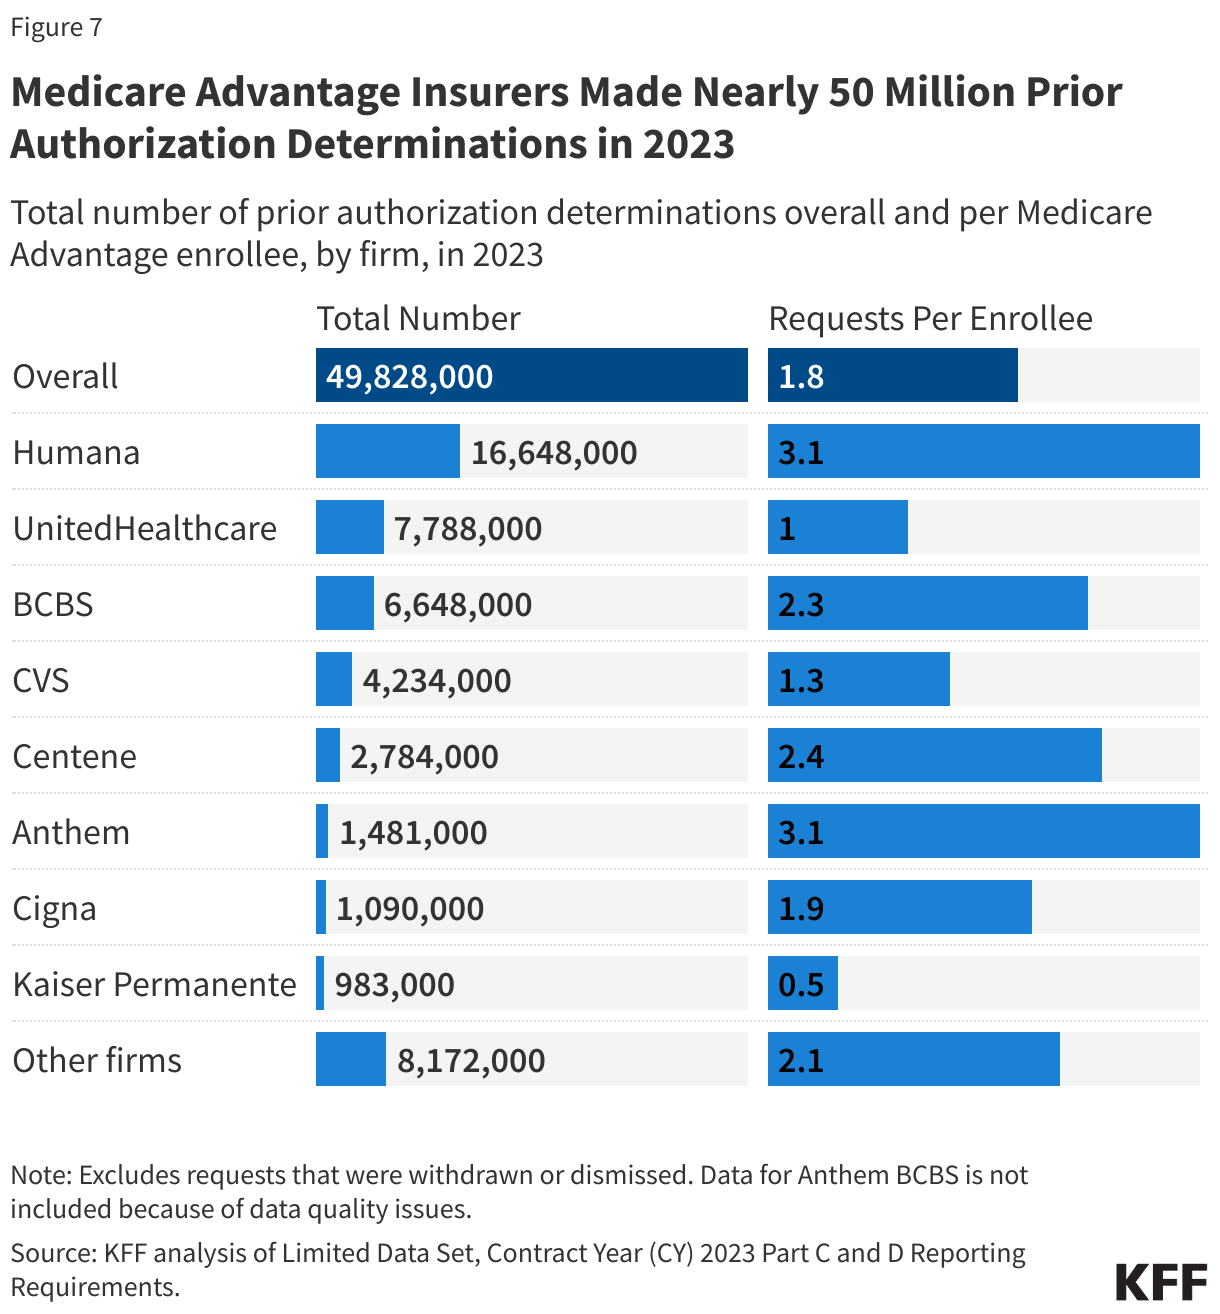
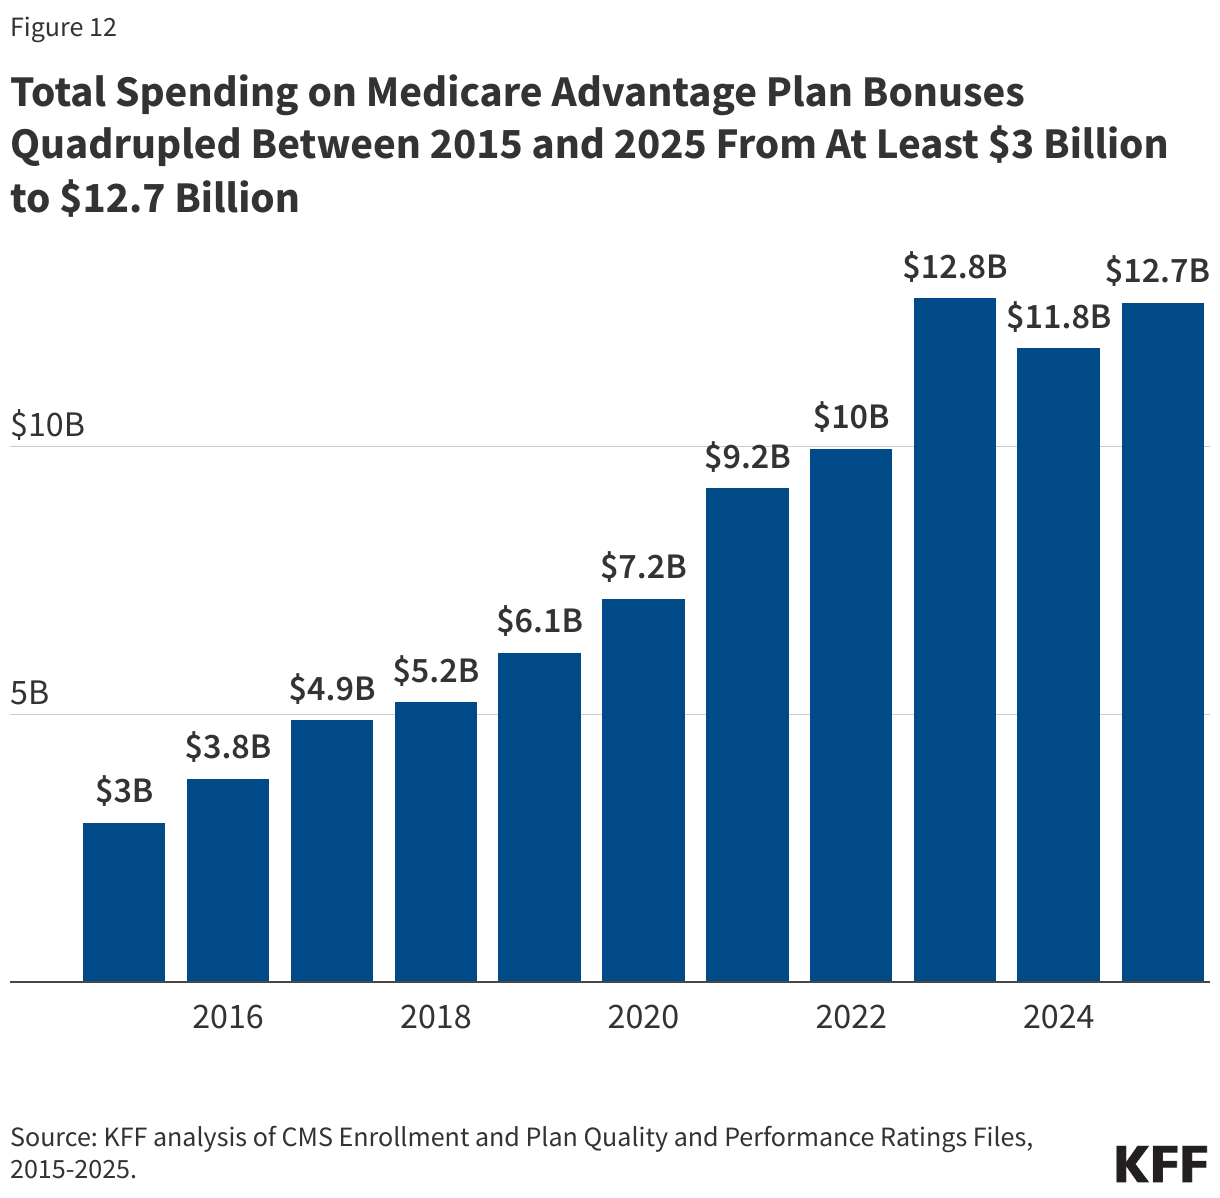
However, the shift toward private plans has sparked a debate over efficiency. The Medicare Payment Advisory Commission (MedPAC) has noted that while MA plans may offer more benefits, they are often paid significantly more than the cost of covering similar beneficiaries in traditional Medicare. In 2025, excess payments to MA plans due to "coding intensity"—where beneficiaries are documented as having more severe health conditions to justify higher risk-adjusted payments—are estimated at $84 billion. These higher payments, combined with quality bonus payments that reached $12.7 billion in 2025, place increasing pressure on the Medicare Hospital Insurance Trust Fund.
Official Responses and Policy Shifts
The federal government, through the Centers for Medicare & Medicaid Services (CMS) and the Innovation Center (CMMI), has attempted to curb rising costs through "alternative payment models." These models, such as the Medicare Shared Savings Program (MSSP), reward providers for managing the health of a patient population rather than simply providing a high volume of services.
In 2023, the MSSP saved Medicare approximately $2.1 billion. Yet, the broader impact of CMMI remains a subject of intense scrutiny. The Congressional Budget Office (CBO) reported that CMMI’s activities increased federal spending by $5.4 billion between 2011 and 2020, as the upfront costs of testing new models often outweighed initial savings.
The strategic direction of these programs is also subject to the political cycle. The Biden administration’s focus on health equity in payment models contrasts with the incoming 2025 administration’s emphasis on competition, transparency, and consumer choice. These competing philosophies ensure that the structure of Medicare payment reform will remain a volatile and evolving landscape.
Implications for the Future
The outlook for Medicare is characterized by three fundamental tensions:
- Solvency Concerns: The Hospital Insurance (Part A) Trust Fund faces depletion. According to the 2025 Trustees report, reserves are projected to be exhausted by 2033. While the CBO offers a more optimistic projection—citing different modeling for medical education payments—the reality remains that without legislative intervention, the program will face a significant funding shortfall.
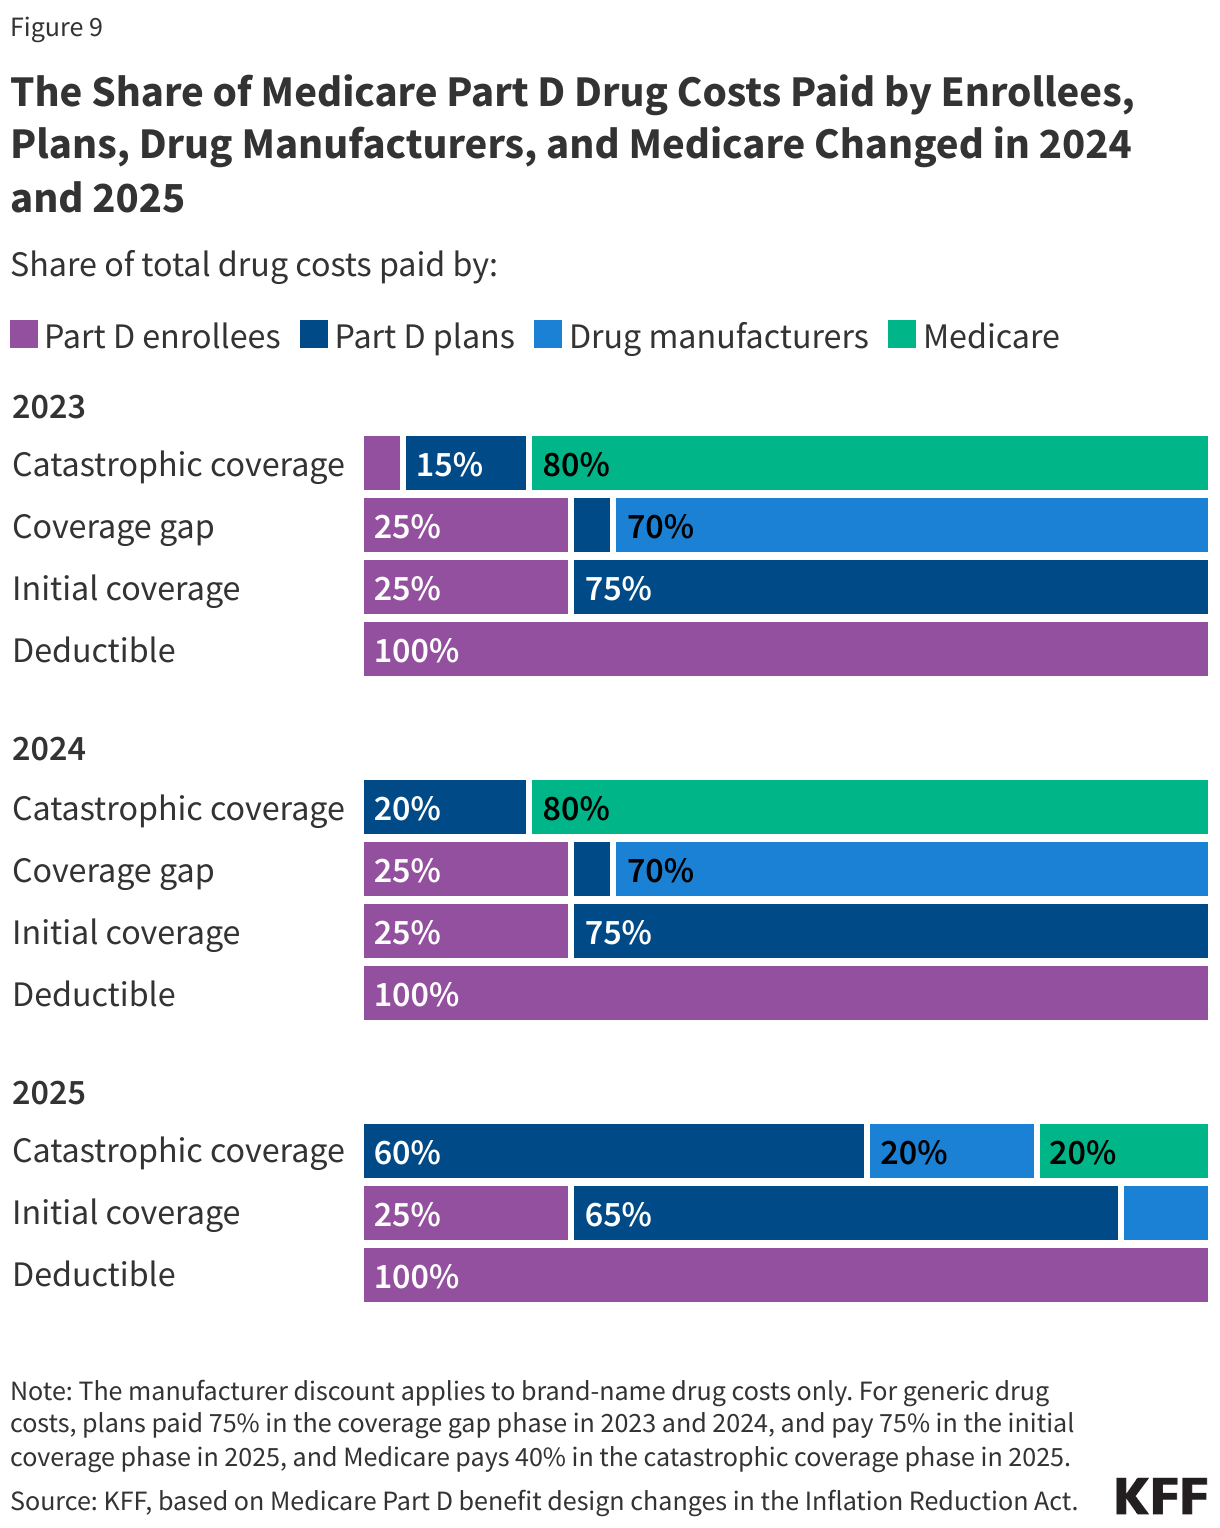
- Affordability vs. Benefits: As the government attempts to control spending, there is a constant risk that cost-cutting measures may reduce the quality of care or the access beneficiaries have to providers. With nearly 11 million Part D enrollees benefiting from the new $2,000 out-of-pocket cap introduced by the IRA, the political appetite for reducing benefits is non-existent, even as fiscal pressures mount.
- The Medicare Advantage Paradox: While MA plans provide popular extra benefits, they also contribute to the long-term strain on the federal budget. Policymakers are faced with the dilemma of how to maintain the attractiveness of these plans for seniors while preventing excessive overpayments to private insurers that threaten the overall sustainability of the system.
Conclusion
Medicare has successfully provided a vital safety net for generations, but its current path is unsustainable without reform. The transition to a more privatized system via Medicare Advantage, the introduction of prescription drug negotiations, and the push for value-based care are all experiments in finding a balance between quality, access, and affordability.
As the program moves toward 2060, the legislative and economic choices made in the coming years will determine whether Medicare can continue to function as a universal promise or if it will be forced to undergo structural changes that fundamentally alter the American approach to aging and healthcare. For now, the program remains the single most important policy lever in the U.S. health system, and its future will continue to be the primary battleground of federal health policy.
About the Author