Executive Summary: The Flexibility Paradox
Medicaid Section 1115 demonstration waivers have long served as the primary laboratory for American healthcare policy. By allowing states to bypass specific federal statutory requirements, these waivers grant governors and state legislatures the authority to test innovative models for care delivery, eligibility expansion, and benefit design—provided the Secretary of Health and Human Services (HHS) deems the project likely to "promote the objectives of the Medicaid program."
However, the "objectives" of Medicaid are subject to profound ideological shifts. As the United States moves through mid-decade, the landscape of 1115 waivers is undergoing a significant transformation. The transition from the policy priorities of the Biden-Harris administration to the current trajectory under the second Trump administration has fundamentally altered the federal-state dynamic. From the rescission of health-related social needs (HRSN) frameworks to the impending enforcement of mandatory federal work requirements, the Medicaid program is currently at a policy crossroads.
Chronology of Policy Flux (2022–2026)
The history of 1115 waivers is a timeline of administrative priorities.
- 2022–2023: The Era of Social Determinants. Under the Biden-Harris administration, CMS encouraged states to tackle "Health-Related Social Needs" (HRSN), such as housing instability and food insecurity, via waivers. Simultaneously, guidance was issued to facilitate pre-release Medicaid coverage for incarcerated individuals to improve continuity of care upon reentry.
- January 2024: The Consolidated Appropriations Act, 2023 mandate took effect, requiring 12-month continuous eligibility for children nationwide.
- March 2025: The Trump administration formally rescinded the Biden-era HRSN guidance. While existing approvals remain intact, the federal posture shifted to a "case-by-case" review process, effectively chilling the momentum for new, expansive social-needs initiatives.
- April 2025: The administration announced a phase-out of federal funding for "Designated State Health Programs" (DSHP), a move aimed at tightening fiscal constraints on state waiver requests.
- July 2025: A pivotal moment occurred when the administration declared it would no longer approve or renew waivers for multi-year continuous eligibility for children or adults. Additionally, initiatives designed to strengthen the primary care and behavioral health workforce were marked for phase-out.
- January 1, 2027: The statutory deadline for mandatory work requirements for ACA expansion adults arrives, setting the stage for nationwide implementation.
The Work Requirement Mandate: A New Regulatory Reality
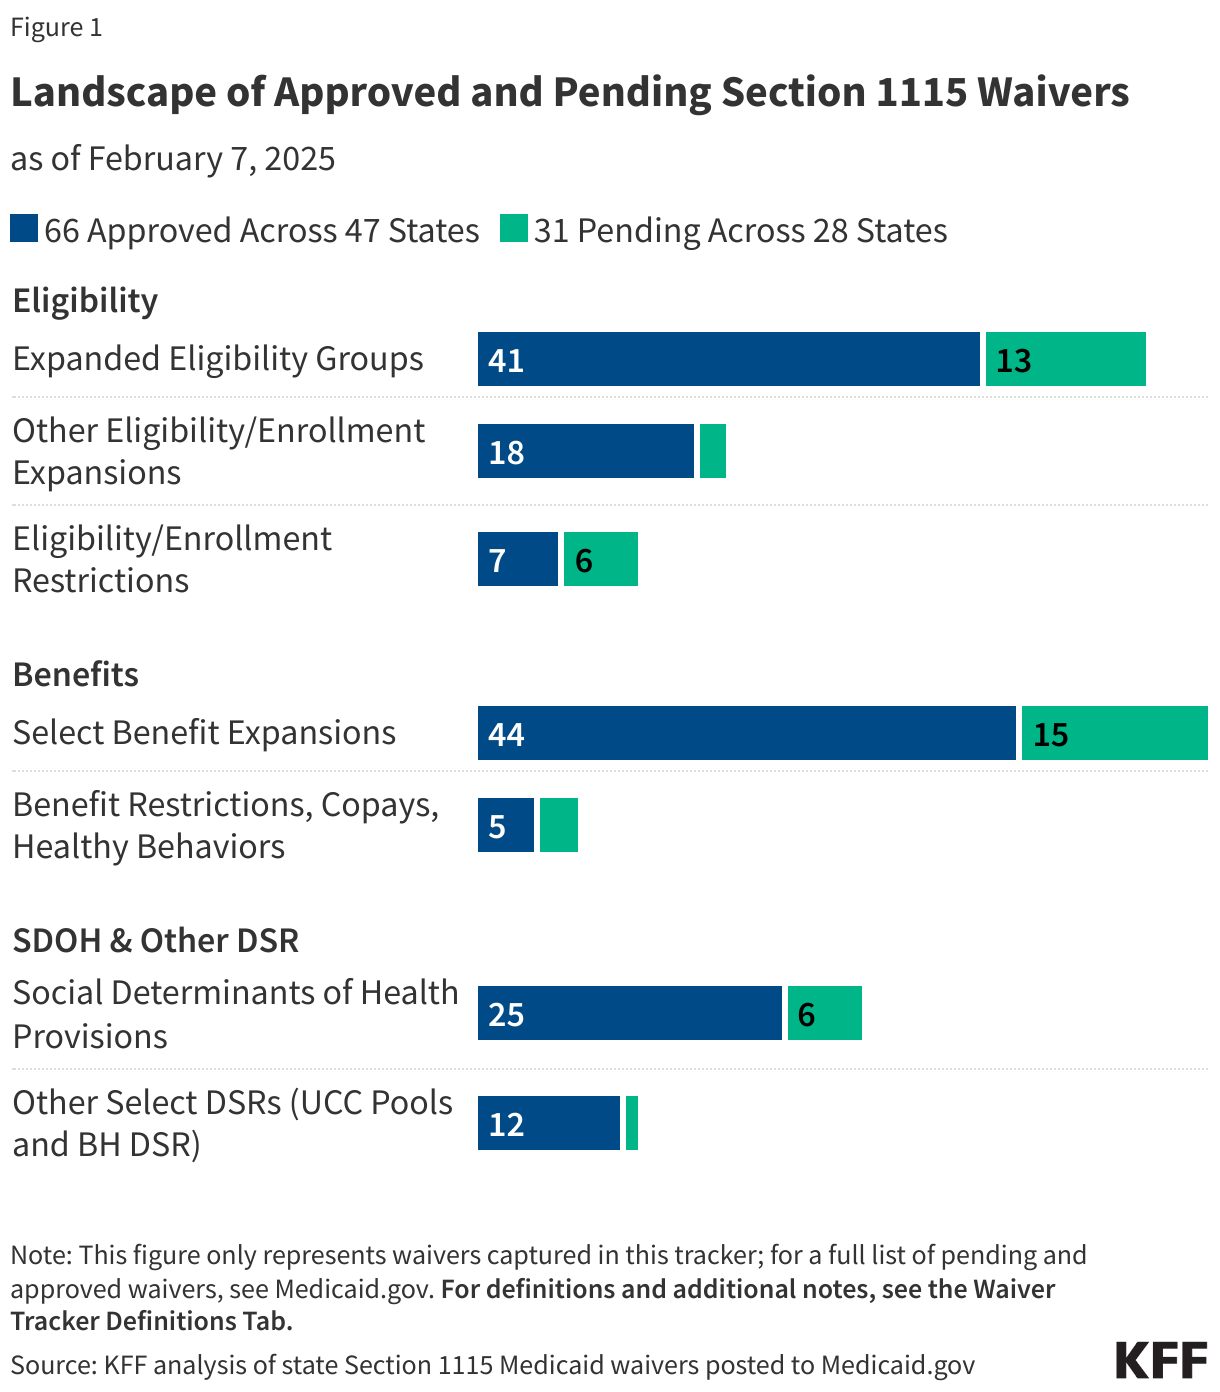
Perhaps the most contentious issue in the Medicaid space remains the requirement for work. While previous battles were fought over whether states could implement work requirements, the 2025 tax and spending law effectively settled the debate by mandating them at the federal level for ACA expansion adults.
Early Implementation and State Strategies
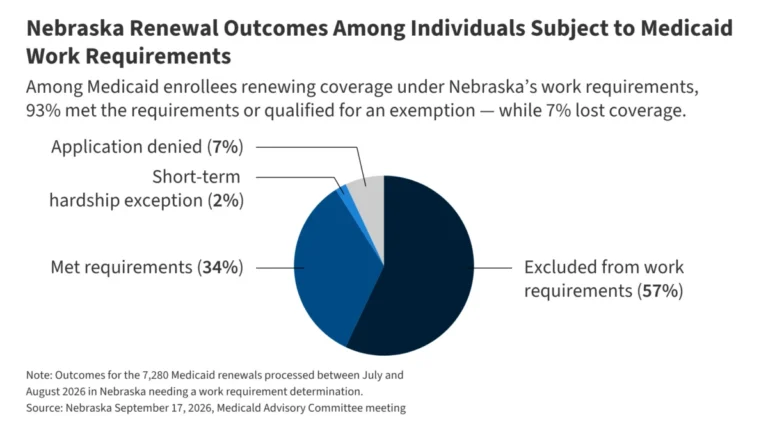
While the federal deadline is January 1, 2027, several states are opting for early adoption through State Plan Amendments (SPAs). Nebraska, for instance, has moved to enforce requirements as early as May 2026, followed by Montana and Iowa. Arkansas has adopted a "soft launch" approach, focusing on administrative readiness before the threat of disenrollment becomes active in 2027.
Georgia remains a unique case study. Following protracted litigation against the Biden administration’s attempts to halt its waiver, Georgia currently operates the only active work requirement program. This waiver is set to expire at the end of 2026, at which point the state will be required to transition into full compliance with the new federal standard.
The Decline of the Waiver Route
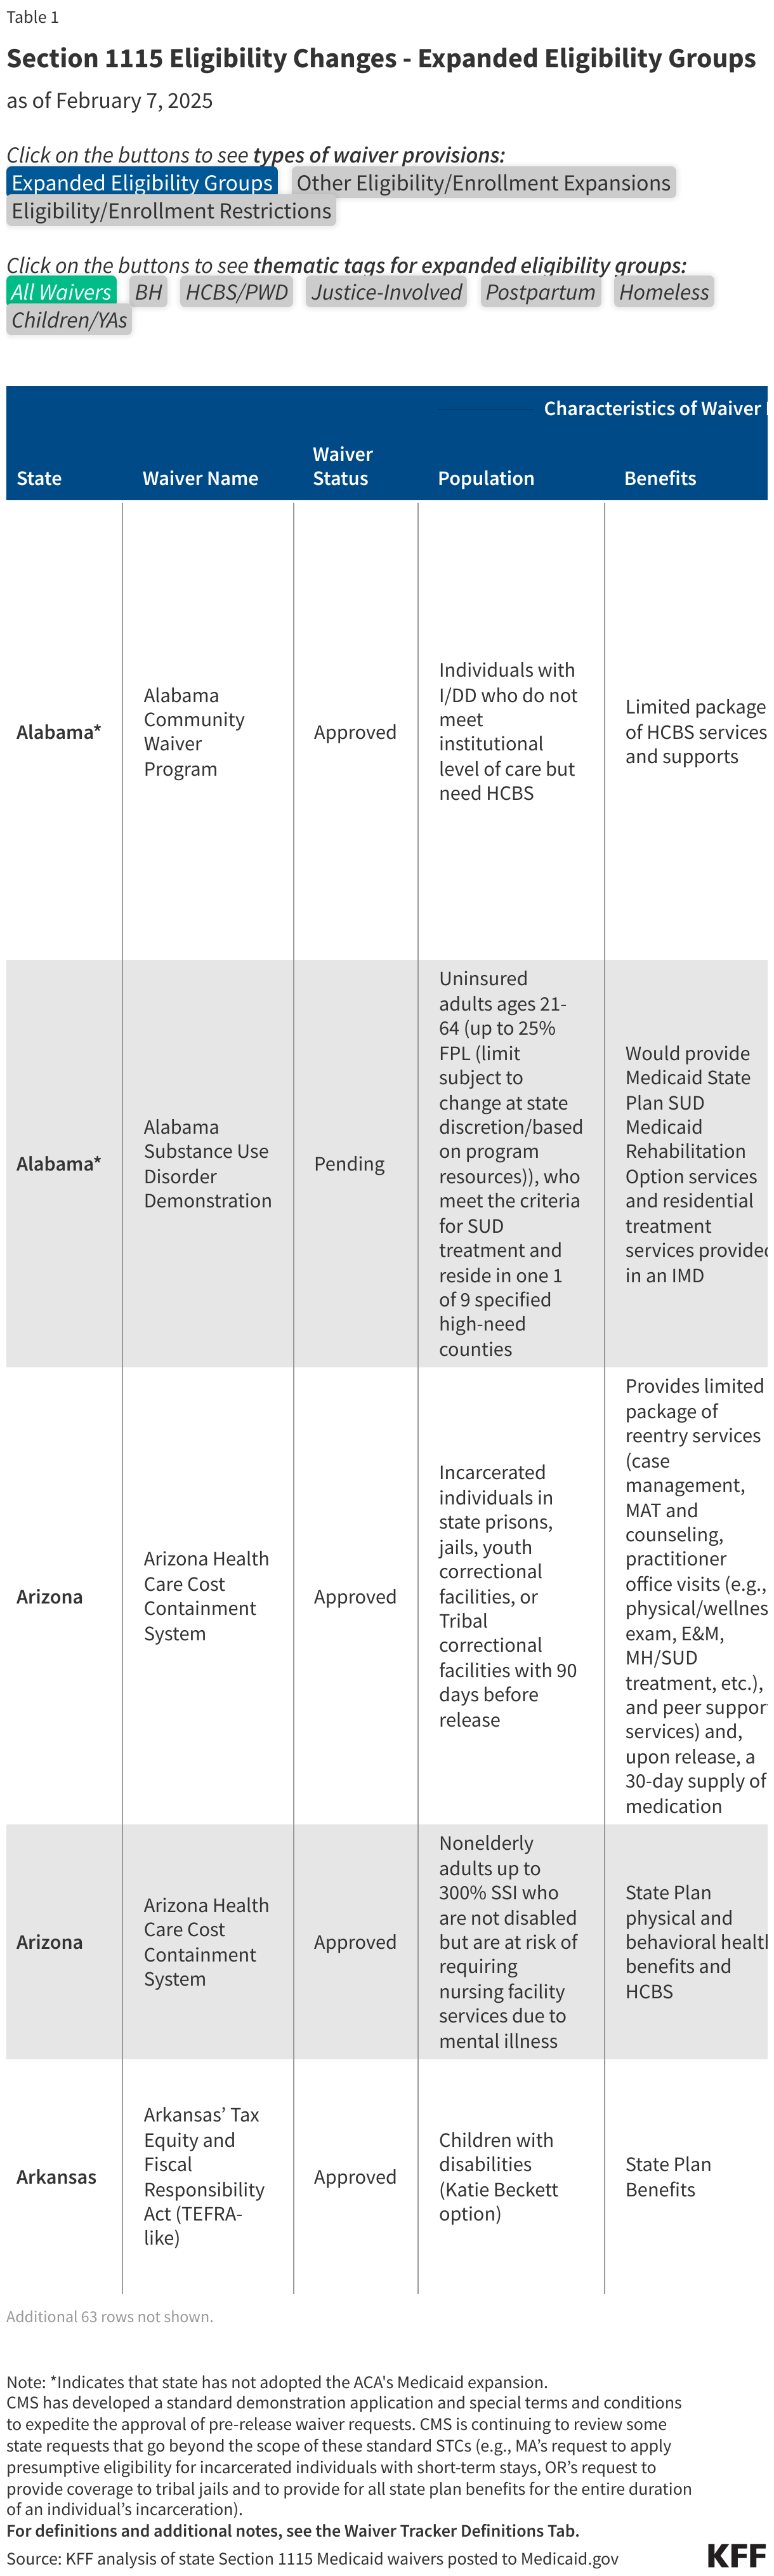
Previously, states used 1115 waivers as the primary vehicle to seek permission for work requirements. Now, with a federal mandate in place, the utility of the 1115 waiver for this purpose has diminished. The administrative burden of navigating federal approval is being bypassed in favor of the more direct, legislatively mandated path.
The Retreat from Social Determinants and Continuous Coverage
For years, advocates and health policy experts pointed to HRSN waivers as a breakthrough in addressing the non-medical drivers of health. By covering services like rent subsidies for the homeless or nutritional counseling for the food-insecure, states were beginning to integrate social care into the medical benefit package.
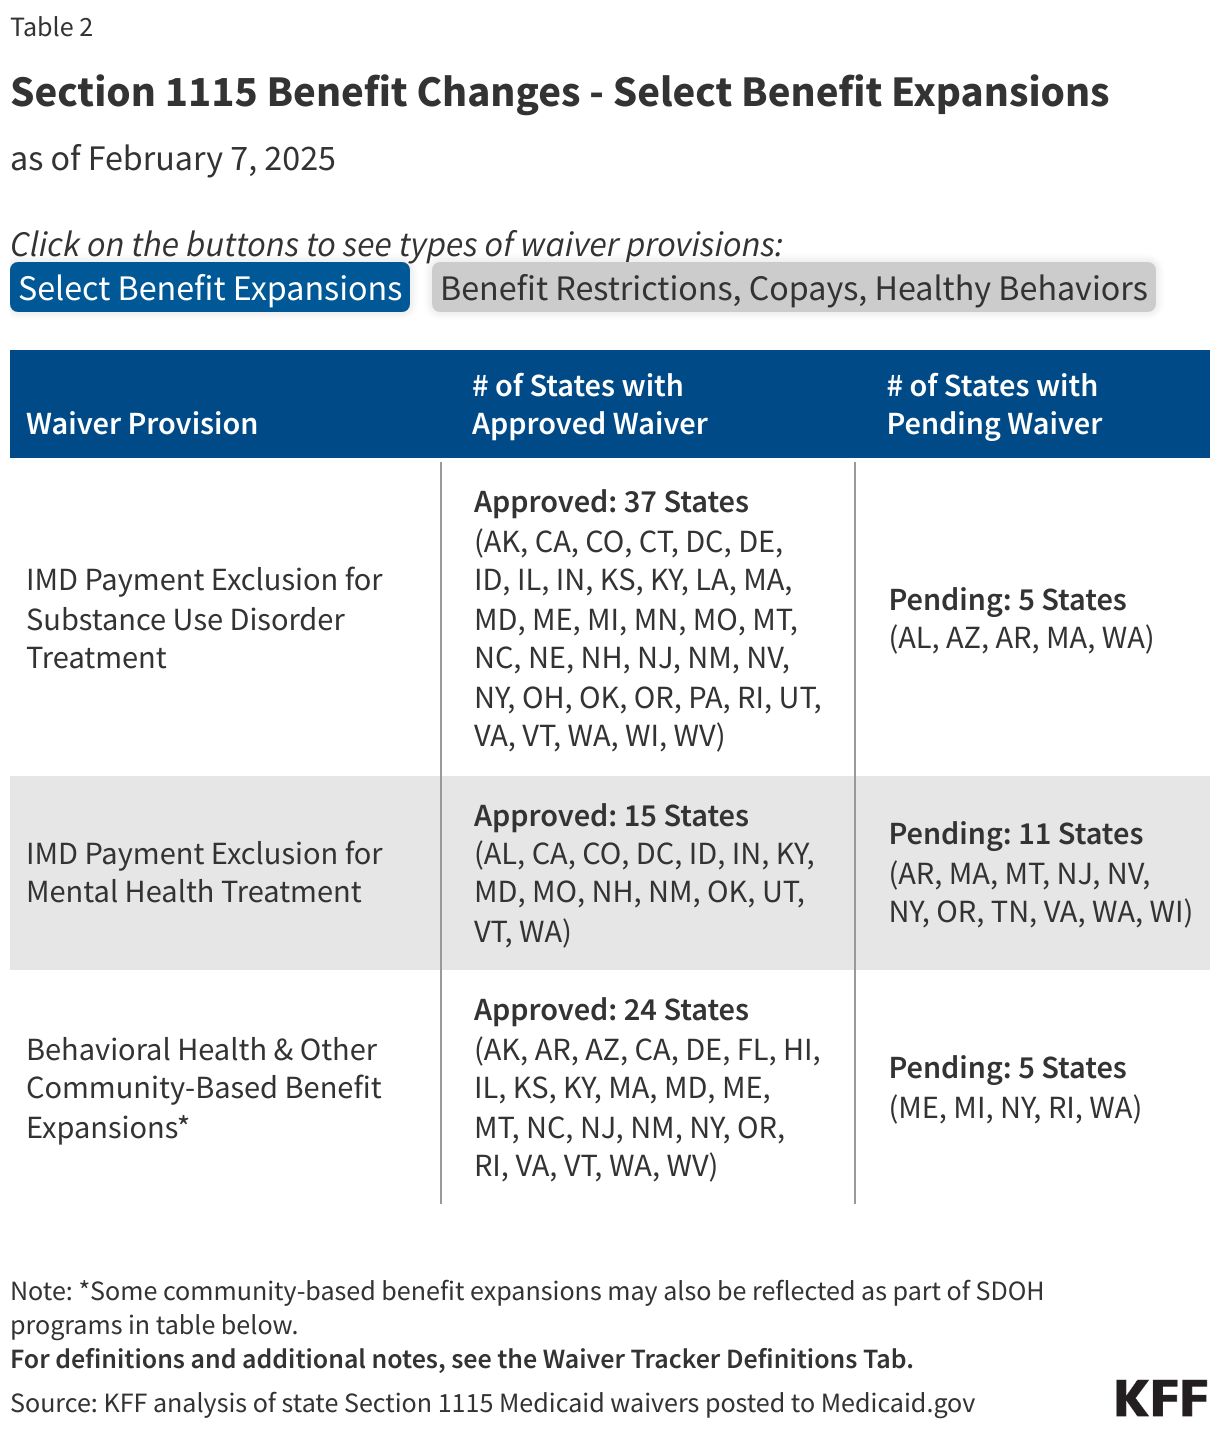
The Trump administration’s decision to rescind the overarching HRSN framework marks a return to a more traditionalist view of Medicaid—one that prioritizes clinical services over social support. The impact on state-level innovation is profound:
- Fiscal Contraction: By phasing out DSHP funding, the federal government has removed a key financial lever that allowed states to experiment with service delivery.
- Continuous Eligibility: The cessation of multi-year continuous eligibility waivers strikes at a policy that had bipartisan support for its ability to reduce "churn." By forcing children and adults back into the traditional annual renewal cycle, the administration is prioritizing administrative efficiency over the stability of coverage.
Implications for Patients and Healthcare Systems
The cumulative effect of these changes is a tightening of the Medicaid "safety net."

For the Beneficiary
The most immediate impact will be felt by low-income adults in expansion states. The combination of mandatory work requirements and the shortening of retroactive eligibility—now capped at one month for expansion enrollees and two months for traditional enrollees—will likely increase the number of uninsured individuals. When coverage is lost due to administrative errors or failure to meet work documentation requirements, the "churn" mentioned in earlier reports will inevitably rise, leading to fragmented care and poorer health outcomes for chronic disease management.
For the Provider
Hospitals and community health centers, particularly those in rural or underserved urban areas, face significant financial risk. Retroactive eligibility has historically served as a financial backstop for providers treating patients who arrive at emergency rooms without active coverage. By shortening this window, the federal government is shifting the burden of uncompensated care back onto health systems.
For the State
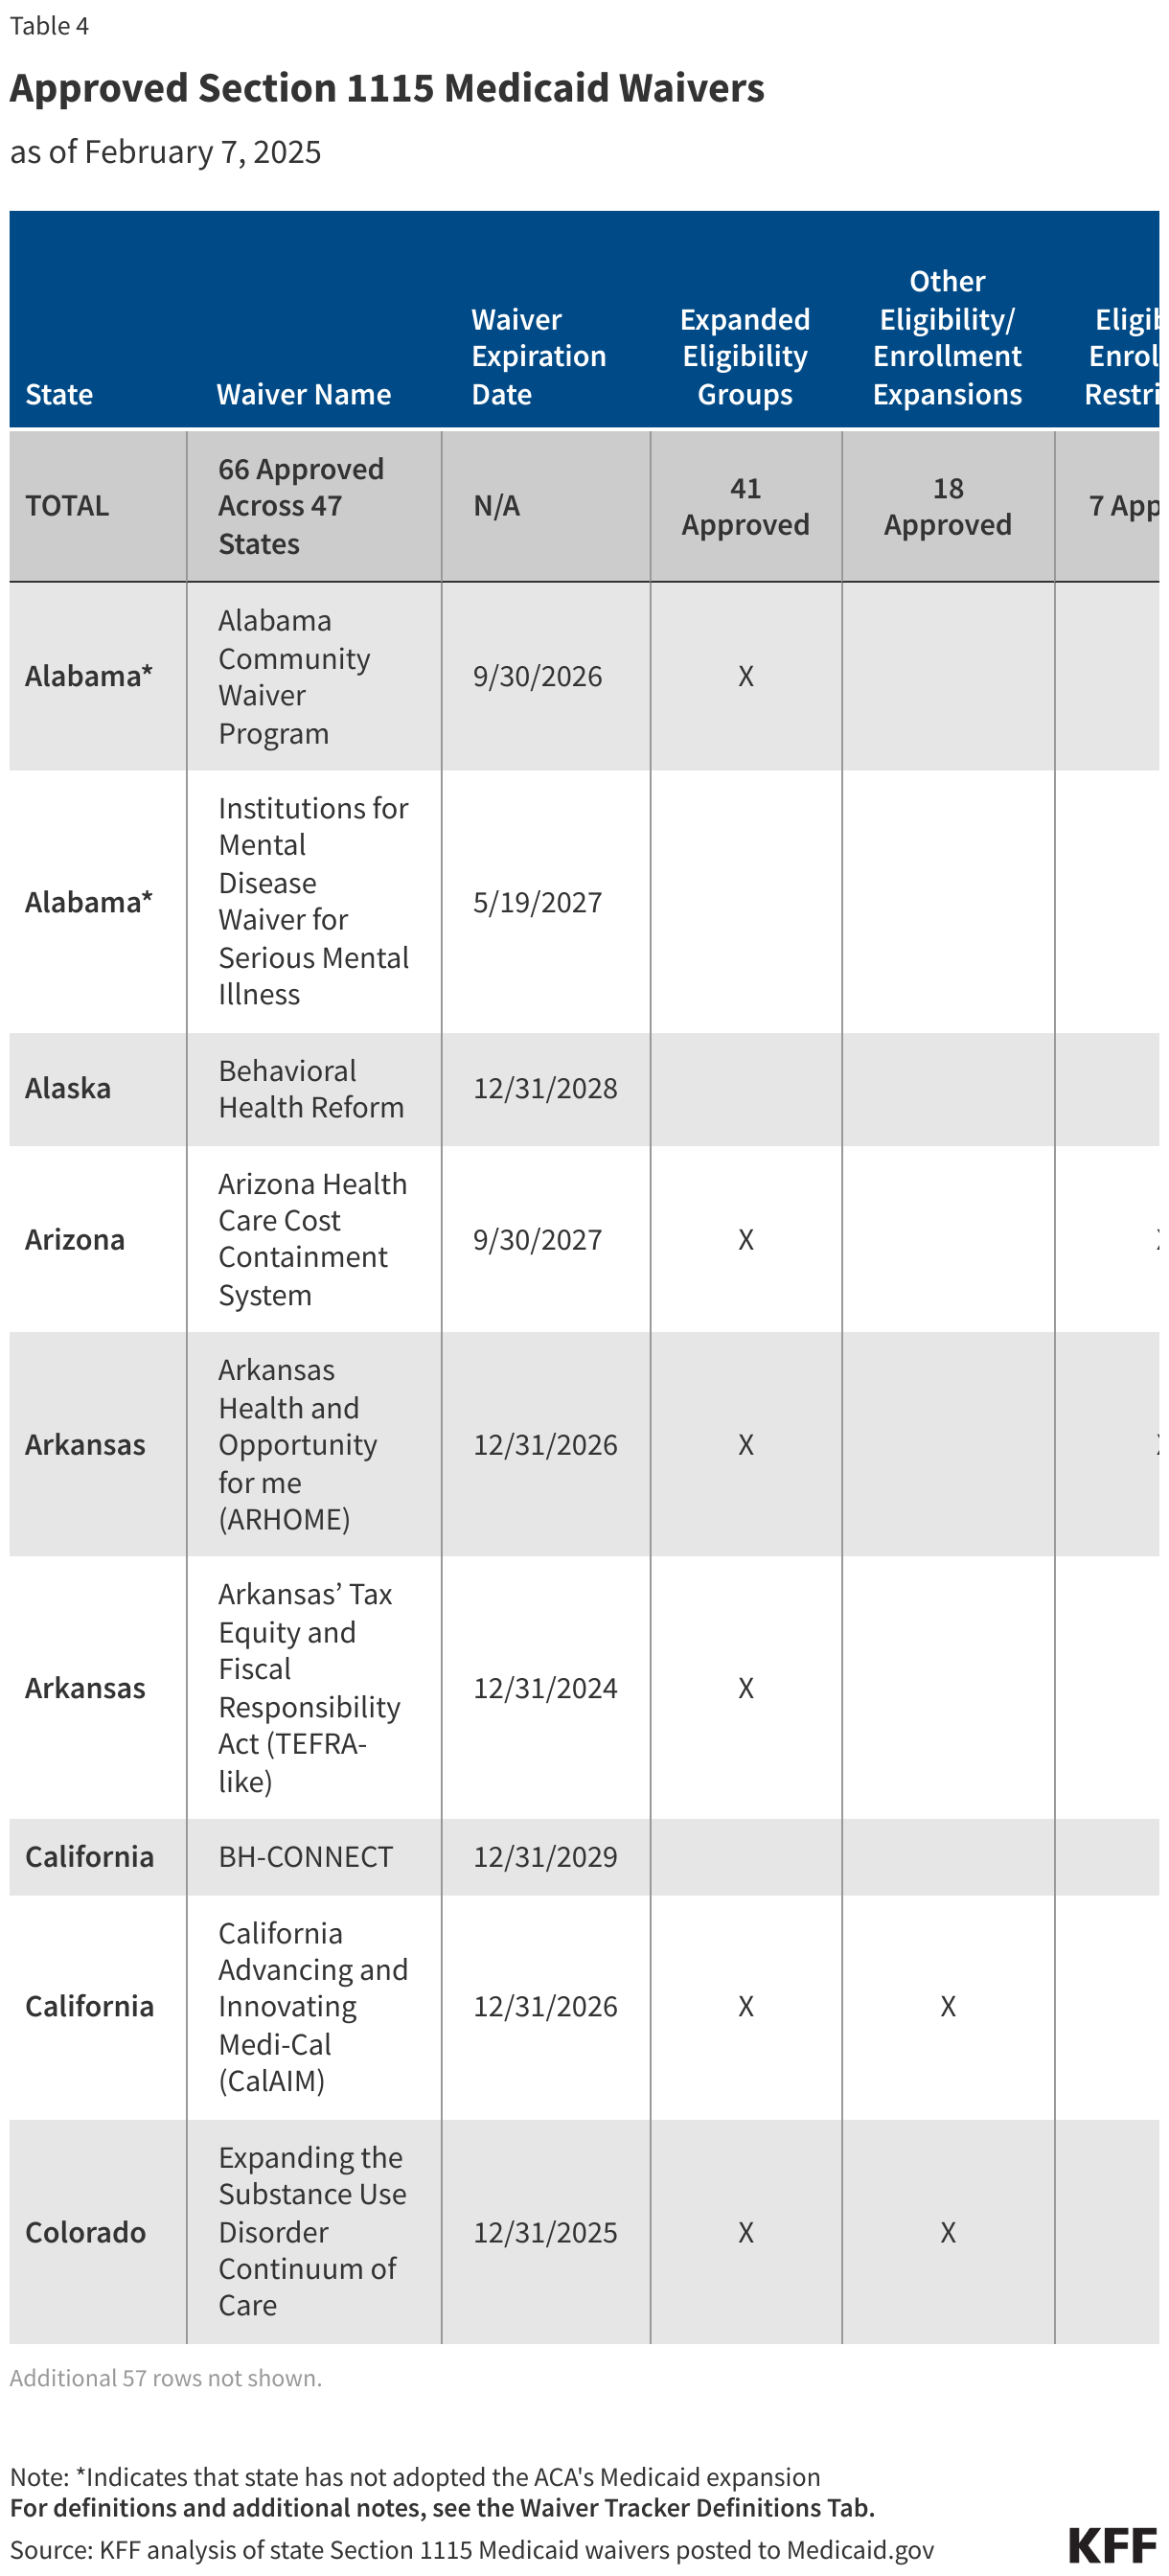
States now face a "compliance over innovation" environment. With federal funding for infrastructure and capacity building being curtailed, states that previously used 1115 waivers to build out robust delivery systems must now pivot to maintain existing services under stricter oversight. The case-by-case review process for social services adds a layer of uncertainty that makes long-term state budgetary planning significantly more difficult.
Looking Ahead: The Role of the Judiciary
As seen in the case of the Healthy Indiana Plan 2.0, the courts remain a major arbiter of Medicaid policy. The D.C. District Court’s decision to vacate federal approval for Indiana’s waiver—specifically regarding premiums and the waiving of Non-Emergency Medical Transportation (NEMT)—reminds us that Section 1115 authority is not absolute. Even when the executive branch attempts to steer the program, the judiciary retains the power to enforce the statutory limits of what the Secretary can authorize.
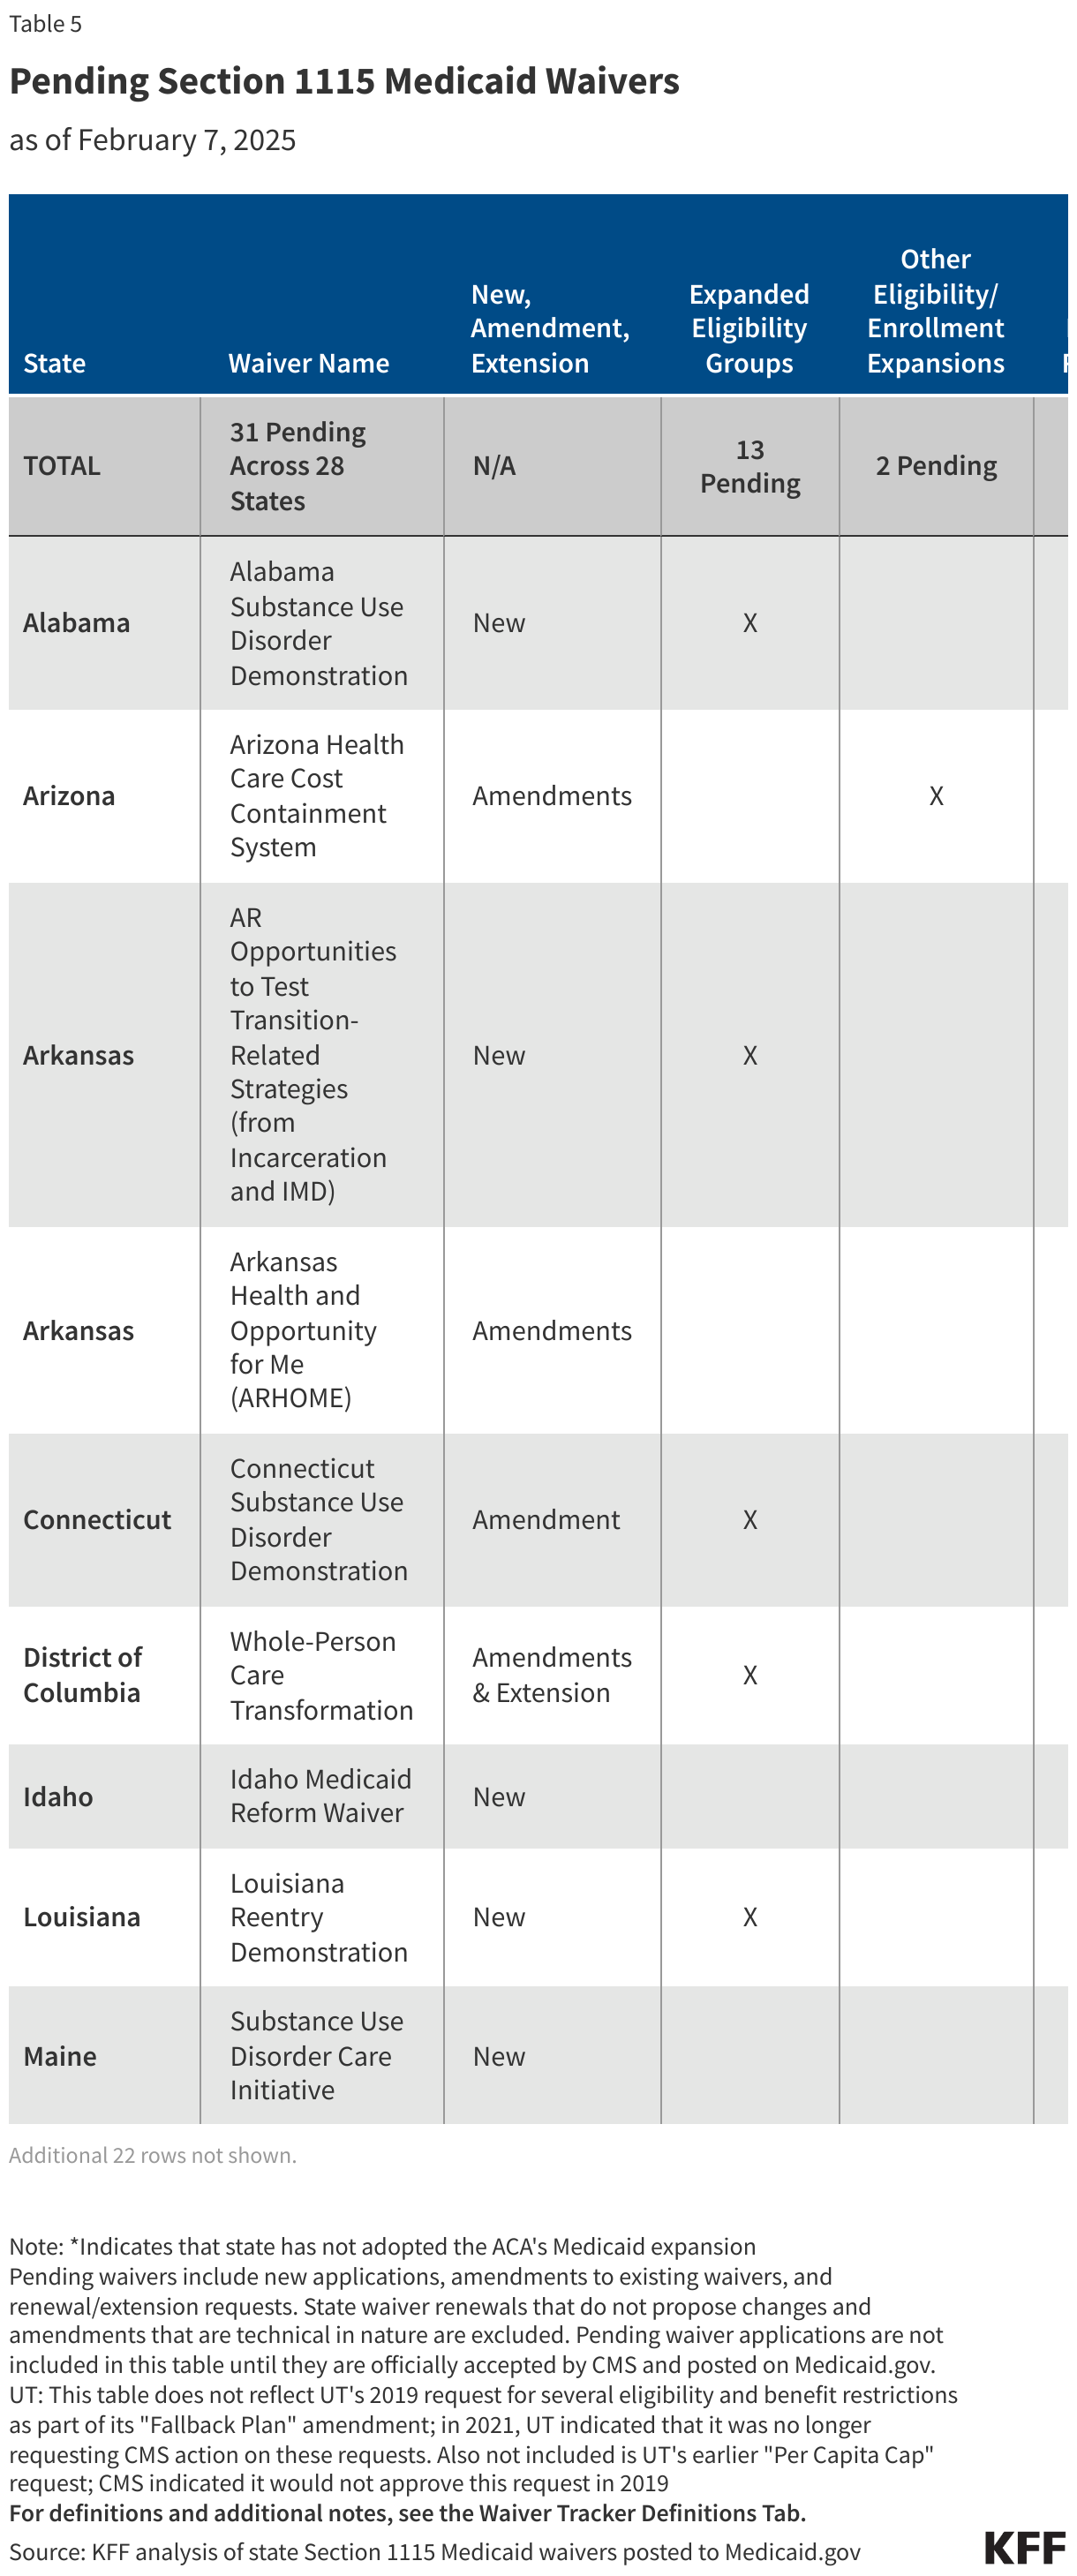
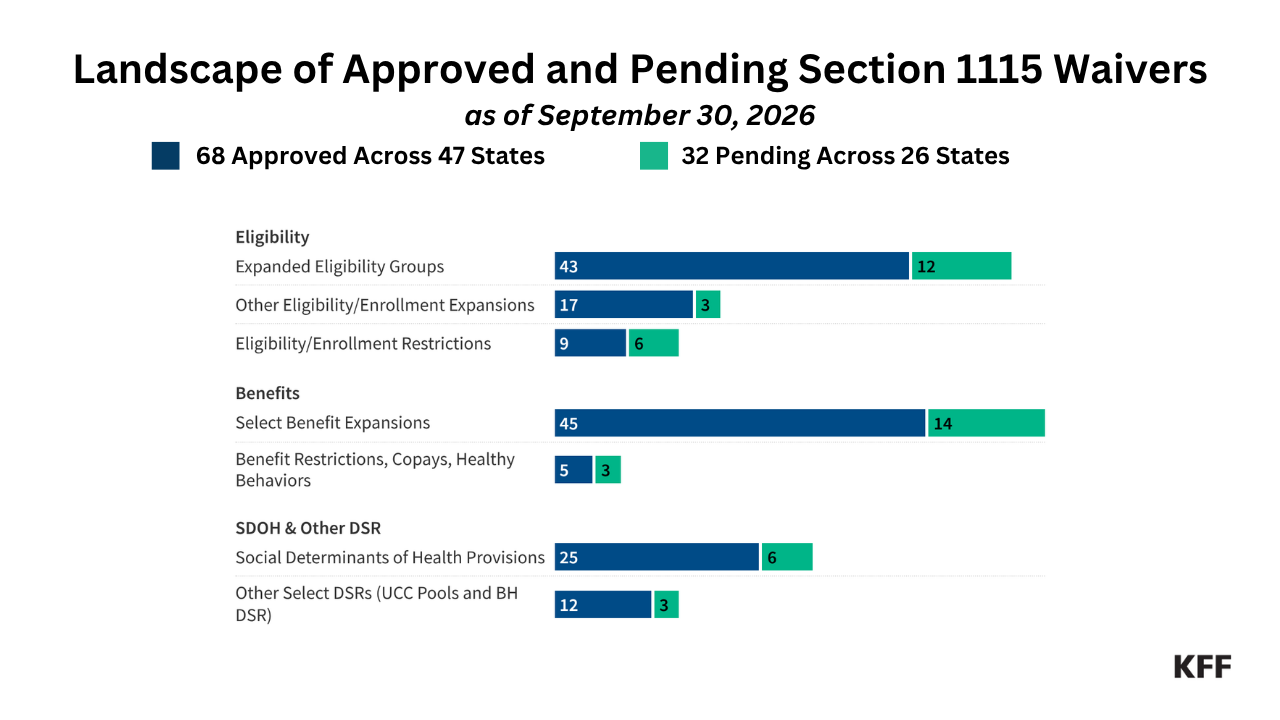
The coming two years will be defined by the transition to the 2027 federal requirements. While the "tracker" data provided by organizations like KFF shows a flurry of activity, the next wave of state submissions will likely focus on administrative compliance rather than the experimental, "demonstration-style" policies that defined the 2022–2024 period.
Conclusion
The Section 1115 waiver, once a tool for expansive, state-led reform, is being repurposed as a mechanism for aligning state programs with a more restrictive federal vision. The focus has moved away from addressing the "whole person" through social supports and toward a framework defined by labor participation and administrative rigor. For the millions of Americans who rely on Medicaid for their health and well-being, the next phase of this policy evolution will be a test of whether the program can maintain its essential function as a safety net in an increasingly austere regulatory climate.
About the Author