The rapid rise of the direct-to-consumer (DTC) telehealth market for compounded GLP-1 weight-loss drugs has evolved into a public health concern of unprecedented scale. As of mid-2026, the FDA has logged more than 1,700 adverse event reports linked to compounded versions of semaglutide and tirzepatide. This surge in reported complications comes against a backdrop of aggressive marketing, questionable clinical oversight, and a complex network of interconnected telehealth storefronts that regulators and legal experts argue may be obscuring the origins of the products they peddle.
The Genesis of a Billion-Dollar Market
The appetite for weight-loss medications like Wegovy and Zepbound created a supply-demand chasm that the pharmaceutical industry could not initially bridge. When the FDA placed these drugs on the national shortage list—starting with Wegovy in March 2022—it inadvertently opened a narrow legal pathway for compounding pharmacies to produce "copies" of these patented medications.
What began as a localized effort to serve patients in need quickly ballooned into a multi-billion-dollar industry. Companies like MEDVi emerged, utilizing generative AI and aggressive digital marketing to scale operations. In April 2026, reports suggested that MEDVi was on track to hit $1.8 billion in annual sales, having already generated $401 million in 2025. However, this financial success has been marred by allegations of deceptive practices.

Chronology of Regulatory Friction
The relationship between federal regulators and the burgeoning compounded GLP-1 sector has been increasingly adversarial.
- 2022–2024: As drug shortages persisted, the FDA granted temporary enforcement discretion, allowing compounders to fill the gap. During this window, massive players like Empower Pharmacy saw their revenue skyrocket; internal records indicate that GLP-1 formulations accounted for 66% of the pharmacy’s $311 million revenue during the first ten months of 2024.
- May 2025: The final enforcement discretion window for these medications officially closed following the stabilization of the national supply.
- February–June 2026: The FDA initiated a series of aggressive crackdowns, issuing dozens of warning letters to telehealth companies for "misbranding" and for making misleading claims regarding the equivalence of their compounded products to FDA-approved versions.
- August 2026: The industry continues to face intense pressure as class-action lawsuits mount and federal legislation, such as the SAFE Drugs Act of 2025, remains under review in the House.
The "Copycat" Playbook: Interconnected Networks
A troubling pattern has emerged in how these companies operate. Investigative findings suggest that a small, overlapping group of clinicians, pharmacy networks, and telehealth platforms are powering dozens of distinct "brands."
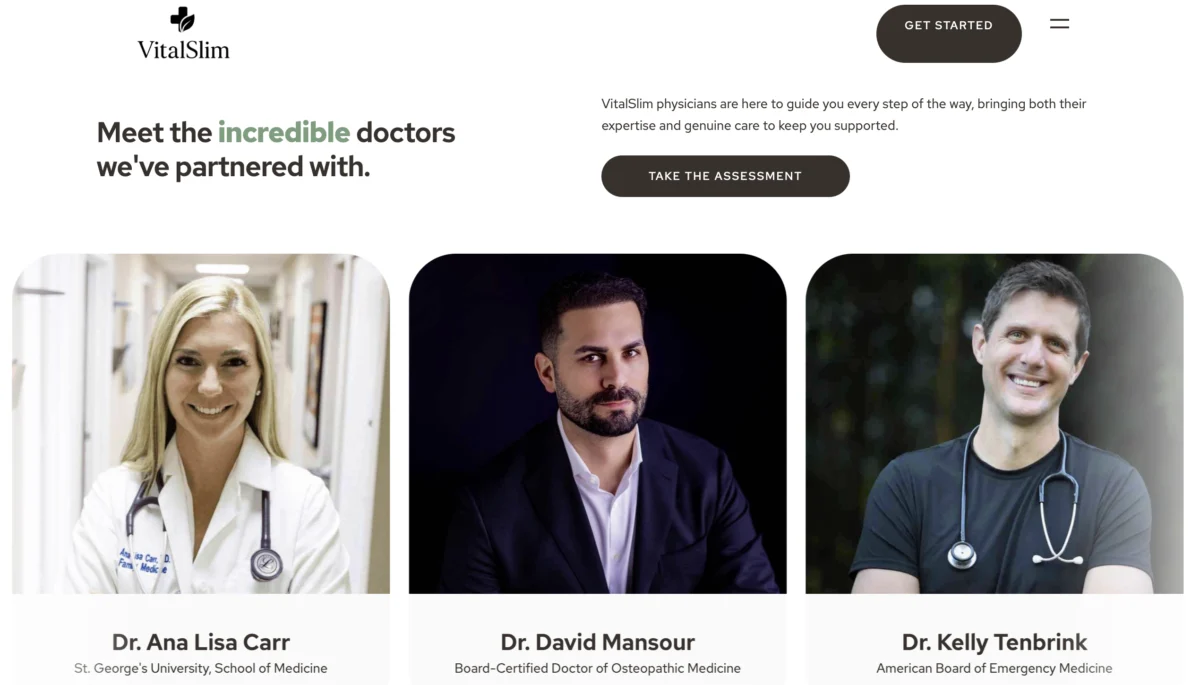
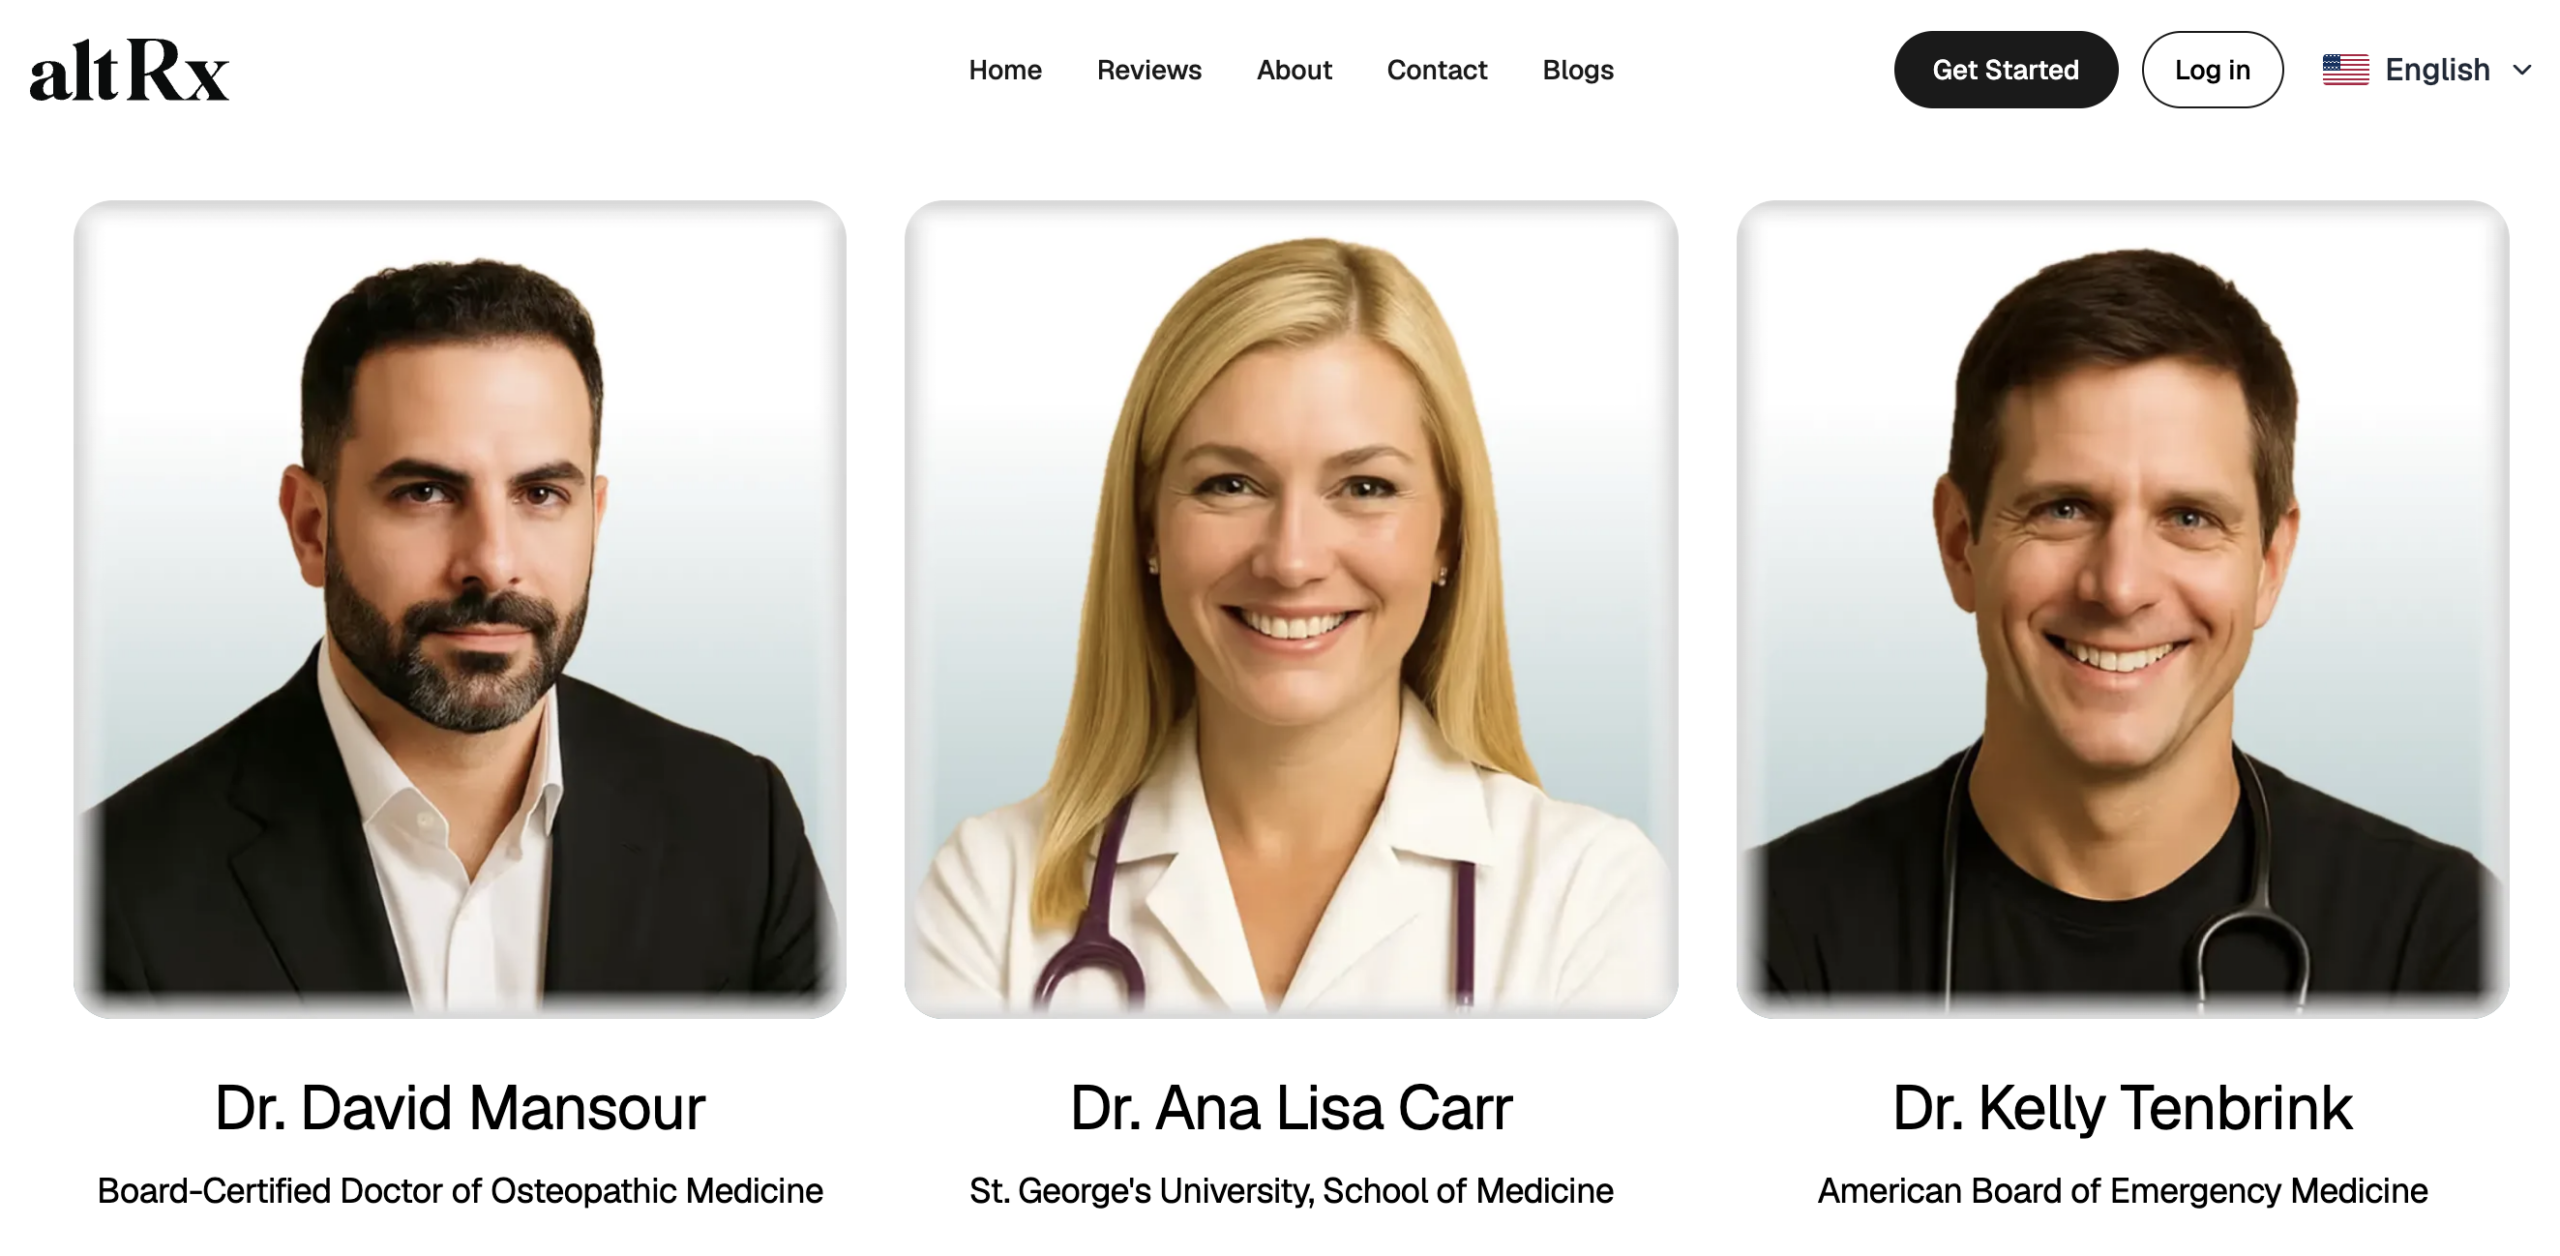
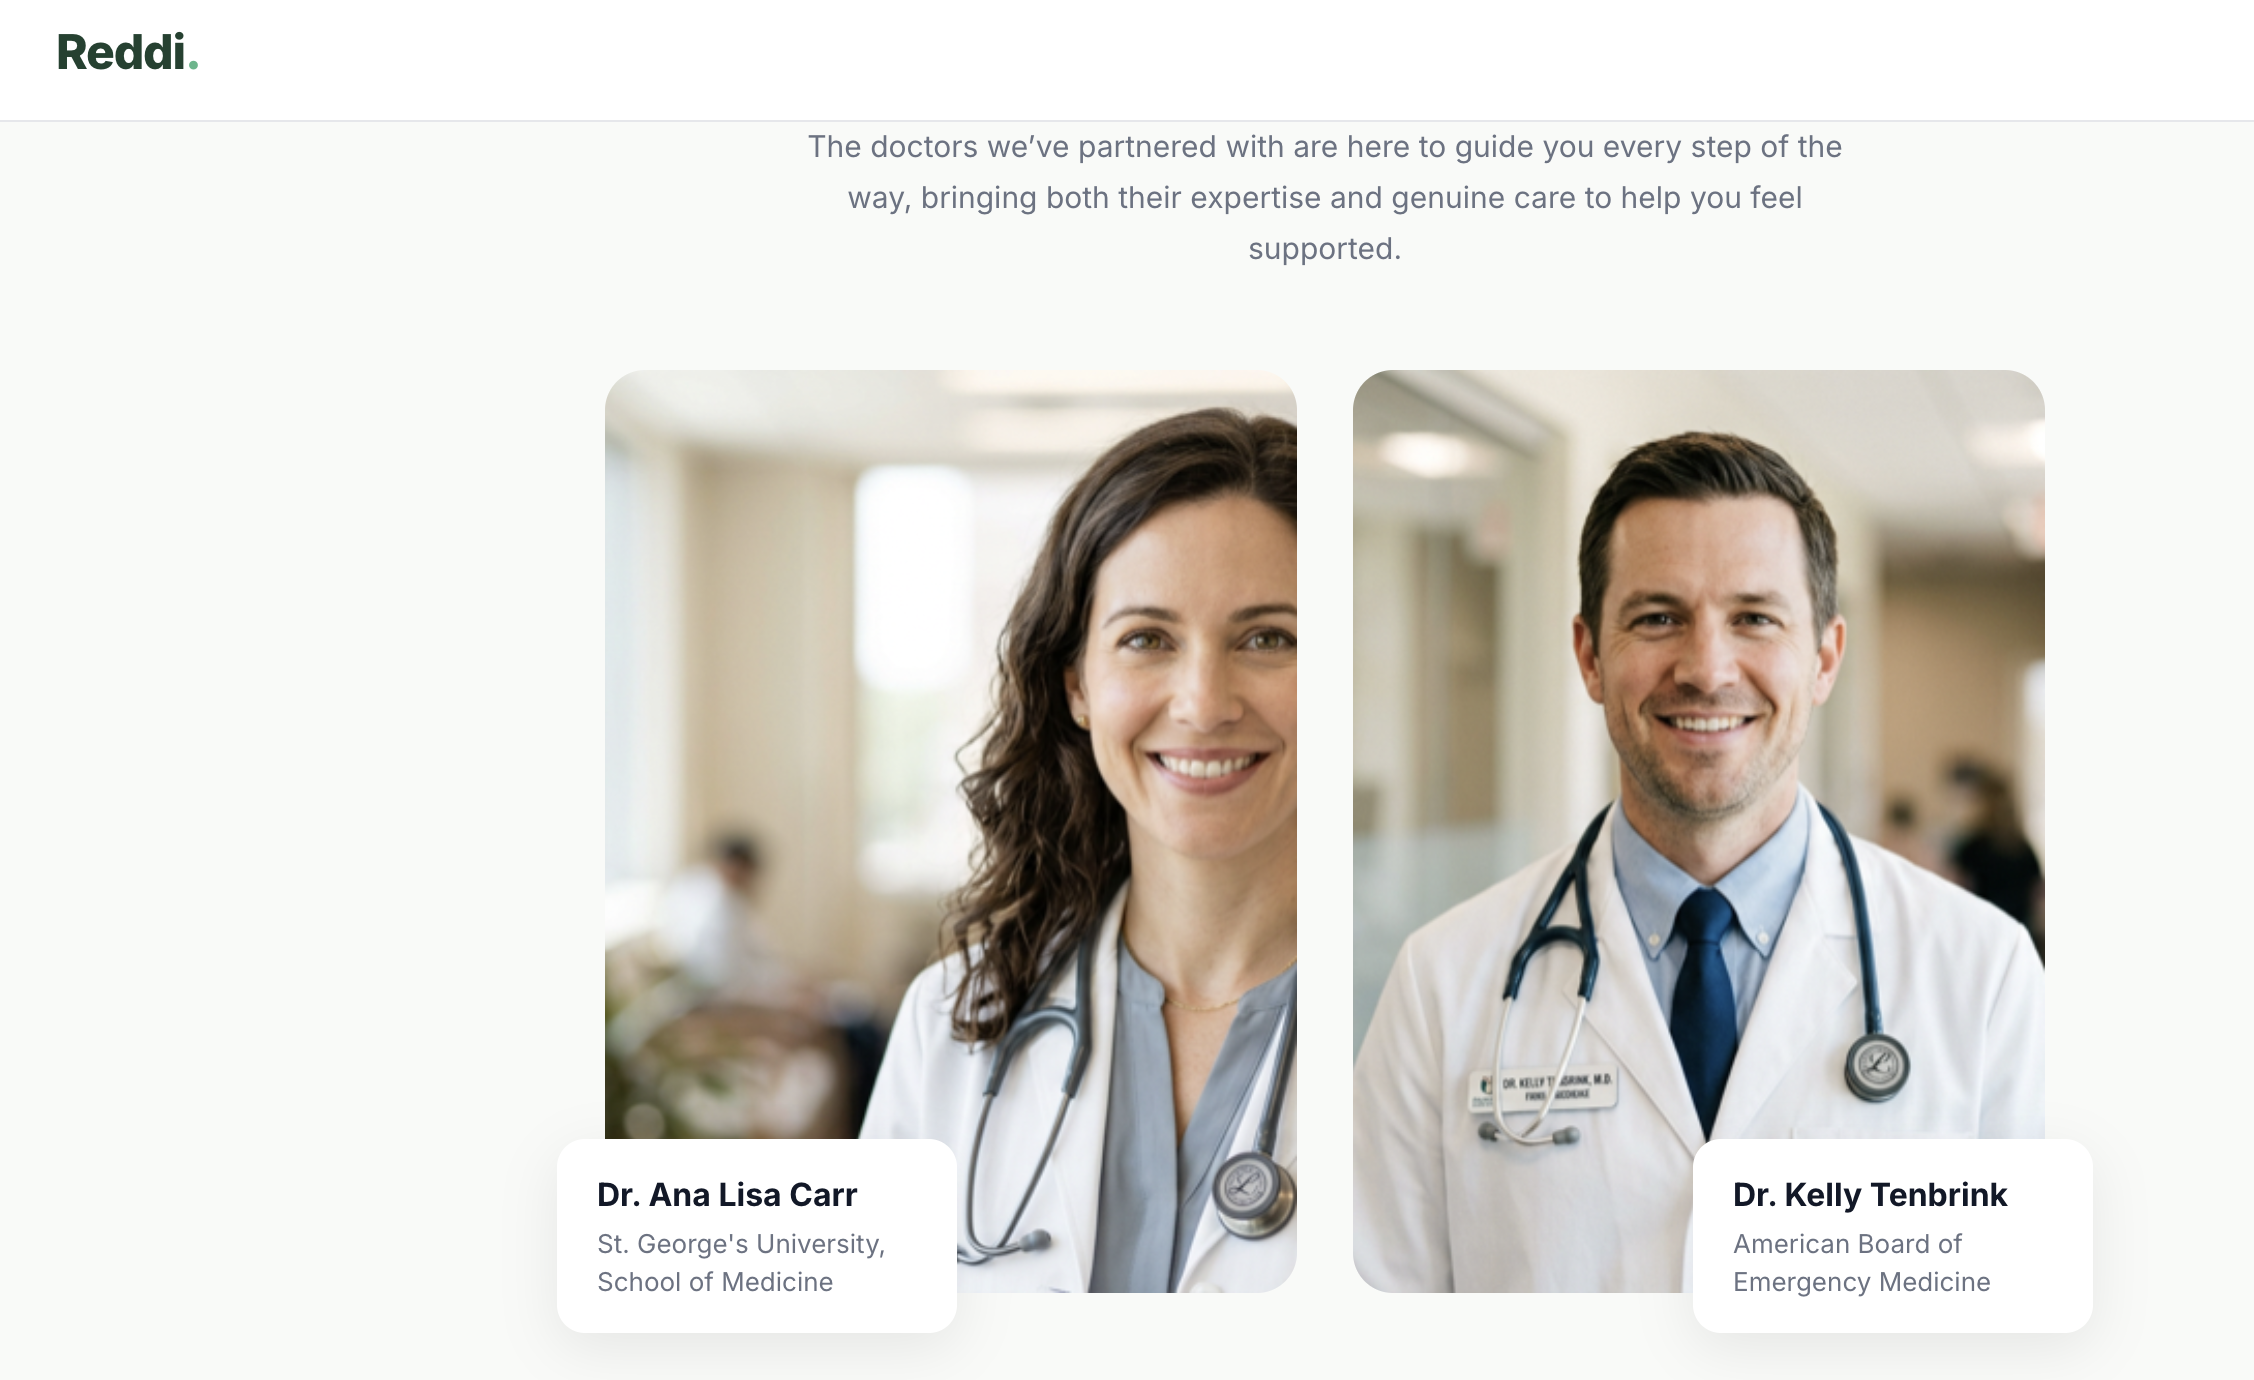
For instance, sites like VitalSlim, MDRxLabs, and AltRx have all featured the same group of physicians—Drs. David Mansour, Ana Lisa Carr, and Kelly Tenbrink—in their promotional materials. These platforms frequently cite the same medical-provider networks, such as OpenLoop Health and CareGLP-affiliated practices. This "white-label" approach to telehealth creates a veneer of legitimacy while making it difficult for patients to identify the actual source of their medication or the entity responsible for their clinical oversight.
In one notable case, an archived January 2026 version of medvi.io redirected users to medvi.org, with terms of service that tied the operation to MEDVi LLC, even as the company later claimed it had never received an FDA warning letter directed at its business, attempting to shift blame onto an "affiliate."
Supporting Data: The Safety Gap
The safety profile of these compounded drugs remains a central point of contention. The FDA explicitly cautions that its 1,700+ adverse event reports—990 for semaglutide and 730+ for tirzepatide—are likely significant undercounts. Because many state-licensed pharmacies are not required to report adverse events to federal databases, the true scope of patient harm remains hidden.
Furthermore, America’s Poison Centers have reported a staggering 1,500% increase in GLP-1 agonist exposure cases between 2019 and 2025, totaling nearly 23,000 incidents. While many involve accidental therapeutic errors with approved drugs, a significant subset involves 10-fold dosing errors linked to compounded products. These errors are often attributed to confusing syringe measurement units provided by compounding pharmacies, which lack the standardized, user-friendly delivery systems of FDA-approved pens.
Official Responses and Legal Pushback
The pharmaceutical giants behind these drugs, Novo Nordisk and Eli Lilly, have waged a comprehensive legal war against the compounding sector. Novo Nordisk has filed over 130 lawsuits across 40 states, securing dozens of permanent injunctions. Eli Lilly has taken similar steps, targeting both the pharmacies producing the drugs and the telehealth platforms distributing them.
Meanwhile, industry advocates are pushing back. The Outsourcing Facilities Association has sued the FDA, challenging the agency’s decision to remove tirzepatide and semaglutide from the shortage lists. They argue the FDA acted prematurely, depriving patients of necessary access. Similarly, the Alliance for Pharmacy Compounding and the National Community Pharmacists Association are actively lobbying against the SAFE Drugs Act, which would impose a strict 20-unit monthly limit on compounding drugs that are "essentially copies" of commercially available products.
Implications for Patients and the Future of Telehealth
The implications of this crisis extend far beyond the balance sheets of pharmaceutical companies. For the patient, the landscape is fraught with potential for financial and physical harm. Reports from consumers regarding "ghost" pharmacies—where the name on the label does not correspond to a legitimate facility—and predatory subscription models have become common.
In one documented instance, a consumer was charged $866 after attempting to verify the price of a consultation, highlighting a systemic lack of transparency in the DTC telehealth model. Additionally, a pending civil RICO complaint alleges that some companies are distributing "oral tirzepatide," a formulation that medical experts note has no proven efficacy or absorption, raising serious questions about the medical ethics of the providers involved.
Conclusion: A Looming Regulatory Reckoning
The "Wild West" era of compounded GLP-1s appears to be drawing to a close, though the transition is proving chaotic. As the FDA tightens its grip and the legal system filters through the complex webs of corporate ownership and liability, the focus is shifting toward patient safety. The surge in these medications, while born from a genuine medical need, has outpaced the regulatory frameworks designed to protect public health. Whether through the passage of the SAFE Drugs Act or continued aggressive litigation, the future of the compounded GLP-1 market will likely be defined by a significant contraction and a return to more stringent, transparent oversight.
For now, the thousands of patients caught in the middle must navigate a market where the line between convenient access and dangerous, unregulated medicine has never been thinner.
About the Author