The landscape of American public health is bracing for a profound transformation as the 2025 tax and budget reconciliation law prepares to reshape eligibility for federally funded health programs. Beginning October 1, 2026, millions of lawfully present immigrants face the potential loss of coverage under Medicaid and the Children’s Health Insurance Program (CHIP). This legislative shift, designed to curb federal spending, creates a complex administrative, logistical, and humanitarian challenge for states and healthcare providers nationwide.
Main Facts: A Shift in Eligibility
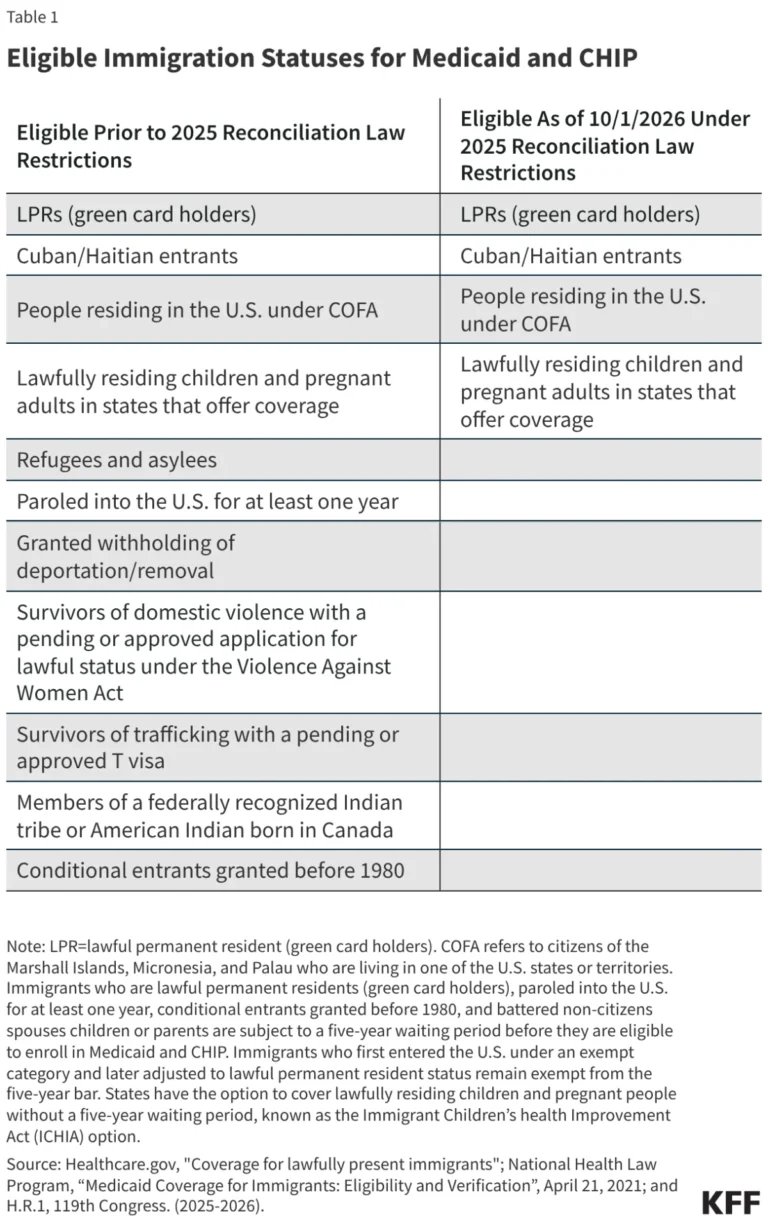
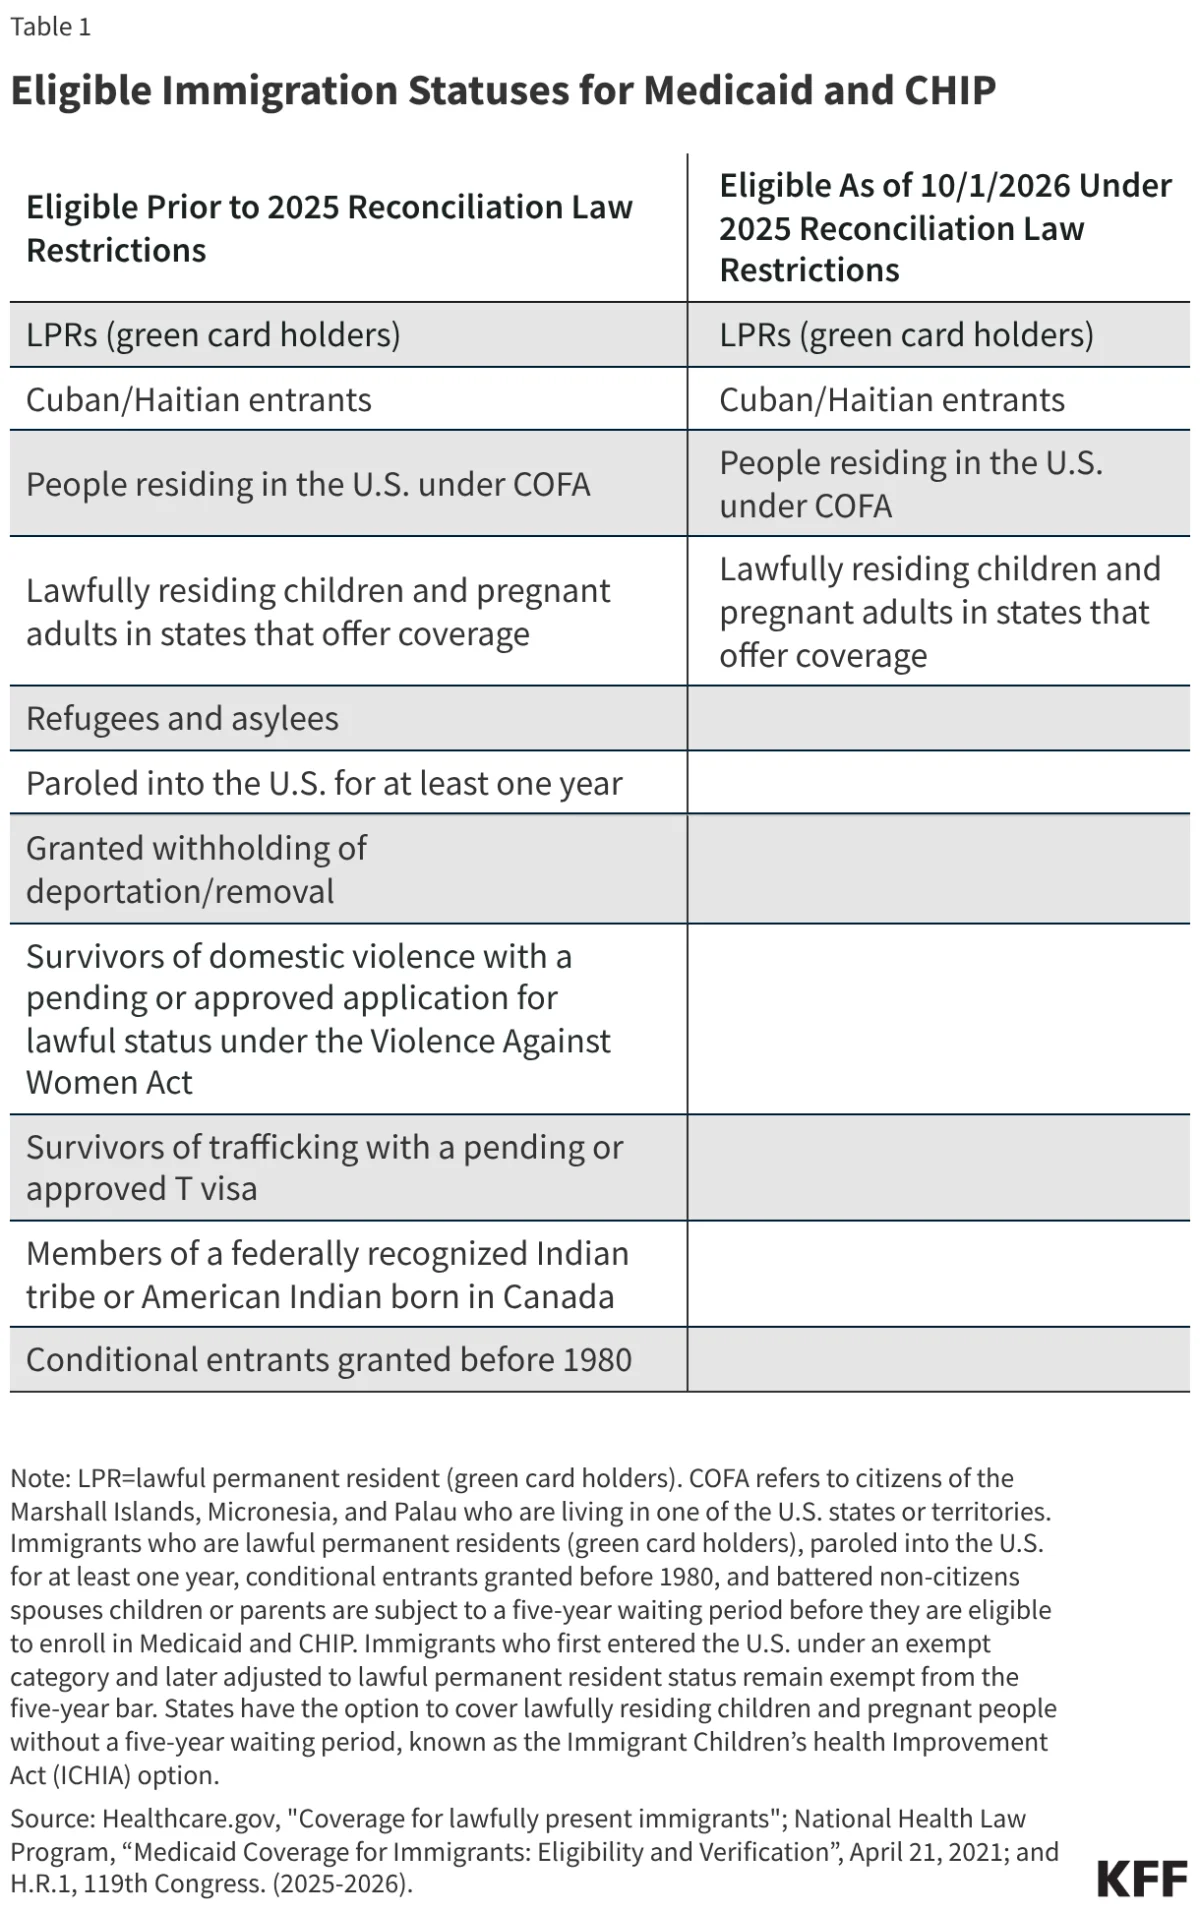
The 2025 reconciliation law marks a significant narrowing of access to essential health services for noncitizens. Under the new statutory framework, eligibility for Medicaid and CHIP will be restricted exclusively to specific cohorts:
- Lawful Permanent Residents (LPRs): Commonly known as "green card" holders.
- Cuban and Haitian Entrants: Recognized under specific humanitarian designations.
- COFA Migrants: Individuals residing in the U.S. under Compacts of Free Association.
- Targeted Coverage Groups: Children and pregnant individuals residing lawfully in states that have elected the Immigrant Children’s Health Improvement Act (ICHIA) option.
Crucially, the law terminates eligibility for broad categories of immigrants who previously qualified, including refugees and asylees who have not yet secured a green card. While the 1996 Personal Responsibility and Work Opportunity Reconciliation Act (PRWORA) already mandated a five-year waiting period for many "qualified" immigrants, the 2025 law layers on further restrictions, ensuring that even those who met previous criteria may now find themselves ineligible for federal support. Undocumented immigrants, who were already excluded from federal programs, remain ineligible under the new provisions.
Chronology of Implementation
The transition to these new rules is set to occur in stages, placing intense pressure on state Medicaid agencies to overhaul their enrollment systems within a truncated timeframe.
- September 2025: Initial guidance released by the Centers for Medicare & Medicaid Services (CMS) regarding managed care capitation adjustments.
- October 1, 2026 (The "Go-Live" Date): The effective date for new Medicaid and CHIP eligibility restrictions. States must have completed redeterminations for all "potentially affected" enrollees.
- December 31, 2026: The deadline for states to submit updated State Plan Amendments (SPAs) reflecting the new eligibility criteria.
- January 1, 2027: New eligibility restrictions extend to subsidized Affordable Care Act (ACA) Marketplace coverage, further limiting options for those displaced from Medicaid.
- 2034: The Congressional Budget Office (CBO) projects that the cumulative impact of these changes will result in 100,000 additional individuals becoming uninsured by this date.
Supporting Data: Fiscal and Human Costs
The rationale behind the law is primarily fiscal, with the CBO estimating that these eligibility restrictions will reduce federal Medicaid and CHIP spending by approximately $6.2 billion. However, the human cost of these savings is significant.
Analysts at KFF suggest that the administrative burden of these changes—often referred to as "procedural disenrollment"—could lead to coverage losses even among individuals who technically remain eligible. Because states vary in the documentation they retain, many eligible immigrants may be dropped from rolls simply because they cannot navigate the complex, time-sensitive requirements to verify their status under the new, more rigorous standards.
Furthermore, the "point-in-time" nature of the Department of Homeland Security’s Systematic Alien Verification for Entitlements (SAVE) system poses a systemic risk. SAVE often fails to reflect recent adjustments in immigration status, meaning individuals who have gained legal protections may be incorrectly flagged as ineligible, forcing them into a cycle of appeals and redetermination.
Official Responses and Administrative Hurdles
The Centers for Medicare & Medicaid Services (CMS) has issued an extensive implementation toolkit, acknowledging the difficulty states face in transitioning. CMS emphasizes that states must:

- Reverify Existing Enrollees: Before contacting individuals, states are required to attempt automated data matches using SSA and DHS databases.
- Provide Reasonable Opportunity: For those whose status cannot be verified automatically, states must grant a 90-day "reasonable opportunity period" during which coverage must remain active.
- System Updates: States must overhaul their enrollment and financial reporting systems to isolate costs for state-only funded programs, ensuring no federal matching funds are used for ineligible groups.
Despite this guidance, state officials have expressed frustration. The lack of final, detailed instructions for "dual-eligible" individuals—those receiving both Medicare and Medicaid—remains a major point of contention. Without clear federal direction, states are left to guess how to handle the intersection of these two complex systems, particularly for disabled individuals receiving Supplemental Security Income (SSI).
Implications: The Widening Coverage Gap
The implications of the 2025 law extend far beyond the immediate loss of insurance cards.
The Safety Net Strain
As federal coverage disappears, the burden will shift to the nation’s safety net. Community Health Centers (CHCs) are expected to see an influx of patients who have been disenrolled. While CHCs provide critical services on a sliding-fee scale, they lack the capacity to replace comprehensive Medicaid coverage, particularly for individuals requiring specialized, long-term care or chronic disease management.
The "Chilling Effect"
Beyond those who lose eligibility, experts fear a widespread "chilling effect." Heightened immigration enforcement, combined with recent CMS data-sharing agreements with Immigration and Customs Enforcement (ICE), has created an environment of fear. Even those who are legally eligible for coverage may choose to drop out of the system or avoid renewing their enrollment out of fear that their information could be used for immigration enforcement purposes. This "public charge" anxiety is likely to result in significant drops in enrollment among immigrant families, even in states that attempt to maintain robust coverage programs.
State-Level Divergence
The impact will not be uniform. States with the fiscal capacity may attempt to fill the void with state-funded programs. However, the current economic climate—characterized by slowing revenue growth and budget pressures—makes this difficult. Several states have already begun to scale back existing state-funded immigrant coverage due to higher-than-expected enrollment and rising costs. This creates a "postcode lottery" where an immigrant’s access to healthcare depends entirely on the state in which they reside.
Administrative Fragility
States are currently managing the implementation of this law alongside other major policy shifts, including new Medicaid work requirements and more frequent redeterminations for ACA expansion populations. The administrative overhead required to train caseworkers, update call center scripts, and redesign notification letters is immense. The readability of these notices—which currently range from fourth-grade to tenth-grade levels—remains a major barrier for non-native English speakers. Without clear, linguistically accessible, and timely communication, the risk of "administrative violence"—where eligible people are excluded due to bureaucratic complexity—is high.
Conclusion
The 2025 reconciliation law represents a fundamental shift in the social contract between the United States and its immigrant population. While the federal government seeks to achieve billions in savings, the downstream effects on public health, state budgets, and the stability of the healthcare safety net remain uncertain. As October 2026 approaches, the success or failure of this policy will likely be defined by the states’ ability to mitigate administrative chaos and the ability of community organizations to provide a bridge for those navigating a suddenly more exclusive healthcare landscape. The long-term consequence of these restrictions may well be a less healthy, more fragmented population, as the barrier between "eligible" and "ineligible" becomes an increasingly insurmountable wall for those in need of care.
About the Author