Editorial Note: This analysis, originally published on April 23, 2026, has been updated to provide a more precise view of HIV-exposed infant testing, shifting focus to the number of infants tested within their first year of life rather than diagnostic sample collection rates.
Introduction: A Program in Transition
Since the inception of the second Trump administration, the President’s Emergency Plan for AIDS Relief (PEPFAR)—a cornerstone of American soft power and global health diplomacy—has entered a period of profound uncertainty. Long heralded as one of the most successful humanitarian initiatives in U.S. history, credited with saving over 26 million lives, the program is currently navigating a fundamental restructuring. As part of a sweeping "America First Global Health Strategy," the administration has implemented significant operational shifts, moving away from disease-specific mandates toward an integrated, bilateral model.
For the first time since these disruptions began, a clearer, albeit limited, picture of the program’s performance has emerged. On April 17, 2026, the U.S. State Department released Fiscal Year (FY) 2025 fourth-quarter (Q4) data. While the release offers a window into the program’s status, it also highlights the administrative turbulence that has left a void in global health monitoring, with data from the first three quarters of FY 2025 remaining largely unavailable.

Chronology of the Shift
The transition within PEPFAR has not been a singular event but a systematic recalibration of U.S. foreign aid. The timeline of these changes reflects the administration’s stated goal of prioritizing domestic interests and streamlining foreign commitments:
- Early 2025: Following the inauguration, the administration initiated a broad foreign aid review. Almost immediately, the PEPFAR data platform—a critical tool for transparency and accountability—was taken offline.
- Mid-2025: The State Department issued a "stop-work order," effectively freezing numerous active awards. This was followed by a series of limited waivers that dictated which services could continue and which were to be terminated.
- Late 2025: The formal announcement of the "America First Global Health Strategy" signaled a shift from vertical, disease-specific programming to a horizontal, integrated approach. Bilateral agreements became the new anchor for all U.S.-funded health interventions.
- April 2026: The release of Q4 FY 2025 MER data provides the first empirical look at how these policies have translated into on-the-ground outcomes.
The lack of data for quarters 1–3 of FY 2025 remains a significant hurdle for analysts. The State Department has attributed this gap to implementation challenges and the logistical strain of reconfiguring reporting systems to align with the new, integrated strategy.
Supporting Data: A Mixed Performance
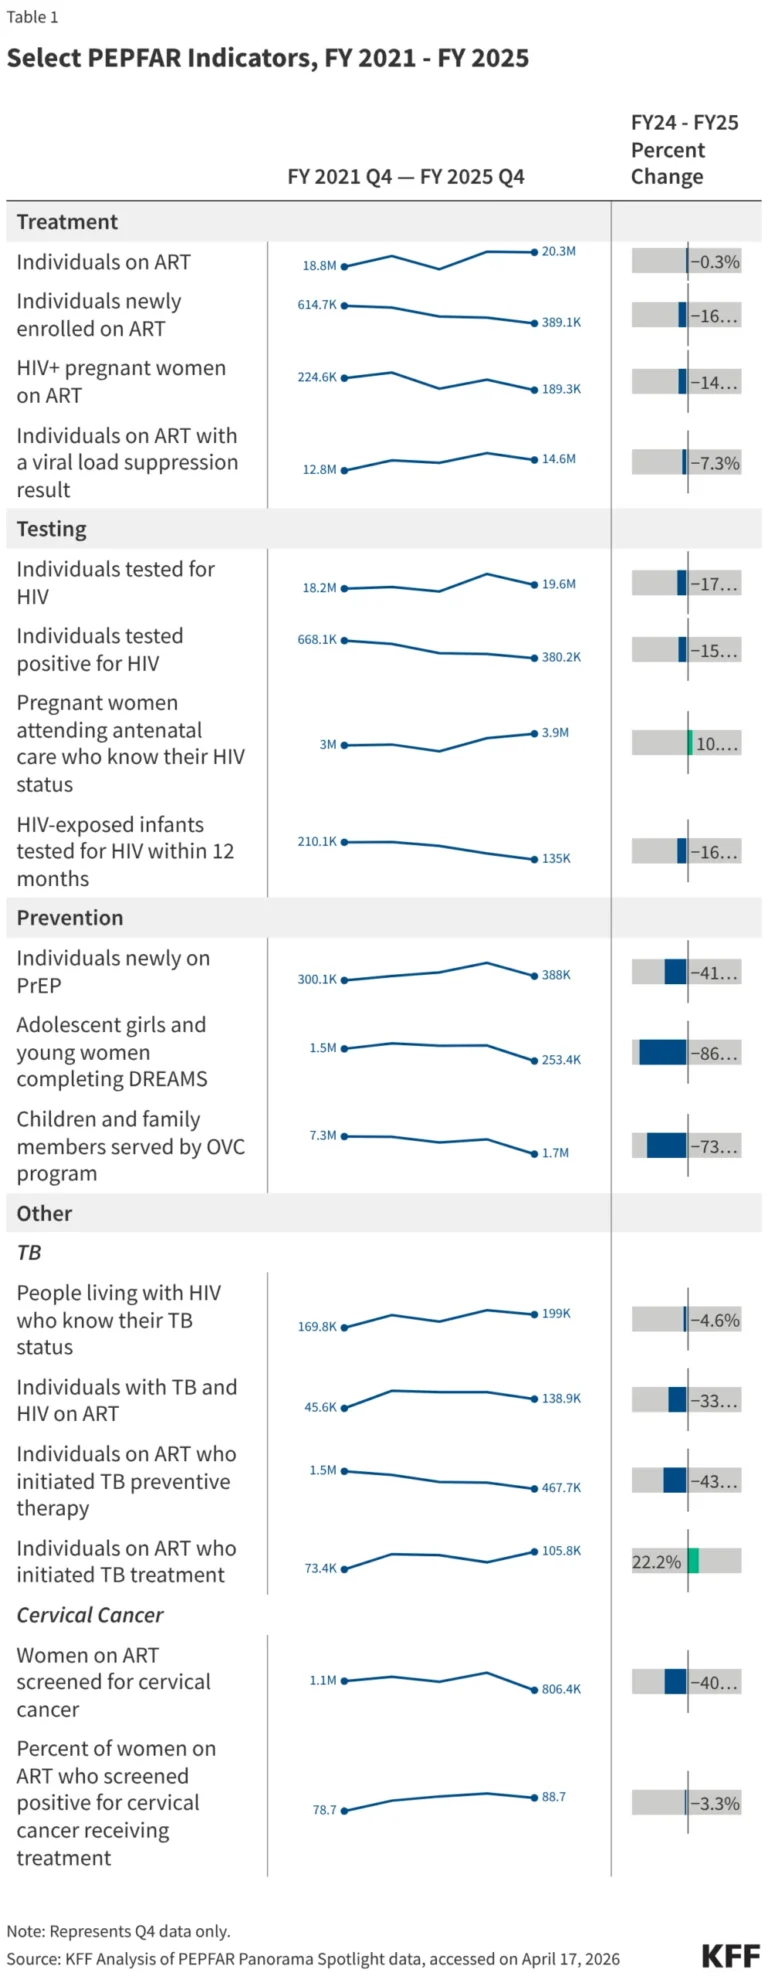
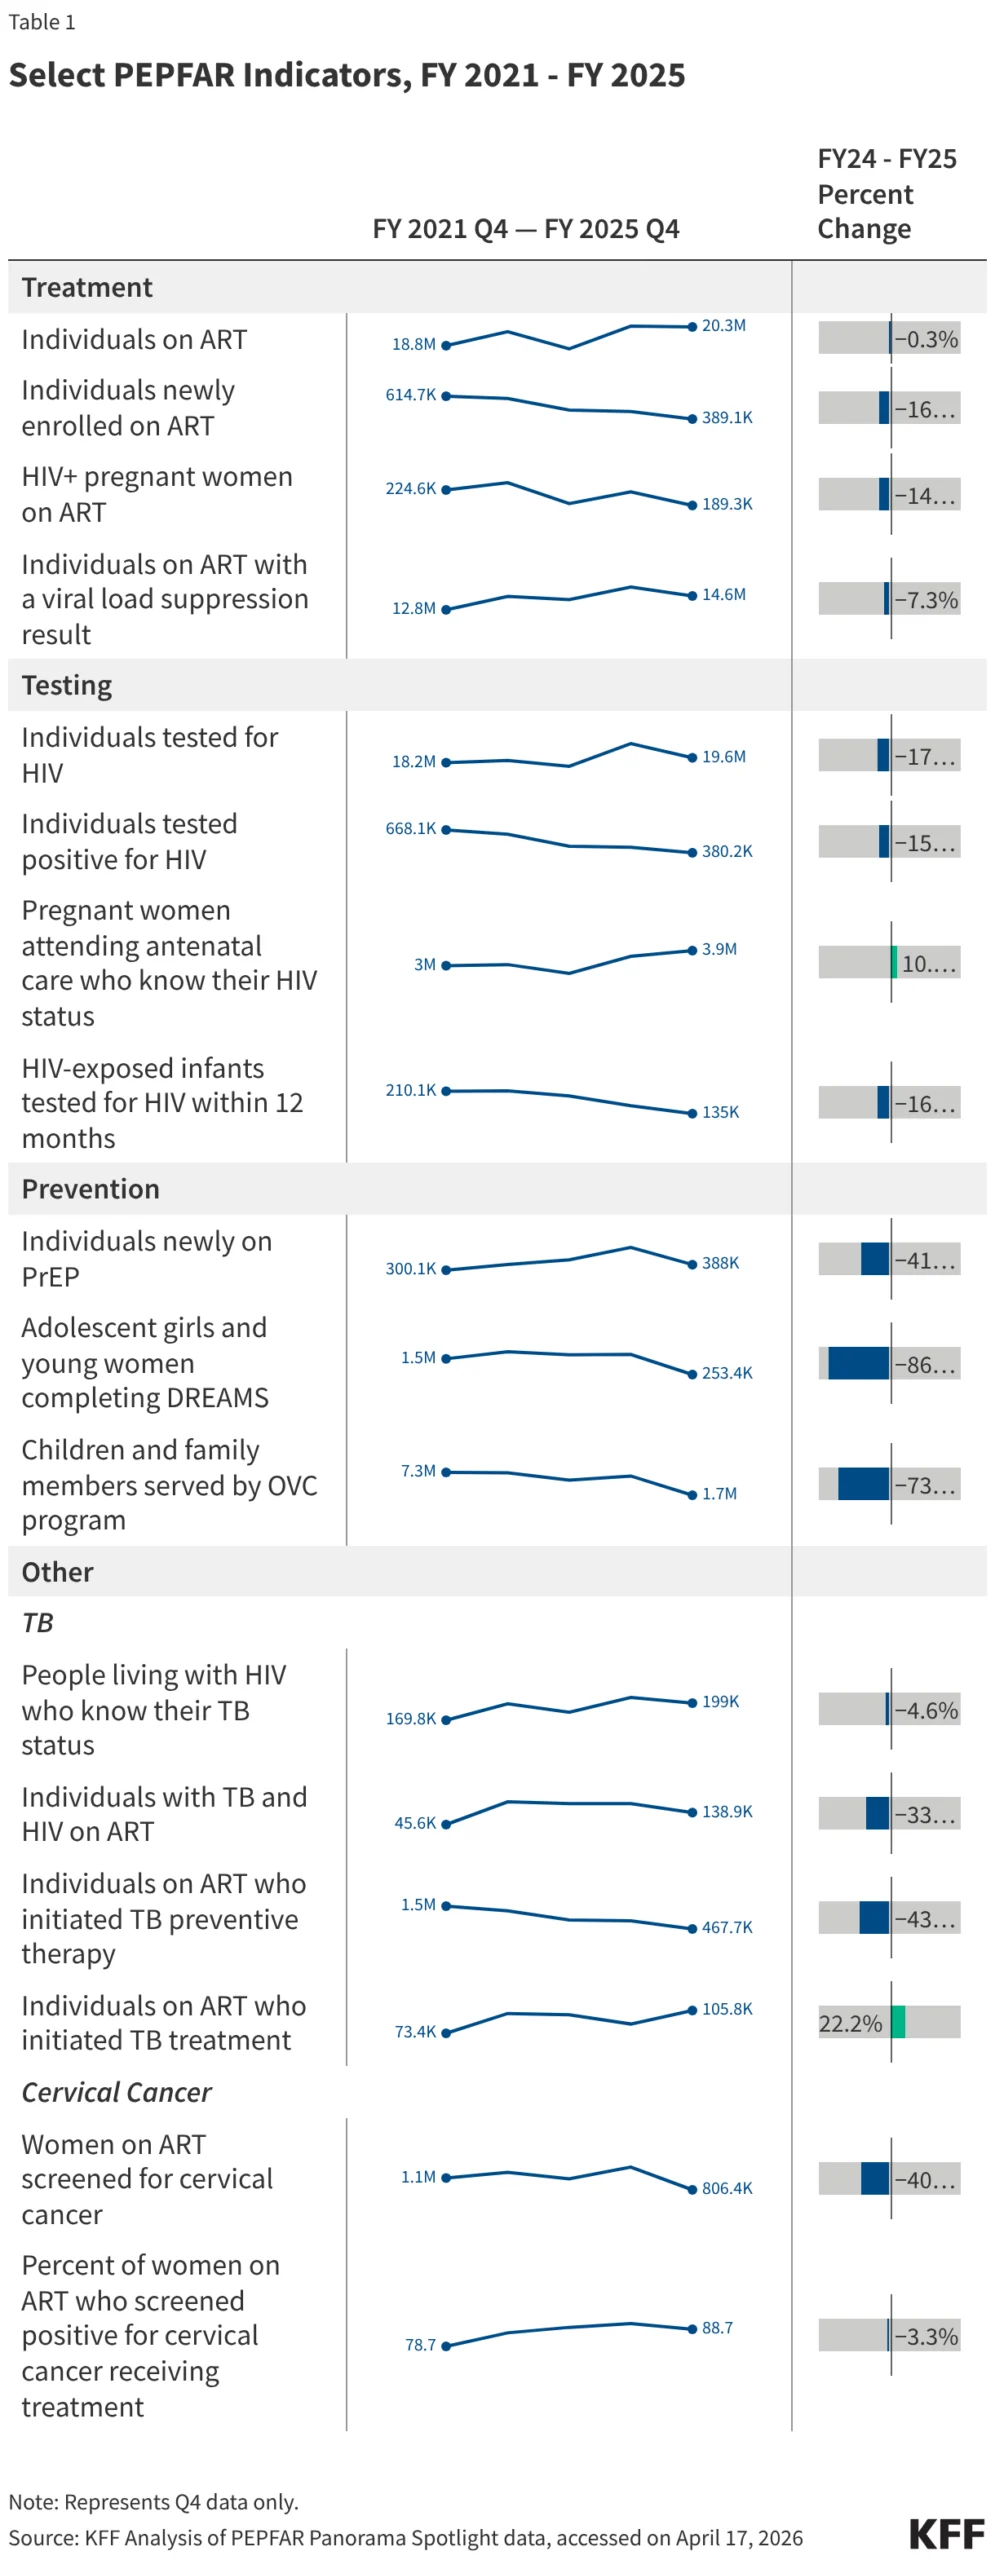
The Q4 FY 2025 results present a complex landscape. To analyze performance, KFF and Boston University researchers compared the Q4 data against the same period over the previous four fiscal years. This longitudinal approach helps account for seasonal reporting fluctuations, though it fails to capture the cumulative impact of disruptions across the full 2025 fiscal year.
Treatment and Care
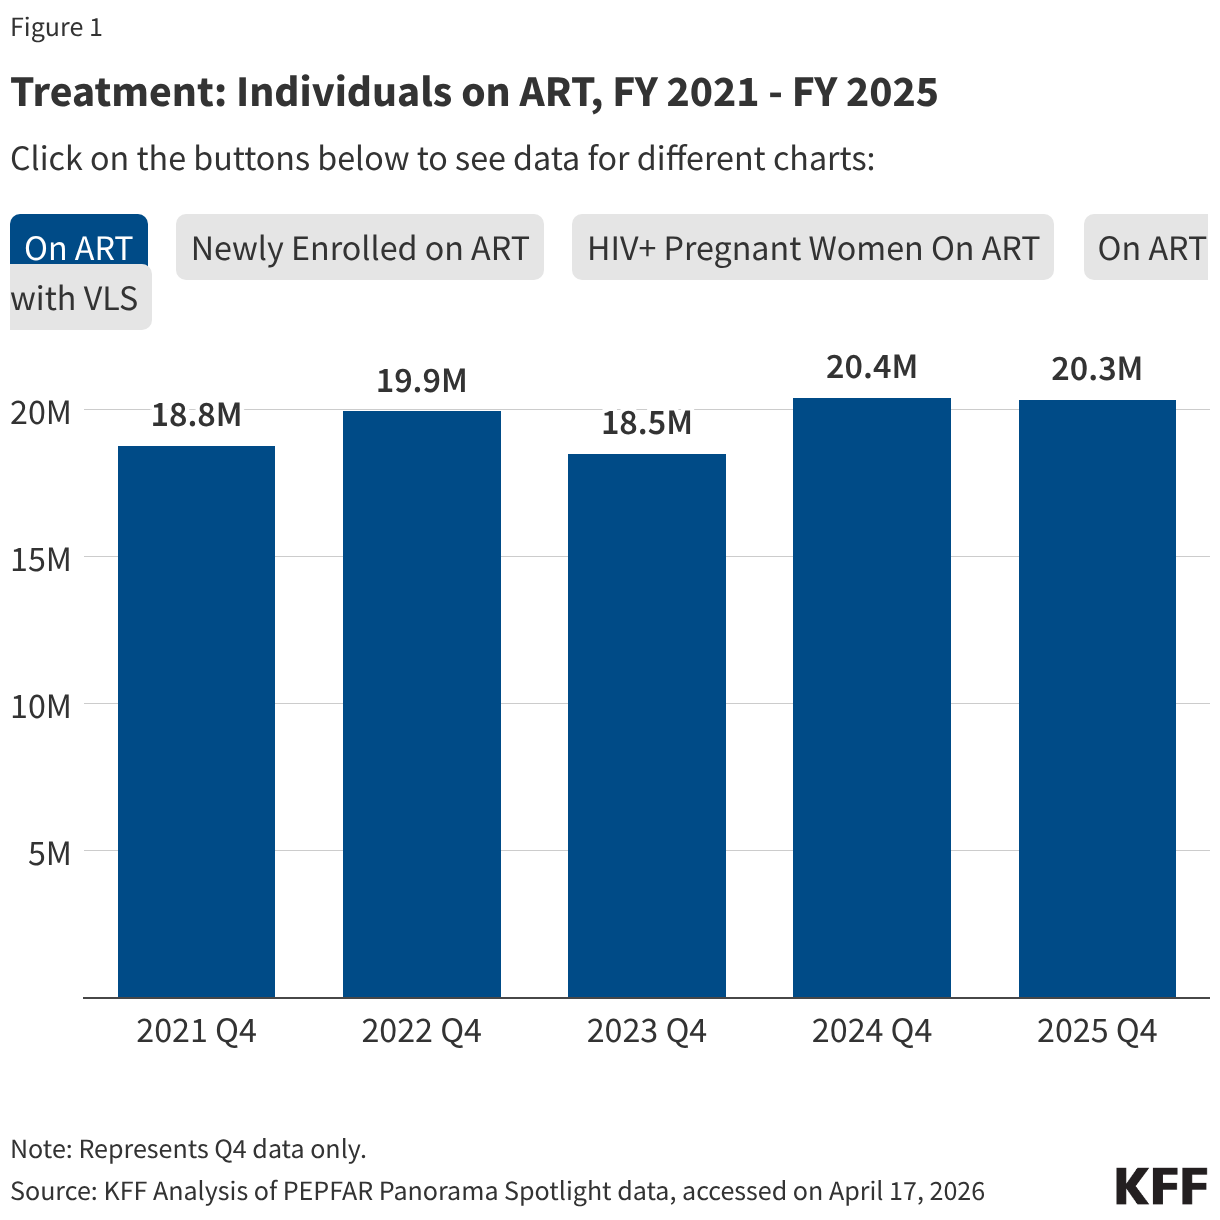
Treatment results remain the most stable aspect of the program, though cracks are beginning to appear. The total number of individuals receiving antiretroviral therapy (ART) has remained relatively consistent. However, the number of newly enrolled patients on ART has seen a noticeable decline. This suggests that while the program is maintaining existing patients, the "front door" of the system—the ability to identify and initiate new patients into care—is facing increased friction.
HIV Testing and Diagnostics
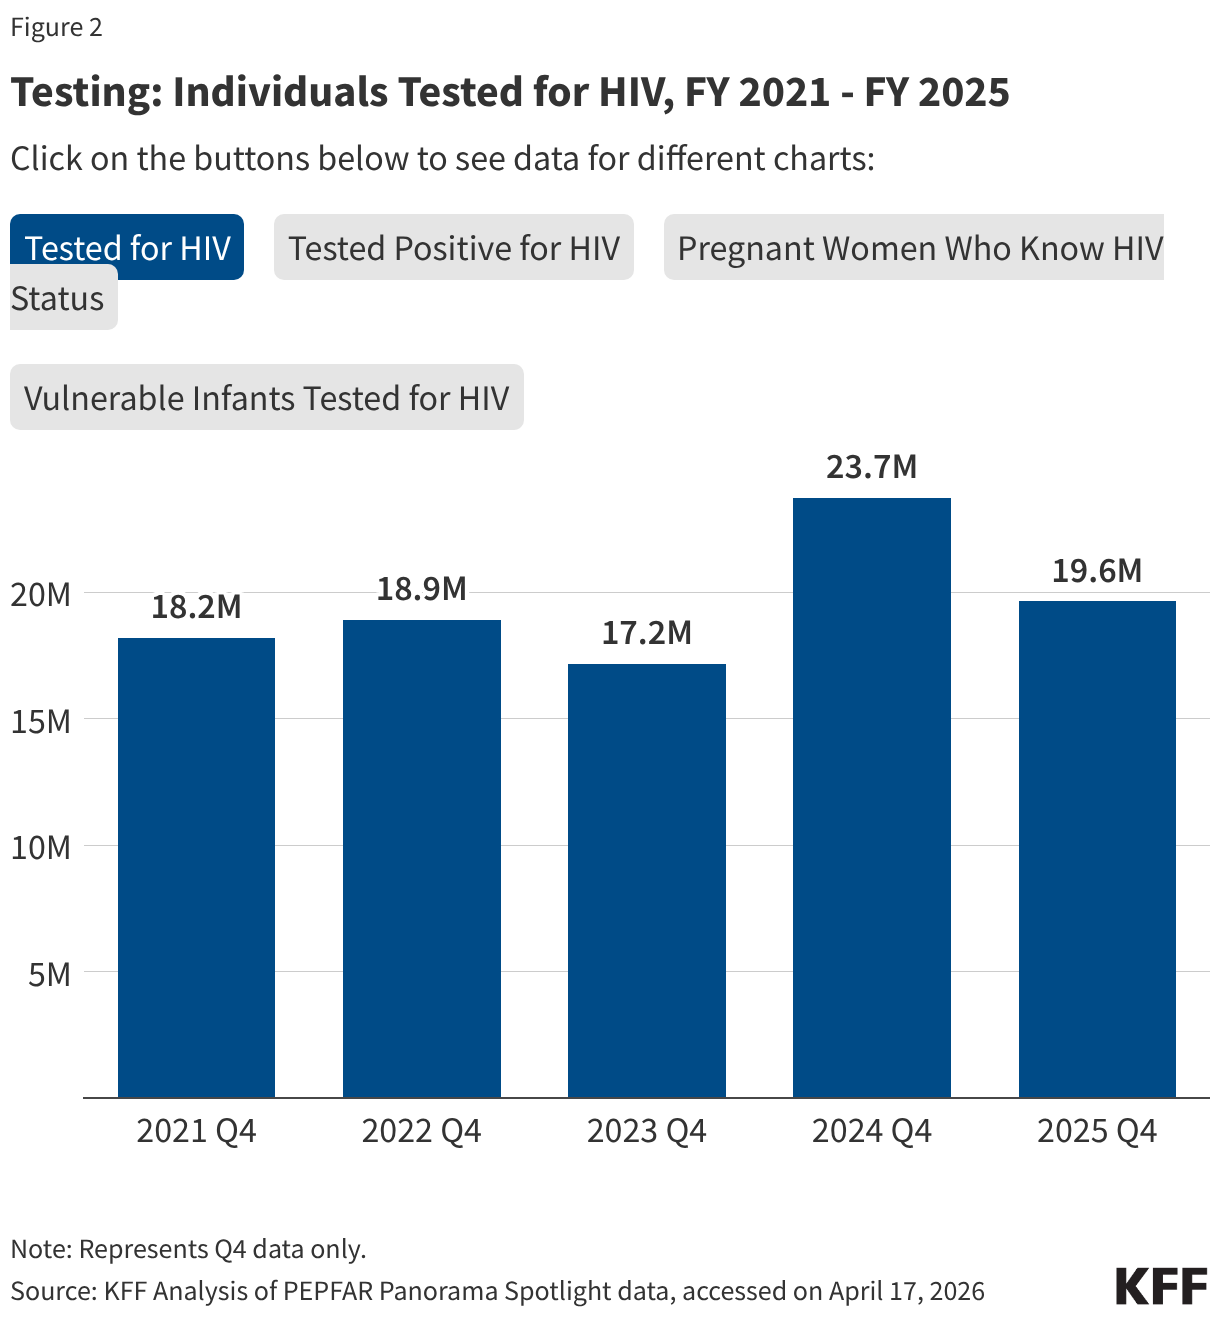
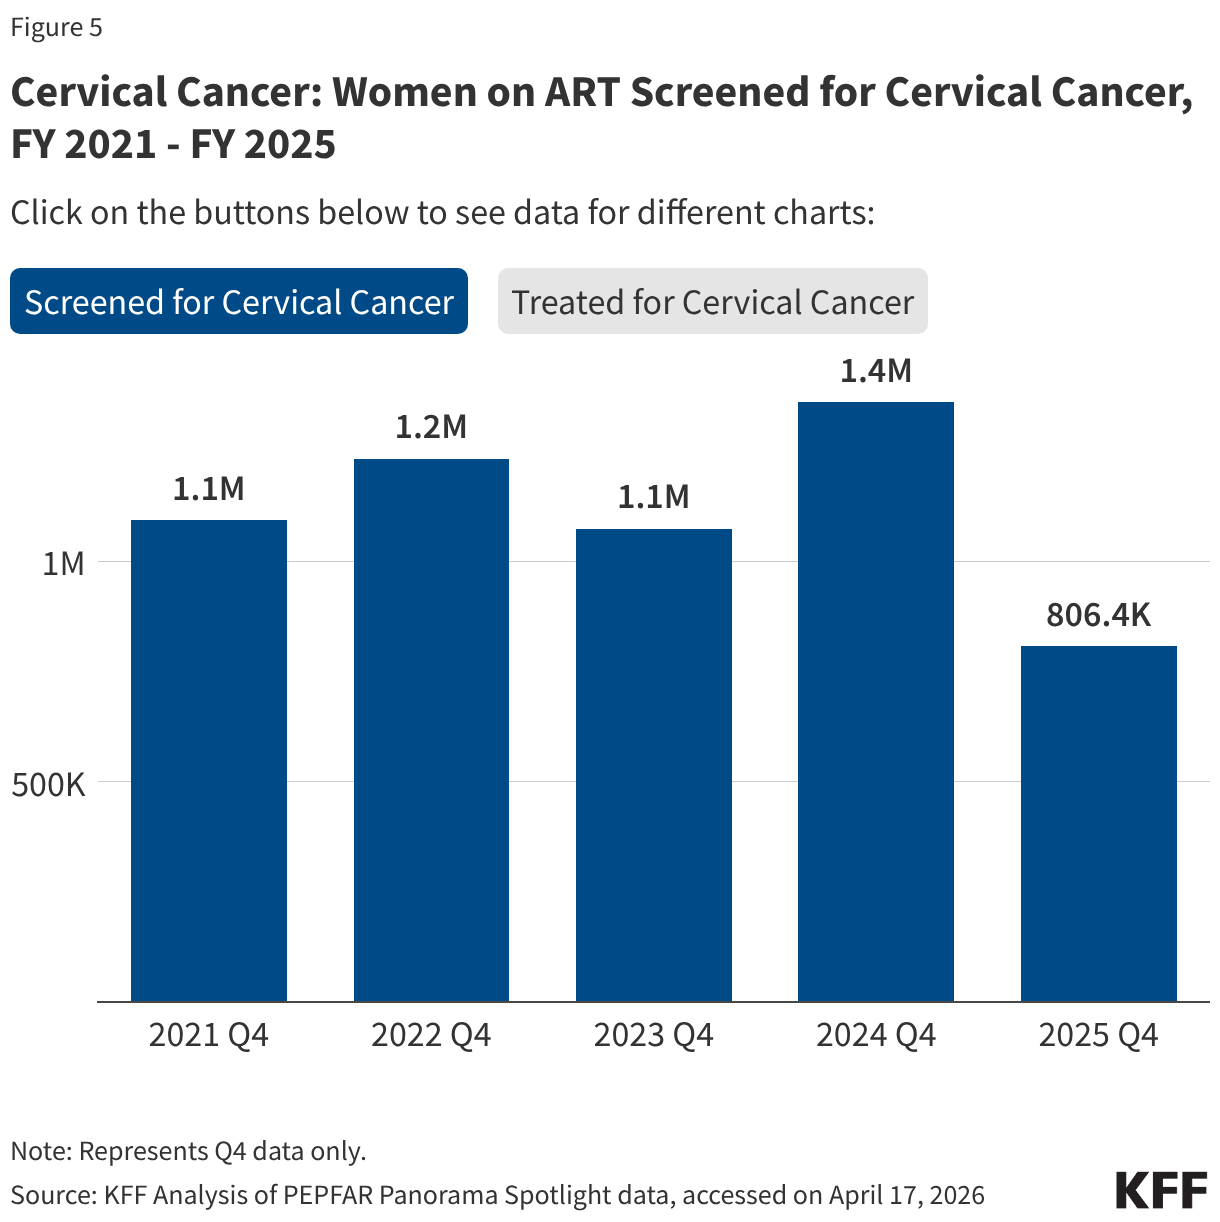
Testing figures show a worrying downward trend. Both the total number of HIV tests conducted and the number of individuals who tested positive have fallen compared to previous years. The ambiguity here is critical: Does this represent a reduction in the incidence of new infections, or does it signal a systemic failure to reach those in need of testing? Without robust surveillance, public health experts fear the latter, warning that unaddressed testing gaps could lead to a resurgence in transmission rates.
Prevention and Vulnerable Populations
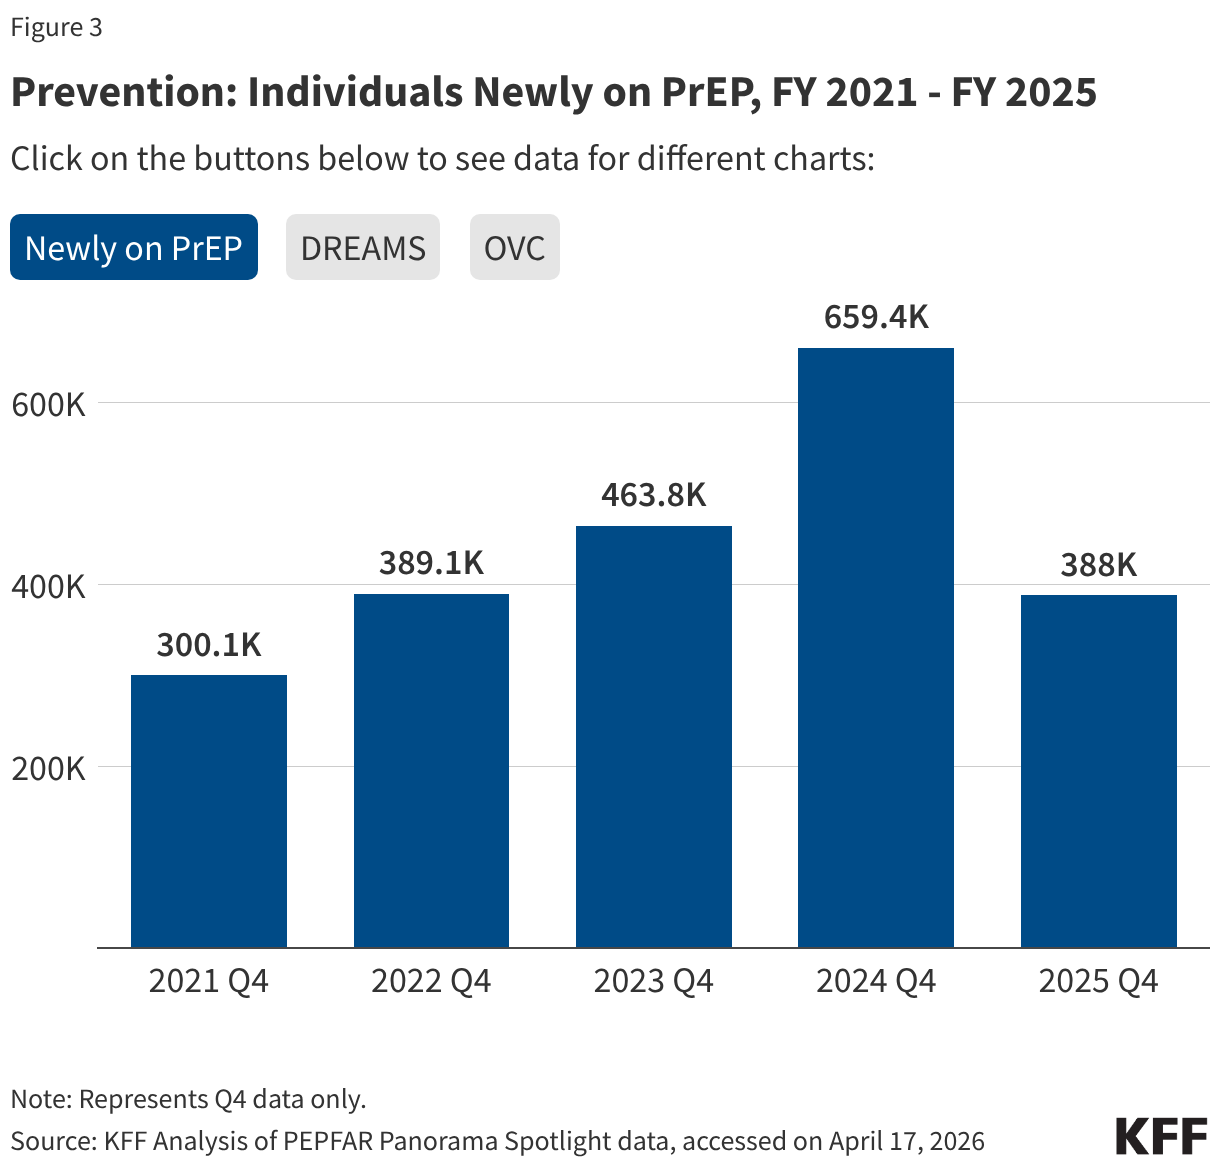
The most dramatic declines were observed in prevention services. The DREAMS program, which focuses on reducing HIV risk among adolescent girls and young women, and access to pre-exposure prophylaxis (PrEP), were significantly scaled back. These programs represent the proactive element of the PEPFAR strategy. By shifting resources away from these preventative measures, the administration is effectively choosing to manage existing disease rather than curb future infection.
TB and Co-infection
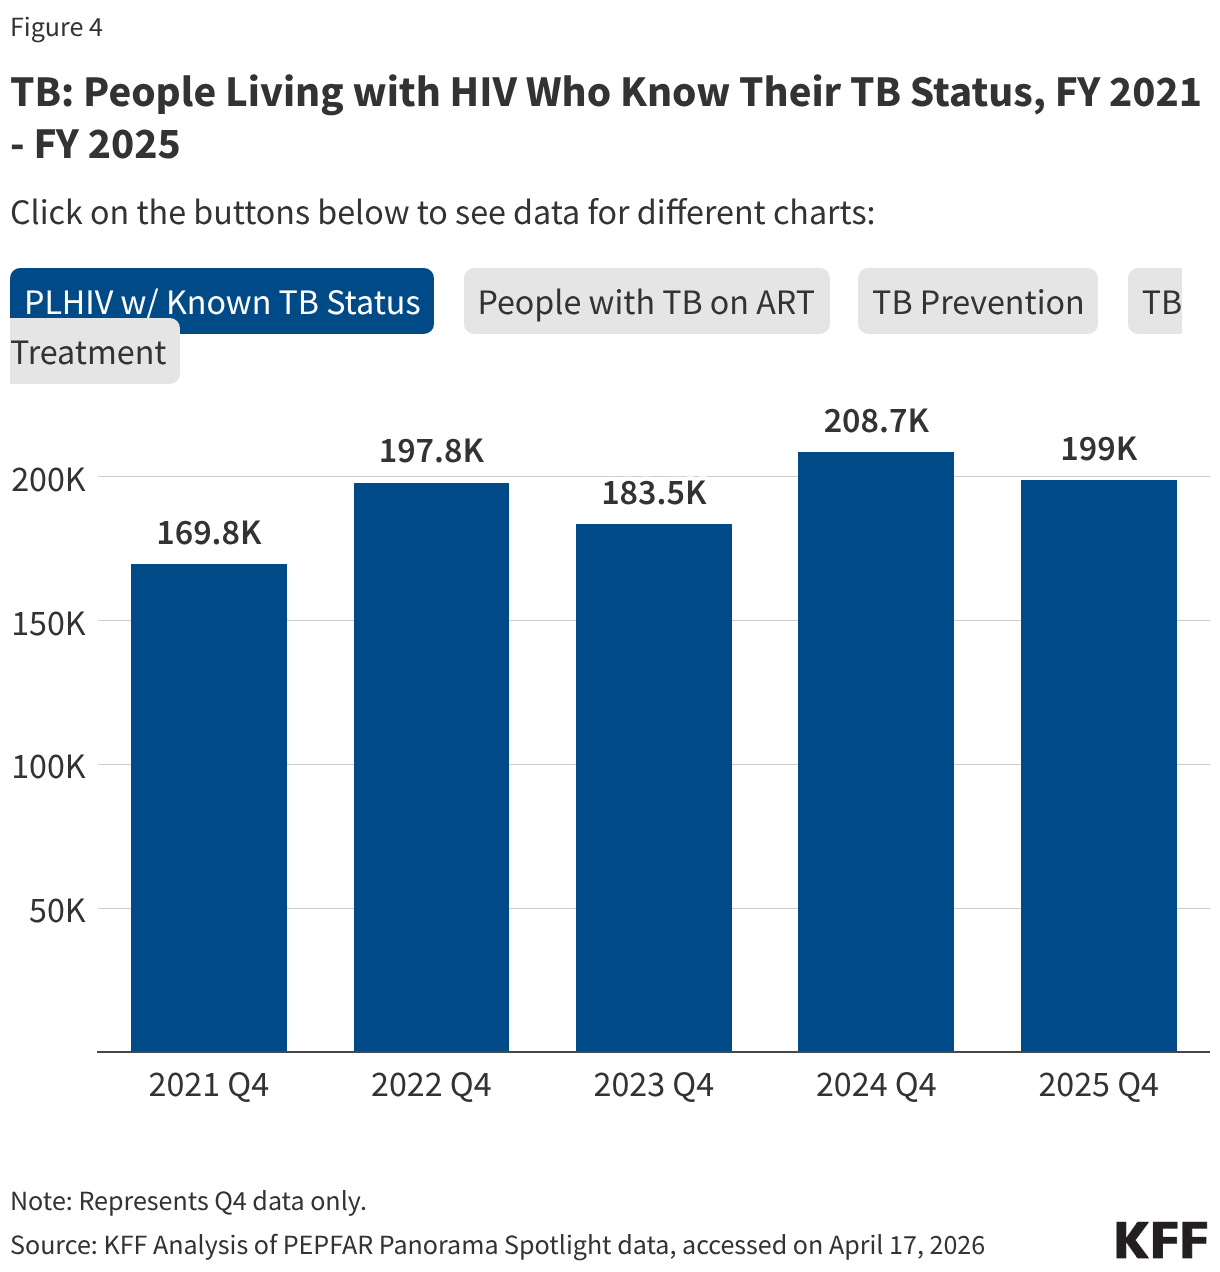
Support for HIV/TB co-infection remains a bright spot in some metrics, with an increase in the number of people living with both conditions who are receiving concurrent treatment. However, the data across other TB indicators remains inconsistent, suggesting that while specific clinical interventions are holding, the broader integration of services is still finding its footing.
Official Responses and Strategy
The State Department has defended these shifts as necessary optimizations. By pivoting to an "America First" model, officials argue they are reducing bureaucratic redundancy and ensuring that host country governments take greater ownership of their health sectors.
"We are moving toward a more sustainable model where health security is embedded within the broader national development goals of our partner countries," a department spokesperson noted during the data release.
However, critics argue that "sustainability" is a euphemism for divestment. The shift to an integrated approach, while theoretically sound, risks diluting the focused expertise that allowed PEPFAR to achieve such high impact over the last two decades. By forcing HIV programs to compete with or be absorbed by general health initiatives, the specific needs of key populations—those most at risk of HIV—may be deprioritized in favor of more generalized, and potentially less effective, primary care initiatives.
Implications: The Uncertainty of Transparency
The most troubling implication of the current situation is not just the decline in specific health metrics, but the erosion of the data-driven culture that defined PEPFAR’s success. For years, the Monitoring, Evaluation, and Reporting (MER) system provided a granular, real-time view of what worked and what didn’t.
With the current data platform lacking FY 2025 program-level data and the future of consistent reporting left in doubt, the global health community is effectively flying blind. The move from "required" to "optional" reporting for several key indicators further complicates the analysis. In many cases, it is now impossible to discern whether a decline in services is due to policy-driven cuts or simply a result of partners no longer being required to track and report those specific metrics.
The Risk of Data Silos
If the trend toward integrated, bilateral agreements continues, the centralized oversight that allowed the U.S. to hold partners accountable will likely diminish. Without standardized reporting, it will be impossible to measure the success of the new strategy. The global health community faces a critical juncture: either the administration must recommit to transparent, public-facing data, or the program will drift toward a model where success is measured by rhetoric rather than outcomes.
A Call for Accountability
As we look toward FY 2026 and beyond, the implications are clear. The gains made in the fight against HIV/AIDS are fragile. The transition to a new global health strategy is an opportunity to improve efficiency, but it must not come at the cost of the rigorous, data-informed standards that made PEPFAR the gold standard of global health.
If the goal is truly to empower local governments and improve health outcomes, transparency is not an optional add-on; it is the fundamental mechanism by which progress is verified. The current lack of visibility into the impact of the "America First" policy creates a vacuum that is increasingly being filled by anxiety among health workers, patients, and international donors.
Without a renewed commitment to open, consistent, and comprehensive data, the world risks losing the ability to track the pulse of the global HIV epidemic. The progress achieved by PEPFAR over the last 20 years was not accidental—it was the result of focused, data-driven, and relentlessly transparent interventions. Losing those pillars could unravel decades of progress, leaving the world less prepared to confront one of the most enduring health challenges of our time.
Conclusion
The data released in April 2026 provides a sobering baseline. We are seeing a program that is struggling to balance its legacy of success with a new, restrictive mandate. While some services remain stable, the indicators related to prevention and new patient enrollment are flashing red. The future of PEPFAR hinges on whether the administration can reconcile its "America First" objectives with the global necessity of ending the HIV epidemic—a goal that requires not just bilateral agreements, but also the clarity, courage, and transparency that have defined the program since its inception.
About the Author