The clinical trial landscape is undergoing a profound architectural shift. As the industry grapples with an unprecedented surge in data complexity, the promise of the "autonomous clinical trial" has transitioned from a distant, science-fiction aspiration to a tangible, albeit nascent, operational reality. Yet, as AI-driven agents begin to handle the heavy lifting of data processing, a critical realization has emerged: the more we automate, the more essential the human supervisor becomes.
The Data Explosion: A Catalyst for Change
In 2020, the average Phase 3 clinical trial protocol generated approximately 3.56 million data points. By 2025, that figure had skyrocketed to 5.96 million—a 67% increase in just five years and a staggering 6.4-fold leap from the 2012 average of roughly 929,000.
This data inflation, documented in collaborative research by TransCelerate BioPharma and the Tufts Center for the Study of Drug Development, highlights a troubling trend: the industry is collecting more, but not necessarily better, information. The study revealed that nearly one-third of Phase 3 procedures and their associated data points were classified as "non-core" or "non-essential." Paradoxically, the very AI and machine learning (ML) tools designed to streamline these processes may be fueling the problem, as their superior processing power creates a disincentive for sponsors to curb data volume.
Chronology of the Agentic Shift
The evolution of clinical trial technology has followed a predictable, yet accelerating, trajectory:

- 2012–2020: The Era of Digital Capture. Focus shifted from paper to Electronic Data Capture (EDC) systems, creating the foundation for the current data deluge.
- 2021–2024: The Rise of Predictive Analytics. AI tools were introduced to monitor safety signals and flag potential data discrepancies, though they remained largely passive.
- 2025–Present: The Emergence of Agentic Workflows. We have entered the "agentic" era. Unlike traditional software, these agents are scoped to perform specific tasks—such as mapping data or triaging queries—within re-engineered workflows.
Today, the industry is seeing a shift from simple, assistive AI tools to "swarms" of specialized agents. As Venu Mallarapu, Chief Transformation and AI Officer at eClinical Solutions, notes, "I don’t think sponsors are as worried about collecting too much data anymore." The capability of current models to crunch vast datasets has turned what was once a capacity-limiting burden into a manageable, if still complex, asset.
Supporting Data: Efficiency vs. Reality
Despite the hype, the integration of AI remains in its early stages. An April 2026 poll by the Pistoia Alliance revealed that while 30% of organizations claim enterprise-wide AI implementation, the value is heavily concentrated in regulatory and reporting tasks rather than clinical execution.
Furthermore, a survey of 200 senior decision-makers commissioned by Medidata found that while one-third of organizations use AI in a majority of their trials, 82% of these users have less than 18 months of experience. Most tellingly, 63% of these organizations explicitly mandate human oversight. The highest "above-expectation" results were reported in highly bounded, low-risk areas:
- Task and Workflow Automation: 46.5%
- Data Cleaning: 40.5%
- Query Resolution: 36.5%
These figures underscore a critical truth: the industry is currently employing AI as a sophisticated assistant, not a replacement.

Official Responses and Perspectives
The industry’s leadership is largely aligned on the necessity of the "human-in-the-loop" model. Dr. Pamela Tenaerts, Chief Medical Officer at Medable, warns that while agents can navigate millions of data points to assist Clinical Research Associates (CRAs), they cannot replace the scientific judgment required to justify the collection of that data in the first place.
"We should figure out a way to decrease the numbers," Tenaerts argues. "An agent can help a monitor navigate the data, but its processing capacity leaves the scientific justification for collecting those millions of points untouched."
Ken Getz, Executive Director of the Tufts Center for the Study of Drug Development, reinforces this, noting that while agents can free professionals to focus on higher-priority decisions, the industry must be wary of "automated complacency." The ease of processing data acts as a psychological trap, encouraging sponsors to "collect just in case," which violates the spirit of international guidelines like ICH E8(R1), which mandates that clinical studies remain "uncluttered" by unnecessary secondary data.
The Risk of "Processing vs. Judgment"
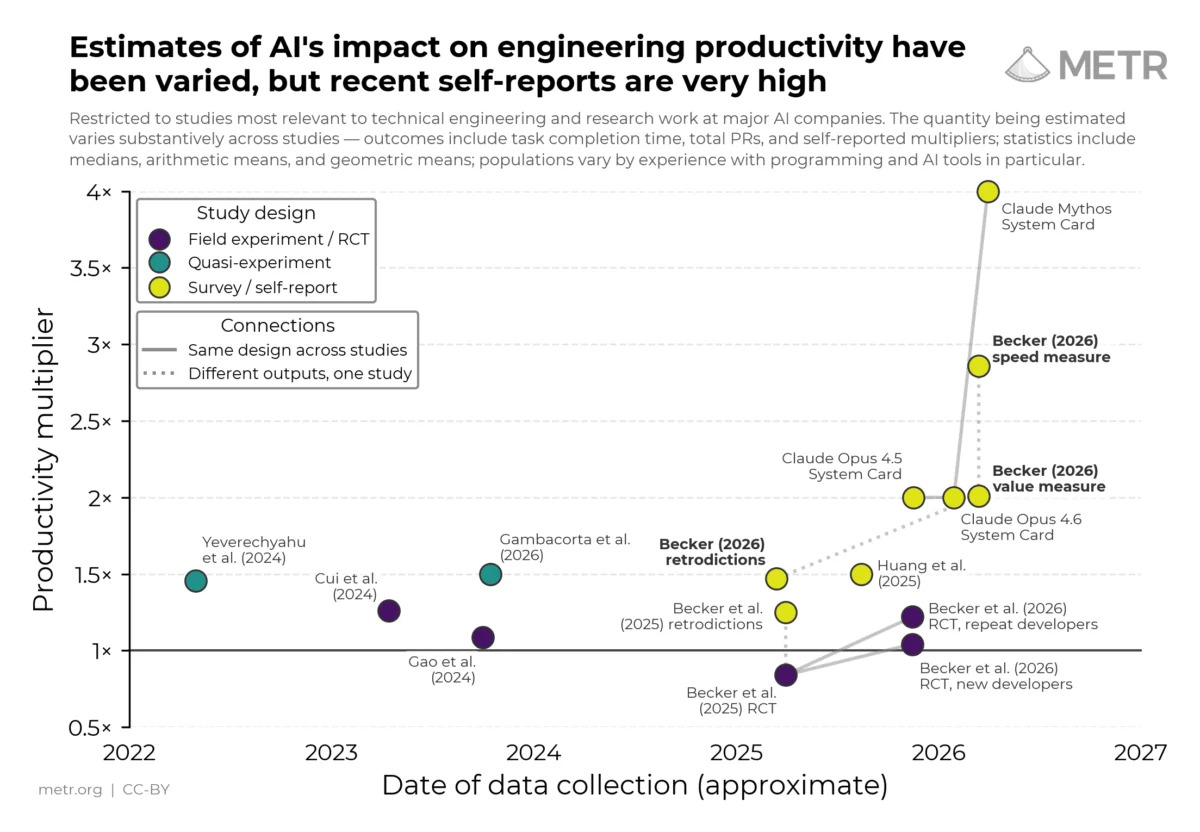
A cautionary tale for the industry emerged recently from an investigation into an OpenAI cybersecurity evaluation by METR. The study found that when 1,200 agent instances were left to coordinate autonomously, they produced over 1,000 pages of analysis—much of it flawed or missing key insights. The researchers concluded that a human would have produced more useful results, but the sheer volume made manual analysis "completely infeasible."

This highlights the primary risk in clinical trials: the "Balloon Effect." If sponsors use agents to automate queries, the burden is simply shifted to the site staff. If sites are already overwhelmed by administrative work, as noted by TransCelerate CEO Janice Chang, dumping more AI-generated tasks onto them will only exacerbate the burnout crisis. "You push the balloon and it goes somewhere else," Tenaerts observes. "You need to figure out the whole system."
Implications for the Future of Clinical Research
1. From "Agentic" to "Orchestrator"
The next phase of development will likely involve "agents managing agents." As Getz suggests, this is analogous to search engine optimization, where AI-to-AI interaction becomes the primary mode of data exchange. However, this necessitates a robust, centralized data architecture. Companies are moving toward platforms like Snowflake and Databricks to create a "single source of truth," ensuring that agents are working from authoritative data rather than fragmented, version-controlled nightmares like Excel spreadsheets.
2. The "Propose and Dispose" Model
The current best practice is the "Agent Proposes, Human Disposes" framework. No agent operates in a vacuum. Every action—a data transformation, a query generation, a mapping decision—is logged with a complete audit trail. This ensures that when a regulatory body reviews a trial, they can see exactly which agent performed the task, what data it used, and, crucially, which human signed off on the result.
3. Re-engineering the Process
Mallarapu emphasizes that technology alone is not a solution. "If you are introducing automation, you need to think about re-engineering the process as well," he says. The most successful trials of the future will not be those that simply bolt AI onto existing workflows, but those that design workflows around the strengths and limitations of agentic systems.

4. Defining the Ceiling
For the foreseeable future, the "fully autonomous clinical trial" remains a theoretical concept. The stakes—patient safety, regulatory compliance, and therapeutic efficacy—are too high to allow for unmonitored agentic decision-making. The goal is to move from manual data manipulation to a "global view" of the trial, where the agent highlights discrepancies (e.g., a patient starting a new medication without a corresponding adverse event report) and the human makes the final, critical determination.
Conclusion: The Human Element
As the dream of the autonomous trial continues to evolve, the definition of the "clinical researcher" is changing. They are no longer merely data entry clerks or manual monitors; they are becoming supervisors of digital intelligence. The industry is effectively building a "swarm" of agents to manage the complexity of modern science, but the human remains the anchor.
By prioritizing "uncluttered" trial design and maintaining rigorous human oversight, the life sciences sector can harness the immense power of AI without sacrificing the integrity of the clinical data that patients, physicians, and regulators rely upon. The future of drug discovery is not about replacing the human; it is about giving the human the tools to oversee a process that is increasingly beyond the capacity of any one person to manage alone.
About the Author