In the rapidly evolving landscape of oncology, Chimeric Antigen Receptor (CAR) T-cell therapy has emerged as a watershed innovation, offering curative potential for patients who have exhausted conventional treatment pathways. However, the success of this immunotherapy is frequently curtailed by the "Achilles’ heel" of modern oncology: antigen escape. When tumor cells mutate to hide the specific protein a CAR T-cell is programmed to recognize, the therapy fails, leading to rapid disease recurrence.
A breakthrough Phase I clinical trial, led by researchers at The Ohio State University Comprehensive Cancer Center – Arthur G. James Cancer Hospital and Richard J. Solove Research Institute (OSUCCC – James), has unveiled a potential paradigm shift. By deploying a trispecific CAR construct—targeting three distinct proteins simultaneously (CD19, CD20, and CD22) and incorporating a unique OX40 co-stimulatory domain—the research team has demonstrated durable clinical responses in patients with relapsed or refractory B-cell lymphoma. These findings, recently published in Blood Cancer Discovery, offer a compelling blueprint for the next generation of precision immunotherapy.
The Challenge of Antigen Escape in B-Cell Malignancies
To understand the magnitude of this development, one must first understand the limitations of current CAR T-cell therapies. Standard treatments, such as those targeting only CD19, have transformed the prognosis for B-cell malignancies. Yet, clinical data consistently shows that a significant percentage of patients experience relapse within the first year of treatment.
The primary driver of this relapse is often antigen loss. Cancer cells are biologically plastic; under the selective pressure of a therapy that targets a single marker, tumors can downregulate or lose that marker entirely. Consequently, the patient’s modified T-cells are left "blind" to the malignancy, allowing the cancer to progress unchecked.
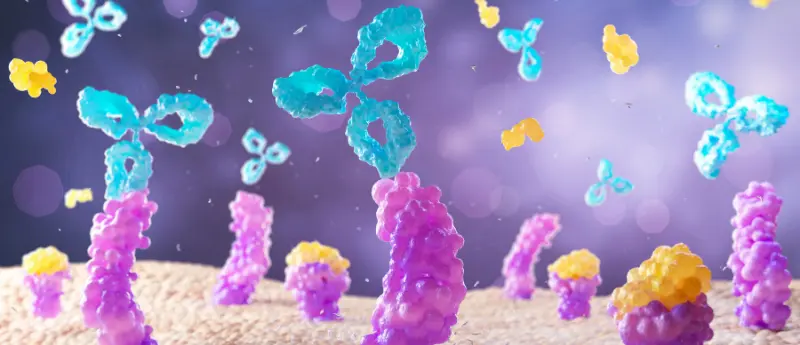
The OSUCCC – James study addresses this by creating a "multi-pronged" attack. By targeting CD19, CD20, and CD22, the researchers have effectively closed the escape routes. If the tumor attempts to downregulate CD19, the CAR T-cell remains equipped to identify and destroy the cell via CD20 or CD22. This redundancy is designed to ensure that the tumor has no viable path to evasion.
Chronology of a Clinical Breakthrough
The journey to these findings represents a meticulously structured effort to address both biological efficacy and logistical feasibility in cell manufacturing.
Pre-Clinical Foundations
Before moving to human trials, the team spent years optimizing the CAR construct. The decision to include the OX40 co-stimulatory domain was strategic. While earlier generations of CAR T-cells utilized different signaling domains, OX40 is known for its ability to promote T-cell proliferation and survival. By integrating this into a trispecific scaffold, the team aimed to enhance the "persistence" of the cells—ensuring they remain active in the patient’s body long enough to eliminate residual disease.
The Phase I Clinical Trial
The trial enrolled 18 patients, all of whom had been diagnosed with relapsed or refractory B-cell malignancies. These were high-risk patients who had already failed a median of three prior lines of therapy, placing them in a category with historically poor prognoses.
- Manufacturing Phase: A critical innovation of this trial was the "point-of-care" manufacturing process. Unlike traditional commercial CAR T-cell therapies, which often require shipping patient cells to a central facility—leading to weeks of waiting—the OSUCCC team developed a system to manufacture the cells locally and rapidly.
- Infusion Phase: Sixteen patients successfully received the trispecific CAR construct. The focus here was on safety and determining the maximum tolerated dose, as the simultaneous targeting of three antigens raised concerns about potential off-target toxicity.
- Observation and Analysis: Patients were monitored closely for adverse events, specifically cytokine release syndrome (CRS) and neurotoxicity, which are common and potentially dangerous side effects of CAR T-cell therapy.
Supporting Data and Clinical Outcomes
The statistical results of the trial are highly encouraging, particularly given the heavily pre-treated nature of the patient population.
- Overall Response Rate (ORR): The trial reported an ORR of 50%.
- Complete Remission (CR): Among patients specifically diagnosed with lymphoma, the complete response rate was a striking 83%.
- Survival Metrics: The one-year overall survival rate stood at 61%. Perhaps more importantly, the patients who achieved complete response exhibited durable remissions, suggesting that the trispecific approach effectively prevented the early relapses typically seen in single-target therapies.
The Role of T-Cell Exhaustion
The study provided a vital secondary insight: the correlation between "apheresis health" and patient outcomes. Researchers discovered that T-cell exhaustion—a state where T-cells become dysfunctional due to chronic stimulation or the tumor microenvironment—was a strong predictor of progressive disease. Patients whose initial cells showed high levels of exhaustion markers were less likely to respond to the treatment. This finding provides a new biomarker for clinicians: screening a patient’s T-cells before engineering could help identify those who might require additional interventions to "rejuvenate" their cells before infusion.
Official Perspectives: The Experts Speak
The study’s success is a testament to the collaborative, multidisciplinary approach fostered at The Ohio State University.
Sumithira Vasu, MBBS, the study’s first and corresponding author, emphasized the novelty of the OX40 integration. "This was the first time a CAR T-cell clinical trial used OX-40 to enhance the process and improve tumor death," Vasu noted. By shifting the co-stimulatory focus, the team has provided a proof-of-concept that the architecture of the CAR molecule itself is as important as the antigens it targets.
Lapo Alinari, MD, PhD, lead senior co-author, highlighted the significance of the "fresh" cell infusion model. "It has been suggested that fresh cell infusions are preferable, and we were able to show the feasibility of rapid manufacturing time and infusion of the fresh cells," Alinari explained. This logistical success is crucial for the future of the field, as it suggests that complex CAR therapies do not necessarily require the lengthy, centralized supply chains that currently limit patient access. The clinical activity, spanning multiple lymphoma subtypes—including mantle cell, follicular, and diffuse large B-cell lymphoma—suggests a broad applicability for this approach.
Marcos de Lima, MD, senior co-author, maintained a tone of cautious, scientific optimism. While acknowledging the "encouraging outcomes," he emphasized the need for broader validation. "More research in larger patient groups is needed," de Lima stated. This underscores the standard progression of clinical research; moving from a successful Phase I safety and feasibility study to larger, randomized Phase II and III trials that can definitively establish the therapy’s superiority over the current standard of care.
Implications for the Future of Oncology
The implications of this trial extend far beyond the immediate success of treating 18 patients. The research suggests three major shifts in how we approach immunotherapy:
1. Moving Toward "Multi-Specific" Architectures
The era of the "single-target" CAR T-cell may be drawing to a close. As the industry learns more about the mechanisms of antigen escape, the development of dual- and trispecific CARs is likely to become the standard. By "covering all bases," clinicians can provide a more robust defense against the tumor’s evolutionary strategies.
2. The Importance of Speed in Manufacturing
The success of the OSUCCC’s point-of-care manufacturing model provides a roadmap for hospitals globally. If CAR T-cell therapies can be produced locally in a hospital setting, it drastically reduces the time-to-treatment. For patients with aggressive, rapidly progressing lymphomas, those few weeks of waiting can be the difference between life and death.
3. Precision Biomarkers
The finding that T-cell exhaustion correlates with treatment failure opens a new avenue for personalized medicine. Future trials might incorporate "fitness checks" for T-cells, potentially using combinations of immunotherapy drugs or epigenetic modulators to reverse exhaustion before the cells are even re-engineered.
Conclusion
The study published in Blood Cancer Discovery is a landmark for the field of hematology-oncology. By successfully navigating the complexities of multi-antigen targeting and integrating innovative co-stimulation, the team at The Ohio State University has provided a beacon of hope for patients who have exhausted all other options.
While the scientific community awaits the results of larger, follow-up trials, this first-in-human trial serves as a definitive proof of concept. It confirms that we can outsmart the tumor’s ability to hide, that we can speed up the delivery of life-saving therapies, and that we are steadily moving toward a future where "relapsed" does not necessarily mean "untreatable." As researchers continue to refine these trispecific constructs, the prospect of long-term, durable, and perhaps even permanent remission for complex B-cell cancers appears closer than ever before.
About the Author