In the landscape of modern oncology, the treatment of breast cancer is undergoing a paradigm shift. As systemic therapies—particularly CDK4/6 inhibitors—extend the survival of patients with metastatic disease, clinicians are increasingly confronted with a unique clinical challenge: the "oligometastatic" or "oligoprogressive" state.
In a recent interview, Dr. Imogen Locke, a leading consultant at The Royal Marsden NHS Foundation Trust, provided an in-depth exploration of how stereotactic ablative radiotherapy (SABR) is emerging as a critical, albeit nuanced, tool in this evolution. By targeting isolated resistant disease clones, SABR offers the potential to delay systemic treatment switches and improve quality of life, marking a move toward highly personalized, biology-driven cancer care.
The Core Challenge: Understanding Oligometastatic Disease
To understand the current shift in radiotherapy, one must first distinguish between the clinical states Dr. Locke identifies. Oligometastatic disease is defined as a limited spread of cancer—typically five or fewer metastases. This can be "synchronous," present at the time of primary diagnosis, or "metachronous," appearing after a disease-free interval.
"In England, it is currently the metachronous scenario where SABR is primarily commissioned," Dr. Locke explains. "We look for a prolonged disease-free interval, which suggests that the disease biology may be more indolent and that ablation of these limited sites could have a meaningful clinical impact."
In contrast, "oligoprogressive" disease occurs in patients already receiving systemic therapy for widespread metastatic cancer. While the systemic treatment remains effective for the majority of the disease, specific "resistant clones" begin to grow in a limited number of sites. Here, the goal of SABR is not necessarily to "cure" the metastatic disease, but to achieve maximum value from existing, low-toxicity systemic therapies by ablating the resistant lesions. This strategy aims to delay the need to transition patients to more toxic, second- or third-line treatments.
Chronology of Treatment: From Long-Course to Rapid Ablation
The history of breast cancer radiotherapy is one of radical de-escalation. When Dr. Locke began her career as a consultant, standard adjuvant radiotherapy courses spanned five to six weeks. Today, the field has moved toward hypofractionation, with the majority of patients completing their treatment in just one week.
The current focus has shifted toward refining these one-week regimens to ensure they are applicable to all patient subgroups, including those requiring internal mammary lymph node irradiation or tumor bed boosts. As the evidence base grows, researchers are looking to consolidate this standard, ensuring that the convenience and efficacy of a one-week regimen are available to the broadest possible demographic.
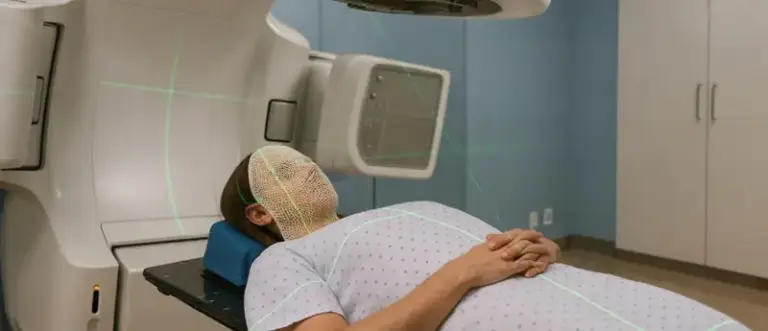
Parallel to this, the adoption of SABR for metastatic disease represents a newer chapter. By delivering highly focused, high-dose radiation, SABR spares the surrounding healthy tissue, making it an exceptionally well-tolerated option for patients who may already be fragile due to systemic disease.
Supporting Data: The Quest for Biological Markers
One of the most pressing questions in oncology is how to accurately select patients for aggressive local therapy. Radiology—while essential—is often an incomplete picture. As Dr. Locke notes, "Radiology can sometimes underestimate the burden of disease. You might see one solitary nodule on a scan, but there may be more widespread microscopic disease that remains hidden."
The Potential of ctDNA
The integration of circulating tumor DNA (ctDNA) analysis is widely viewed as the next frontier. The CURB trial, which examined ablative radiotherapy in both breast and lung cancer populations, provided a glimpse into this future.
In lung cancer cohorts, a progression-free survival benefit from radiotherapy was directly mirrored by a decrease in ctDNA mutation burden. Interestingly, in the breast cancer group, where the primary endpoint was not reached, the ctDNA levels remained unchanged. This suggests that ctDNA may serve as a future "gatekeeper" for therapy, helping clinicians identify which patients possess true oligoprogressive disease and who would benefit most from local ablation versus systemic escalation.

Official Perspectives and Clinical Dilemmas
Dr. Locke highlights that the clinical decision-making process is fraught with "what-if" scenarios. In a recent case study, a patient with triple-negative breast cancer (TNBC) presented with a single progressing lung lesion. Despite the temptation to perform immediate SABR, Dr. Locke opted for caution, performing interval imaging to observe the disease trajectory.
The subsequent findings—the rapid emergence of widespread liver metastases—confirmed the danger of acting on a single visible lesion without understanding the underlying disease momentum. This underscores a vital principle in modern radiotherapy: before subjecting a patient to ablative treatment, the clinician must be certain that the target is a true representative of the patient’s overall disease status.
The Role of Ongoing Trials
The UK is currently at the forefront of this research, with a robust portfolio of trials designed to answer these lingering questions:
- The FAST-Forward Trial: Aiming to solidify the one-week treatment schedule for all adjuvant breast cancer patients.
- The PARABLE Trial: Investigating the potential niche role of proton therapy in adjuvant settings.
- PRADA2: Exploring the sequencing of radiotherapy in the context of DIEP reconstruction, ensuring that oncological success does not come at the cost of cosmetic outcomes.
Implications for Future Practice
The future of radiotherapy in breast cancer lies in the integration of biological data with advanced imaging. As Dr. Locke emphasizes, the next phase of development will move away from "one-size-fits-all" protocols toward personalized treatment plans tailored to the specific molecular signature of the cancer.
1. Personalized Biology
The focus is shifting from "how much radiation" to "what is the biology of this specific cancer?" By incorporating translational studies into every major trial, researchers are seeking to map how individual tumor genetics influence response to radiation.
2. Treatment De-escalation and Quality of Life
The success of shorter, one-week regimens has profoundly changed the patient experience. The ongoing goal is to extend this efficiency to surgical cases and complex reconstructions, ensuring that the "cancer journey" is as non-intrusive as possible.
3. Precision in the Metastatic Setting
For patients with oligometastatic or oligoprogressive disease, the paradigm is becoming increasingly sophisticated. Rather than viewing surgery or radiotherapy as a "last resort," clinicians are beginning to use these tools strategically to extend the shelf-life of successful systemic therapies.
Conclusion: The Horizon of Breast Cancer Care
As Dr. Locke reflects on her career, the transformation of the field is undeniable. "Breast radiotherapy has changed so much," she notes. "Now, I think the real unanswered question, and the one where we do need trials, is how we personalize radiotherapy more to the biology of the disease."
The marriage of advanced radiotherapy with systemic innovation and molecular diagnostics represents a new dawn for breast cancer patients. While challenges remain—particularly in defining the true oligoprogressive state—the dedication to rigorous, trial-led evidence ensures that the next decade will likely be as transformative as the last. For patients, this means more than just longer survival; it means the possibility of achieving sustained disease control while maintaining the highest possible quality of life.
Through the collaborative efforts of institutions like The Royal Marsden and the continued development of tools like ctDNA monitoring, the oncological community is inching closer to a future where every treatment is a precise, calculated strike against the specific biological vulnerabilities of the individual’s cancer.
About the Author