Introduction
A significant shift in U.S. immigration and healthcare policy has created a precarious landscape for some of the nation’s most vulnerable residents. Following the enactment of the 2025 reconciliation law, thousands of refugees and asylees—individuals who have fled persecution and established a legal foothold in the United States—now face a critical loss of access to federally funded health coverage.
Under the new regulatory framework, access to Medicaid, the Children’s Health Insurance Program (CHIP), subsidized Affordable Care Act (ACA) Marketplace coverage, and Medicare is effectively tied to Lawful Permanent Resident (LPR) status, commonly known as a "green card." This legislative change has transformed U.S. Citizenship and Immigration Services (USCIS) processing times from a routine administrative matter into a determinant of basic survival. As USCIS processing backlogs mount, refugees and asylees are being left in a state of “coverage limbo,” stripped of health security while waiting for their residency applications to be adjudicated.
The Chronology of Policy Shifts
The erosion of health access for humanitarian migrants did not occur in a vacuum; it is the culmination of years of shifting immigration priorities.
- Historical Context (1980–2024): Since the Refugee Act of 1980, the United States maintained a robust, formal system for humanitarian protection. Refugees and asylees were historically granted immediate access to social safety nets, including food assistance and health coverage, to facilitate their transition from traumatic environments to self-sufficiency.
- The 2025 Reconciliation Law: The landscape shifted dramatically with the passage of the 2025 reconciliation law. This legislation explicitly eliminated the exemption that allowed refugees and asylees—who have not yet obtained LPR status—to enroll in federally funded health programs.
- Implementation Phases: The impact of this law was staged to maximize its reach. Medicaid and CHIP restrictions were the first to take effect on October 1, 2026. Shortly thereafter, in January 2027, the gates to subsidized ACA Marketplace plans and Medicare were closed to these populations.
- Administrative Slowdown (2025–2026): Concurrently, the federal government enacted significant restrictions on new admissions. By reducing the refugee admission ceiling from 125,000 in FY2025 to 7,500 in FY2026 and effectively sealing the southern border to asylum seekers, the administration signaled a pivot toward extreme administrative restrictionism.
Supporting Data: The Processing Crisis
The correlation between administrative efficiency and health access is stark. KFF analysis of USCIS data reveals that the federal government is failing to process green card applications at a pace that matches the needs of those whose health coverage now depends on these documents.
The Decline in Completed Applications
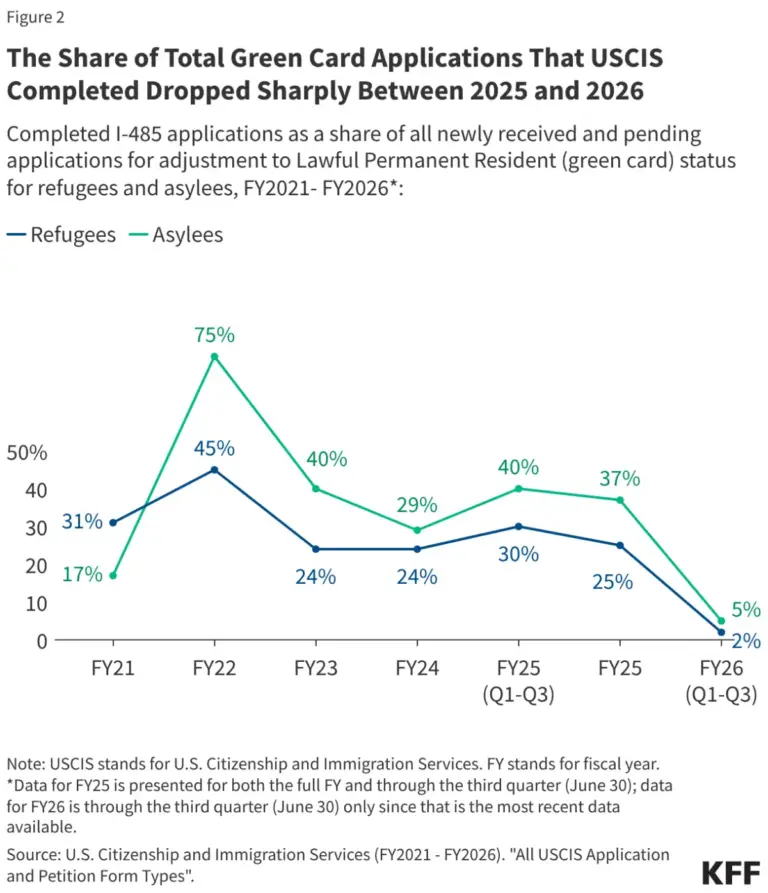
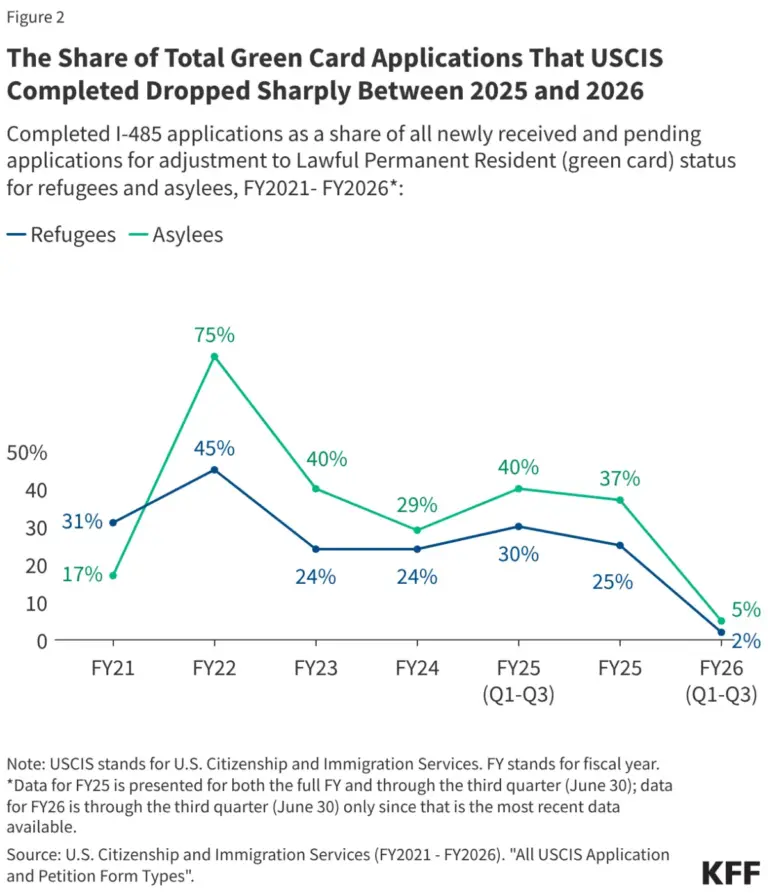
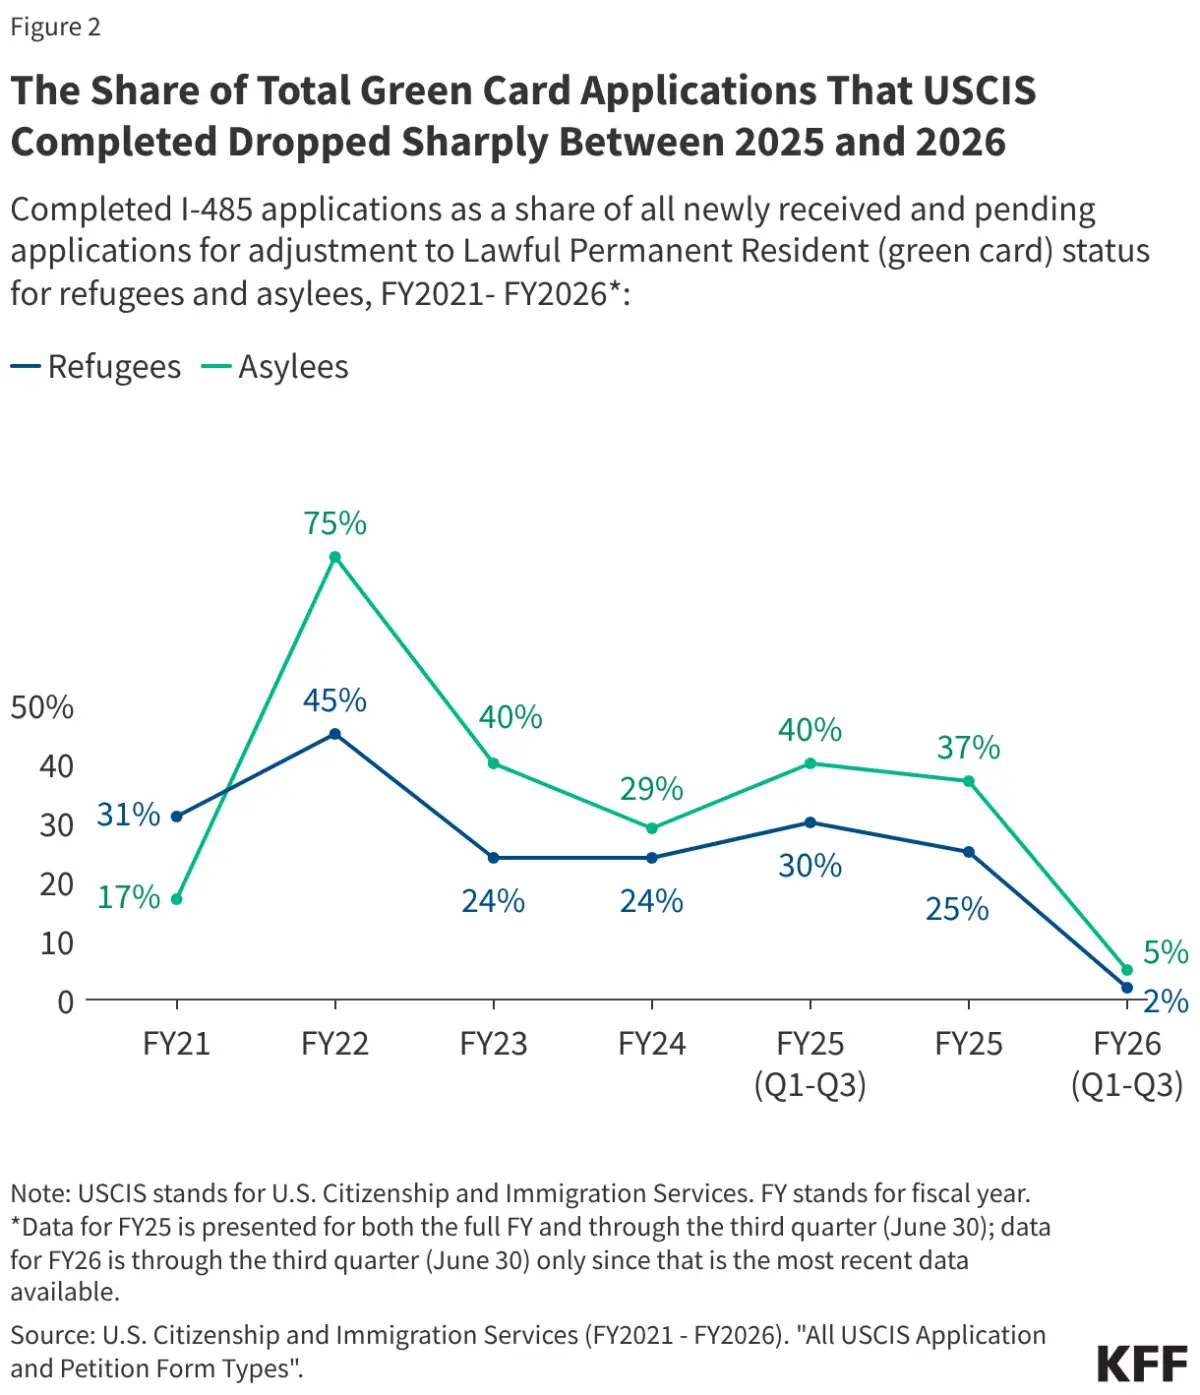
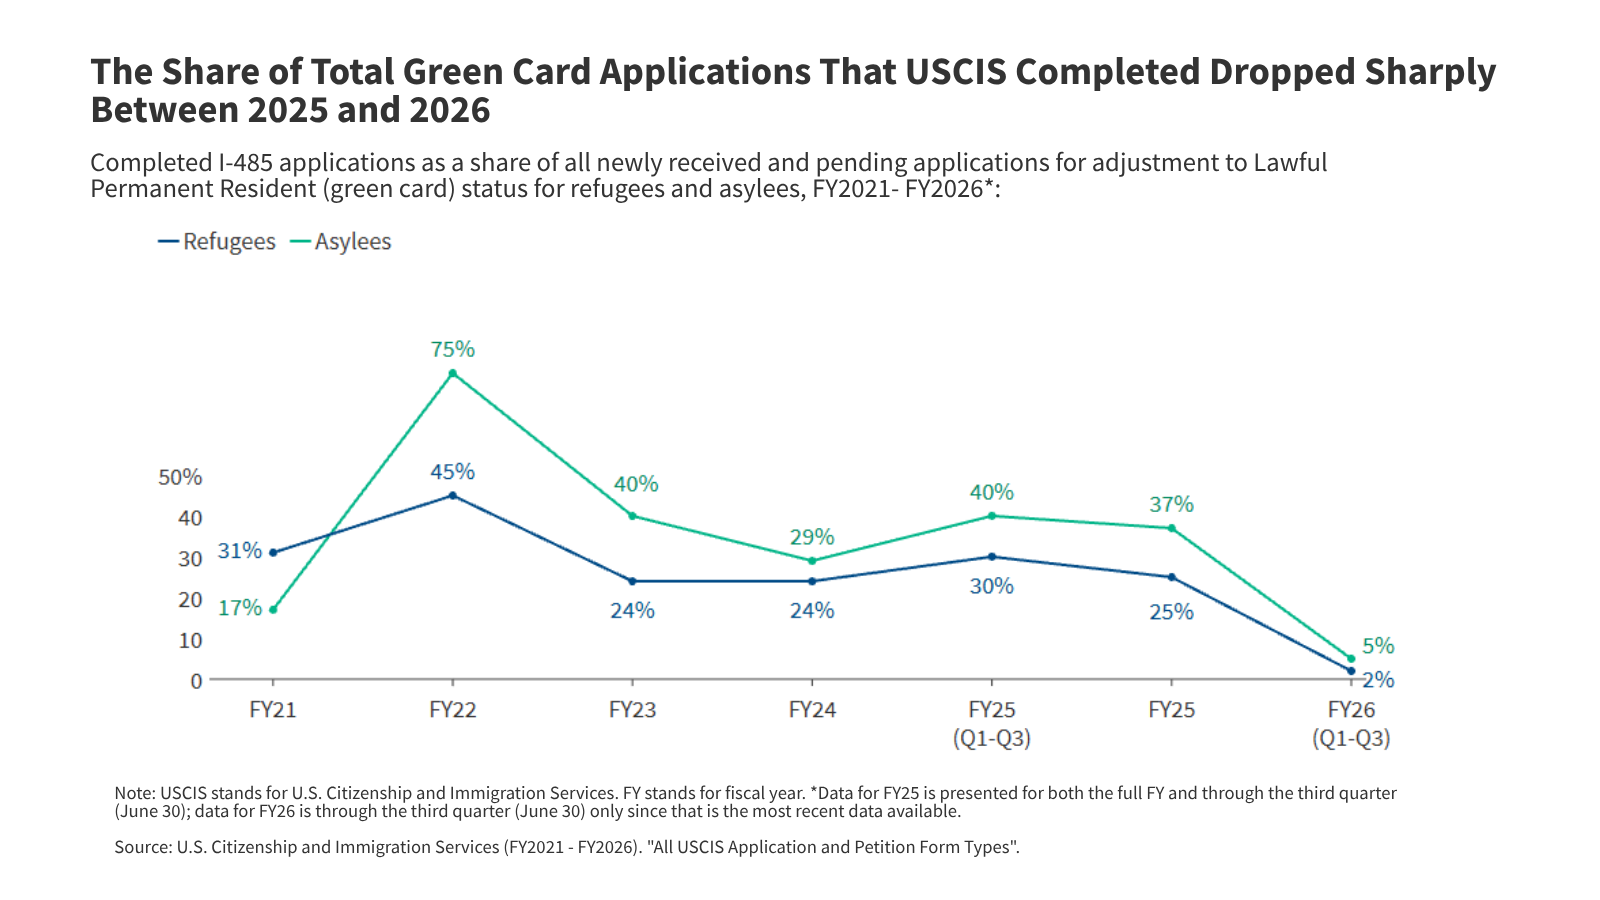
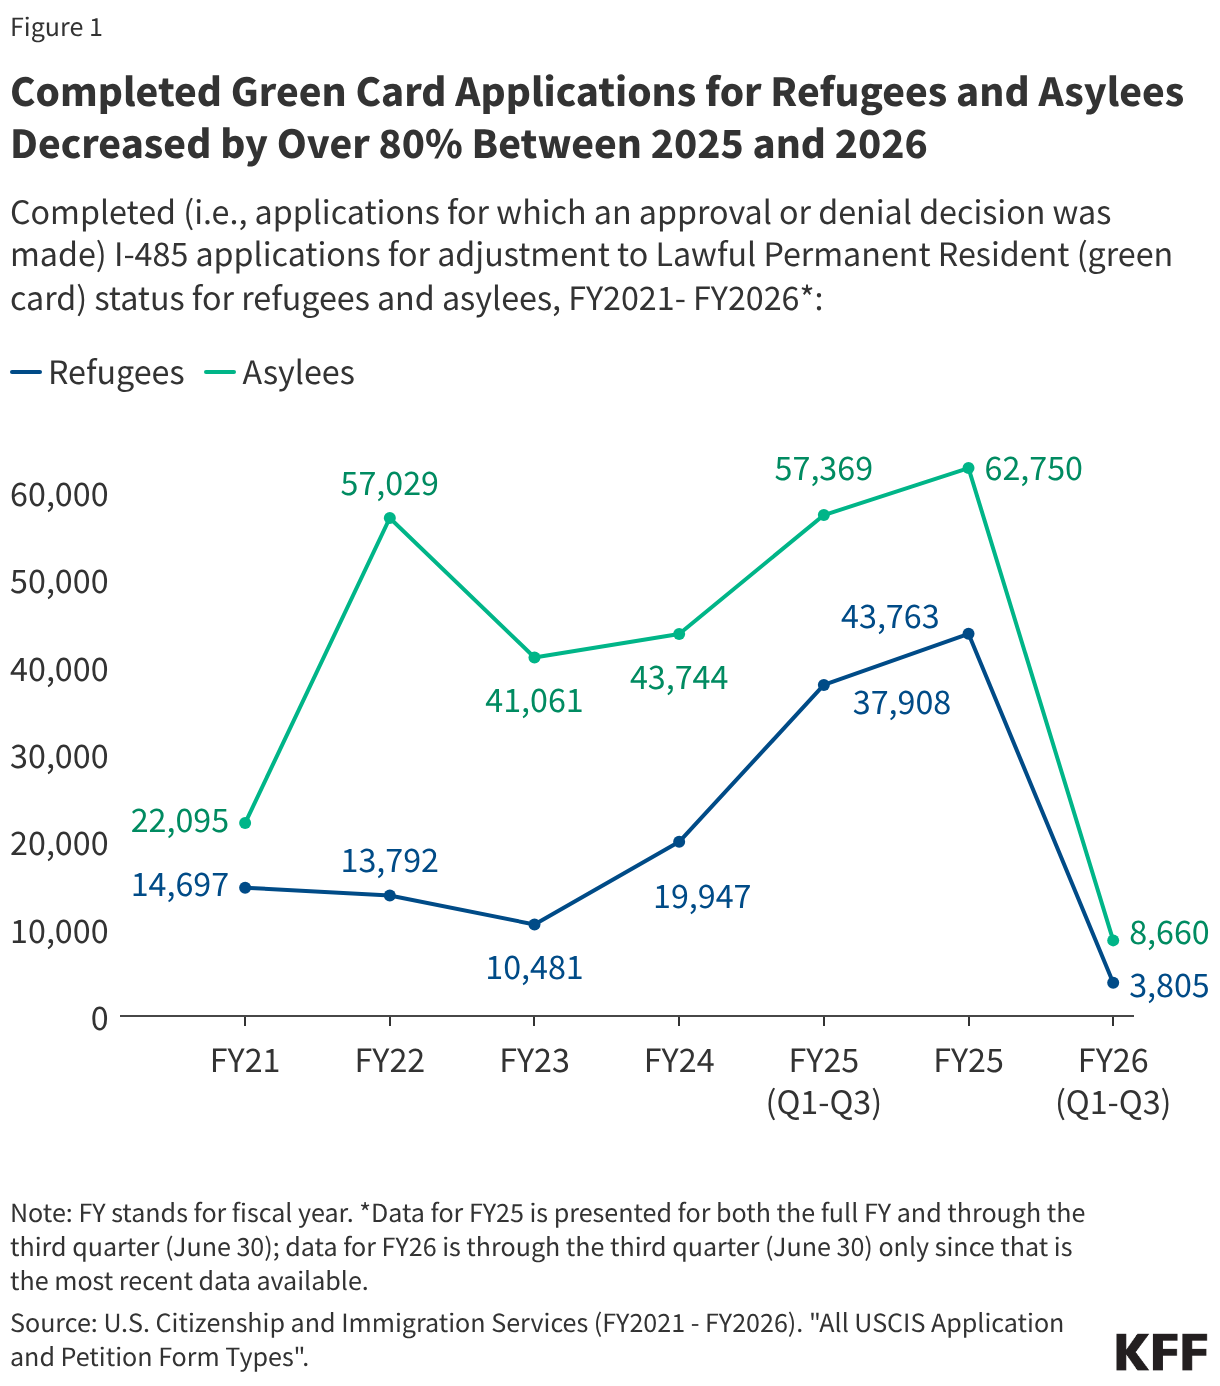
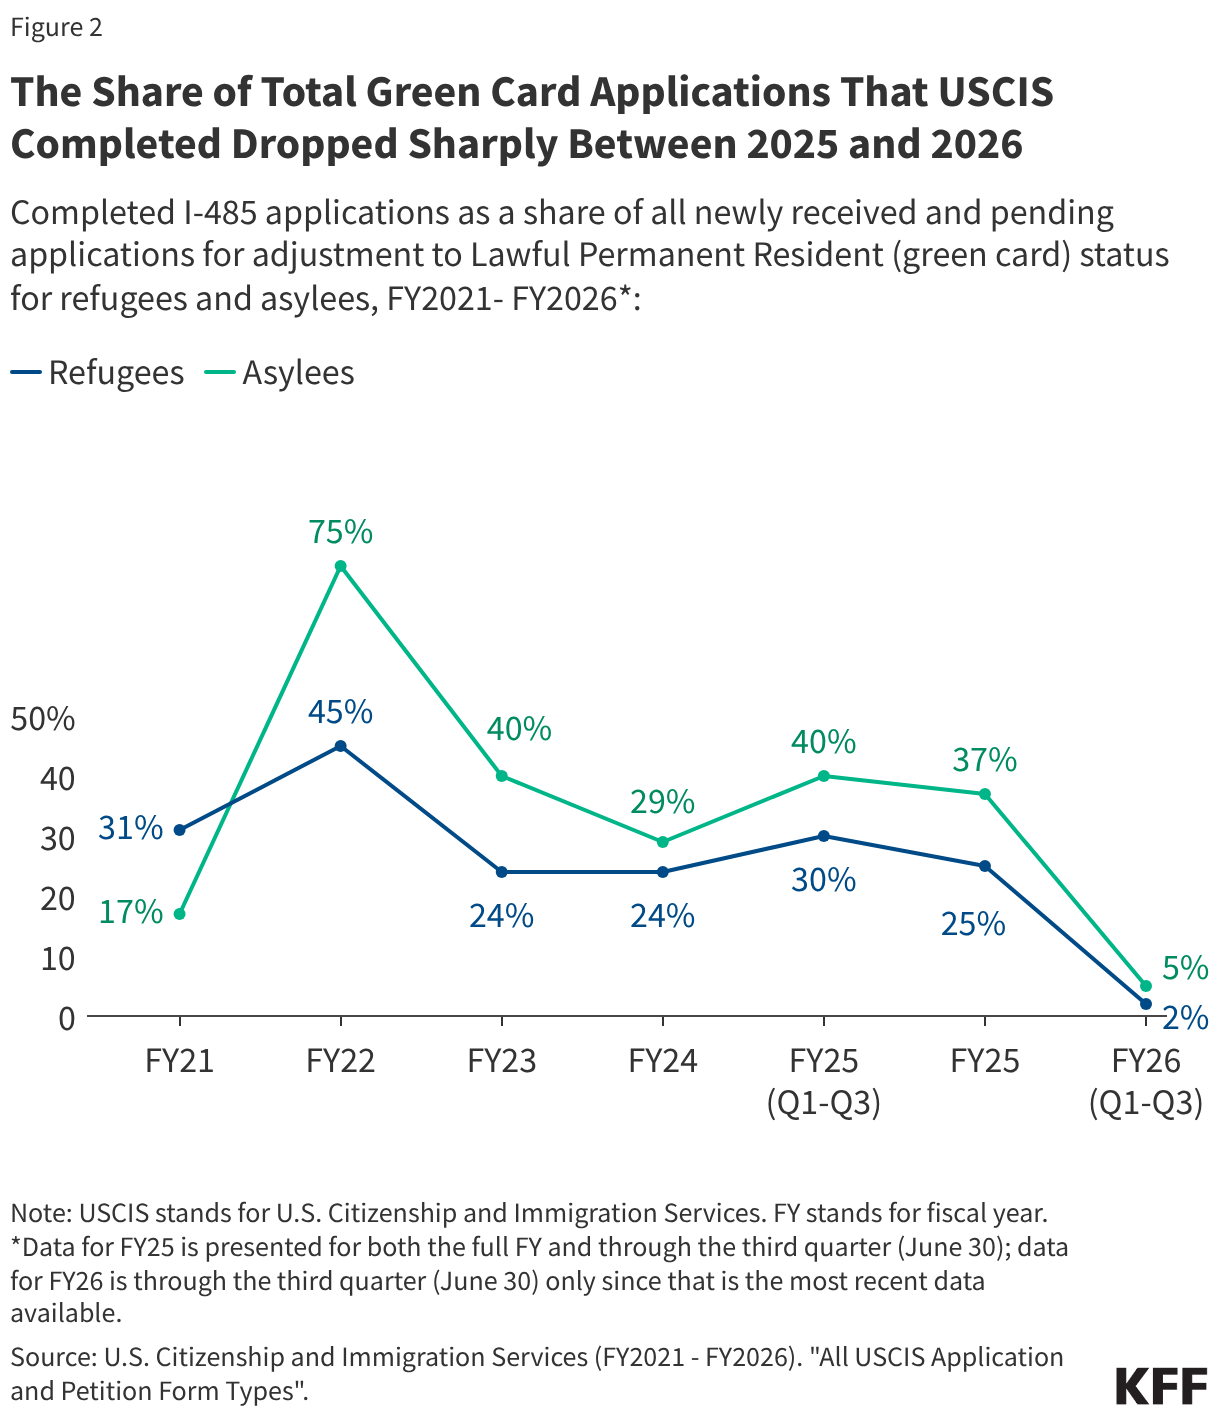
Between FY2021 and FY2025, USCIS had made significant progress in clearing backlogs, with application completions increasing by 198% for refugees and 184% for asylees. However, this momentum collapsed between FY2025 and FY2026. In the first three quarters of FY2026, the number of completed applications plummeted by 90% for refugees and 85% for asylees compared to the same period in the previous year.
The Rise of the Pending Backlog
As of June 30, 2026, the backlog of pending I-485 applications (the form used for adjustment to LPR status) reached a staggering 275,737. This accumulation is not merely a statistical curiosity; it represents hundreds of thousands of people awaiting a decision that determines their eligibility for life-saving medical care.
Processing Time Escalation
The most alarming indicator is the rapid expansion of average processing times. For refugees, wait times climbed from 7.8 months in FY2025 to 13.3 months by mid-2026. The situation is even more dire for asylees, who saw their wait times jump from 10.7 months to 19.9 months. Within the 2026 fiscal year alone, these times accelerated monthly, with asylee processing reaching an average of 25.6 months by the third quarter—meaning some applicants could be waiting more than two years for a decision that grants them the right to purchase subsidized health insurance.
Official Responses and Political Justifications
The policy changes have been met with intense scrutiny from public health experts, humanitarian organizations, and policymakers.
Proponents of the 2025 reconciliation law argue that these measures are necessary to prioritize federal resources for U.S. citizens and to streamline the immigration system. Supporters emphasize that the five-year waiting period for federal benefits, which applies to most immigrants, should also apply to those seeking humanitarian refuge, arguing that this creates a uniform standard for all "qualified" immigrants.
Conversely, health policy advocates and human rights groups have condemned the move. The Congressional Budget Office (CBO) has projected that these eligibility restrictions will lead to approximately 1.4 million people becoming uninsured by 2034. Critics argue that forcing refugees—many of whom arrive with significant, untreated health conditions resulting from the trauma of displacement—to wait years for coverage is not only a moral failure but a public health risk.
USCIS, while rarely commenting on the political drivers of its processing times, has pointed to a combination of increased application volume, staffing challenges, and evolving security screening protocols as reasons for the mounting backlogs. However, critics point out that the sharp decline in "completions" during 2026 suggests that the bottleneck is as much about policy-driven prioritization as it is about resource constraints.
Implications for Public Health and Society
The intersection of bureaucratic delay and legislative restriction creates a "perfect storm" for the health of immigrant communities.
The Financial Burden of Being Uninsured
Without access to Medicaid or subsidized ACA plans, refugees and asylees are left to rely on charitable care or out-of-pocket payments. For families living on low incomes, this is a financial impossibility. The result is the delay of preventative care, which often leads to the deterioration of manageable health conditions into acute, emergency-room-level crises. This creates an unintended "cost-shift," where the burden of care is moved from the insurance system to hospitals, which are legally required to provide emergency treatment regardless of a patient’s ability to pay.
Social Integration and Economic Productivity
Health is a foundational element of successful integration. Refugees and asylees are expected to find work and integrate into their new communities rapidly. The stress of being uninsured, coupled with the uncertainty of one’s legal and financial status, acts as a significant barrier to employment. A worker who is physically unwell and lacks access to a primary care provider is less likely to remain consistently employed, creating a cycle of poverty that the U.S. immigration system is ostensibly designed to prevent.
A Long-Term Demographic Crisis
By 2034, the projection of 1.4 million uninsured individuals underscores the long-term nature of this crisis. If the current administrative trend continues, the backlog will likely continue to grow, rendering the path to LPR status—and the health security that comes with it—a theoretical possibility rather than a practical reality.
Conclusion
The 2025 reconciliation law, coupled with the administrative slowdown at USCIS, has fundamentally altered the terms of entry for refugees and asylees. By tethering health coverage to a processing system that is currently operating at a fraction of its former capacity, the U.S. has created a system where legal status does not guarantee basic welfare.
As the backlog of 275,000 applications continues to grow, the human cost is mounting. For those fleeing persecution, the journey to the United States was meant to be the end of their struggle for safety. Today, however, that journey is increasingly marred by an administrative reality that denies them the very health security necessary to build a new, stable life. The challenge moving forward remains clear: without either a legislative reversal of these coverage restrictions or a massive, immediate investment in the administrative capacity of USCIS, a significant portion of the immigrant population will continue to live in the shadows of an American healthcare system that has effectively locked them out.
About the Author