
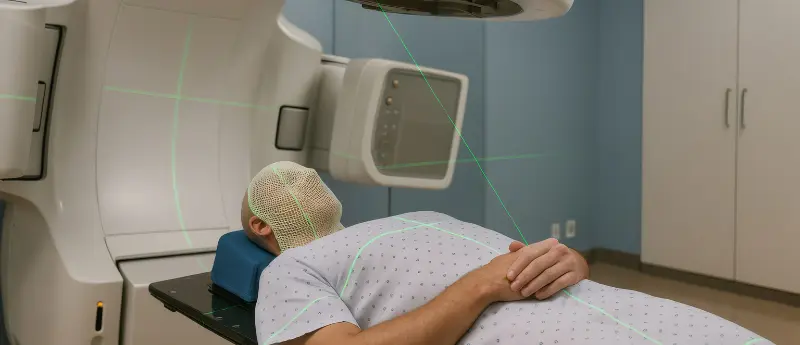
For decades, the standard of care for patients diagnosed with brain metastases originating from small cell lung cancer (SCLC) has been anchored in whole-brain radiotherapy (WBRT). While stereotactic radiosurgery (SRS) has become the gold standard for managing brain metastases from most other tumor histologies—largely due to its superior ability to preserve neurocognitive function and maintain quality of life—SCLC patients have historically been excluded from the landmark trials that cemented SRS as the preferred modality.
The recently concluded NRG-CC009 Phase III clinical trial, however, has fundamentally challenged this status quo. Presented at the 2026 American Society for Radiation Oncology (ASTRO) Annual Meeting in Boston, the study’s findings suggest that while SRS may not provide the expected neurocognitive reprieve over hippocampal-avoidant WBRT (HA-WBRT), it offers a significant and unexpected survival advantage. This revelation is poised to reshape clinical guidelines and patient counseling for one of the most aggressive forms of cancer.
Main Facts: The NRG-CC009 Trial Overview
The NRG-CC009 study was designed to determine whether SRS could replace HA-WBRT as the preferred treatment for patients with brain metastases from SCLC. The trial recruited 151 eligible patients, who were stratified based on their disease-specific graded prognostic assessment (GPA) scores and the total number of intracranial lesions. Participants were randomized in a 1:1 ratio to receive either SRS alone or HA-WBRT combined with memantine—a drug often used to protect against neurocognitive decline during radiation therapy.
The primary objective of the trial was to evaluate "time to neurocognitive failure." Secondary endpoints were equally critical, focusing on overall survival (OS), intracranial disease progression, neurological death, the need for salvage therapies, and the incidence of grade 3-5 adverse events.
While the trial failed to meet its primary endpoint—showing no statistically significant difference in neurocognitive failure between the two treatment arms—the secondary findings were striking. Patients treated with SRS exhibited a median overall survival of 17.4 months, compared to just 8.6 months for those who received HA-WBRT. This significant survival benefit, coupled with comparable central nervous system (CNS) control, has provided a new pathway for oncologists to treat a patient population that has long been considered high-risk for poor outcomes.
Chronology: The Evolution of SCLC Brain Metastasis Management
The journey to the NRG-CC009 results is marked by a long-standing clinical apprehension regarding the use of SRS in SCLC. Historically, SCLC is characterized by its rapid doubling time and high propensity for systemic and intracranial dissemination. Because of this, clinicians have long feared that "upfront" SRS alone—which focuses radiation on specific lesions rather than the entire brain—would leave occult microscopic disease untreated, leading to diffuse CNS progression and, ultimately, a faster decline in both neurological function and survival.
- The WBRT Era: For years, WBRT was the default, as it was believed to provide essential prophylactic control over potential microscopic metastases throughout the brain.
- The Cognitive Shift: As other cancer types (such as non-small cell lung cancer and melanoma) moved toward SRS, clinicians began to recognize the long-term neurocognitive toxicity associated with WBRT, leading to the development of HA-WBRT with memantine as a way to mitigate these effects.
- The Inception of NRG-CC009: Recognizing the lack of data for SCLC, researchers initiated the NRG-CC009 trial to rigorously test the hypothesis that SRS could match the intracranial control of WBRT while offering a superior neurocognitive profile.
- The 2026 ASTRO Plenary: The presentation of the final results in Boston marked a turning point. The data confirmed that while the neurocognitive benefit was not realized, the surprising survival benefit shifted the conversation entirely, moving SRS from a "risky alternative" to a "reasonable standard of care."
Supporting Data: Analyzing the Trial Metrics
The statistical robustness of the NRG-CC009 trial is underscored by its rigorous design. With 91 events recorded, the study was powered at 85% to detect a 17% absolute reduction in neurocognitive failure. The baseline characteristics of the 151-patient cohort were well-balanced, with a median of two brain metastases per patient (range, 1-26; interquartile range, 1-5).
Key Statistical Outcomes
- Neurocognitive Failure: No significant difference was observed between the two cohorts. The adjusted hazard ratio (HR) for the SRS arm was 0.83 (95% CI, 0.53–1.28; p=0.39).
- Overall Survival: The most significant finding was the superior survival in the SRS group. The median OS was 17.4 months (SRS) versus 8.6 months (HA-WBRT), with an adjusted HR of 0.60 (95% CI, 0.39–0.91; p=0.016).
- Disease Control and Toxicity: Perhaps most importantly for safety concerns, there was no statistically significant difference in adjusted analyses regarding intracranial failure, neurological mortality, or the incidence of treatment-related grade 3-5 adverse events.
These data points effectively neutralize the primary counter-argument against SRS in SCLC: that it would lead to rapid neurological death due to untreated intracranial disease. The results indicate that SRS is not only safe but is associated with improved survival, a finding that warrants deeper investigation into the biological mechanisms driving this outcome.
Official Responses and Expert Commentary
The research community has received these findings with a mix of surprise and cautious optimism. Lead investigators have emphasized that the results provide a much-needed evidence base for shared decision-making.
Dr. Chad Rusthoven of the University of Colorado Anschutz, the lead author of the abstract, noted that the fears surrounding SRS in SCLC were largely unfounded based on the trial data. "One of the fundamental concerns with upfront SRS alone for SCLC is that patients might develop diffuse CNS progression leading to worse neurologic and survival outcomes. However, that is not what we observed in NRG-CC009," Dr. Rusthoven stated. "Although there were no differences in neurocognitive failure, treatment with SRS was associated with superior overall survival compared to HA-WBRT. These findings support SRS as a reasonable standard of care option for patients with SCLC brain metastases."
Dr. Vinai Gondi of the Northwestern University Feinberg School of Medicine, the lead Principal Investigator of the trial, highlighted the practical utility of these findings for clinicians. "NRG-CC009 provides results that will help physicians better counsel their patients on treatment approaches for SCLC brain metastases. The overall survival difference is an important factor to be discussed with patients," he noted.
Implications for Clinical Practice
The implications of NRG-CC009 are immediate and far-reaching. For the oncologist, this trial provides the necessary clinical validation to move away from WBRT in eligible SCLC patients.
Changing the Standard of Care
The trial suggests that SRS should no longer be viewed as a secondary option for SCLC patients. Instead, it should be offered as a front-line alternative. By avoiding the potential systemic and cognitive side effects of whole-brain radiation, while simultaneously potentially extending life, SRS offers a more patient-centric approach to care.
The Role of Shared Decision-Making
Because the trial did not show a clear superiority in neurocognitive outcomes, physicians must now engage in nuanced conversations with patients. The decision-making process will likely weigh the improved overall survival seen in the SRS arm against the specific clinical presentation of the patient’s intracranial disease.
Future Directions
While NRG-CC009 is a landmark study, it also opens the door for further research. Future trials may look at combining SRS with systemic therapies—such as immunotherapy or newer targeted agents—to see if the survival benefit observed in this trial can be further compounded. Additionally, researchers will likely continue to analyze the "neurocognitive failure" metric to understand if there are specific subsets of SCLC patients who might derive a greater cognitive benefit from one treatment over the other.
Conclusion
The NRG-CC009 trial stands as a testament to the importance of challenging entrenched medical dogma. By rigorously testing the use of stereotactic radiosurgery in small cell lung cancer, the research team has successfully dismantled the long-standing prohibition against SRS in this patient population. While the primary hypothesis regarding neurocognitive preservation was not supported, the discovery of a nearly two-fold increase in median overall survival is a clinical victory of the highest order. As the medical community digests these results, it is clear that for many patients with SCLC brain metastases, the future of treatment is looking significantly brighter, more effective, and more precise.
Disclaimer: This project was supported by grants U10CA180822 (NRG Oncology SDMC), UG1CA189867 (NCORP), U24CA180803 (IROC), and several others from the National Cancer Institute (NCI). The content is solely the responsibility of the authors and does not necessarily represent the official views of the National Institutes of Health.
About the Author








