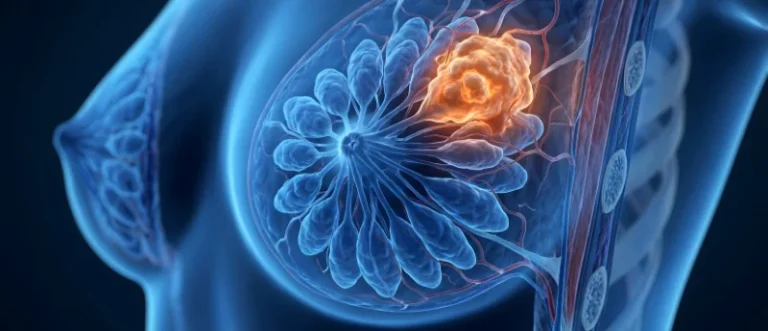
For many cancer patients, the physical toll of treatment—surgical scars, hair loss, weight fluctuations, and shifts in sexual functioning—is not merely a side effect to be managed; it is a profound psychological rupture. According to Licensed Clinical Social Worker (LCSW) Carrie Panzer, a specialist in cancer survivorship, these transformations can fundamentally shatter a patient’s sense of bodily trust, leaving them to navigate a new, often alien, physical reality.
As the oncology field shifts toward more personalized, patient-centered models, the conversation surrounding body image is moving from the periphery to the center of clinical care. Panzer argues that without proactive psychoeducation and long-term support, the psychological distress triggered by bodily changes can severely impede treatment adherence and diminish long-term quality of life.
The Core Crisis: When the Body Becomes a Stranger
At the heart of the oncology experience lies a difficult transition: the movement from a body that is perceived as a reliable, healthy vessel to one that feels vulnerable, betrayed, or fundamentally "broken."
"When patients aren’t adequately prepared for the physical transformations brought on by a cancer diagnosis and subsequent treatment, their capacity to cope and adapt over the long term can be significantly compromised," says Panzer.
This erosion of bodily trust is not purely aesthetic. It encompasses deep-seated emotional struggles involving gender identity, perceived attractiveness, and the capacity for intimacy. When these internal shifts are not addressed, they can manifest as shame and social withdrawal, effectively isolating the patient exactly when they require the most support.
The "Fire Hose" Effect
Upon diagnosis, patients are often overwhelmed by a deluge of medical information, a phenomenon Panzer describes as "drinking from a fire hose." During this acute phase, the loss of control over one’s schedule and routine is exacerbated by a loss of control over one’s physical form. Proactive education—setting expectations for hair loss, surgical changes, or metabolic shifts—serves as a grounding mechanism, helping patients maintain a tether to their sense of self even as their bodies undergo radical changes.
Chronology of Care: A Continuum of Intervention
Addressing body image is not a "one-and-done" task; it requires a tiered approach that spans the entire oncology journey.
Phase 1: The Initial Diagnosis
At the moment of diagnosis, the primary goal is the normalization of distress. Panzer notes that early in the journey, terms like "body positivity" can feel dismissive or unachievable. Instead, the focus should be on creating a safe space for the patient to grieve the loss of their pre-cancer body. By acknowledging that feelings of betrayal and shame are valid, care teams can prevent these emotions from becoming internalized stigmas.

Phase 2: Active Treatment
During the grueling cycle of chemotherapy, radiation, or surgery, the goal shifts to management and adaptation. Here, the oncology social worker plays a pivotal role. While oncologists focus on the life-saving biological interventions, social workers provide the necessary scaffolding to help patients process the grief of their changing physical self.
Phase 3: The Survivorship Gap
The most critical point of vulnerability, according to Panzer, occurs when active treatment concludes. Patients often report being "pushed out the door," moving from a highly structured medical environment to a post-treatment landscape where they are expected to "go back to normal." This transition is often where the psychological weight of the experience truly settles in, leading to depression and a persistent fear of recurrence.
Supporting Data and Therapeutic Frameworks
To navigate these complex emotional landscapes, Panzer advocates for the use of Acceptance and Commitment Therapy (ACT). Unlike traditional approaches that may focus on changing thoughts, ACT-based interventions in oncology encourage patients to gain perspective on their struggles without becoming trapped in emotional resistance.
"By guiding them to acknowledge and accept their current reality, and the grief that comes with it, we empower them to reconnect with what matters most and live a meaningful, values-driven life alongside those changes," Panzer explains.
Furthermore, the data suggests that psychosocial support is not just a "nice-to-have" luxury; it is a clinical necessity. Patients with unaddressed body image distress are statistically more likely to exhibit non-adherence to treatment regimens, which directly correlates to poorer oncological outcomes.
The Paradigm Shift: Addressing the Needs of Younger Patients
Historically, cancer care models were designed with an older demographic in mind. However, the rise in early-onset cancer cases demands a modern, specialized approach. For patients in their 20s and 30s, a diagnosis is not just a medical event; it is a developmental catastrophe.
The Developmental Disruption
Consider a young adult undergoing a bilateral mastectomy or chemotherapy-induced menopause. While their peers are hitting milestones—getting married, starting families, or climbing career ladders—these patients are grappling with permanent alterations to their reproductive and sexual health.
The contrast between the "normal" life of their peers and the clinical reality of their survivorship can lead to profound isolation. Panzer emphasizes that current one-size-fits-all models are insufficient. Health systems must invest in Adolescent and Young Adult (AYA) survivorship pathways that explicitly account for:

- Fertility and reproductive counseling.
- Workplace accommodation and professional identity.
- Dating and intimacy in the age of chronic illness.
Implications for Clinical Practice and Policy
If we are to improve the long-term psychological health of cancer survivors, the standard of care must evolve. Panzer offers a clear roadmap for oncology professionals and policymakers.
The Role of the Care Team
Every member of the clinical team—from the oncologist to the nursing staff—bears responsibility for initiating the conversation. "Too often, body image concerns are left unaddressed because no one opens the door," says Panzer. Normalizing the fact that cancer alters one’s relationship with their body does not require a mental health degree; it requires empathy, observation, and the willingness to ask, "How are you feeling about the changes in your body?"
Mandating Long-Term Survivorship Programs
The most transformative change, however, would be at the systemic level. Panzer advocates for the mandatory funding and institutionalization of long-term survivorship programs.
The current system essentially abandons patients at the "cliff" of post-treatment. By integrating psychosocial support into the long-term survivorship framework, institutions can provide:
- Ongoing Surveillance: Monitoring not just for cancer recurrence, but for the late effects of treatment (e.g., neuropathy, lymphedema, sexual dysfunction).
- Psychosocial Continuity: Maintaining a bridge between the patient and the care team to mitigate social withdrawal and depression.
- Values-Based Counseling: Helping patients redefine their "new normal" and reintegrate into their personal and professional lives with confidence.
Conclusion: A Call to Action
The journey through cancer is as much a psychological trial as it is a biological one. As we advance in our ability to treat the disease, we must be equally ambitious in our treatment of the person. By prioritizing early psychoeducation, embracing evidence-based therapeutic models like ACT, and mandating comprehensive, long-term survivorship programs, the medical community can ensure that patients are not merely surviving the cancer, but reclaiming their lives.
As Carrie Panzer highlights, "The moment of post-treatment is when they truly begin to process what they’ve been through." It is our responsibility to ensure that when they reach that moment, they are not alone.
For oncology professionals looking to deepen their expertise in this area, the Association of Oncology Social Work (AOSW) provides extensive resources and training on integrating psychosocial care into the cancer continuum. Visit www.aosw.org to learn more about advocacy and best practices in the field.
About the Contributor:
Carrie Panzer, LCSW, is a clinical social worker and Licensed Be Body Positive Facilitator. With a career spanning roles at Memorial Sloan Kettering and St. Luke’s Health System, her work focuses on the intersection of grief, loss, and healthy embodiment. She currently maintains a private practice dedicated to helping individuals navigate the profound personal transformations inherent in the cancer experience.
About the Author