In the intricate landscape of American healthcare, the Medicaid program represents a critical safety net for millions. Protecting the integrity of this massive federal-state partnership is a complex, high-stakes endeavor that relies on a specialized frontline of law enforcement: the Medicaid Fraud Control Units (MFCUs). As the Trump Administration intensifies its focus on rooting out waste, fraud, and abuse across federal agencies, these state-based units have found themselves at the center of a brewing federal confrontation. With recent funding suspensions in high-profile states, the role and future of MFCUs have become a flashpoint for debate over fiscal responsibility and state autonomy.
The Mandate: What Are MFCUs?
Under federal law, every state is required to operate an MFCU—a specialized law enforcement entity tasked with investigating and prosecuting provider fraud and protecting patients in Medicaid-funded facilities from abuse and neglect. To ensure objectivity, these units are structurally insulated from the state Medicaid agencies that manage program disbursements. Typically housed within the office of the State Attorney General, MFCUs are staffed by multidisciplinary teams of investigators, attorneys, and auditors.
While their primary objective is the recovery of taxpayer funds through the identification of fraudulent billing, MFCUs serve a dual mandate: policing criminal acts against the program and safeguarding the welfare of vulnerable populations in nursing homes, hospitals, and assisted living facilities. It is important to note that their jurisdiction is specific to provider fraud. Beneficiary fraud—misconduct by patients—falls under the purview of state Medicaid agencies, though evidence suggests such cases are statistically rare compared to provider-side malfeasance.
Chronology of a Federal Crackdown
The landscape for MFCUs shifted dramatically in early 2026 as the federal government adopted a more aggressive oversight posture.
- May 2026: HHS Inspector General (HHS-OIG) sent a formal notice to all state Attorneys General, signaling an era of "rigid MFCU compliance." The letter promised a new, robust review process ahead of annual recertifications.
- June 2026: The tension escalated when the HHS-OIG issued a historic denial of recertification for the MFCUs in Hawaii and New York. This move effectively suspended federal funding for these units, citing insufficient case outcomes and low recovery rates.
- August 2026: In a strategic pivot to boost investigative capacity, the HHS-OIG issued a waiver allowing MFCUs to conduct data mining for fraud patterns without prior federal approval, removing a long-standing bureaucratic hurdle.
- September 2026: As of mid-September, the HHS-OIG has begun a wave of "conditional recertifications" for 11 states, mandating specific corrective actions. This marks a departure from historical norms, as conditional status was rarely, if ever, utilized prior to 2026.
The Mechanics of Enforcement: From Referral to Recovery
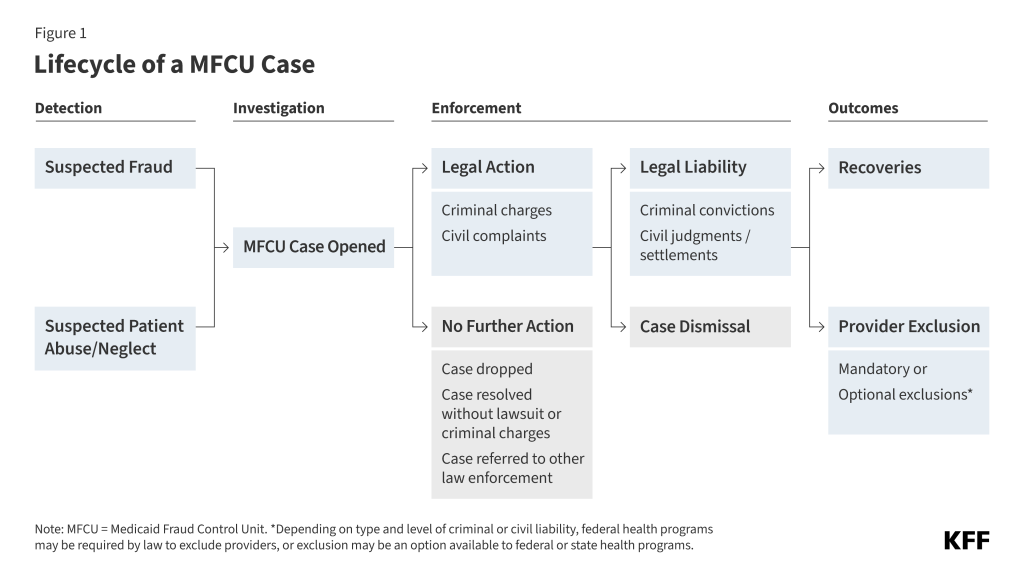
The life cycle of a Medicaid fraud case is a rigorous, often years-long process. It typically begins with a "trigger"—a referral from a state Medicaid agency, a Managed Care Organization (MCO), or a whistleblower complaint.

Modern fraud detection has shifted from manual auditing to sophisticated data analytics. Agencies now scan for billing anomalies, such as "upcoding" (billing for more expensive services than were provided), "double-billing," or inexplicable spikes in hours reported by providers. Once a lead is substantiated, the MFCU initiates a formal investigation. If the evidence meets the burden of proof, the unit may pursue criminal charges, civil litigation, or both.
The end goal is twofold: punishment and restitution. Convictions can lead to incarceration, hefty fines, and permanent exclusion from participating in any federally funded healthcare program. Recoveries are the financial cornerstone of these efforts, with billions of dollars returned to state and federal coffers annually. However, the "pay and chase" model—recovering money after it has been stolen—is increasingly viewed as a secondary strategy to the more proactive goal of fraud prevention.
Supporting Data: The Scale of the Challenge
The statistical reality of MFCU operations reveals both the massive scale of the Medicaid program and the limitations of current enforcement metrics.
Caseloads and Outcomes
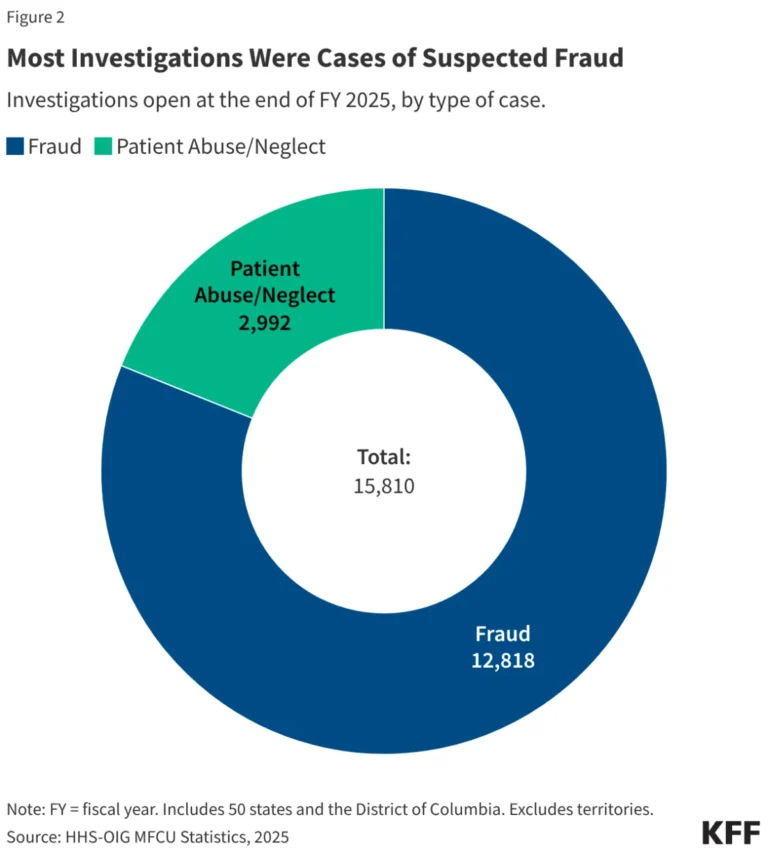
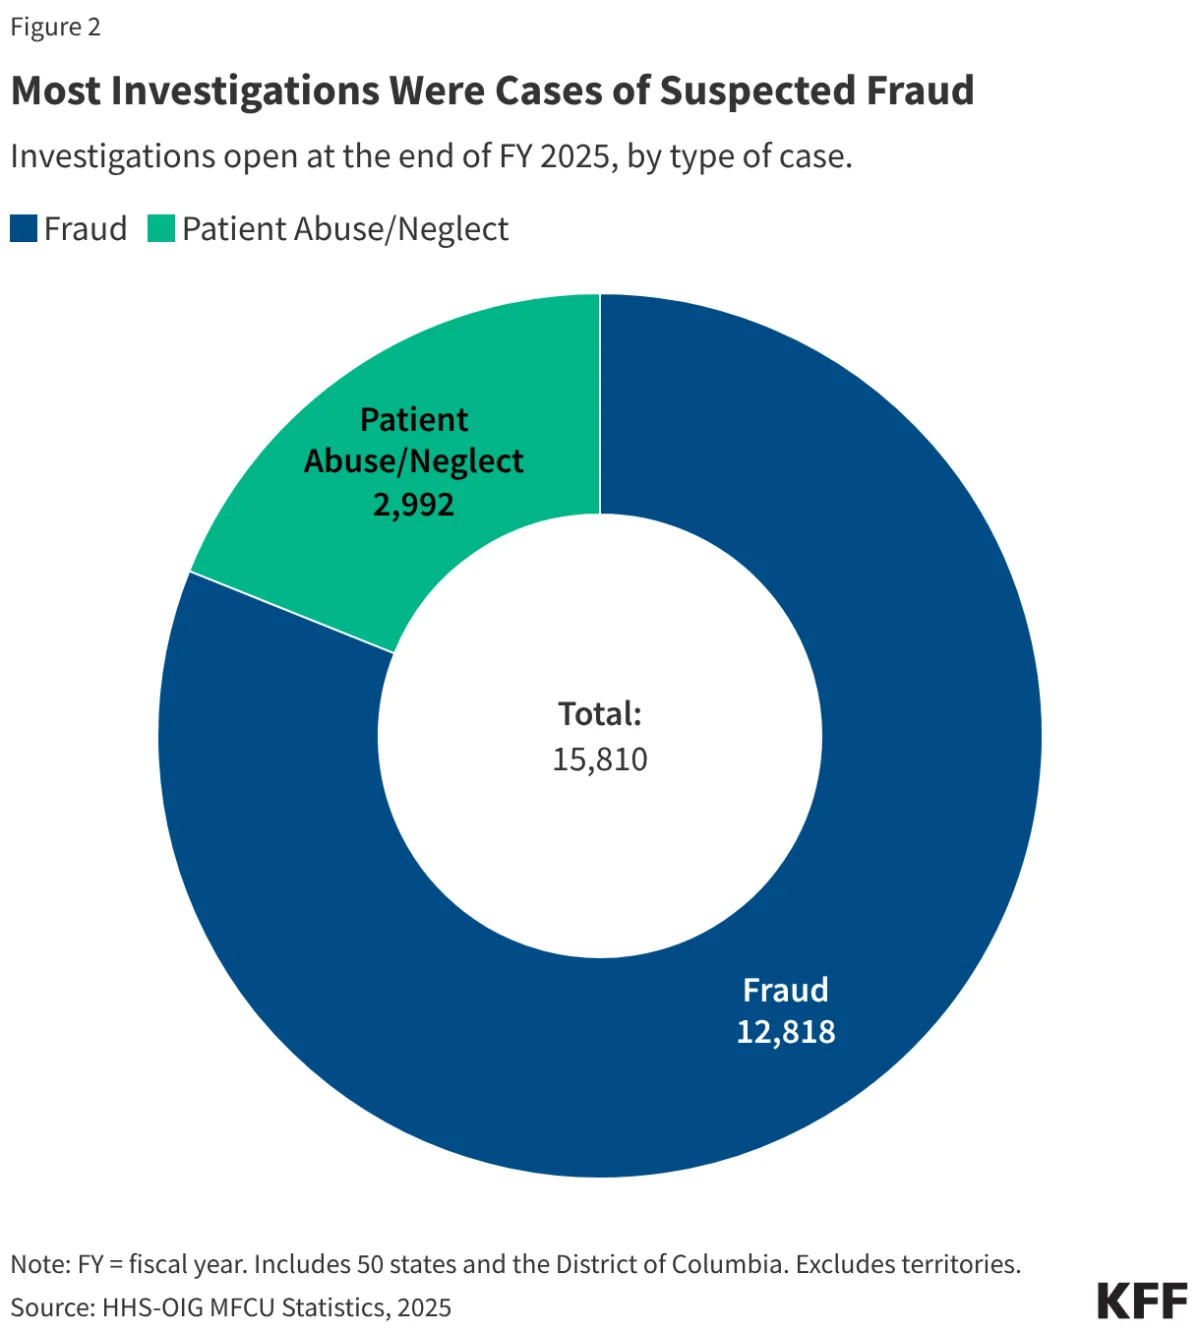
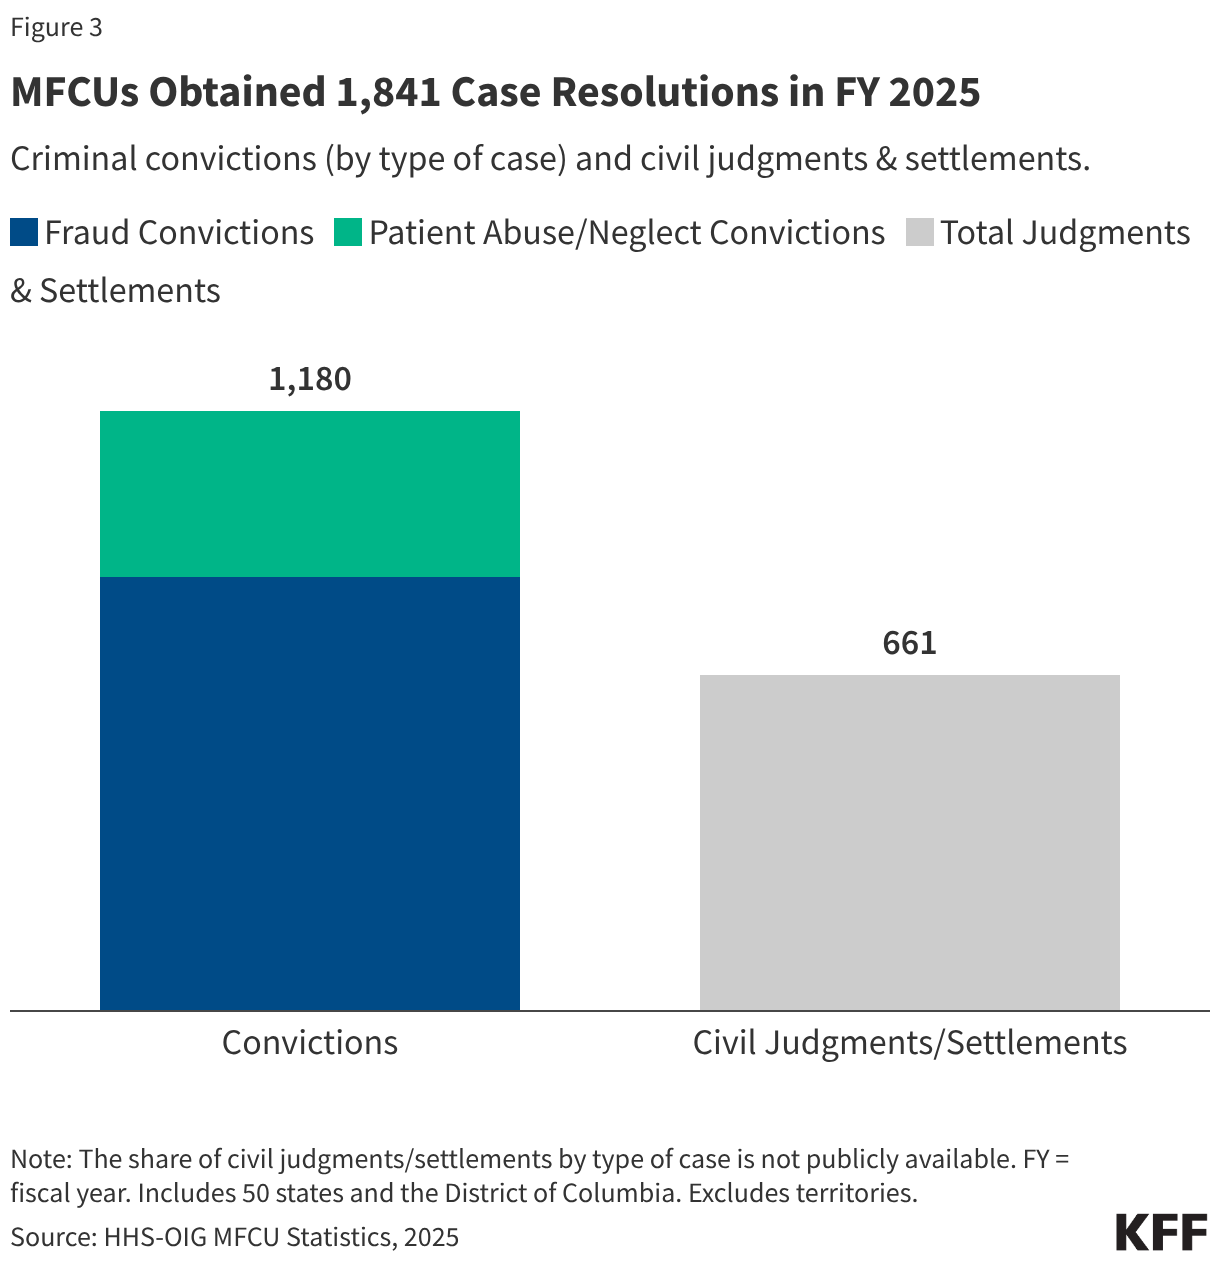
At the close of Fiscal Year 2025, there were over 15,800 active investigations nationwide. The vast majority of these focus on provider fraud. In that same fiscal year, MFCUs secured 1,180 criminal convictions and reached 661 civil settlements. These actions triggered 900 exclusions from federal programs, effectively barring bad actors from future participation in the healthcare system.
Financial Recoveries
Nationally, MFCUs recovered nearly $2 billion in FY 2025. While this figure is substantial, it represents only a fraction of total Medicaid spending. Economists and policy analysts note that comparing recovery dollars to total program spending is an imperfect "performance indicator." A state with very high recoveries might actually have a high rate of fraud, while a state with lower recoveries might be excelling at fraud prevention, thereby stopping the theft before the money leaves the treasury.
The "Rolling Average" Perspective
Over the last decade, recoveries have fluctuated, dipping during the COVID-19 pandemic as administrative focus shifted to emergency operations. While raw dollar amounts fluctuate, the five-year rolling average suggests that recoveries have remained relatively steady, even as overall Medicaid enrollment and total expenditures have seen significant growth. This disparity has fueled the current federal argument that enforcement efforts are not keeping pace with program expansion.
Official Responses and Political Friction
The denial of federal funding for the New York and Hawaii units has sparked a heated debate regarding federal overreach versus accountability.
The Federal Position: The HHS-OIG maintains that its primary responsibility is the stewardship of federal tax dollars. In its denial letters, the office pointed to a lack of "meaningful outcomes." For Hawaii, the OIG noted that recoveries had failed to scale with the state’s massive Medicaid budget growth. For New York, the issue was an imbalance between the unit’s substantial operating budget and the relatively low number of criminal convictions produced.
The State Response: State officials have pushed back vigorously. New York’s Attorney General characterized the move as an aggressive, politically motivated attempt to slash funding for state-level oversight. Hawaii officials have opted for a more conciliatory, procedural route, filing for reconsideration and emphasizing their commitment to program integrity. Both states argue that raw conviction counts fail to account for the deterrent effect of active investigations, which cannot always be measured in dollars or indictments.
Implications: A Shifting Regulatory Landscape
The current crisis surrounding MFCUs carries profound implications for the future of healthcare oversight in the United States.

1. The Death of "Pay and Chase"
The federal government is signaling a clear move away from merely recouping losses toward a model that prioritizes early detection and prevention. By waiving the data-mining approval requirement, the OIG is empowering states to use real-time analytics to stop fraud before payment is even issued.
2. Increased Vulnerability for States
The suspension of federal funding for two major state programs serves as a warning shot. States that cannot demonstrate high-volume enforcement—or at least satisfy the OIG’s rigorous performance metrics—risk losing their federal subsidies. This could lead to a scenario where states with smaller budgets or less sophisticated data infrastructure are disproportionately penalized.
3. The Challenge of Uniformity
The "conditional recertification" process suggests that the OIG is moving toward a standardized, nationwide enforcement mandate. However, because state laws regarding fraud, patient abuse, and criminal procedure vary wildly, forcing a "one-size-fits-all" performance standard may be legally and operationally difficult.
4. Patient Safety vs. Financial Auditing
There is a lingering concern among patient advocacy groups that the focus on "recoveries" and "convictions" might overshadow the MFCUs’ other critical role: protecting patients from abuse and neglect. If MFCUs are judged primarily on their ability to generate revenue through settlements, investigators may feel pressured to prioritize high-dollar fraud cases over the more resource-intensive, lower-dollar, but deeply vital investigations into patient mistreatment.
Conclusion
The Medicaid Fraud Control Units stand at a crossroad. The drive for "program integrity" is an undeniably noble pursuit, essential for sustaining the public trust and the financial viability of the Medicaid program. However, as the federal government tightens the screws on these state-level entities, the risk of bureaucratic friction and diminished local autonomy grows.
Whether the current wave of oversight leads to a more efficient, high-tech, and proactive system of fraud prevention, or whether it simply creates a culture of defensive, metric-driven enforcement remains to be seen. What is clear is that for the thousands of investigators working in these units, the pressure to prove their worth has never been greater. As we move into 2027, the outcomes of the Hawaii and New York appeals, along with the fate of the "conditionally recertified" states, will likely define the future of how America protects its most critical healthcare investment.
About the Author