Updated: September 25, 2026
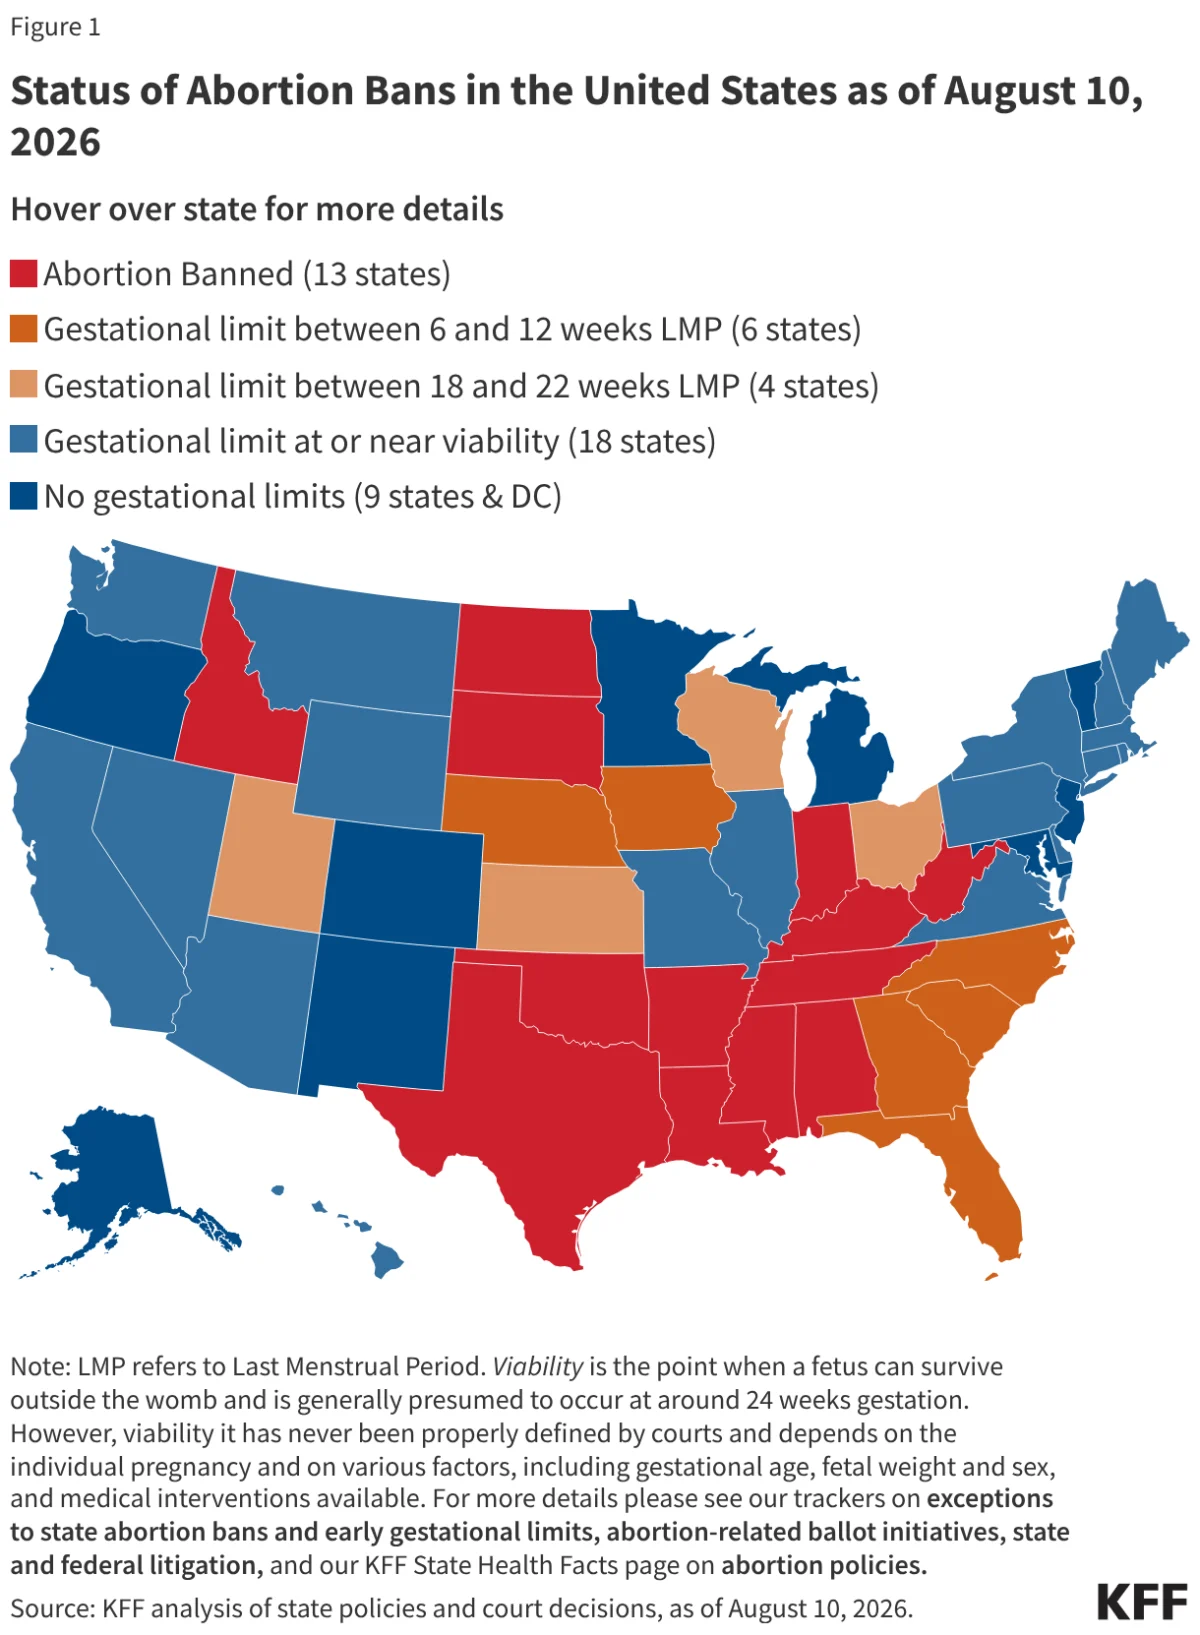
The landscape of reproductive healthcare in the United States has undergone a seismic shift since the Supreme Court’s 2022 decision in Dobbs v. Jackson Women’s Health Organization. By overturning Roe v. Wade, the Court effectively dismantled nearly 50 years of federal constitutional protection for abortion, granting individual states the authority to ban or strictly regulate the procedure from the moment of conception. As of late 2026, the U.S. remains a patchwork of starkly different legal realities, where a patient’s ability to access care is determined largely by their zip code.

Main Facts: The New Reality of Reproductive Care
Abortion remains a common, safe medical service, yet it is currently the most heavily regulated procedure in the American healthcare system. The Dobbs ruling ended the federal standard that previously permitted abortion up to the point of fetal viability—generally considered around 24 weeks of gestation.
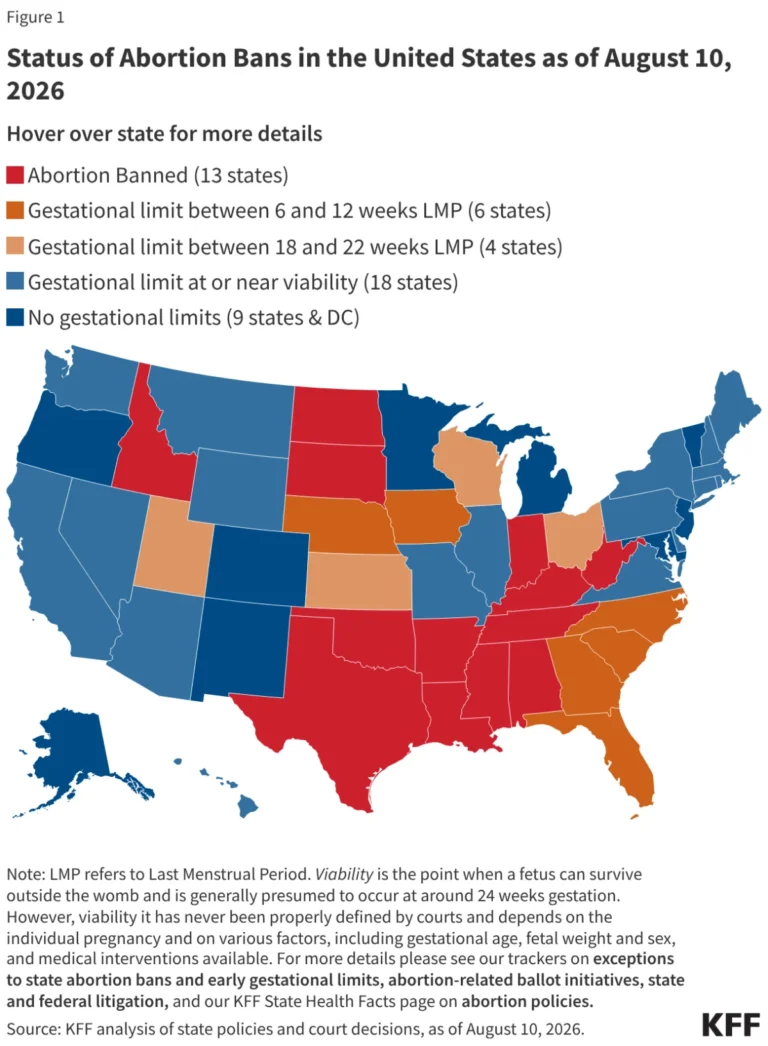
Today, the nation is divided. In 13 states, abortion is almost entirely banned, with only narrow, often unworkable exceptions for the life of the pregnant person. Conversely, other states have moved to enshrine protections for abortion access into their own laws. Amidst this legal volatility, the total number of abortions in the U.S. has not decreased; in fact, recent data indicates a paradoxical rise in the national volume of procedures. This increase is driven largely by the proliferation of telehealth services, the mailing of medication abortion pills, and the emergence of "shield laws" in states that protect clinicians who provide care to patients in restricted regions.
Chronology: From Federal Protection to State-Level Fragmentation
- 1973–2022: Under Roe v. Wade, states were prohibited from banning abortion before fetal viability, establishing a baseline of access across the country.
- June 24, 2022: The Supreme Court issues its ruling in Dobbs v. Jackson Women’s Health Organization, eliminating the federal constitutional right to abortion.
- Late 2022–2023: A wave of state-level bans and early gestational limits (6–12 weeks) takes effect. Clinic closures spike in the South and Midwest.
- December 2021–January 2023: The FDA updates its policies, permanently removing the in-person dispensing requirement for mifepristone and allowing retail pharmacies to dispense the medication, facilitating the expansion of telehealth.
- 2024–2026: A new, complex ecosystem emerges. While in-person clinic visits have declined in restricted states, telehealth-based medication abortions and interstate travel for care have surged, leading to a net increase in annual abortion volume despite stringent state-level prohibitions.
Supporting Data: Volume, Demographics, and Methodologies
Tracking abortion volume is a complex task involving the CDC, the Guttmacher Institute, and the Society for Family Planning. While the CDC has historically been the gold standard, its reporting is voluntary and often faces a two-to-three-year delay. Consequently, researchers now rely on monthly data from providers and clinics to capture real-time trends.
The Volume Paradox
In 2025, there were an estimated 1,129,020 abortions in the United States. Following the Dobbs decision, the monthly average of abortions has trended upward:
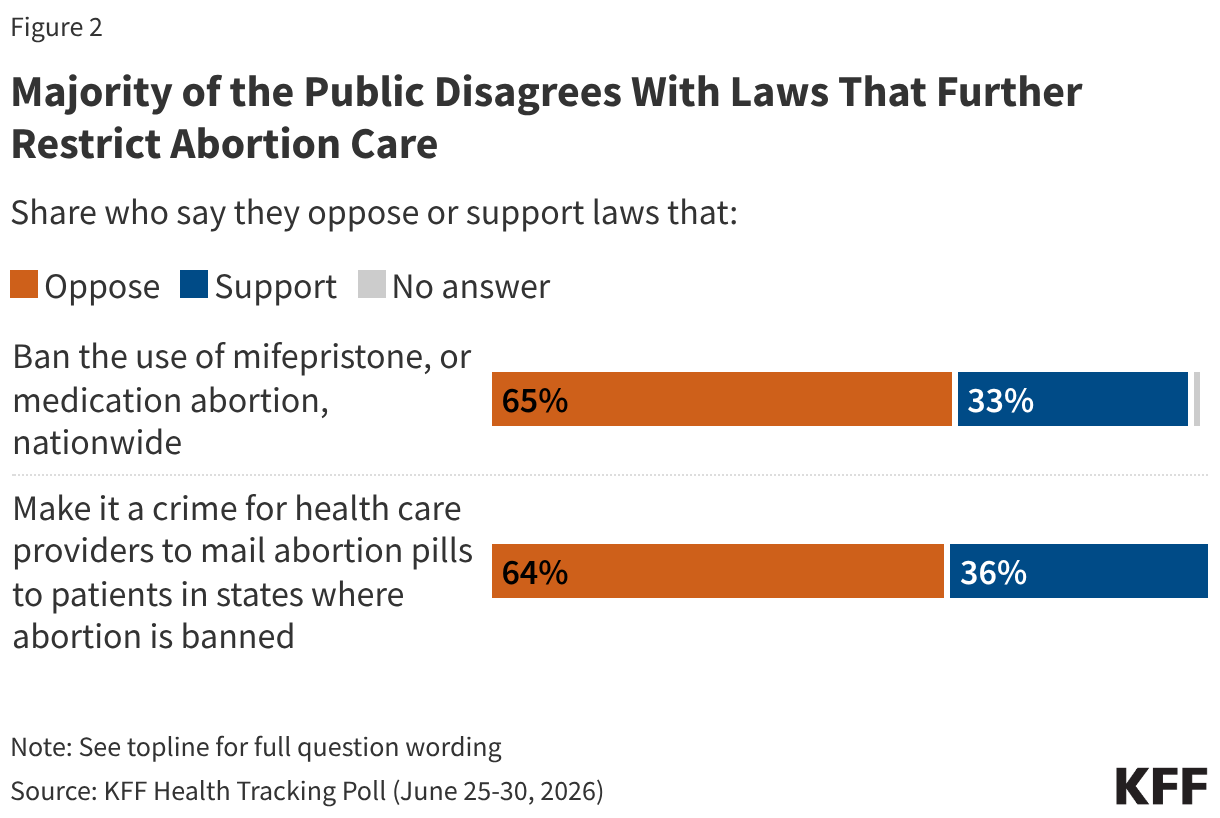
- 2022 (April–Dec): 77,560 per month
- 2023: 85,780 per month
- 2024: 92,400 per month
- 2025: 94,090 per month
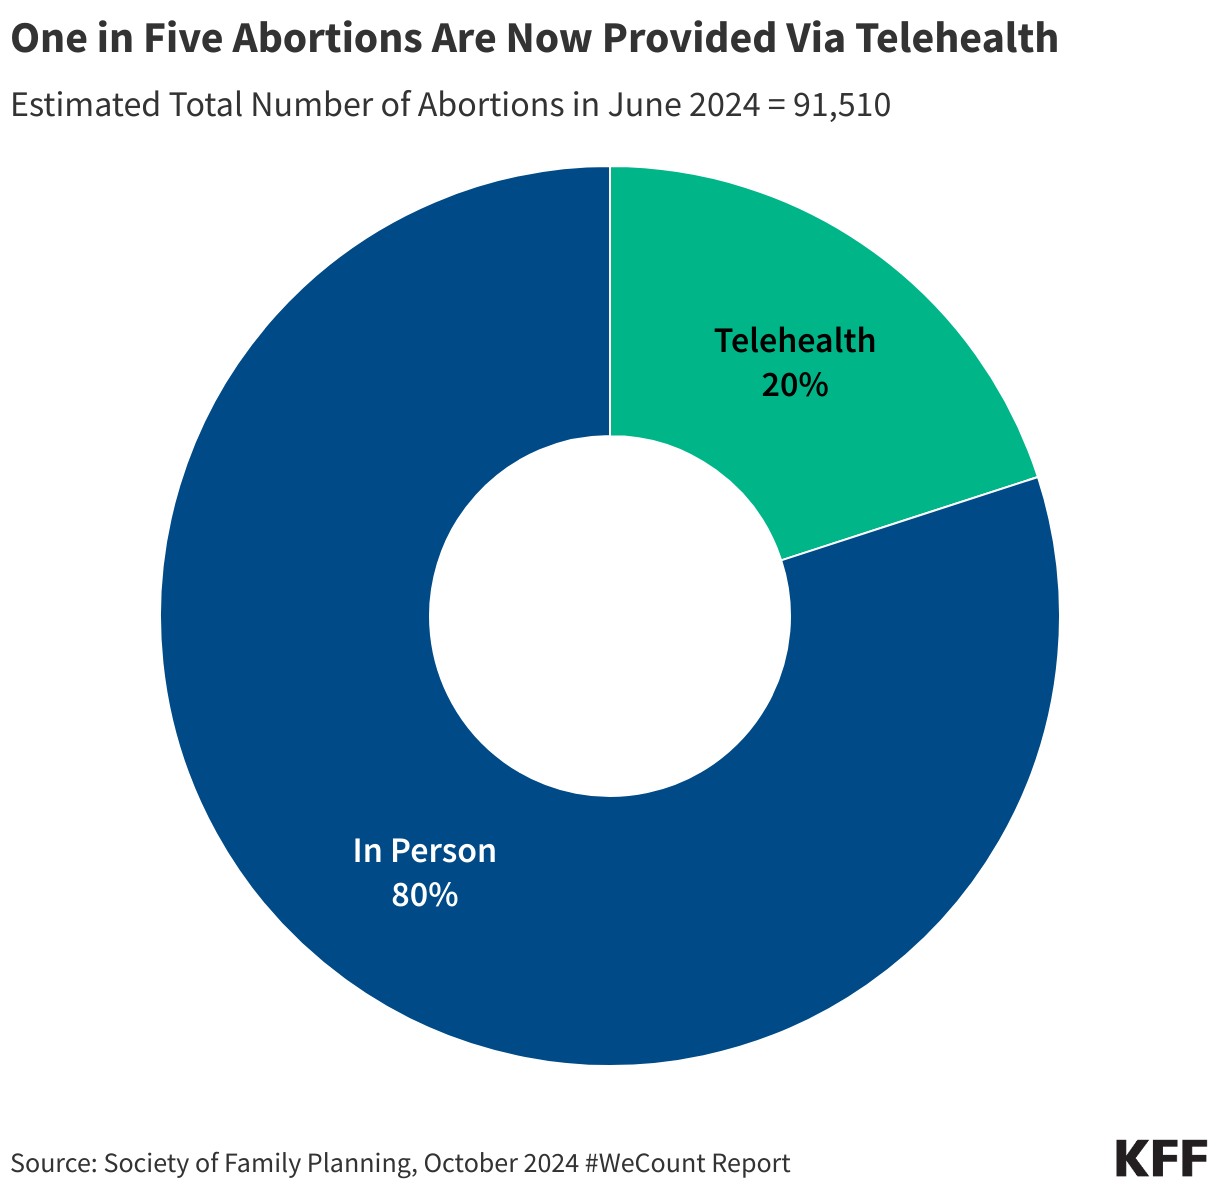
This growth is primarily attributed to the expansion of virtual clinics and medication abortion. Telehealth now accounts for roughly 28% of all abortions in the U.S.
Patient Demographics and Timing
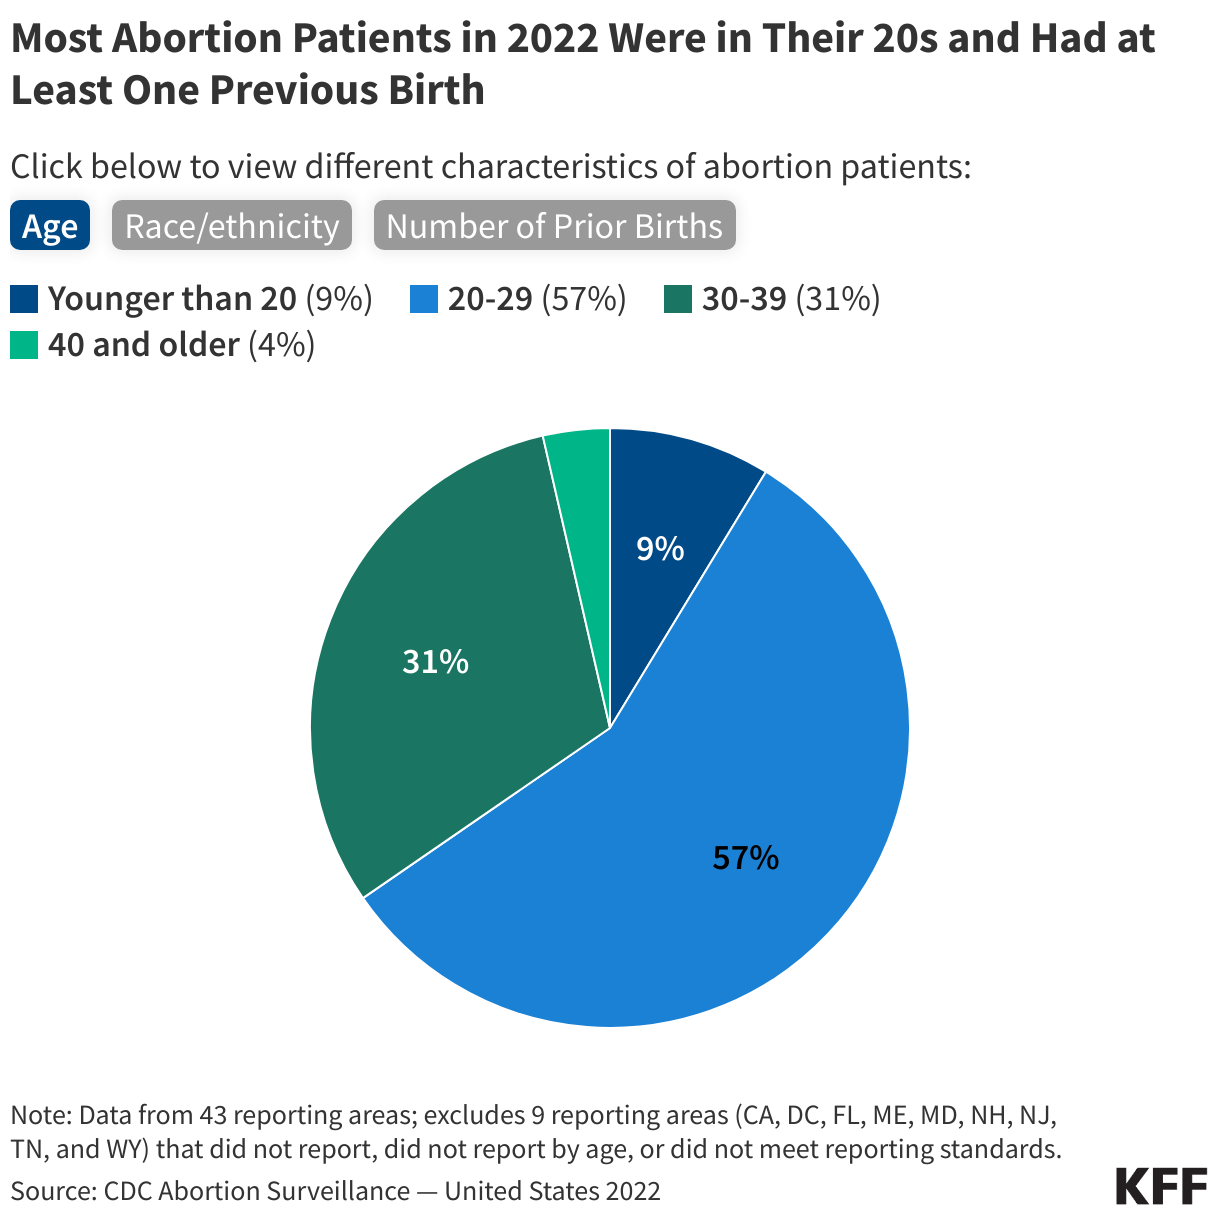
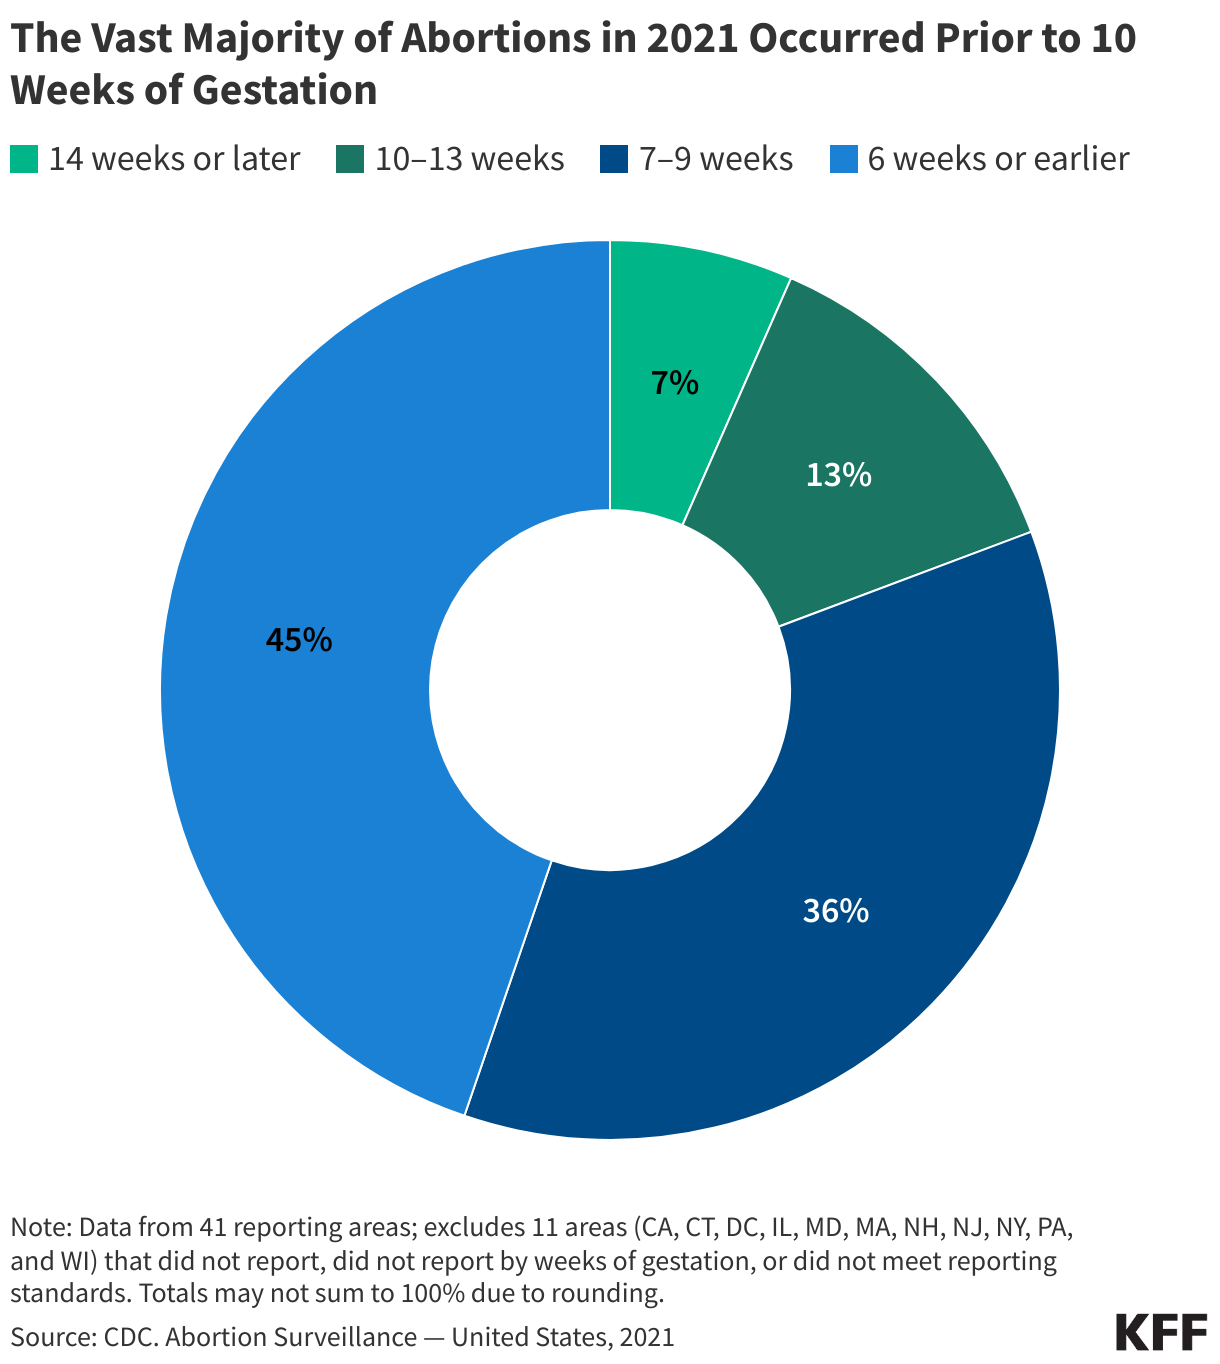
Data from 2022 reveals that the majority of those seeking abortions are in their twenties, low-income, and women of color. Notably, 93% of abortions occur during the first trimester. Of those, 40% occur at or before six weeks of gestation, and another 39% occur between seven and nine weeks. The common narrative that many abortions occur late in pregnancy is not supported by data; only 7% of abortions happen after the first trimester, and in those instances, the procedures are almost exclusively linked to lethal fetal anomalies or severe risks to the pregnant person’s life.
Official Responses and Policy Implications
The legislative reaction to the Dobbs ruling has been characterized by sharp partisan polarization.
Exceptions and Their Limitations
While all states that ban abortion include exceptions to save the life of the pregnant person, these have proven to be largely ineffective. Medical professionals often report that the legal ambiguity surrounding "life-threatening" conditions creates a chilling effect, where clinicians fear prosecution if they intervene too early or if their judgment is challenged by prosecutors. This leaves patients in dire medical straits, often forced to wait until their condition reaches a crisis point before receiving care.
Insurance and Financial Barriers
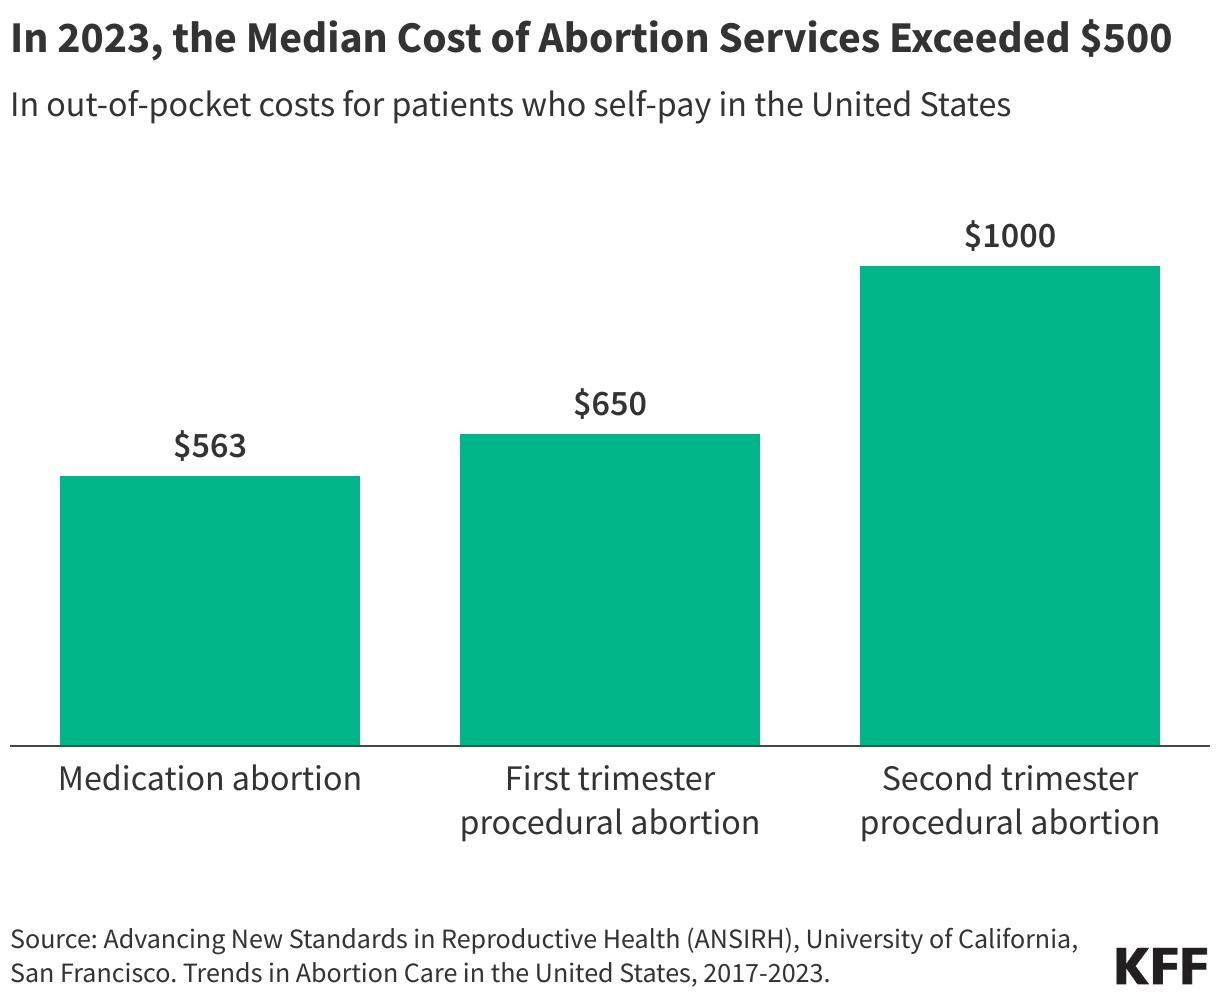
Financial access is an ongoing hurdle. While the median cost of an abortion can be as low as $40 through some virtual clinics, it can exceed $1,000 for procedures performed later in pregnancy. Insurance coverage remains fragmented due to the Hyde Amendment, which bars federal funds (Medicaid/Medicare) from covering abortions except in specific, limited circumstances. While 21 states use state-only funds to cover abortions for Medicaid enrollees, many others have restricted or entirely banned coverage in private insurance plans.
The Rise of Telehealth and Interstate Travel
The expansion of medication abortion via telehealth has acted as a critical safety valve. In 2024, approximately 155,000 patients traveled across state lines to access care—nearly double the number recorded in 2020. States like Illinois, New Mexico, and Kansas have become hubs for patients fleeing more restrictive neighbors. However, this travel imposes significant logistical and financial burdens, disproportionately affecting those with limited means.
Implications: A System Under Strain
The post-Dobbs era has revealed a system that is increasingly bifurcated. For those living in states with protective laws, access has been bolstered by the integration of telehealth and robust legal support. For those in states with bans, the situation is characterized by a "two-tier" system: those who can afford to travel or access medication through virtual channels, and those who remain stranded, potentially facing forced birth or seeking care outside the formal healthcare system.
The Regulatory Future
The legal battle over abortion is far from settled. With the FDA’s authority to approve and regulate mifepristone being challenged in various courts, the availability of medication abortion—the cornerstone of the current system—remains vulnerable to federal intervention.
Furthermore, the surge in self-managed abortions, where patients obtain pills without the direct involvement of a domestic clinician, poses new challenges for healthcare providers and public health officials. Because these services operate largely outside the formal health system, they are difficult to track, and the long-term public health implications remain a subject of active research.
Public Sentiment
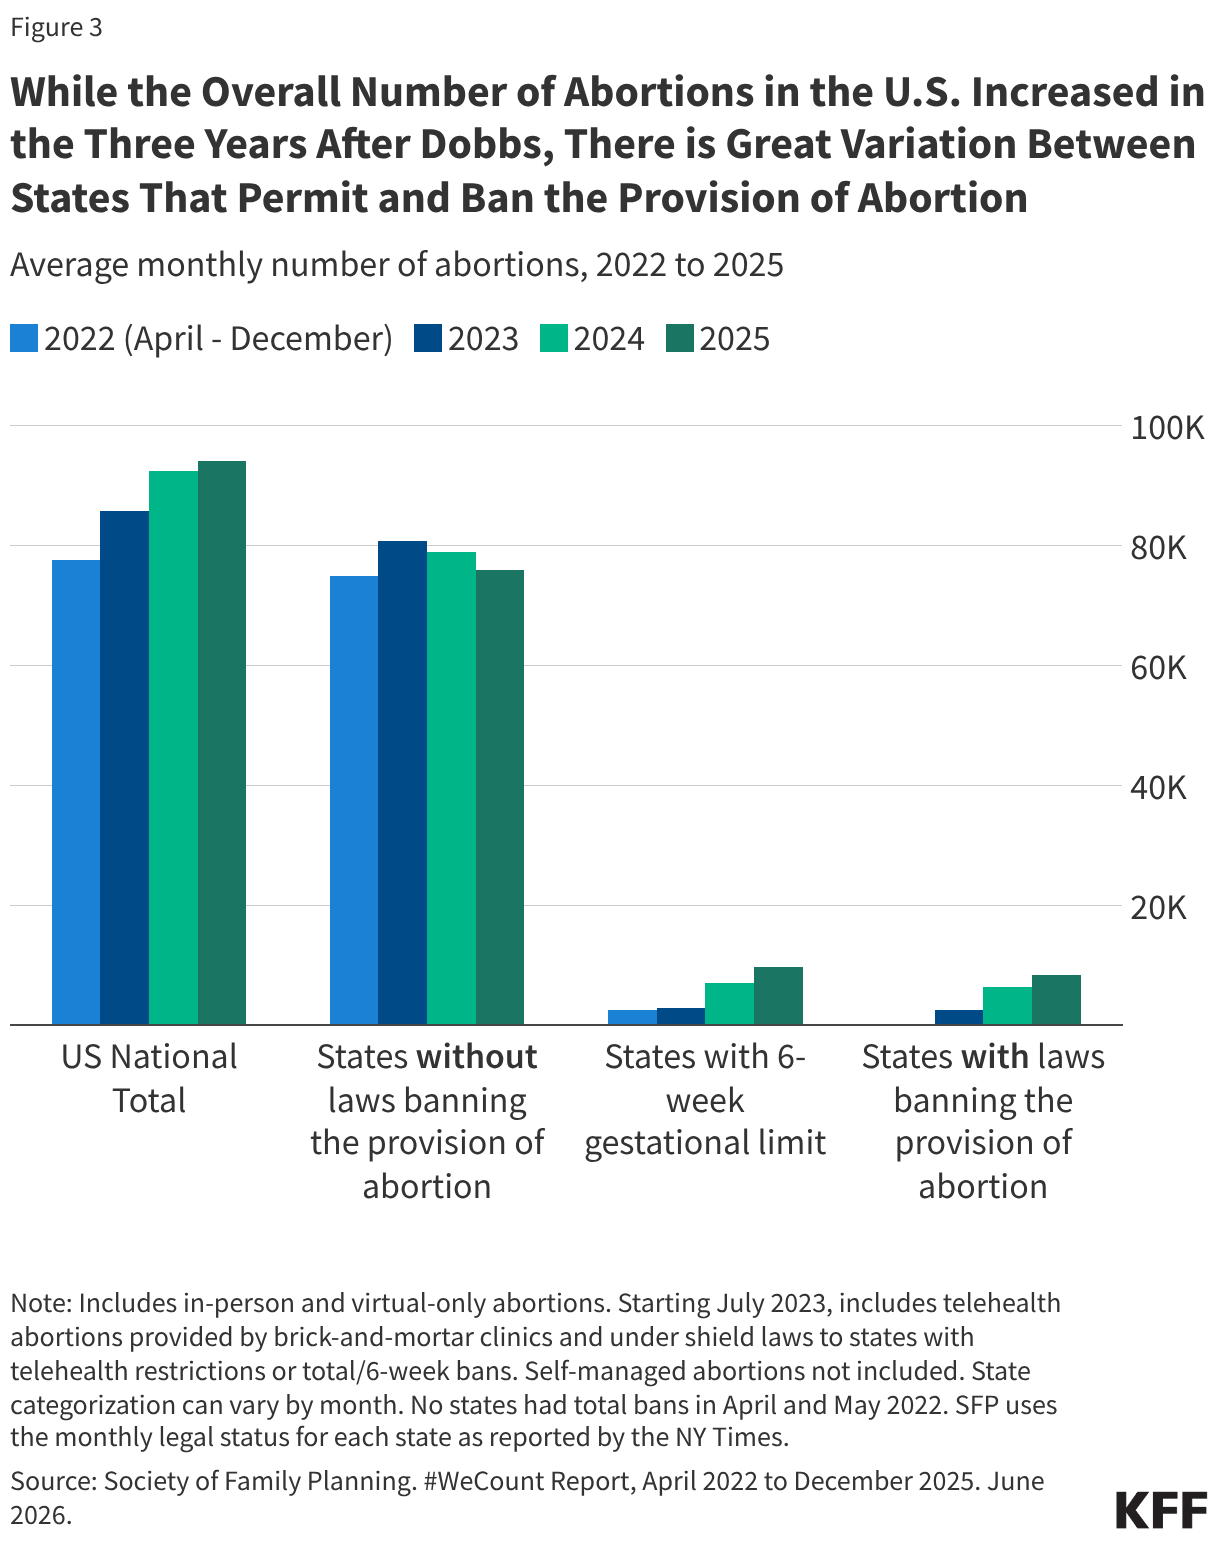
Despite the legislative trend toward restriction in many states, national public opinion remains firmly against the total criminalization of abortion. KFF polling consistently shows that a majority of the American public opposes the further restriction of abortion care, indicating a growing disconnect between state-level legislative actions and the preferences of the electorate.
In conclusion, the U.S. has entered a period of profound uncertainty regarding reproductive rights. While the Dobbs decision was intended to shift the authority of abortion policy to the states, it has instead created a national health crisis defined by uneven access, legal jeopardy for providers, and an increasing reliance on a decentralized, digital network of care that remains under constant political and judicial threat. As we look toward the remainder of 2026 and beyond, the resilience of the U.S. healthcare system in the face of these challenges will be tested as never before.
About the Author