Despite the existence of highly effective, curative therapies for over a decade, Hepatitis C virus (HCV) remains a stubborn public health crisis. In 2023 alone, an estimated 69,000 Americans contracted the virus—a figure roughly double the infection rates observed in the mid-2010s. While medical science has evolved from the era of grueling, low-success interferon injections to the age of rapid-acting oral antivirals, the gap between clinical efficacy and real-world eradication is widening.
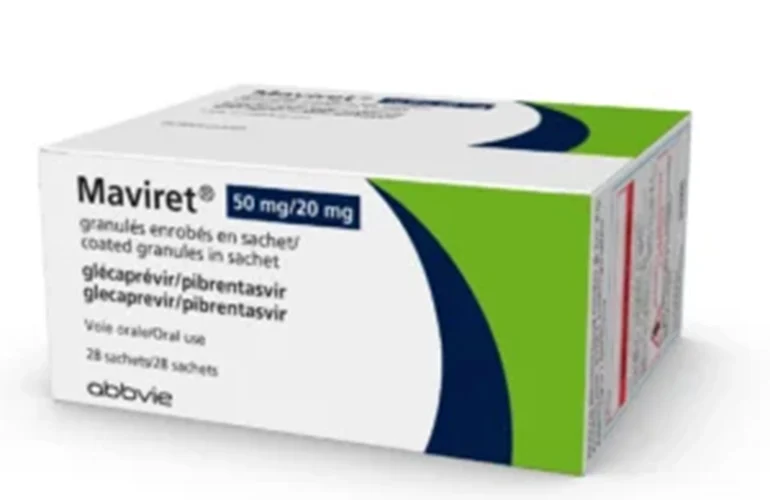
The recent label expansion of AbbVie’s Mavyret (glecaprevir/pibrentasvir)—now approved for acute HCV in both the United States and the European Union—represents a significant pharmacological victory. Yet, as the medical community celebrates a 96% cure rate in clinical trials, experts are increasingly sounding a cautionary note: medicine alone cannot solve a crisis deeply rooted in systemic healthcare access and social determinants of health.
The Evolution of HCV Treatment: A Chronology of Progress
The journey toward modern HCV management has been marked by a staggering leap in efficacy. For decades, clinicians relied on alpha-interferon injections, a grueling regimen that resulted in viral eradication for a mere 10% of patients.
- 1991: The FDA grants approval to the first alpha-interferon therapies, setting a low bar for cure rates that would persist for years.
- 2017: A watershed year for hepatology. The European Union and the FDA grant approval for AbbVie’s Mavyret, a direct-acting antiviral (DAA) capable of treating chronic HCV across all major genotypes (GT 1–6) in as little as eight weeks.
- 2025 (June): The FDA approves a critical label expansion for Mavyret, allowing its use for acute HCV infections. This marks the first time an antiviral has been officially cleared for early-stage intervention, removing the bureaucratic hurdle of waiting for an infection to become "chronic" before treating it.
- 2026 (June): The European Commission follows suit, granting the same acute-indication approval for MAVIRET in the EU, standardizing the approach to early intervention across major global markets.
Supporting Data: Efficacy vs. Reality
The clinical profile of Mavyret is robust. In the Phase 3 trial supporting its acute-indication approval, the drug demonstrated a sustained virologic response (SVR) of 96.2% at 12 weeks in the intention-to-treat population. Perhaps more impressively, in the modified intention-to-treat group—which excluded non-virologic failures—the cure rate hit 100%. Remarkably, the study observed zero on-treatment virologic failures and no post-treatment relapses.
The Complexity of Reinfection
One of the most persistent concerns regarding HCV elimination is the potential for reinfection among high-risk populations, such as people who inject drugs (PWID) and individuals with high-frequency sexual exposure. The data from the Phase 3 trial provided a surprising and optimistic insight: prior infection history did not dampen the efficacy of the drug.
Among the study participants, nearly 18% were being treated for at least their second HCV infection, and 40% of that subset had battled the virus two or more times. Two participants had even experienced six prior infections. Despite this history, the SVR remained consistent.
However, the "real-world" context remains grim. Systematic reviews indicate that while the general population sees HCV reinfection rates of approximately 1.27 per 100 person-years, that number jumps to 5.9 per 100 person-years among individuals with recent drug use. These figures underscore a painful reality: treating the virus without addressing the environment of exposure is a cycle that cannot be broken by a pill alone.
Official Responses and Clinical Perspectives
The medical community views the recent label expansions as a powerful, albeit incomplete, tool. John Ward, director of the Coalition for Global Hepatitis Elimination, emphasizes that if patients are caught during the acute phase, the path to eradication is theoretically straightforward. "If treated early with safe and effective therapies, providers can cure virtually all patients with hepatitis C before it escalates to chronic disease," Ward noted in a press release.
Dr. Ivan Gentile, an infectious disease specialist at the University of Naples Federico II and a co-author of the trial, highlights that the shift in labeling serves a critical administrative function. Previously, clinicians were often forced to wait for evidence of chronicity before prescribing, a process that introduced unnecessary diagnostic delays. "That delay can add unnecessary visits, create administrative barriers and, most importantly, increase the risk that patients disengage from care," Gentile explained.
The "Engagement" Gap
Despite his optimism regarding the drug’s potency, Dr. Gentile remains cautious about how these trial results translate to the most vulnerable populations. "This study provides strong evidence of antiviral efficacy, but it does not fully answer the question of effectiveness in populations that are least engaged in care," he admitted.
In the clinical trial, 50% of participants were co-infected with HIV. Because they were already receiving antiretroviral therapy, they were—by definition—already connected to a stable healthcare system. Only 14.3% of the study group were people who currently or recently injected drugs. This demographic skew suggests that while the drug is chemically effective for everyone, it is practically inaccessible for the segments of the population most likely to spread the virus.
Implications for Public Health and Future Policy
The path forward, according to clinical experts, requires a paradigm shift in how we view "treatment." If the goal is the elimination of HCV, the medical community must stop treating the virus as a siloed clinical event and start viewing it as part of a broader social health ecosystem.
1. Integration with Harm Reduction
Antiviral treatment does not change the underlying exposure risks. Consequently, Dr. Gentile and other experts argue that repeat treatment must be integrated into comprehensive prevention strategies. This includes:
- Expansion of needle exchange and harm-reduction services.
- Increased access to substance-use disorder treatment.
- Routine, low-barrier sexual health interventions.
- Rapid-access HCV RNA testing in community centers rather than just hospitals.
2. Redefining "Success"
Public health policy must shift to view reinfection not as a failure of the patient or the drug, but as a systemic signal. Instead of withholding or delaying therapy for those at risk of reinfection, policy should favor "rapid retreatment." For the purposes of population-level elimination, treating someone who has been reinfected has the highest public health value, as it effectively removes a source of ongoing transmission from the community.
3. Closing the Data Gap
Current research is insufficient regarding those who are completely unconnected to the healthcare system. Future clinical studies must evolve to capture "real-world" metrics:
- The proportion of diagnosed individuals who actually start treatment.
- The time interval between initial diagnosis and the first dose.
- The rates of loss-to-follow-up in non-clinical settings.
- The speed and efficiency of retreatment after documented reinfection.
Conclusion
AbbVie’s Mavyret is undeniably a medical triumph, representing a decade of progress in antiviral pharmacology. The ability to cure a patient in weeks is a feat that would have seemed impossible in the 1990s. However, the rising tide of new infections proves that the "cure" is not the same as "elimination."
The challenge of the next decade will not be the drug’s efficacy, but the delivery of that efficacy to the people who need it most. By removing administrative barriers to acute treatment, the medical community has taken a vital step. Now, the burden of proof shifts to the healthcare system to ensure that these drugs reach the margins of society, where the cycle of transmission is most persistent. If the goal is to end Hepatitis C, we must ensure that the miracle of modern medicine is not kept behind the locked doors of the conventional, stable healthcare system, but is instead carried into the community with the same urgency as the disease itself.
About the Author