The landscape of American public health coverage has undergone a seismic shift since the onset of the COVID-19 pandemic. For three years, a federal "continuous enrollment" provision protected millions of Americans from losing their Medicaid coverage. However, the expiration of this policy triggered an unprecedented administrative undertaking known as the "unwinding," which saw states re-evaluate the eligibility of tens of millions of enrollees. As of late 2026, the dust has largely settled on this massive redetermination process, leaving policymakers and healthcare advocates to grapple with the long-term implications for access, equity, and fiscal sustainability.
Main Facts: The State of Medicaid/CHIP Enrollment
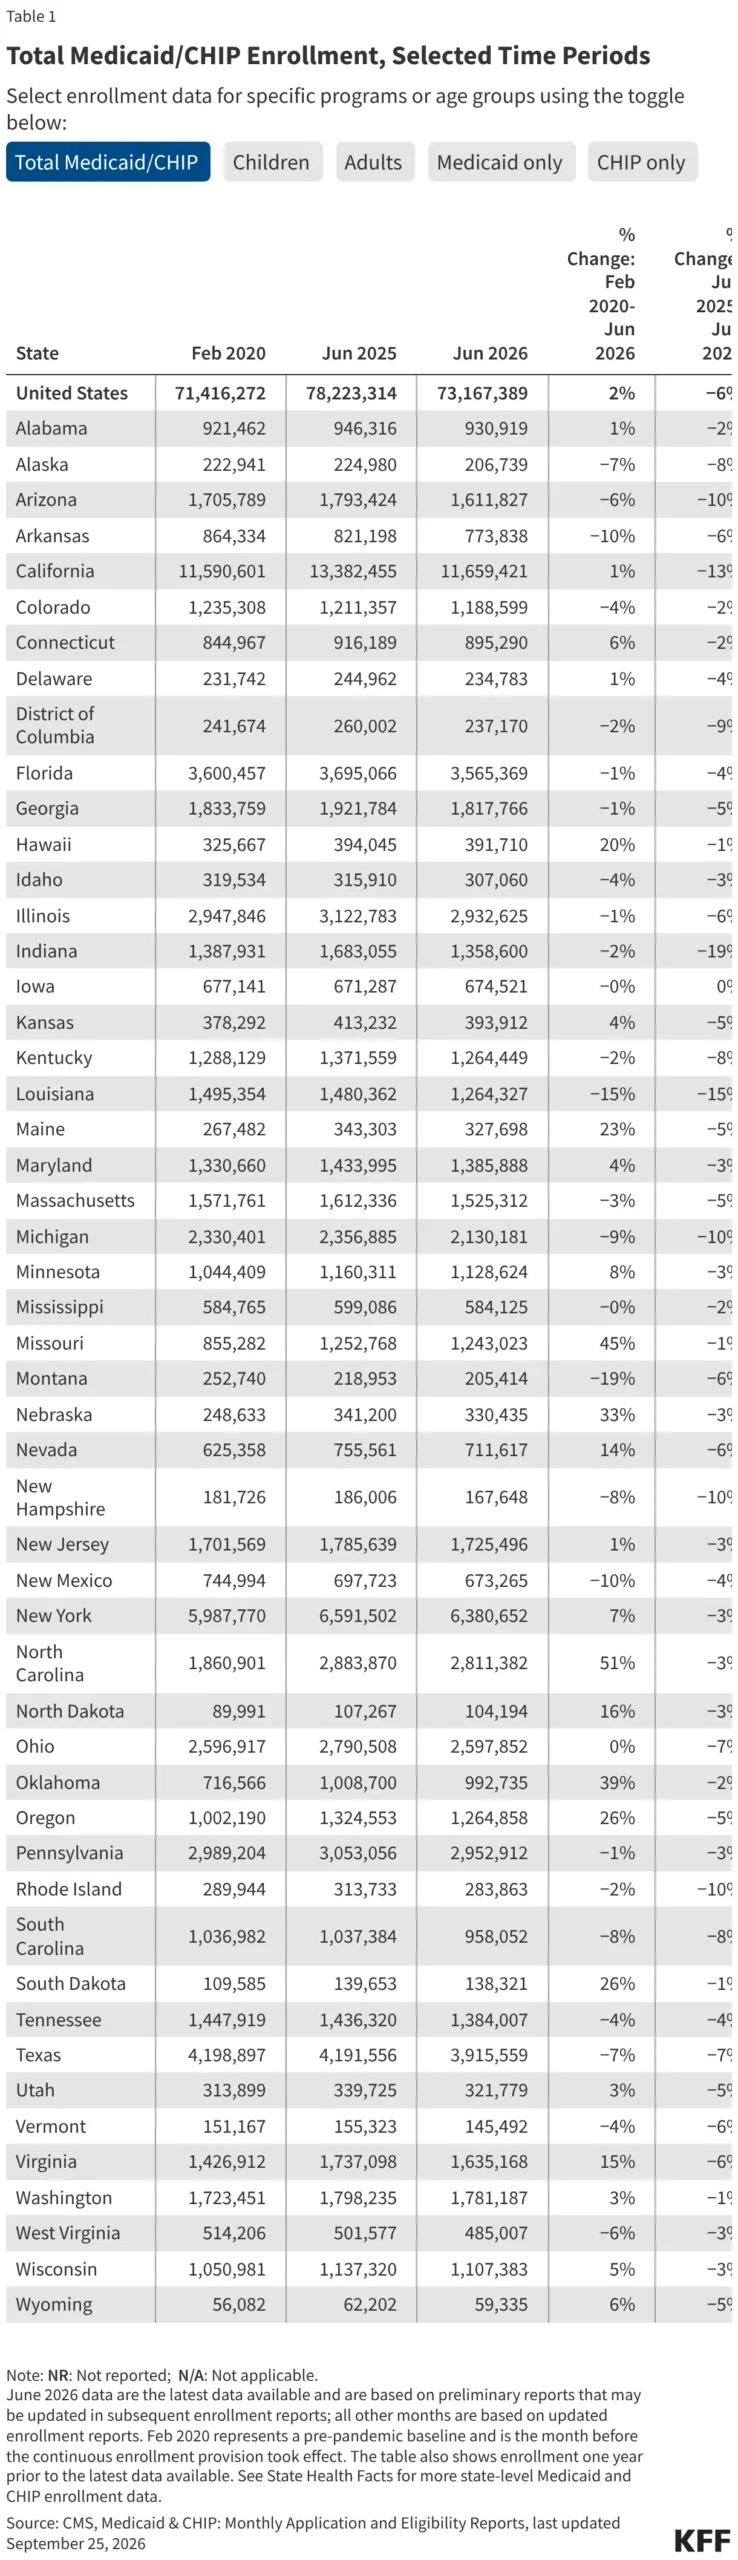
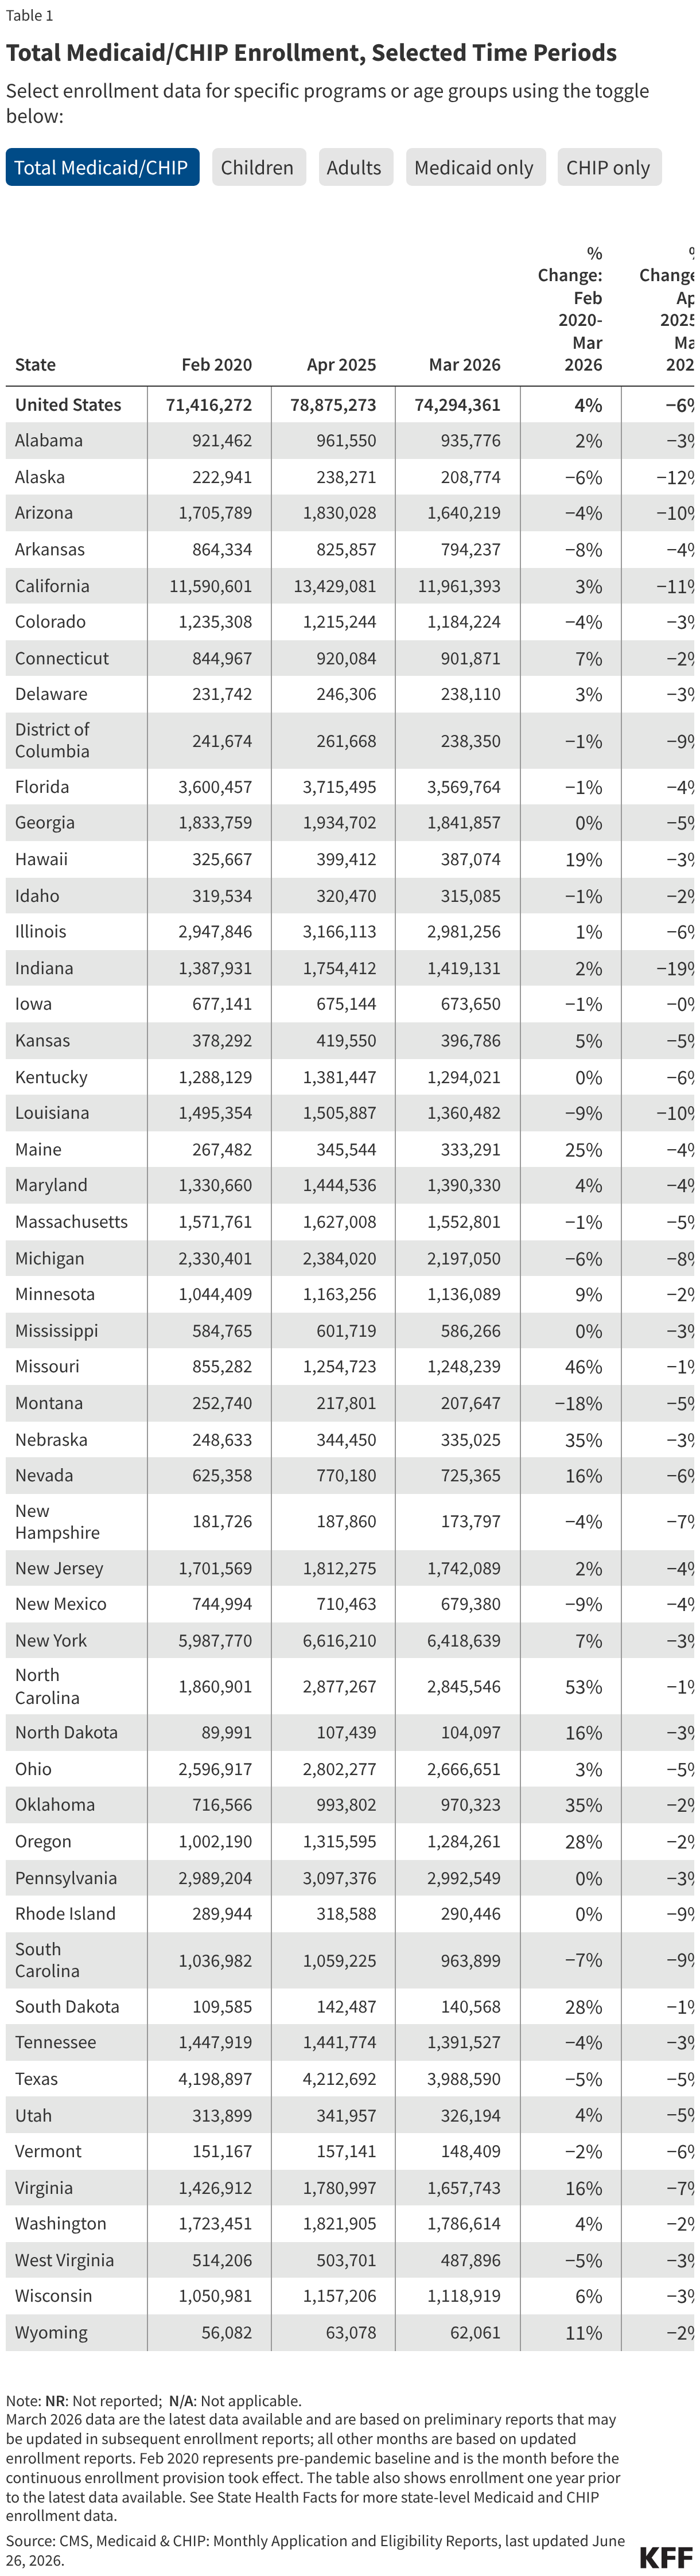
The most recent data from the Centers for Medicare & Medicaid Services (CMS) Performance Indicator Project, updated through June 2026, offers a sobering look at the current state of the Medicaid and Children’s Health Insurance Program (CHIP). While these programs remain the bedrock of the U.S. healthcare safety net, the numbers reflect a post-unwinding reality defined by significant churn and administrative complexity.
It is crucial to understand that these data represent "full-benefit" enrollees. They do not capture the entirety of the Medicaid population, as individuals receiving limited benefits—such as those enrolled exclusively for family planning services—are excluded. Consequently, while the data are invaluable for identifying broad trends, they do not provide a total census of the Medicaid population. Furthermore, these metrics are not currently configured to track enrollment changes by specific eligibility pathways, such as the Medicaid expansion group, limiting our ability to granularly analyze the impact of shifting eligibility rules on specific demographics.

Chronology: From Pandemic Protections to 2027 Policy Shifts
The timeline of Medicaid in the 2020s is defined by three distinct eras:
- The Continuous Enrollment Era (2020–2023): Triggered by the Families First Coronavirus Response Act, states were prohibited from disenrolling Medicaid beneficiaries in exchange for enhanced federal matching funds. This resulted in historic highs in enrollment, as millions who would have otherwise been cycled out of the program remained covered.
- The Unwinding (2023–2024): With the federal public health emergency declared over, states began the massive task of verifying eligibility for every enrollee. This phase, which dominated the landscape through much of 2024, saw tens of millions of individuals processed, with a heavy emphasis on "ex parte" renewals—the process of using existing data to renew coverage without requiring a beneficiary to submit new paperwork.
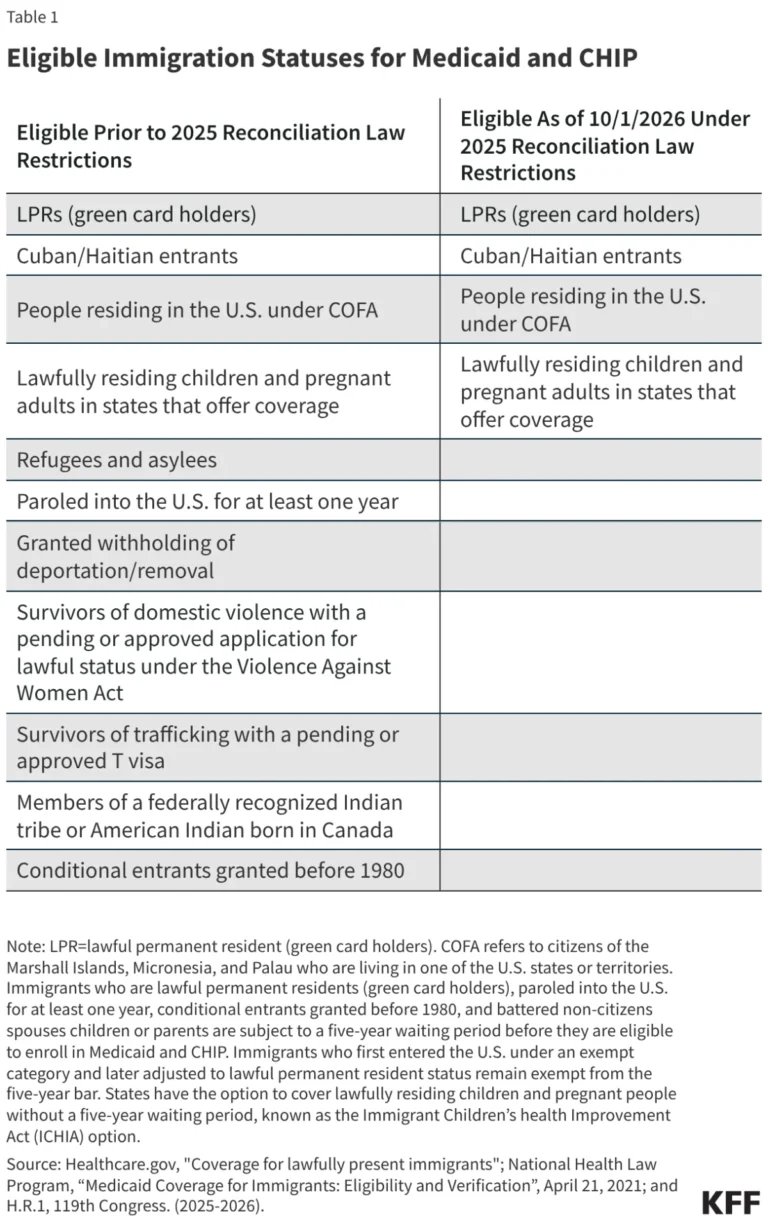
- The New Statutory Era (2025–2027): The 2025 federal budget reconciliation law introduced structural changes that are expected to redefine the program for the next decade. Notably, new work and reporting requirements for adults in the expansion group and certain 1115 waiver programs are set to take effect in January 2027. Experts anticipate that these mandates will contribute to a sustained, long-term reduction in enrollment compared to projections under prior law.
Supporting Data: Dissecting the Unwinding
The data collected during the unwinding process reveal profound disparities and administrative hurdles. By September 2024, when the vast majority of state-level unwinding had concluded, the scale of the transition was staggering.
The Scope of Disenrollment
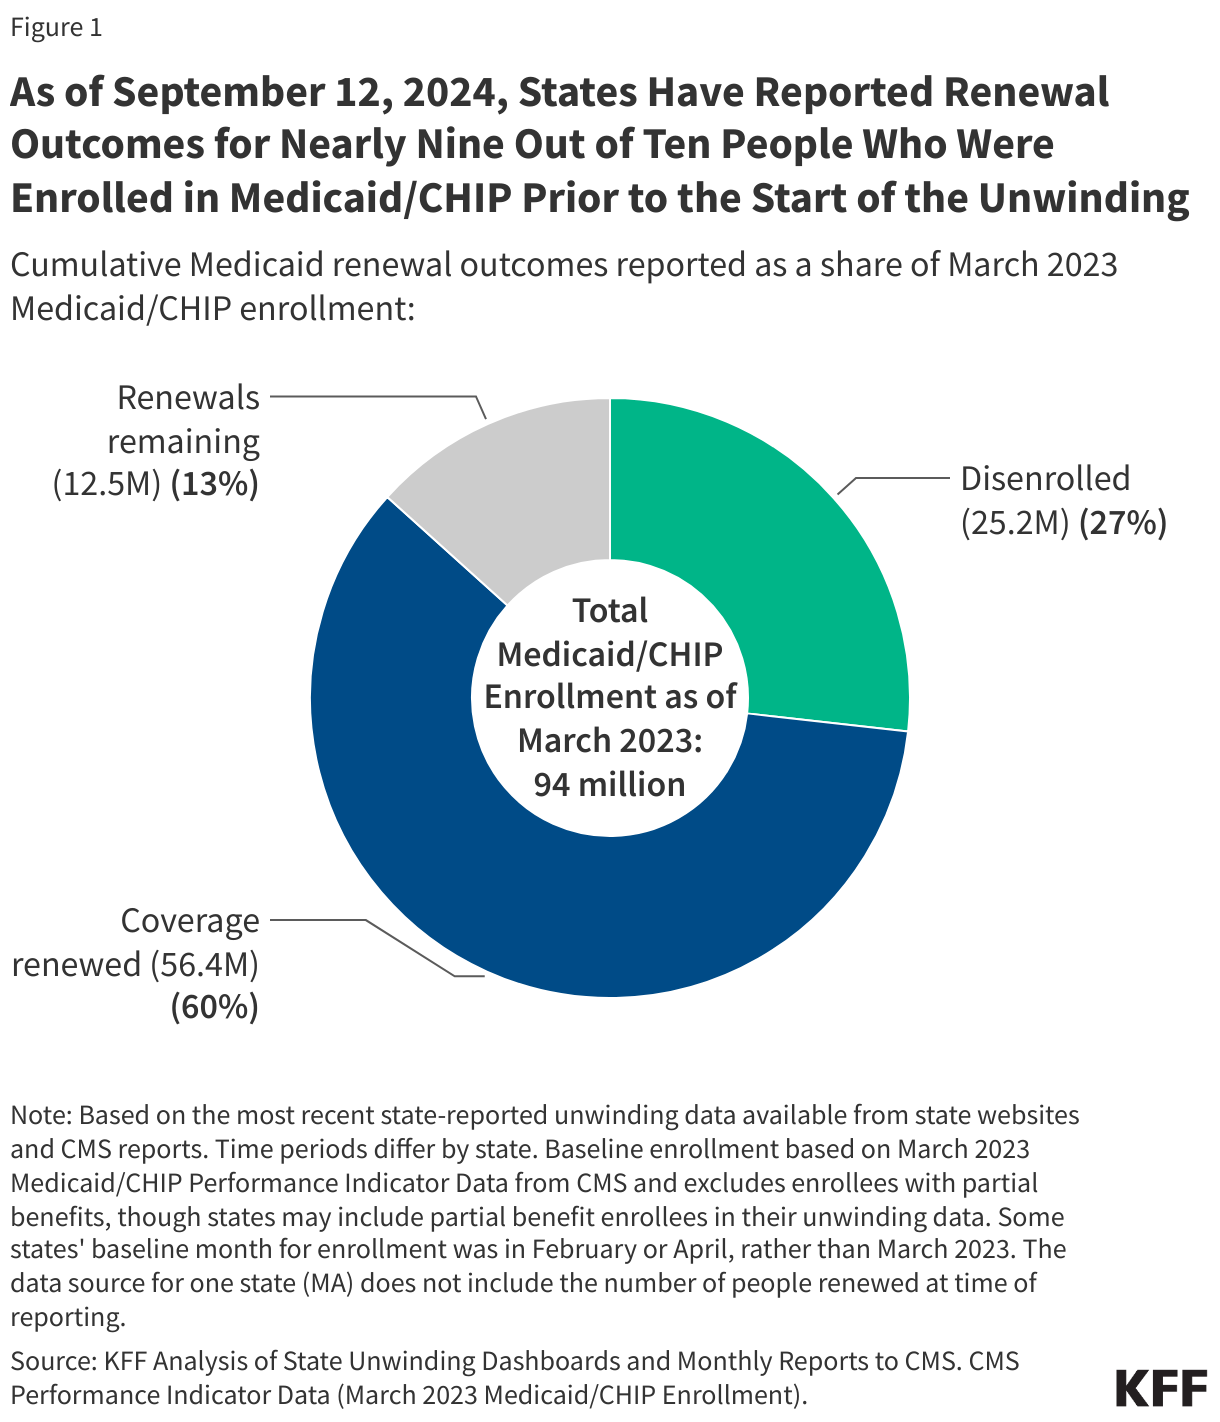
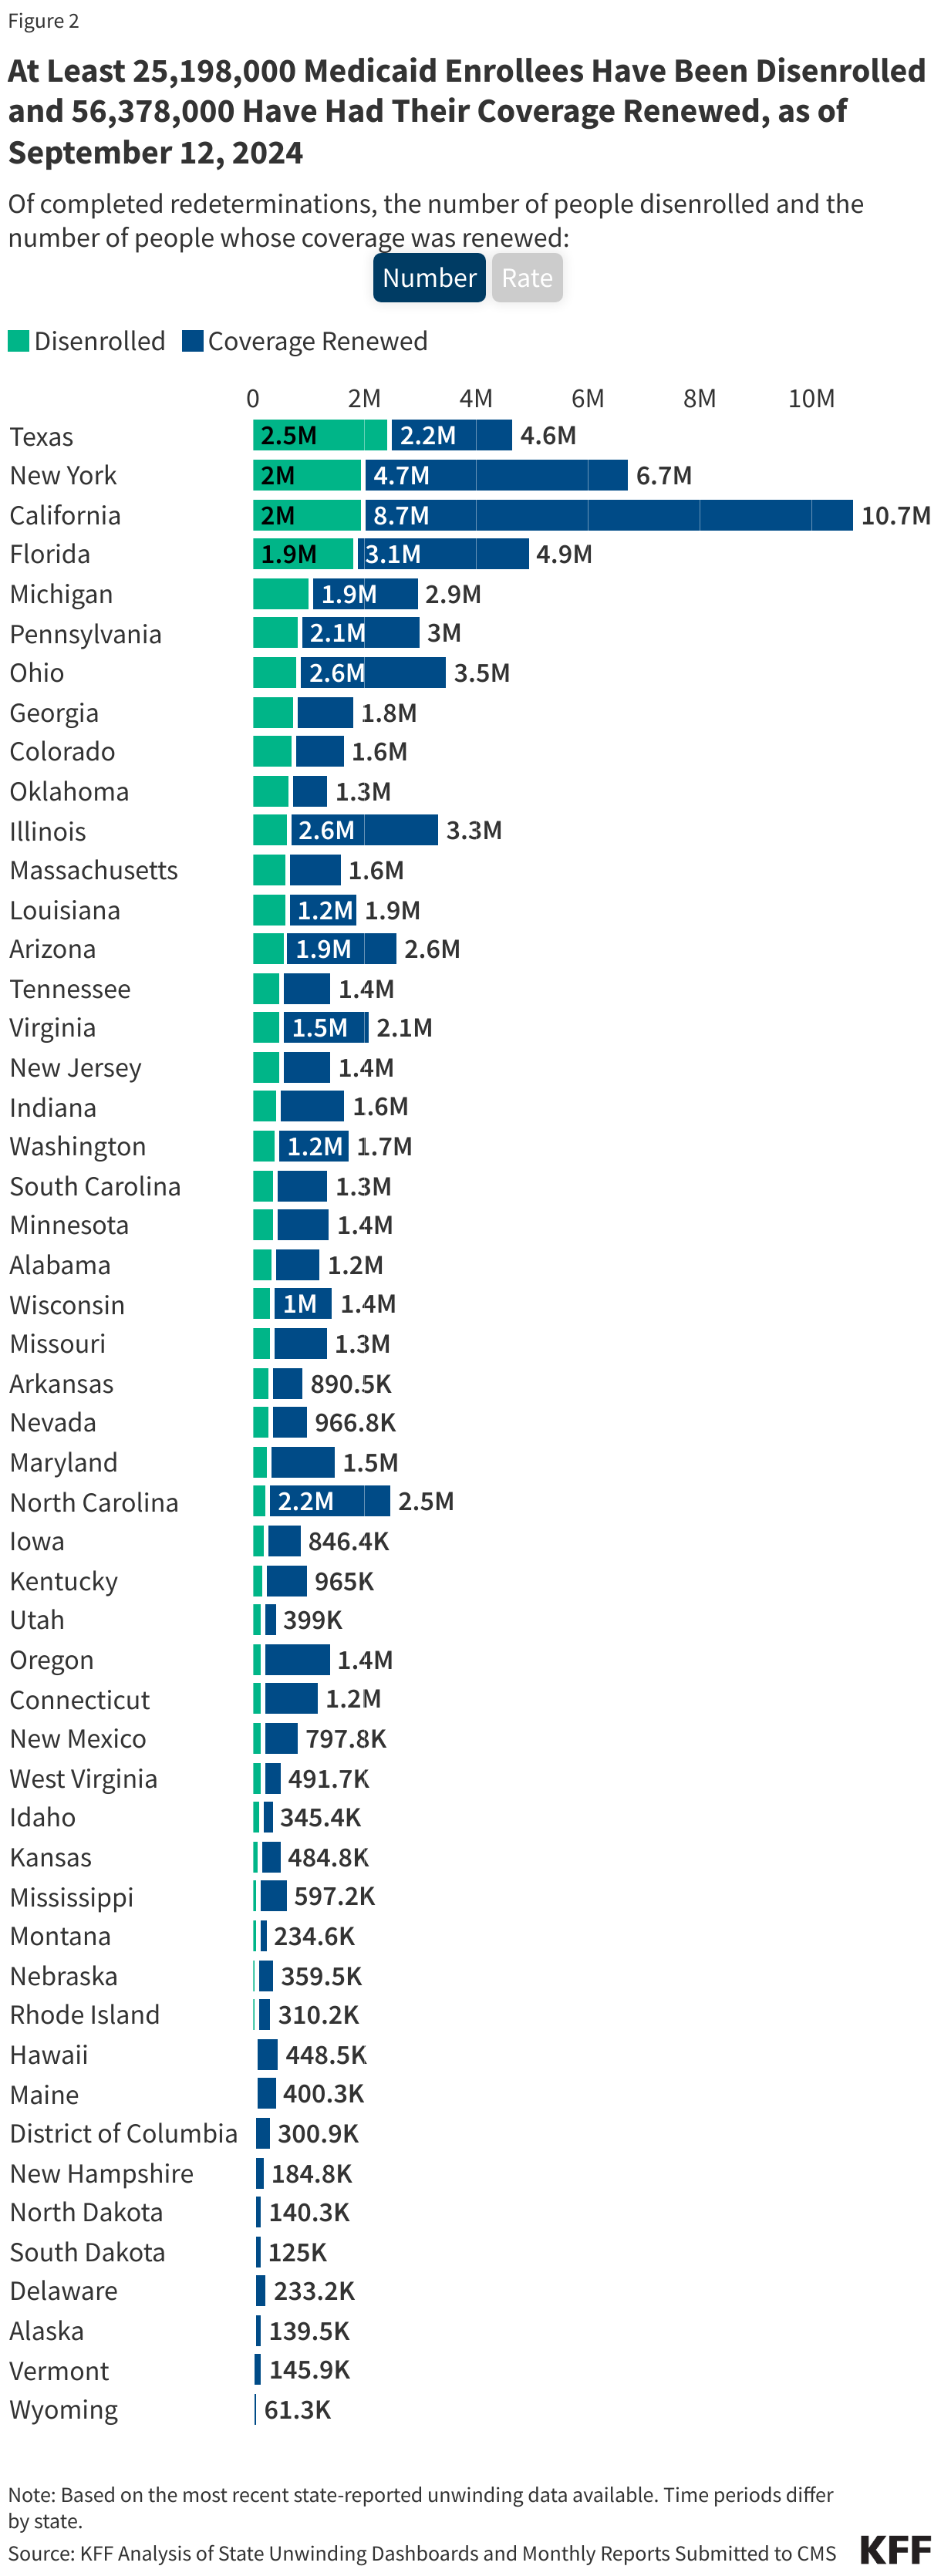
Nearly 90% of individuals who were enrolled in Medicaid/CHIP prior to the start of the unwinding had their status resolved. Out of the completed redeterminations, the numbers are stark: at least 25.2 million individuals were disenrolled from the program, while 56.4 million successfully had their coverage renewed.
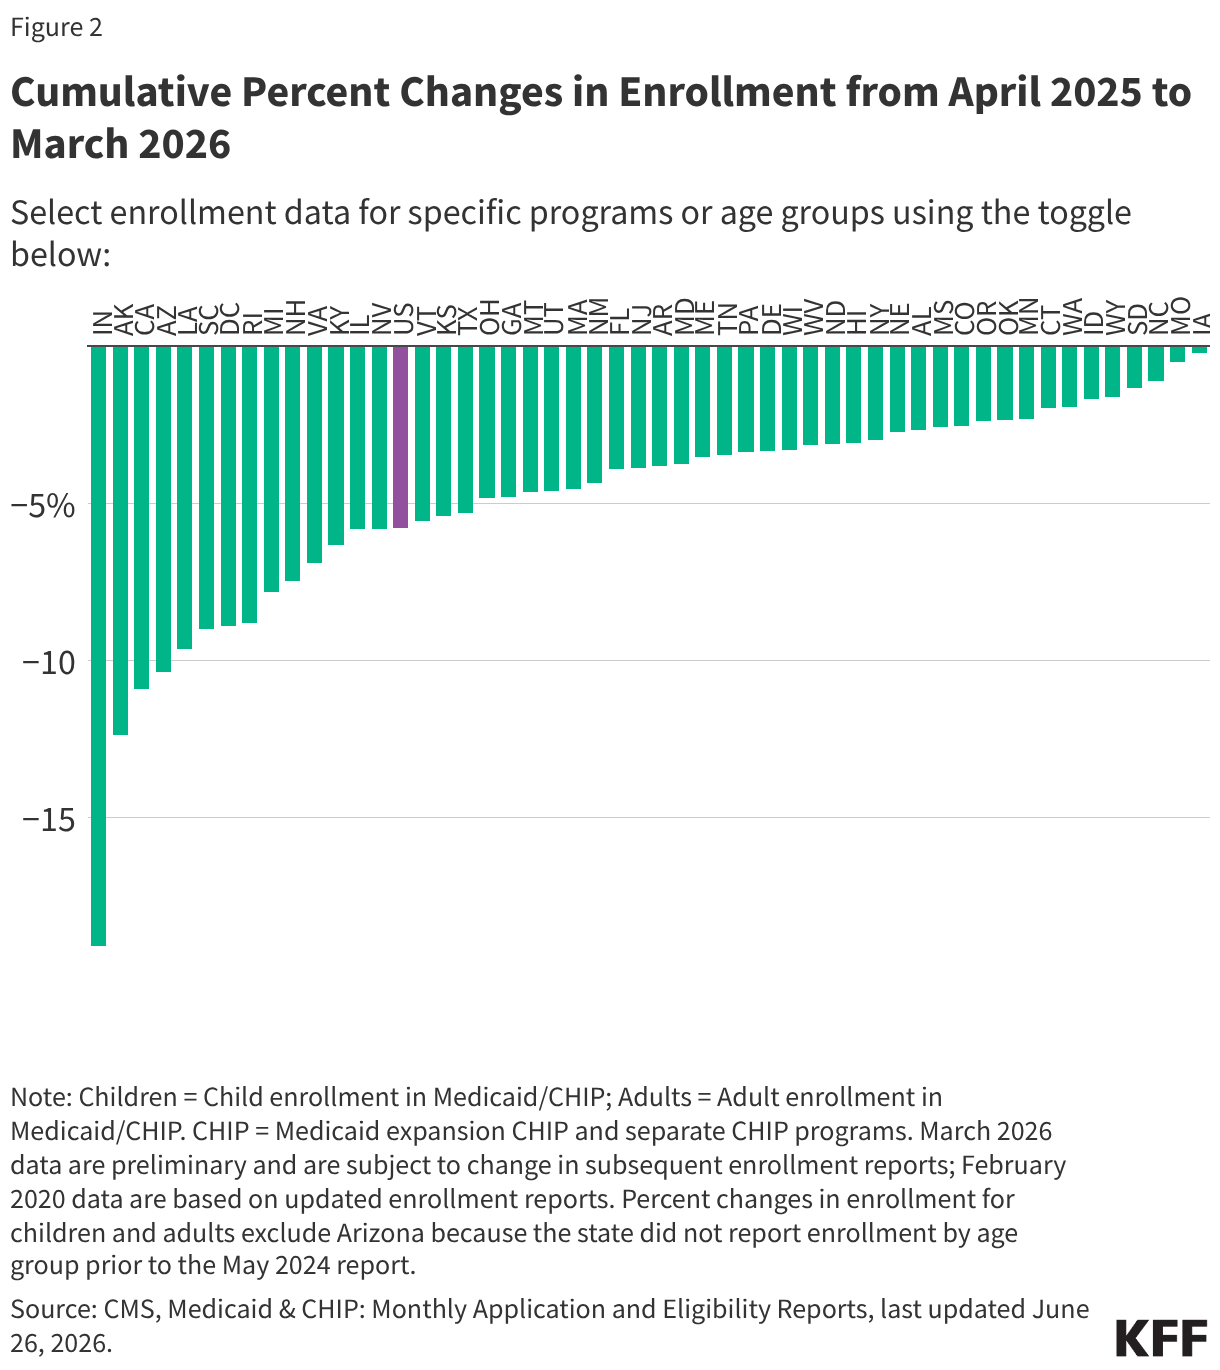
The variation between states remains a focal point of concern. Some states managed to retain the vast majority of their populations, while others saw disenrollment rates as high as 57%. This disparity is frequently attributed to differences in administrative capacity, the efficacy of outreach programs, and the stringency of state-level verification processes.
The "Procedural" Problem
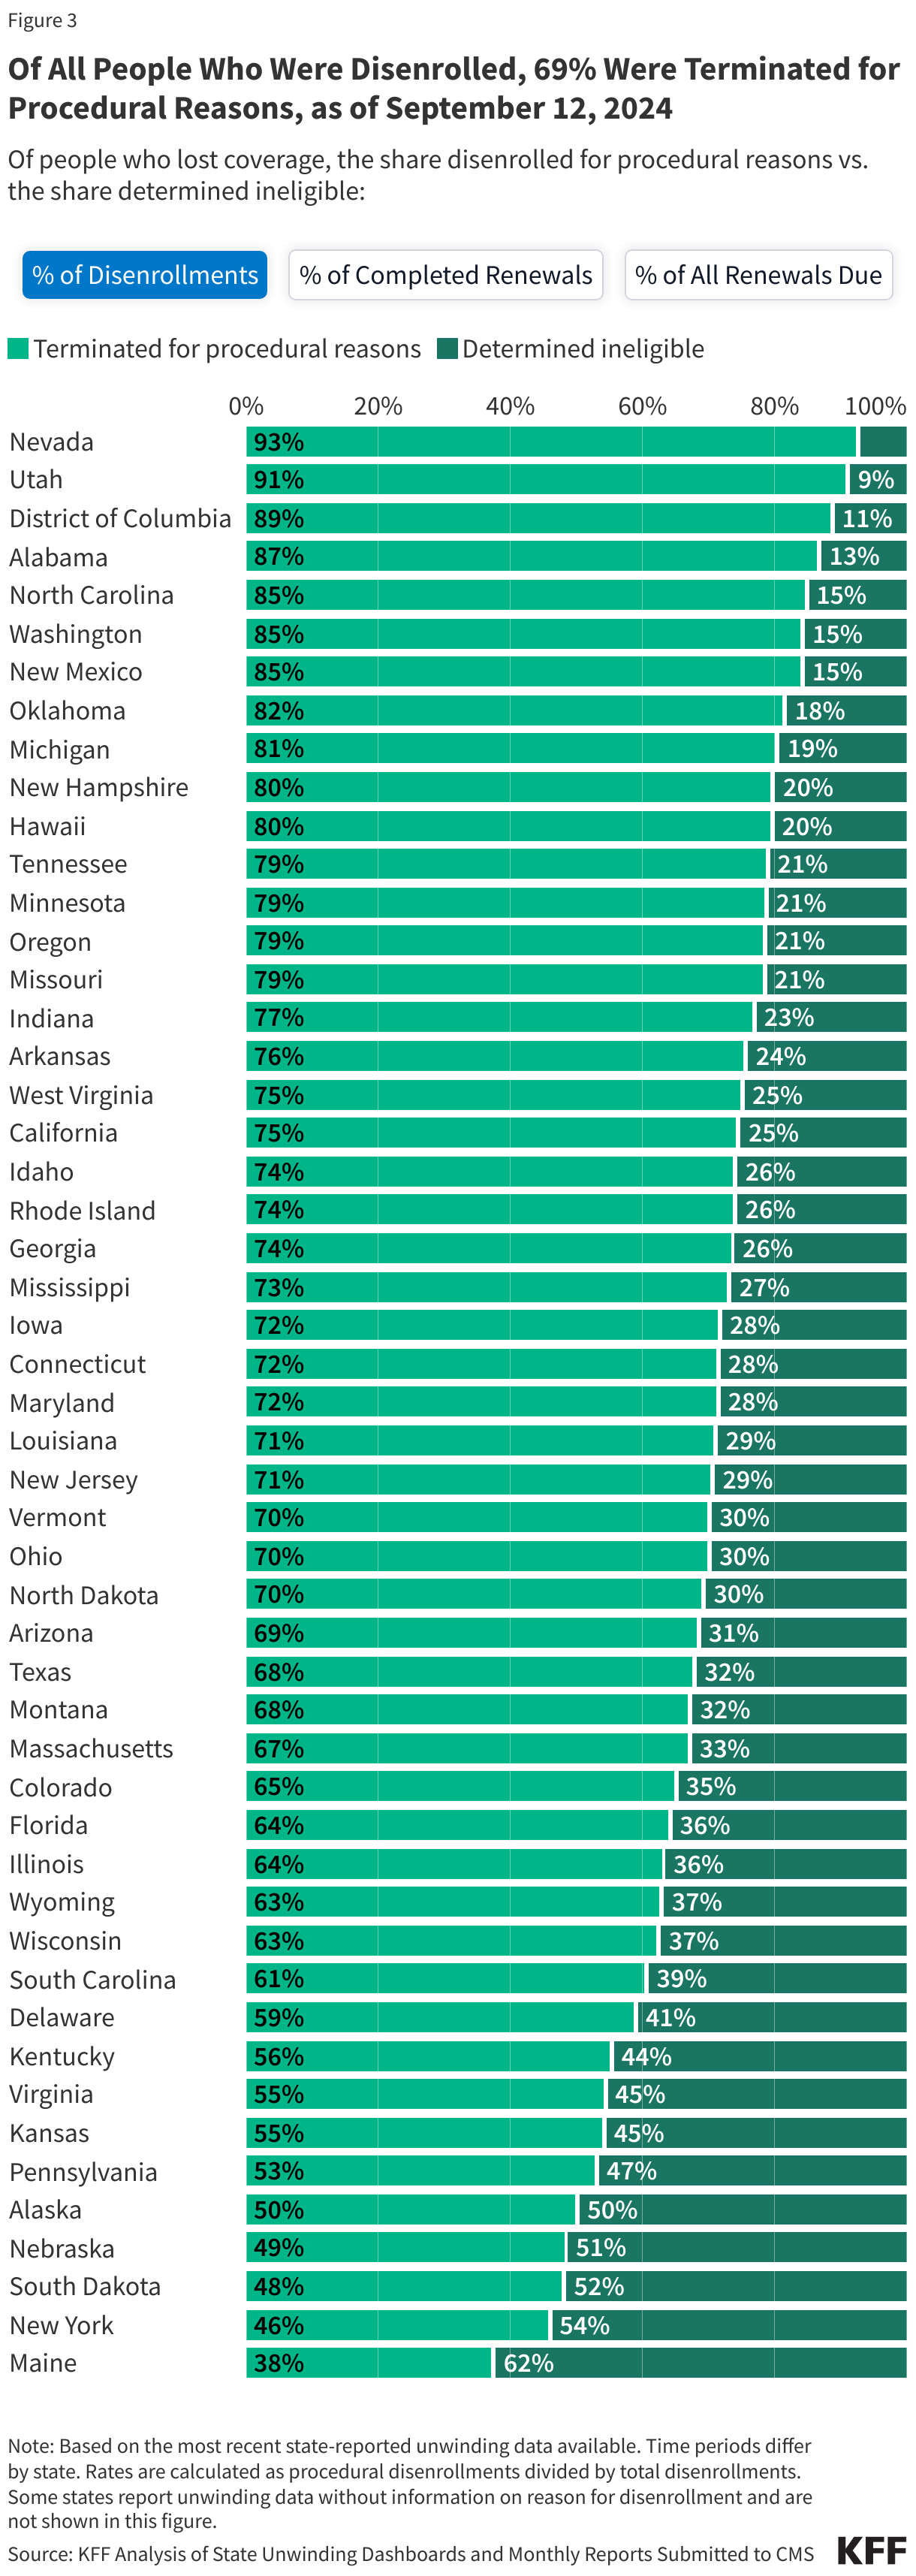
One of the most concerning findings from the data is the prevalence of "procedural disenrollments." As of September 2024, approximately 69% of all disenrollments were categorized as procedural. This means these individuals were removed from the rolls not because they were found ineligible, but because they failed to complete the renewal process—often due to missing notices, language barriers, or difficulties navigating complex state portals.
This statistic highlights a critical failure point in the social safety net: many individuals who likely remained eligible for coverage lost it simply because they could not clear the administrative hurdles presented to them during the transition.
Official Responses and Administrative Challenges
The Centers for Medicare & Medicaid Services (CMS) has maintained a rigorous reporting schedule throughout this period. However, the data underscore a persistent friction between federal reporting requirements and state-level execution.
CMS-reported data often lag by several months behind state-specific dashboards. This creates a dual-data environment where analysts must balance federal consistency with the timeliness of state-provided information. For instance, while CMS provides a national baseline, states like Kansas, Michigan, and Oregon have utilized their own dashboards that often exclude pending renewals, making it difficult to generate a perfectly unified national picture.
Moreover, several states implemented "mitigation strategies" during the unwinding, such as pausing procedural terminations or delaying system updates to ensure that eligible families were not prematurely cut off. These efforts, while well-intentioned, added layers of complexity to the national dataset, necessitating the extensive footnotes and caveats seen in current reporting.
Implications: The Road Ahead
The implications of these data for the American healthcare system are profound.
Health Equity and Access
The high rate of procedural disenrollment suggests that the burden of maintaining health coverage has shifted significantly onto the shoulders of the most vulnerable enrollees. For children and low-income families, the loss of Medicaid often results in a "coverage gap," where they remain uninsured until a health crisis forces them to re-apply. The long-term impact on public health outcomes—particularly regarding the management of chronic conditions like diabetes and hypertension—will likely be a subject of intense academic study for years to come.
The 2027 Policy Shift
Looking toward January 2027, the implementation of federal work requirements introduces a new variable into the Medicaid equation. If the past four years have taught us anything, it is that administrative complexity is the greatest enemy of consistent coverage. If the reporting requirements associated with the new work mandates are as cumbersome as the renewal forms were during the unwinding, the healthcare system may face a second wave of massive coverage churn.
Economic Considerations
From a fiscal perspective, the 2025 reconciliation law aims to curb the rapid growth of Medicaid spending. However, the trade-off is clear: as enrollment decreases, the number of uninsured individuals is expected to rise. This shift may place increased pressure on hospital systems—particularly rural facilities and safety-net providers—that rely on Medicaid reimbursements to sustain their operations.
Conclusion
The data presented here serve as a historical record of a period of immense change. As we move further into the post-unwinding era, the focus must shift from merely tracking the number of people who have left the program to understanding the lived experiences of those who were disenrolled.
The lessons of the 2023–2024 unwinding—the importance of accessible renewals, the danger of administrative barriers, and the persistent gaps in state-level data infrastructure—are essential guideposts. As policymakers prepare for the 2027 implementation of new work and reporting requirements, the goal must be to ensure that the administrative machinery of government does not inadvertently strip coverage from those who need it most.
For those navigating this complex landscape, the data remain a vital tool for advocacy and oversight. By maintaining transparency and holding systems accountable for their renewal processes, stakeholders can continue to protect the integrity of the Medicaid program, ensuring that it remains a stable, accessible, and effective safety net for millions of Americans.
About the Author