The pharmaceutical industry stands at a critical juncture, balancing the promise of life-saving innovation against the crushing weight of rising development costs and stagnant success rates. A groundbreaking new analysis from the Tufts Center for the Study of Drug Development (CSDD) and the clinical trial platform Medable has quantified a potential paradigm shift, revealing that AI-powered "clinical monitoring agents" could unlock massive financial value, offering up to an 82x return on investment (ROI) in phase 3 oncology trials.
This collaboration marks a significant departure from the speculative hype often surrounding generative AI. By anchoring their findings in the language of Expected Net Present Value (eNPV), the researchers have provided the industry with a tangible framework for evaluating the fiscal impact of agentic workflows in drug development.
The Core Findings: A New Financial Benchmark
The study focused on the implementation of Medable’s Clinical Monitoring Agent, specifically within the complex, high-stakes domain of oncology. The findings are staggering: the analysis estimates an 82x ROI for phase 3 trials and a 64x ROI for phase 2.
In monetary terms, this efficiency translates to an estimated $21 million in added financial value for a single phase 3 trial and $7.5 million for phase 2. For sponsors managing large portfolios, the implications are profound. Dr. Pamela Tenaerts, Chief Medical Officer at Medable, projects that a sponsor with 20 active oncology indications could realize an incremental portfolio eNPV of $226 million. For a larger enterprise juggling 50 indications, that number balloons to an estimated $565 million.
A Chronology of the Clinical AI Evolution
The integration of AI into clinical research has been a gradual, multi-year progression that is now hitting an inflection point.
- 2012–2024: The Data Explosion: During this period, the complexity of clinical trials skyrocketed. A Tufts CSDD/TransCelerate analysis of 105 protocols across 15 companies revealed that phase 3 protocols grew from an average of 929,000 data points in 2012 to 5.9 million by the mid-2020s. This surge created a "data-wrangling" crisis for Clinical Research Associates (CRAs).
- 2025: The Year of Efficiency: As organizations sought to manage this data deluge, AI/ML use cases began to proliferate. A 2025 Tufts CSDD analysis of 36 industry-reported use cases identified an average 18% reduction in trial cycle times, with the most significant gains occurring in patient monitoring and enrollment assessment.
- Late 2025–2026: The Rise of Agentic AI: Moving beyond simple predictive analytics, the industry shifted toward "agents"—software that can execute multi-step workflows with limited human intervention. This period was marked by massive enterprise investment, with 93% of organizations surveyed by McKinsey reporting that they had exceeded their AI budgets in a bid to harness these tools.
- Mid-2026: The Quantified Breakthrough: The current Tufts-Medable study represents the first rigorous attempt to move beyond pilot projects and provide hard, audited numbers on the financial viability of agentic clinical monitoring.
The Mechanics: How Agents Tame Complexity
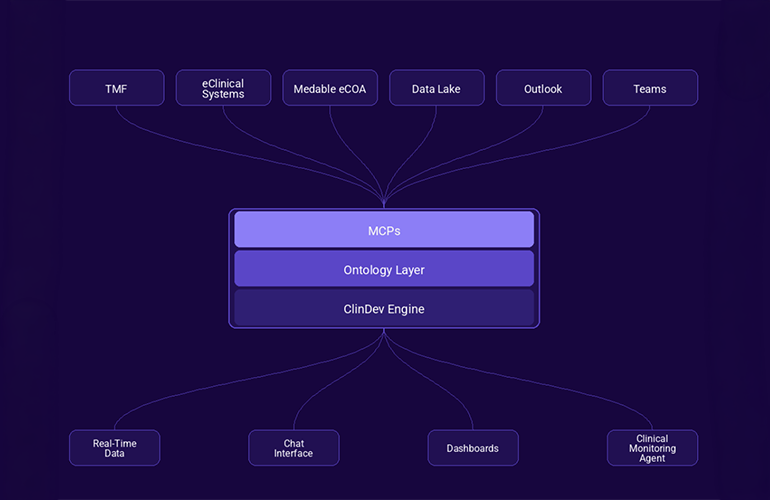
To achieve these returns, Medable utilizes a prebuilt architecture designed for rapid deployment. Rather than building from scratch, sponsors implement pre-configured monitoring and Trial Master File (TMF) agents that utilize roughly 40 standardized connectors. These integrations link to critical systems including EDC (Medidata Rave, Oracle InForm, Veeva), CTMS, safety reporting databases like Oracle Argus, and data warehouses such as Snowflake and Databricks.
"A lot of those agents still need about 20% tweaking, because systems are different and it has to be configured," explains Dr. Tenaerts.
In practice, the agent acts as a force multiplier for the CRA. In a live demonstration, the agent analyzed data from multiple, disparate clinical systems to identify a site with inconsistent adverse-event reporting. It not only flagged the discrepancy but also drafted the necessary queries for the Electronic Data Capture (EDC) system and prepared correspondence for the site. This allows the human operator to move from "data janitor"—manually searching for patterns—to "clinical strategist," focusing on high-level protocol adherence and safety.
Expert Perspectives: Bridging the Gap Between Hype and Reality
Ken Getz, executive director of the Tufts CSDD, emphasizes that the primary goal of the study was to provide the "language of investment" that has been absent in the AI discourse.
"We’ve known for some time that companies have been piloting AI enablement tools, but what they’ve often been lacking is any kind of quantification of the actual ROI," Getz noted. By defining these gains, the study provides a roadmap for executives who need to justify the capital expenditure required to transition from manual, legacy processes to AI-augmented workflows.

However, industry leaders are careful to distinguish between "assistant" AI and the "fully autonomous" agents popularized by science fiction. Venu Mallarapu, Chief Transformation and AI Officer at eClinical Solutions, notes that while the industry is making strides, the "human-in-the-loop" model remains the standard for risk management.
"There’s nobody that is running fully autonomous agents that not only process the data but also make decisions without human involvement," Mallarapu stated. "At least I haven’t seen that within our customer base."
Implications for Drug Development and Patient Safety
The most significant impact of this technology may be its ability to address the "failure rate" that has plagued oncology drug development for decades. With small-molecule cancer drugs facing a 95% failure rate from phase 1 through phase 3, any tool that can provide earlier insights is invaluable.
The agentic model offers a unique advantage: speed of detection. By identifying trends in adverse events or protocol deviations faster than a human team could process the raw data, agents provide a window of opportunity to intervene. This could mean adjusting a dosing schedule, correcting a site error before it compromises a patient, or identifying a design flaw that would otherwise derail a trial months later.
Solving the "Balloon" Effect
One of the most profound insights from the study is the warning regarding system-wide bottlenecks. Dr. Tenaerts pointedly highlights that increasing the speed of monitoring isn’t a silver bullet. If an AI agent generates 100 queries for a clinical site in an hour, but the site staff lacks the capacity to process them, the problem has simply been moved from one part of the pipeline to another.

"You push the balloon and it goes somewhere else," Tenaerts observed. "You need to figure out the whole system." This suggests that the next phase of clinical AI evolution will involve not just monitoring agents, but "site-side" agents that help investigators manage the influx of data, creating a truly connected, automated ecosystem.
Future Outlook: Beyond Oncology
While the current analysis is restricted to oncology, the scalability of the model is clear. The complexity of oncology trials—which often serve as the "stress test" for clinical research—makes them the ideal testing ground for agentic AI. As the technology matures, it is expected to migrate into immunology, rare disease research, and other therapeutic areas where complex, multi-site data management is required.
Ultimately, the Tufts and Medable analysis confirms what many have suspected: AI agents are not just a productivity play; they are a fundamental shift in how the industry manages capital, time, and patient safety. By turning millions of disparate data points into actionable, high-ROI insights, these agents are moving the industry closer to a future where trials are faster, cheaper, and, most importantly, more reliable.
As Ken Getz concluded, the power of these tools lies in their ability to free human professionals to focus on the truly difficult, high-stakes decisions—the very decisions that determine whether a drug succeeds or fails in its journey to the patient.
About the Author